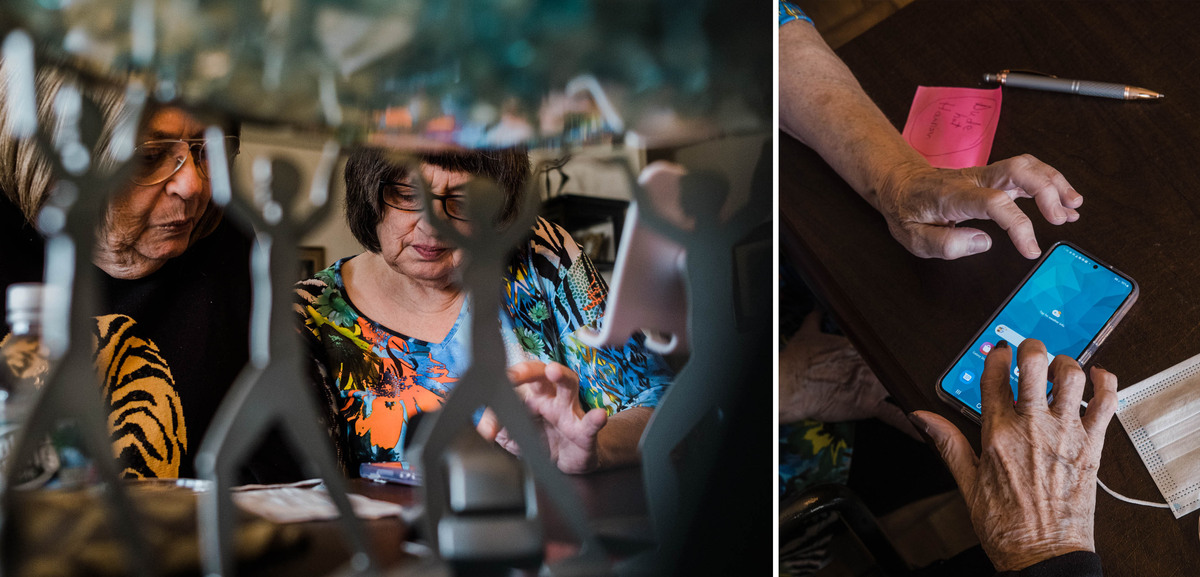Bernie Sanders chairs Senate committee looking to fix the health worker shortage : Shots

Bernie Sanders chairs Senate committee looking to fix the health worker shortage : Shots

Sen. Bernie Sanders, I-Vt., is chairing the Senate’s top health committee which is focused on solving the U.S. health care worker shortage.

J. Scott Applewhite/AP


hide caption

toggle caption

J. Scott Applewhite/AP


Sen. Bernie Sanders, I-Vt., is chairing the Senate’s top health committee which is focused on solving the U.S. health care worker shortage.

J. Scott Applewhite/AP

Senators are eying the growing shortage of health care workers in the United States as one of the few problems where there is room for bipartisan solutions, even in a deeply divided Congress gearing up for a presidential election cycle.

The shortage that’s only worsened since the pandemic is a prescription for skyrocketing costs, suffering, and unnecessary death, warned Sen. Bernie Sanders, I-Vt., who is the new chairman of the Senate’s top health committee. He spoke in his committee’s first hearing last week.

“We are going to produce legislation, and I think people will be surprised about the level of bipartisan supporters,” Sanders said in a brief interview during a break from the hearing. He called for the committee to “produce something meaningful.”

The shortage of health care workers of all sorts is a widespread problem, but is especially acute in rural areas and minority communities. Sanders pointed to the startling numbers of Americans living in medical care deserts to illustrate the point. There are nearly 100 million people who don’t have easy access to a primary care physician, almost 70 million with no dentist at hand, and some 158 million people who have few local mental health providers, Sanders said.

The COVID pandemic contributed to the nation’s existing worker shortage as many left the workforce as the crisis worsened. Some contracted the virus themselves, and large numbers of health care providers died. An investigation by KHN and The Guardian revealed more than 3,600 health workers in the United States died during the pandemic’s first year alone. Many others got burnt out or sought higher-paying jobs elsewhere.

“Despite all of our health care spending, we don’t have enough doctors, nurses, nurse practitioners, dentists, dental hygienists, pharmacists, mental health providers, and other medical professionals,” Sanders said, pointing to data that suggest the nation faces a shortfall of about 450,000 nurses and 120,000 doctors in the coming years, and 100,000 dentists now.

While Democrats and Republicans alike acknowledged the shortages hobbling care for hundreds of millions of Americans, any legislative solution must pass not only the Senate Health, Education, Labor and Pensions Committee, but also the full Senate and House of Representatives.

Far-right House Republicans have threatened to go so far as forcing the federal government to default on its debts as they demand spending cuts, and high government spending on health care could make new legislation a ripe target.

Sen. Bill Cassidy of Louisiana, the committee’s top Republican who is also a doctor, cited a few programs the committee is responsible for updating this year, such as an expiring program that trains many of the nation’s pediatricians. He said funding should reflect what works in the health care system and come “with the appropriate spending offsets.”

“We have to make sure that we’re not wasting the money we’re trying to productively spend,” he said.

None of the senators in the hearing disagreed with the fundamental problem that too many medical professionals are leaving their fields and that educational institutions are not graduating enough new ones to replace them and meet the growing needs of an aging population.

Members on both sides of the aisle recognized growing levels of burnout in the medical professions; increased threats faced by health care workers; the costs and challenges of working underserved areas; and financial incentives that steer younger professionals toward more lucrative specialties and higher-income areas.

Senators agreed on some strategies to boost numbers of health workers, such as encouraging more lower-cost educational options like community college and ensuring that existing programs are extended this year, such as the National Health Service Corps that trains doctors for underserved areas and graduate education programs.

A whiff of partisan thinking drifted into the conversation, with some Republicans focused more on decrying government interference in health care. Sen. Mitt Romney, R-Utah, suggested the State Department should do a better job clearing foreign students and practitioners to immigrate here. Cassidy raised electronic health records requirements as a contributor to physician burnout, saying they consume too much time.

Even in those areas, there were signs lawmakers could agree. Sen. Tim Kaine, D-Va., also raised the idea of unjamming the immigrant backlog.

Sen. Rand Paul, R-Ky., said vaccine requirements were an impediment. Sen. Roger Marshall, R-Kan., raised regulations barring some surprise medical bills as harmful to doctors.

“I think the fact that the committee has made this the first hearing means a number of us have bills. We may try to take a bunch of them up together and see if we can combine them into something,” said Kaine, pointing in particular to the idea of expanding loan forgiveness for people willing to go into areas with shortages. “I think there’s great prospects for bipartisan progress on this.”

Some of the senators credited Sanders with the initial progress toward a compromise. He spent his first weeks in his post meeting with committee members from both parties to identify areas of bipartisan agreement.

Sen. Lisa Murkowski, R-Alaska, said Sanders reached out to meet with her and discuss her priorities. They both named workforce shortages as a top issue, she said, adding, “We’ve got good stuff to work on.”

“In my conversation with him just on the floor this week, about what we might be able to do with the workforce issue, I think he was kind of probing to see if we could put together some efforts to just focus on these workforce shortages,” Murkowski told KHN. “There is a great deal of interest in legislating in this space.”

“What it’s going to look like, I can’t tell you yet,” she added.

“We are going to produce legislation,” Sanders said as the hearing ended. “I don’t do hearings for the sake of hearings.”

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

How the Medicare political wars could hurt seniors : Shots

How the Medicare political wars could hurt seniors : Shots

Previous 7 days in Florida, at the University of Tampa, President Joe Biden promised to guard and reinforce Social Security and Medicare, as effectively as reduce overall health care prices.

Mandel Ngan/AFP through Getty Images


conceal caption

toggle caption

Mandel Ngan/AFP by means of Getty Visuals


Past 7 days in Florida, at the College of Tampa, President Joe Biden promised to safeguard and strengthen Social Stability and Medicare, as properly as reduce wellness treatment expenditures.

Mandel Ngan/AFP through Getty Photos

The Medicare wars are again, and practically no a person in Washington is stunned.

This time it truly is Democrats accusing Republicans of seeking to maim the pretty well-liked federal well being plan that covers 64 million seniors and persons with disabilities. In the previous, Republicans have efficiently pinned Democrats as the risk to Medicare.

Why do politicians persistently wield Medicare, as well as Social Security, as weapons? Due to the fact heritage displays that performs at the ballot box. Generally, the celebration accused of menacing the sacrosanct entitlements pays a rate — although it’s the thousands and thousands of beneficiaries relying on feuding lawmakers to keep the systems funded who stand to drop the most.

Republicans have repeatedly warned they would maintain boosting the federal debt ceiling hostage until Democrats negotiated changes to Medicare, Medicaid, and Social Protection. The 3 systems jointly, along with funding for the Inexpensive Care Act and Kid’s Health Insurance policy Method, account for almost 50 {bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the federal spending plan.

The political bomb that went off all through President Joe Biden’s Point out of the Union speech had been ticking for months. In his speech, Biden threatened to veto any Republican efforts to cut Social Security or Medicare. It was one particular of only 3 veto threats he designed that night time. For the duration of a journey to Florida just after the speech, he stated it more forcefully: “I know a large amount of Republicans, their dream is to lower Social Safety and Medicare. Properly, let me say this: If which is your aspiration, I am your nightmare.”

Senior Republicans have distanced them selves from the proposals Biden was referencing, notably ideas from the Home Republican Research Committee and Sen. Rick Scott, R-Fla., to make cuts or even permit Medicare expire unless Congress votes to preserve it going.

“That’s not the Republican program which is the Rick Scott strategy,” Senate Minority Leader Mitch McConnell stated on a Kentucky radio demonstrate Feb. 9, echoing his opposition to the program last yr.

“Cuts to Social Safety and Medicare are off the table,” Residence Speaker Kevin McCarthy declared the day prior to Biden’s veto danger.

McConnell and McCarthy know a thing that Rick Scott seemingly does not: Politicians threaten large, well-known entitlement packages at their peril. And, typically, it’s been Republicans who put up with the electoral outcomes.

How Medicare fights have shaped elections

This dates at the very least to 1982, when Democrats used threats of Republican cuts to Social Security to select up additional than two dozen Residence seats in President Ronald Reagan’s initial midterm elections. In 1996, President Invoice Clinton won reelection in section by convincing voters that Republicans led by House Speaker Newt Gingrich required to privatize Medicare and Social Protection.

At the commencing of his next term, in 2005, President George W. Bush designed it his best priority to “partly privatize” Social Safety. That proved singularly unpopular. In the following midterm elections, Democrats won again the Dwelling for the to start with time given that getting rid of it in 1994.

In 2010, Republicans turned the tables, employing what they explained as “Medicare cuts” in the Cost-effective Care Act to sweep again to electrical power in the House. (These “cuts” have been typically reductions in payments to companies beneficiaries essentially obtained more advantages by the ACA.)

The use of the Medicare cudgel possible reached its zenith in 2012, when Democrats took intention at Medicare privatization proposals presented by Paul Ryan, the Home Price range Committee chair and Republican vice presidential applicant. That discussion developed a controversial political ad, paid for by the progressive Agenda Project Action Fund and recalled by many in Washington, that showed a suited male in a purple tie – presumably, Ryan – dumping a wheelchair-bound “granny” off a cliff as the terms flashed, “Is The us Stunning without the need of Medicare?”

The actuality is that Medicare’s price as a political weapon also sabotages any hard work to occur alongside one another in a bipartisan way to resolve the program’s financing troubles. The last two instances the Medicare Clinic Insurance policy Have faith in Fund was this close to insolvency — in the early 1980s and late 1990s — Congress passed bipartisan costs to keep the application afloat.

A person person’s ‘cut’ can be another’s ‘benefit’

Even the phrase “slash” can be political. A person stakeholder’s Medicare “lower” is another’s gain. Decreasing payments to health-related companies (or, additional normally, cutting down the size of payment boosts to doctors and hospitals) could decrease premiums for beneficiaries, whose payments are primarily based on full prices of the Medicare software.. Meanwhile, increasing premiums or cost sharing for beneficiaries is a reward to all taxpayers, who enable fund Medicare. Increasing offered rewards allows physicians, hospitals and other health and fitness companies, as perfectly as beneficiaries, but prices a lot more for taxpayers. And on, and on.

There are essential variances involving the events that cannot be papered more than. Lots of Republicans want Medicare to shift from a “described profit” plan — in which beneficiaries are guaranteed a particular set of solutions and the authorities pays whatsoever they value — to a “described contribution” system, in which beneficiaries would get a certain amount of money of income to finance as much as they can — and would be on the hook for the rest of their health care expenses.

This would change the risk of overall health inflation from the government to seniors. And even though it plainly would advantage the taxpayer, it would disadvantage equally companies and the persons on Medicare.

But there are quite a few, quite a few intermediate steps Congress could acquire to at least delay insolvency for both equally Medicare and Social Protection. Some are more controversial than others (elevating the payroll tax that funds Medicare, for instance), but none are further than the measures preceding Congresses have taken each and every time the packages have neared insolvency.

Republicans are right about this: Medicare and Social Security are unable to be “set” until equally sides lay down their weapons and start conversing. But each time a politician unsheathes their speaking details about “Medicare cuts,” that truce looks considerably less and a lot less achievable.

Johns Hopkins University to shut down its COVID tracker : Shots

Johns Hopkins University to shut down its COVID tracker : Shots

The COVID-19 dashboard produced by the Johns Hopkins Centre for Devices Science and Engineering is shown all through a briefing on Capitol Hill in early March 2020, when only 245 confirmed scenarios experienced been claimed in the U.S.

Samuel Corum/Getty Illustrations or photos


conceal caption

toggle caption

Samuel Corum/Getty Photos


The COVID-19 dashboard produced by the Johns Hopkins Centre for Devices Science and Engineering is exhibited during a briefing on Capitol Hill in early March 2020, when only 245 confirmed scenarios experienced been documented in the U.S.

Samuel Corum/Getty Pictures

In one more indicator of the altering state of the pandemic, an priceless resource of information and facts about the virus more than the last a few many years is shutting down, NPR has acquired.

The Johns Hopkins Coronavirus Source Middle options to cease operations March 10, officers advised NPR.

“It can be bittersweet,” suggests Lauren Gardner, an engineering professor who released the project with 1 of her students on March 3, 2020. “But it is really an suitable time to shift on.”

When the pandemic erupted, no just one knew considerably of anything at all about the virus and how to react. Was it safe to go grocery browsing? How quickly could a person get contaminated on a bus or teach? Could runners get sick just by passing a further jogger in the park?

“As anyone can bear in mind, there was extremely small info, particularly at the beginning of the pandemic,” suggests Beth Blauer, an affiliate vice provost at Johns Hopkins who has served operate the heart.

“And when we started out to see the scenarios go out of China and in by way of Europe and headed towards our shores, we knew that there were heading to be a collection of general public coverage conclusions that would have to be made,” Blauer suggests.

People selections included the place to impose remarkable but very important public wellness steps. Ought to mayors close faculties? Really should governors mandate masks? Should really CEOs shut down factories? Ought to heads of point out seal borders?

But there was no great details out there to make individuals choices. Neither the Centers for Disorder Manage and Avoidance nor the Globe Well being Business had been giving enough helpful numbers in serious time. So journalists and tutorial researchers at locations like Johns Hopkins jumped in to fill the void.

NPR launched its personal tracker on March 16, 2020, drawing facts from Johns Hopkins. It was seen about 52 million situations more than the final three decades as visitors sought to stay current on COVID metrics. On Feb. 1, NPR ceased updating the website page, recognizing that Individuals can obtain the data they need on the CDC’s COVID internet site. This was not the scenario early in the pandemic.

“I know CDC has the potential to do this and has done it quite a few instances in the earlier,” suggests Dr. Ali Khan, a former CDC official who is now dean of the Higher education of Community Wellness at the University of Nebraska Healthcare Middle. “So it was unconventional that at the commencing of this COVID pandemic that they did not gather this details and place it out in a well timed quite a few. Very unconventional and really stunning.”

Johns Hopkins “in essence filled the vacuum,” Khan claims, “That was invaluable to recognize what was heading on.”

Soon after Johns Hopkins launched the challenge, the web-site rapidly turned crucial for determining almost everything from in which drug providers should test vaccines to in which Hollywood need to film flicks. Even the White Home and the British key minister ended up relying on Hopkins data.

Gardner recollects a lot of conversations “with people today that were just out about executing their task — touring in Japan, listed here and there — who would tell me the dashboard was the driving power in determination-generating for them … about quitting their task and then coming household so that they wouldn’t get caught.”

The site’s maps of the globe and particular person nations became an iconic way of tracking the virus’s inexorable distribute.

“I would refresh my computer screen over and about again over the training course of the get the job done working day seeking to see what the latest numbers ended up,” suggests Dr. Celine Gounder from the Kaiser Household Basis, who was performing as an infectious illness professional at the Bellevue Hospital in New York when the pandemic commenced.

“It was definitely startling to see even above the training course of the day how the quantities had been evolving. I consider my colleagues imagined I was a very little obsessive,” Gounder suggests. “But it was also viewing history unfold in real time on your display screen.”

The web page, which Blauer and Gardner notice was developed and run largely by females, value $13 million and at some point drew extra than 2.5 billion views, Blauer claims.

“It is a staggering total of visitors,” she states. “These are figures I do not think I’ll at any time see yet again in my specialist occupation.”

But now that the threat of the pandemic is receding, states are reporting info less usually and the CDC has ramped up the agency’s data reporting, the college determined it was time to shut it down.

“There is certainly surely a bitter sweetness about the conclusion,” Blauer says. “But we are at an inflection place.”

Equally Blauer and Gardner say they hope the CDC and the general public health and fitness method will carry on to commit in facts collection so the country will be greater organized in the long term. But they are well prepared to step back in if vital.

“There will be yet another pandemic,” Gardner states. “And, so we are going to have to see.”

Long COVID diagnosis puts extra strain on family caregivers : Shots

Long COVID diagnosis puts extra strain on family caregivers : Shots

Louise Salant (right), 72, and her aunt Eileen Salant (center), 86, both got very sick with COVID-19 in 2020. And as Eileen developed long COVID symptoms, so too did Louise, who struggled with fatigue and shortness of breath while also managing her aunt’s care. Nearly three years later, home health aides like Elfnesh Legesse (left) help Louise take care of her aunt.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Louise Salant (right), 72, and her aunt Eileen Salant (center), 86, both got very sick with COVID-19 in 2020. And as Eileen developed long COVID symptoms, so too did Louise, who struggled with fatigue and shortness of breath while also managing her aunt’s care. Nearly three years later, home health aides like Elfnesh Legesse (left) help Louise take care of her aunt.

Gabriela Bhaskar for NPR

For Louise Salant, long COVID has meant new stress, new responsibilities, and multiple medical crises to manage. It’s transformed her life.

But there’s a twist. She’s had to deal with this condition not just as a patient but also as a caregiver for her 86-year-old aunt Eileen Salant, who has coped with long COVID’s disabling symptoms for almost three years.

Eileen and Louise both caught an acute bout of COVID-19 in March of 2020. Eileen had been taking care of her brother, who was admitted to a New York City hospital with heart failure during those dark days of the early pandemic. He got COVID there, and died from his infection with the virus. Both aunt and niece also became very ill.

It was early days of the pandemic in New York, and hospitals were so crowded that Louise was told to stay home and fight out the illness on her own. Meanwhile, Eileen was hospitalized and stayed there all spring, including two months on a ventilator. After that, she spent five months at a rehab hospital. She finally came home to her apartment in Riverdale, the Bronx, the day before Thanksgiving in 2020 — but she was very weak.

Eileen and Louise both got COVID-19 in the early days of the pandemic in New York. Eileen ended up on a ventilator for two months and then spent five months in a rehab hospital. Louise fought the illness at home as hospitals started filling up.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Eileen and Louise both got COVID-19 in the early days of the pandemic in New York. Eileen ended up on a ventilator for two months and then spent five months in a rehab hospital. Louise fought the illness at home as hospitals started filling up.

Gabriela Bhaskar for NPR

“She could barely sit up in bed, couldn’t hold a fork,” says Louise, who lives a 10-minute taxi ride away.

Over the years, Louise, now 72, has worked at various times as an art therapist, taught piano to children and adults and done medical interviewing for a cancer research team. But when COVID hit, all that ground to a halt. Though she hadn’t always been emotionally close to her aunt, she says, she took on the caregiving role, “because someone needed to” — even as she, too, dealt with her own symptoms of long COVID, including crushing fatigue and shortness of breath.

An overwhelming need

Louise Salant set about organizing home aides, occupational therapy and physical therapy for her aunt and oversaw all other aspects of the older woman’s care. She had to learn to deliver injections of blood thinning medicine, then trained the aides to do it too. For months, she kept track of Eileen’s expenses, maintained all her medical information and patient history, and ran all her errands.

She found that being a caregiver for someone with long COVID, as for other serious and chronic medical conditions, is not just being an aide. It’s running the patient’s life. “Every single day, there’s something she’d need,” Louise says. “I was dealing with the pharmacy, dealing with the doctor, keeping her schedule. And when I’m not there, I’d worry. I have to always be available on the phone.”

Louise began managing all aspects of her aunt’s life while dealing with her own debilitating fatigue. She hired and trained home health aides, made doctor’s appointments for Eileen, and picked up prescriptions from the pharmacy.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Louise began managing all aspects of her aunt’s life while dealing with her own debilitating fatigue. She hired and trained home health aides, made doctor’s appointments for Eileen, and picked up prescriptions from the pharmacy.

Gabriela Bhaskar for NPR

Eileen recently got a new phone; Louise showed her how to use it.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Eileen recently got a new phone; Louise showed her how to use it.

Gabriela Bhaskar for NPR

Between 8 and 23 million Americans are thought to have long COVID — meaning they have long-lasting symptoms that endure or arise months after infection, such as difficulty concentrating (“brain fog”), extreme tiredness, anxiety and shortness of breath. But there is no solid estimate of how many need caregiving help. Stats from one clinic hint at the size of the problem: Out of the 1,782 patients seen at the Penn Medicine Post-COVID Assessment and Recovery Clinic between June 2020 and January 2023, about one-fifth said they felt uncomfortable dealing with daily activities like driving, shopping, or using public transit, suggesting the need for a caregiver.

And, like roughly 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of U.S. caregivers, Louise had her own chronic health problems to manage. It was the exhaustion of long COVID that almost took her under, especially in the first months of caregiving. After three or so hours of helping her aunt, she says, “this sickening feeling would come over my whole body, and I’d have to go home. I’d be in bed sick for two or three days.” In August 2021, Louise got a new inhaler from her lung doctor that helped her breathe better and started to give her more energy.

Why caregiving is harder when the medical condition is new and poorly understood

Stories like the Salants’ reveal another unfortunate reality about dealing with a complex chronic disease like long COVID, in contrast to an illness with a more straightforward diagnosis: Meeting the demands of the health care system itself can be a major burden. Because the medical condition is new and poorly understood, patients often consult multiple specialists who order a long sequence of tests to rule out other illnesses. Caregivers must schedule each of those visits, often go with the patient to the test, and often need to follow up with multiple physicians about the results.

Louise sorts through Eileen’s medications. “She’s been wonderful to me,” Eileen says of Louise. “Like a daughter would help her mother.”

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR

With unpredictable symptoms that can wax and wane mysteriously, long COVID also requires exceptionally good record-keeping, in order to provide doctors with new clues. But because the disease often causes fatigue and brain fog, some patients can’t keep track for themselves. They rely on friends or family for help.

“The family caregiver becomes the care manager, advocating and managing the system,” the late John Schall, former CEO of the Caregiver Action Network, an education and advocacy nonprofit, told us last year. “And you’re doing it by guesswork. Nobody tells you what to look for.”

In interviews with a half-dozen family caregivers of people with long COVID, the complexity of managing care emerged again and again. Judith Friedman, a Brooklyn mom who is helping her adult daughter who has long COVID, maintains a list of 14 doctors she consults regularly or periodically and another list that includes 10 daily prescription drugs, plus supplements and other as-needed medications her daughter takes.

Slowly, over time, Eileen began regaining her strength. By March 2022, she was able to venture out with Louise, for adventures beyond the neighborhood.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Slowly, over time, Eileen began regaining her strength. By March 2022, she was able to venture out with Louise, for adventures beyond the neighborhood.

Gabriela Bhaskar for NPR

The task can be overwhelming even for experts. Tonya LaGrange has helped her husband Brent LaGrange since 2020 through a huge range of problems stemming from long COVID, including heart arrhythmias, joint pain, neurological problems and difficulty breathing. During doctors’ appointments, she is his advocate and backstop, making sure nothing gets forgotten and details don’t get lost. “It’s probably why he’s still alive now,” LaGrange says. “I’ve been able to intervene when he slips through the cracks.”

In 2020, at the peak of her husband’s illness, she was always doing something for his care, she says, whether it was emailing case managers during the day, or monitoring his breathing at night to wake him up when he would especially struggle. It’s not quite as intense now as it once was, she says, but she is still always “on” — juggling phone calls, appointments and follow-ups in between the demands of her job as the director of rehabilitation at a skilled nursing facility.

Even though LaGrange works in health care herself (including training as a physical therapist), and all her husband’s doctors are in one health system she finds care management a challenge. “I know how the field works, I know the system, I know the terminology, and we’re having trouble,” she says. “What about people who don’t have the education I have? It’s devastating.”

Caregivers need support, too

Louise says her own long COVID symptoms have finally mostly eased. She says she took on the caregiving role for her aunt when COVID-19 hit them both, “because someone needed to.”

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Louise says her own long COVID symptoms have finally mostly eased. She says she took on the caregiving role for her aunt when COVID-19 hit them both, “because someone needed to.”

Gabriela Bhaskar for NPR

About half of all family caregivers say they take the lead in coordinating their ill loved one’s care, according to surveys from AARP. And while hands-on caregiving can be emotionally rewarding, dealing with forms, bills and scheduling generally isn’t, says Jennifer Olsen, CEO of the Rosalynn Carter Institute for Caregivers. “It’s challenging to spend half your day on the phone with insurance to make sure you have the right justification for the right test,” she says. “Caregiving project management is something we don’t talk about.”

These responsibilities add to the strain of worrying about a loved one’s health and keeping the household running too. It can be intense, says Sheria Robinson-Lane, assistant professor at the University of Michigan School of Nursing, who studies caregiving. “One family member might have taken care of paying the bills, and now this person has to learn all those tasks, which wasn’t part of the division of labor,” she adds. “That causes stress.”

Louise rests on the couch while visiting Eileen at her apartment in the Bronx. Naps were a regular part of each caregiving day a couple of years ago, when Louise could only function about three hours a day, she says. A new inhaler she was prescribed in August 2021 helped her breathe better, and gave her more energy.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Louise rests on the couch while visiting Eileen at her apartment in the Bronx. Naps were a regular part of each caregiving day a couple of years ago, when Louise could only function about three hours a day, she says. A new inhaler she was prescribed in August 2021 helped her breathe better, and gave her more energy.

Gabriela Bhaskar for NPR

Robinson-Lane recommends that caregivers move quickly to reinforce their own emotional support systems, whether that’s friends, family or, ideally, a professional counselor. Local senior centers can often help people who aren’t necessarily elderly, she adds: Advice and connections may be available for those over 55, or for disabled people of any age. Simply talking to your insurance provider can also point the way to assistance: “In my experience they’re incredibly helpful once you get someone on the phone,” says Robinson-Lane.

The next chapter of care

By the late winter of 2021, months after she first came home from the rehab hospital, Eileen Salant started feeling stronger, and by April of that year she was able to venture out to the kosher deli in her neighborhood. By March of 2022, with the help of her niece Louise, the two took longer adventures — taxi trips to Nordstrom and Saks Fifth Avenue in Manhattan. “I was just determined to get out,” Eileen says.

Later that month, she had a major setback, and was hospitalized again for a week. But thanks to Louise’s help, and the support of paid caregivers at home, Eileen eventually bounced back.

Louise says that despite the difficult circumstances, she and her aunt have become closer these past few years.

Gabriela Bhaskar for NPR


hide caption

toggle caption

Gabriela Bhaskar for NPR


Louise says that despite the difficult circumstances, she and her aunt have become closer these past few years.

Gabriela Bhaskar for NPR

“She’s been wonderful to me,” Eileen says of Louise. “Like a daughter would help her mother.” Despite the difficulty of the last few years, the two are closer now, Louise says, and have come to respect and love each other.

Louise has advice for other long-COVID caregivers: Find a doctor who is knowledgeable about the disease, or at least willing to learn more about it. She also recommends the online patient-support group Survivor Corps. “The best resource is other people,” Louise says.

Other family caregivers praise the Body Politic COVID-19 support group. And LaGrange recommends simply finding someone to talk to who is not part of the family — perhaps a friend or a therapist.

Although specific treatments for long COVID are elusive so far, many people do eventually recover on their own. The biggest study so far found that long COVID symptoms endured an average of 9 months for people who’d been hospitalized with COVID-19, and 4 months for those who hadn’t needed hospitalization .

Louise also reports that her long-COVID symptoms have finally eased, and she, too, is feeling better. The overwhelming fatigue seems to be gone, although she’s still tired, and she even started teaching piano again for one nearby family.

She’s been able to step back a little bit from her daily responsibilities in caring for her aunt, although she knows that could change at any moment. She still sleeps with her phone by her bed, she says — but now at least she sleeps through the night.

Kat McGowan is a freelance writer in California focused on caregiving. This story was produced with support from the Alicia Patterson Foundation.

U.S. winter COVID surge is mild and fading fast : Shots

U.S. winter COVID surge is mild and fading fast : Shots

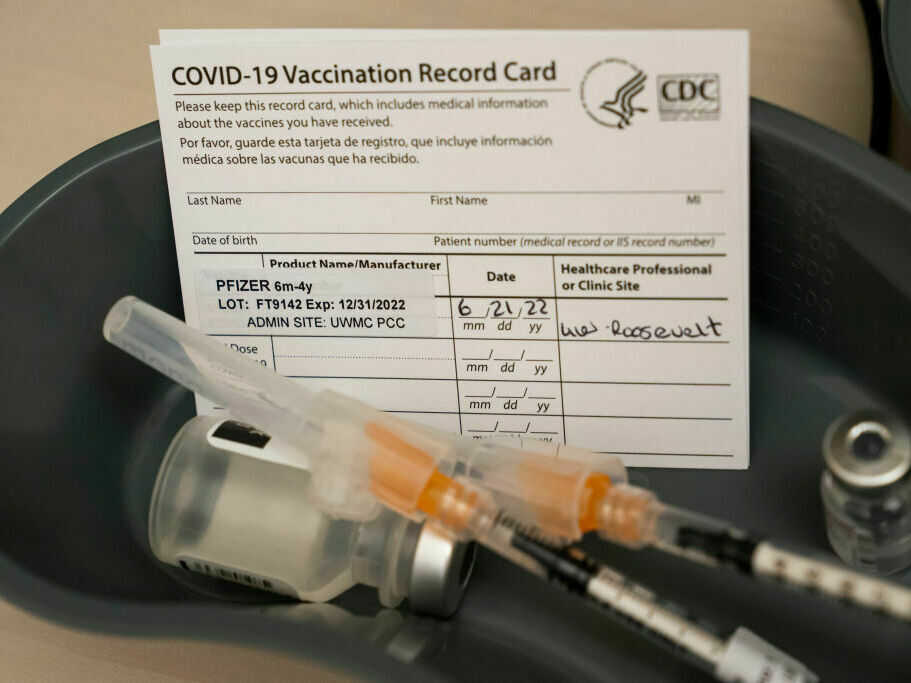
Immunity Individuals acquired by means of vaccination or by way of prior an infection with the SARS-CoV-2 virus may account for the lighter than anticipated COVID surge in the U.S. this winter, scientists say.

David Ryder/Getty Photos


conceal caption

toggle caption

David Ryder/Getty Pictures


Immunity People obtained through vaccination or by way of prior an infection with the SARS-CoV-2 virus might account for the lighter than anticipated COVID surge in the U.S. this winter, researchers say.

David Ryder/Getty Visuals

This winter’s COVID-19 surge in the U.S. appears to be fading without hitting almost as challenging as several experienced feared.

“I believe the worst of the wintertime resurgence is about,” says Dr. David Rubin, who’s been tracking the pandemic at the PolicyLab at Kid’s Medical center of Philadelphia.

No one predicted this winter’s surge to be as undesirable as the past two. But each the flu and RSV arrived roaring back again seriously early this slide. At the similar time, the most contagious omicron subvariant still took off just as the holiday seasons arrived in late 2022. And most persons were acting like the pandemic was around, which allowed all a few viruses to unfold promptly.

So there have been huge fears of hospitals getting completely confused once again, with many people today acquiring seriously unwell and dying.

But that is not what occurred.

“This virus continues to throw 210-mile-for each-hour curve balls at us. And it appears to defy gravity or logic at times,” suggests Michael Osterholm, who heads the Center for Infectious Condition Research and Policy at the University of Minnesota.

“Folks all assumed we would see key transmission. Very well, just about every time we assume we have some explanation to think we know what it really is heading to do, it does not do that,” Osterholm says.

‘The worst’ of the surge of COVID, flu and RSV may possibly be more than

Infections, hospitalizations and deaths did improve in the U.S. soon after New Year’s. But the number of men and women catching the virus and obtaining hospitalized and dying from COVID soon started to slide again and have all been dropping now for weeks, according to the most up-to-date facts from the Centers for Sickness Manage and Avoidance.

The drop flu and RSV waves carry on to fade far too. And so the worst seems to be like it really is possibly above, a lot of public health experts say.

“I am glad to say that we didn’t have as significantly of a crush of bacterial infections as numerous considered was doable, which is quite welcome news,” says Jennifer Nuzzo, who heads the Pandemic Middle at Brown College.

The huge dilemma is: Why? Numerous factors might have performed a roll.

A person risk could be that men and women averted crowds, wore a mask and took other safety measures a lot more than public overall health authorities had anticipated they would. But that would not actually appear to be the situation.
May well ‘viral interference’ perform a position?

A further probability is “viral interference,” which is a principle that sometimes when a particular person gets infected with a person virus, their immune response could protect them from finding contaminated with a further virus. So maybe RSV and flu crowded out COVID in the same way COVID crowded out all those other viral infections at a variety of periods above the last two a long time.

“At this place, I feel which is extra of a guess fairly than really good proof,” Nuzzo suggests. “But if it is really correct, that could possibly necessarily mean we may well be additional inclined to viewing a rise in bacterial infections when these viruses are not all around.”

Nuzzo and other industry experts suspect as an alternative that the main cause the COVID surge is ebbing is all the immunity we’ve all crafted up from prior infections, and/or the COVID vaccinations lots of of us have been given.

“We have what I would get in touch with now a far better immunity barrier,” says Dr. Carlos Del Rio, an infectious illness expert at Emory College who heads the Infectious Disease Modern society of America.

“Between vaccinations and prior infection I consider all of us are in a unique area than we were being prior to,” he suggests. “All of us, if not thoroughly secured, we are considerably greater safeguarded. And that immunologic wall is true.”

Why COVID-19 continues to be a substantial threat

But none of this suggests the region would not have to get worried about COVID any more. Additional than 400 individuals are even now dying each and every day from COVID-19. Which is considerably fewer than the thousands who died throughout the darkest days of the past two winter surges. But it really is nonetheless several more people today than die from the flu each individual day, for instance.

“Make no mistake: COVID-19 stays a considerable community wellness danger,” Nuzzo states. “That has not changed. And the fact that we are nevertheless losing hundreds of people a day to this virus is deeply troubling. So we shouldn’t have to acknowledge that stage of ailment and death that we are observing.”

William Hanage, an epidemiologist at the Harvard T.H. Chan Faculty of General public Wellness, agrees.

“It can be over and above dilemma that modern society has moved into a phase the place the pandemic is for most of us if not over then surely tranquil. And that’s a terrific factor. Extensive may perhaps it continue being so,” Hanage states. “Is it the case that there is no preventable suffering? No. There is even now preventable struggling and loss of life.”

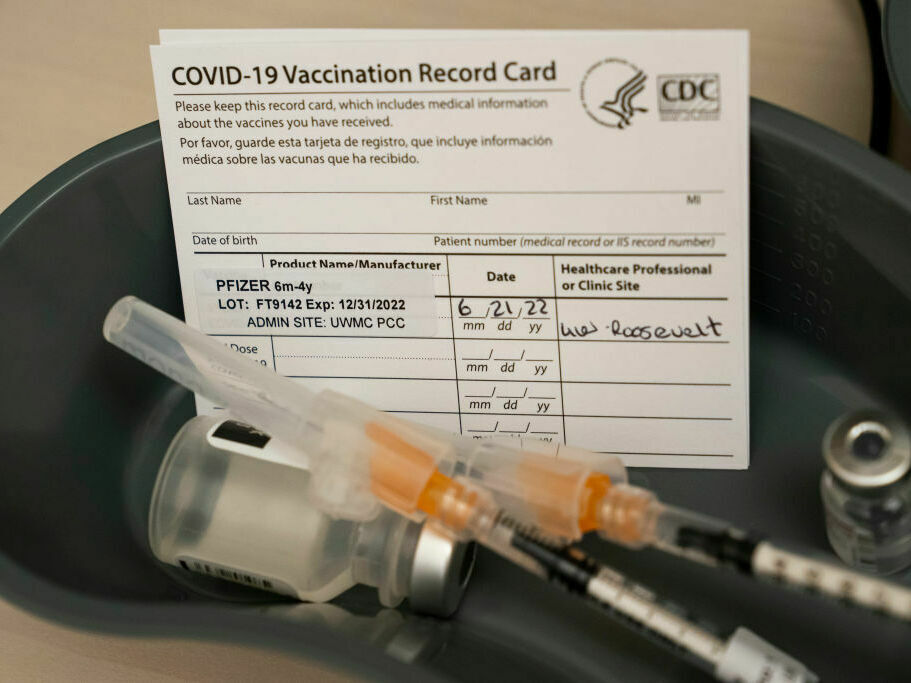
Most of the individuals dying are aged, numerous of whom have not been given the latest booster towards COVID-19. So acquiring them boosted could help a great deal. And the immunity the relaxation of us have built up could preserve fading. That indicates quite a few of the rest of us could at some issue will need to get a further booster to enable further reduce the risk from COVID.

An additional wave of flu could nonetheless strike this year, general public wellness industry experts note, and the danger carries on that still another new, even a lot more perilous variant of SARS-CoV-2 could arise.

“This virus is not carried out with us still,” Osterholm states.

The hospital treating her baby was in-network, but another hospital charged her : Shots

The hospital treating her baby was in-network, but another hospital charged her : Shots

Brenna Kearney plays with her daughter, Joey, at home in Chicago. When Kearney was pregnant, she developed a rare type of preeclampsia and had to undergo an emergency cesarean section. Joey was discharged after a 36-day stay in the NICU.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Brenna Kearney plays with her daughter, Joey, at home in Chicago. When Kearney was pregnant, she developed a rare type of preeclampsia and had to undergo an emergency cesarean section. Joey was discharged after a 36-day stay in the NICU.
Taylor Glascock for KHN

Brenna Kearney was seven months pregnant in December 2019 when she experienced what she thought were bad flu symptoms.

Her husband, Casey Trumble, drove her from their Chicago home to her OB-GYN’s office at Northwestern Medicine Prentice Women’s Hospital downtown. With suddenly elevated blood pressure and protein in her urine, she was diagnosed with preeclampsia, a potentially fatal but treatable pregnancy complication. Doctors admitted her to the hospital, saying she could expect to stay up to six weeks and have an induced delivery.

Then Kearney developed a bad headache and her blood platelet count plummeted, signs she was experiencing a rare, dangerous type of preeclampsia and required an immediate delivery by cesarean section.

Casey Trumble shows a photo of his daughter, Joey, after her premature birth in 2019. Her parents later learned she was treated in her Chicago hospital’s NICU by out-of-network neonatologists from the children’s hospital next door.

(Taylor Glascock for KHN)


hide caption

toggle caption

(Taylor Glascock for KHN)


Casey Trumble shows a photo of his daughter, Joey, after her premature birth in 2019. Her parents later learned she was treated in her Chicago hospital’s NICU by out-of-network neonatologists from the children’s hospital next door.

(Taylor Glascock for KHN)

Kearney’s daughter, Joey, born at 31 weeks, was placed on a ventilator and moved to the hospital’s neonatal intensive care unit. Small but healthy, she slowly began breathing on her own and eating normally. She was discharged in late January 2020, after 36 days in the NICU.

Then the bill came.

The Patient: Josephine “Joey” Trumble, now 3, was covered by her mother’s health plan through her employer, an advertising agency. For 2019, it was an Aetna plan, and for 2020, it was a plan from Blue Cross and Blue Shield of Illinois. Both policies were fully insured plans governed by Illinois laws.

Medical service: Neonatology physician services provided in January 2020. Joey needed tube feeding and ventilator care to provide oxygen.

Service rovider: Ann & Robert H. Lurie Children’s Hospital of Chicago, whose staff physicians treated Joey at Northwestern Medicine Prentice Women’s Hospital. Ownership-wise, Lurie is independent of Northwestern Medicine, but it is physically connected to Prentice Women’s by an enclosed walkway. Lurie has a collaboration agreement with Northwestern Medicine to provide neonatology and pediatric physician services to Prentice Women’s patients.

Total bill: Aetna paid for nearly all of Joey and her mother’s hospital and physician charges in December, while Blue Cross picked up nearly all of Joey’s hospital charges in January. Physician charges from Lurie in January totaled $14,624.55, of which the family was asked to pay $12,531.58 after payments from Blue Cross.

What gives: It took Kearney months of calls to Blue Cross and the two hospitals to find out why Lurie billed more than $14,000 for physician services: The physicians treating her daughter at Prentice Women’s — an in-network hospital under her health plan — actually worked for a separate, out-of-network hospital.

Illinois law bars insurers from charging patients out-of-network rates for neonatal care at in-network hospitals.

Kearney said no one had told her or her husband that Lurie doctors were treating their daughter. She said the family never signed an agreement consenting to receive care from out-of-network doctors.

Though it did not happen here, many patients unknowingly sign broad financial agreements — saying they’ll pay for almost anything their insurance doesn’t cover — in the piles of paperwork they receive upon admission to a hospital. In many cases, they are simply asked to sign on a screen, without seeing the document.

Blue Cross agreed to pay Lurie the in-network rate for the doctors’ services, reducing the bill to about $12,500 — which Lurie expected the family to pay.

In November 2020, Kearney started receiving letters from ICS Collection Service, a collection agency.

“Talking to Blue Cross was impossible, and Lurie said it’s not their problem and just wanted to put us on a payment plan,” Kearney said.

Details of the out-of-network medical bills totaling about $12,500 that Brenna Kearney and husband Casey Trumble received after their daughter, Joey, was born prematurely in 2019.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Details of the out-of-network medical bills totaling about $12,500 that Brenna Kearney and husband Casey Trumble received after their daughter, Joey, was born prematurely in 2019.

Taylor Glascock for KHN

Joey’s 36-day stay in the NICU happened before the federal government implemented the No Surprises Act barring surprise out-of-network billing. A state law prohibiting it, though, was in effect.

Since 2011, Illinois law has prohibited insurers from charging out-of-network rates for neonatologists, anesthesiologists, and certain other physicians when patients are treated at in-network hospitals.

Kearney said she repeatedly mentioned the law to Lurie and Blue Cross representatives, who denied knowledge of the provision.

“It definitely appears that under the 2011 law, Brenna can only be billed for in-network cost sharing,” said Kathy Mikos, a registered nurse and patient advocate with the Navocate Group in Woodridge, Illinois, who is not involved with Kearney’s case.

In December 2020, an insurance broker working for Kearney’s employer persuaded Blue Cross to pay the full out-of-network charges for the Lurie doctors, leaving the family owing $289.63 for coinsurance, which they promptly paid.

Having spent nearly the first year of her daughter’s life fighting medical bills from her birth, Kearney thought the ordeal was over.

Then, last month, she got a call from the collection agency, which again demanded payment at the full out-of-network rate for Lurie physician services provided to her daughter three years ago — the bill she believed Blue Cross had paid.

It took five hours on the phone for Kearney to piece together what had happened. Blue Cross had indeed paid the out-of-network charges in December 2020 — but, two days later, had taken back the money, ultimately paying Lurie’s doctors only the in-network rate.

A Lurie representative said Kearney and her husband still owed thousands of dollars. A Blue Cross representative suggested she set up a payment plan.

“I was at wits’ end, and I didn’t know how to fight this anymore,” Kearney said.

Lurie, Blue Cross, and Northwestern Medicine did not respond to numerous requests from KHN for comment. Lurie cited patient privacy, despite receiving a release from Kearney regarding the federal Health Insurance Portability and Accountability Act, or HIPAA, which authorized the hospital to discuss Joey’s case with KHN.

Joey Trumble was born prematurely in 2019 at Northwestern Medicine Prentice Women’s Hospital in Chicago. Unbeknownst to her parents, she was treated in the NICU by doctors from Lurie Children’s Hospital next door — and charged despite a state law protecting patients from such out-of-network billing.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Joey Trumble was born prematurely in 2019 at Northwestern Medicine Prentice Women’s Hospital in Chicago. Unbeknownst to her parents, she was treated in the NICU by doctors from Lurie Children’s Hospital next door — and charged despite a state law protecting patients from such out-of-network billing.

Taylor Glascock for KHN

The resolution: After KHN contacted Lurie and Blue Cross, a Lurie representative called Kearney offering to accept payment at the in-network rates after all.

Kearney said Tracy A. Spicer, manager of consolidated services at Lurie, told her Lurie has a “long-standing policy” of accepting in-network rates for Lurie physician services provided at Prentice Women’s. Spicer subsequently described it as a “long-standing courtesy,” then explained that acceptance of in-network rates was subject to “case-by-case consideration,” Kearney said.

Spicer said the family owed about $3,000, for their coinsurance share, and offered to set up a payment plan.

A day later — following additional requests by KHN for comment — Spicer called Kearney and said she would remove all physician charges for her daughter’s care. Spicer did not return KHN’s call seeking comment.

“I’m certain I’m not the only person still dealing with this” kind of predicament, Kearney said.

Kearney has filed complaints with the Illinois Department of Insurance and the Illinois Attorney General’s Office. The attorney general’s office told KHN it had never enforced the 2011 law barring certain out-of-network billing.

Presented with the facts of Kearney’s case, state Sen. Ann Gillespie, who sponsored a 2022 state law expanding consumer protections against out-of-network bills, told KHN she plans to contact Lurie, Blue Cross, and Northwestern Medicine to ask about their billing arrangement and whether they are in compliance with state law.

“We’ll see if it was a pattern and whether they need to look back and see if refunds are warranted,” Gillespie said.

The attorney general’s office told KHN it will investigate Kearney’s complaint, including whether Lurie violated the state Consumer Fraud and Deceptive Business Practices Act by telling her it was extending a “courtesy” by charging her only in-network rates, when that is what the 2011 law required. The insurance department also said it would investigate the complaint.

Brenna Kearney and husband Casey Trumble at home with daughter Joey, 3, and their 5-month-old son. Joey was born prematurely in 2019 and, unbeknownst to her parents, treated in the NICU by doctors from a neighboring hospital, Lurie Children’s.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Brenna Kearney and husband Casey Trumble at home with daughter Joey, 3, and their 5-month-old son. Joey was born prematurely in 2019 and, unbeknownst to her parents, treated in the NICU by doctors from a neighboring hospital, Lurie Children’s.

Taylor Glascock for KHN

The Takeaway: Even resourceful consumers who appear to have the law on their side, like Kearney, may find themselves in a losing, time-consuming battle with medical billing bureaucracies and facing collection actions.

Gillespie, the state senator, said Lurie, Northwestern Medicine, and Blue Cross should have known about the state law. She said patients who believe they have been improperly charged should file complaints with their state’s insurance department, which can trigger a broader investigation.

The federal No Surprises Act, which took effect last year, prohibits medical providers or insurers from billing patients for out-of-network physician charges at an in-network hospital, unless the patient formally consents to an out-of-network doctor. To be safe, patients should ask treating doctors whether they are in or out of network, even at an in-network hospital.

While the federal law offers patients new protections from out-of-network bills, many Americans still face problems from before the law took effect, said Loren Adler, associate director at the USC-Brookings Schaeffer Initiative for Health Policy. Illinois is one of relatively few states that had prior laws to protect consumers.

Also, some out-of-network physicians continue to bill patients, despite the new federal protections. So know your rights. Cite the new law. And don’t write the check.

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.