

Bernie Sanders chairs Senate committee looking to fix the health worker shortage : Shots

Bernie Sanders chairs Senate committee looking to fix the health worker shortage : Shots

Sen. Bernie Sanders, I-Vt., is chairing the Senate’s top health committee which is focused on solving the U.S. health care worker shortage.

J. Scott Applewhite/AP


hide caption

toggle caption

J. Scott Applewhite/AP


Sen. Bernie Sanders, I-Vt., is chairing the Senate’s top health committee which is focused on solving the U.S. health care worker shortage.

J. Scott Applewhite/AP

Senators are eying the growing shortage of health care workers in the United States as one of the few problems where there is room for bipartisan solutions, even in a deeply divided Congress gearing up for a presidential election cycle.

The shortage that’s only worsened since the pandemic is a prescription for skyrocketing costs, suffering, and unnecessary death, warned Sen. Bernie Sanders, I-Vt., who is the new chairman of the Senate’s top health committee. He spoke in his committee’s first hearing last week.

“We are going to produce legislation, and I think people will be surprised about the level of bipartisan supporters,” Sanders said in a brief interview during a break from the hearing. He called for the committee to “produce something meaningful.”

The shortage of health care workers of all sorts is a widespread problem, but is especially acute in rural areas and minority communities. Sanders pointed to the startling numbers of Americans living in medical care deserts to illustrate the point. There are nearly 100 million people who don’t have easy access to a primary care physician, almost 70 million with no dentist at hand, and some 158 million people who have few local mental health providers, Sanders said.

The COVID pandemic contributed to the nation’s existing worker shortage as many left the workforce as the crisis worsened. Some contracted the virus themselves, and large numbers of health care providers died. An investigation by KHN and The Guardian revealed more than 3,600 health workers in the United States died during the pandemic’s first year alone. Many others got burnt out or sought higher-paying jobs elsewhere.

“Despite all of our health care spending, we don’t have enough doctors, nurses, nurse practitioners, dentists, dental hygienists, pharmacists, mental health providers, and other medical professionals,” Sanders said, pointing to data that suggest the nation faces a shortfall of about 450,000 nurses and 120,000 doctors in the coming years, and 100,000 dentists now.

While Democrats and Republicans alike acknowledged the shortages hobbling care for hundreds of millions of Americans, any legislative solution must pass not only the Senate Health, Education, Labor and Pensions Committee, but also the full Senate and House of Representatives.

Far-right House Republicans have threatened to go so far as forcing the federal government to default on its debts as they demand spending cuts, and high government spending on health care could make new legislation a ripe target.

Sen. Bill Cassidy of Louisiana, the committee’s top Republican who is also a doctor, cited a few programs the committee is responsible for updating this year, such as an expiring program that trains many of the nation’s pediatricians. He said funding should reflect what works in the health care system and come “with the appropriate spending offsets.”

“We have to make sure that we’re not wasting the money we’re trying to productively spend,” he said.

None of the senators in the hearing disagreed with the fundamental problem that too many medical professionals are leaving their fields and that educational institutions are not graduating enough new ones to replace them and meet the growing needs of an aging population.

Members on both sides of the aisle recognized growing levels of burnout in the medical professions; increased threats faced by health care workers; the costs and challenges of working underserved areas; and financial incentives that steer younger professionals toward more lucrative specialties and higher-income areas.

Senators agreed on some strategies to boost numbers of health workers, such as encouraging more lower-cost educational options like community college and ensuring that existing programs are extended this year, such as the National Health Service Corps that trains doctors for underserved areas and graduate education programs.

A whiff of partisan thinking drifted into the conversation, with some Republicans focused more on decrying government interference in health care. Sen. Mitt Romney, R-Utah, suggested the State Department should do a better job clearing foreign students and practitioners to immigrate here. Cassidy raised electronic health records requirements as a contributor to physician burnout, saying they consume too much time.

Even in those areas, there were signs lawmakers could agree. Sen. Tim Kaine, D-Va., also raised the idea of unjamming the immigrant backlog.

Sen. Rand Paul, R-Ky., said vaccine requirements were an impediment. Sen. Roger Marshall, R-Kan., raised regulations barring some surprise medical bills as harmful to doctors.

“I think the fact that the committee has made this the first hearing means a number of us have bills. We may try to take a bunch of them up together and see if we can combine them into something,” said Kaine, pointing in particular to the idea of expanding loan forgiveness for people willing to go into areas with shortages. “I think there’s great prospects for bipartisan progress on this.”

Some of the senators credited Sanders with the initial progress toward a compromise. He spent his first weeks in his post meeting with committee members from both parties to identify areas of bipartisan agreement.

Sen. Lisa Murkowski, R-Alaska, said Sanders reached out to meet with her and discuss her priorities. They both named workforce shortages as a top issue, she said, adding, “We’ve got good stuff to work on.”

“In my conversation with him just on the floor this week, about what we might be able to do with the workforce issue, I think he was kind of probing to see if we could put together some efforts to just focus on these workforce shortages,” Murkowski told KHN. “There is a great deal of interest in legislating in this space.”

“What it’s going to look like, I can’t tell you yet,” she added.

“We are going to produce legislation,” Sanders said as the hearing ended. “I don’t do hearings for the sake of hearings.”

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.
Two decades of stagnant funding have rendered Canada uncompetitive in biomedical research. Here’s why it matters, and how to fix it.

You may imagine that the hard part of being a Canadian scientist is having a bright idea. However, while curiosity, persistence and inventiveness are prerequisites for scientific success, the major obstacle to being a biomedical scientist in Canada is obtaining research funding.

Canadian biomedical scientists receive funding to hire scientific staff and buy experimental materials by applying for federally funded grants from the Canadian Institutes of Health Research (CIHR).

To purchase their high-tech tools (infrastructure), researchers apply for grants from the Canada Foundation for Innovation (CFI). These grant agencies are underfunded, and some of their programs are poorly designed, with funding success rates so low scientists must apply repeatedly to obtain funding that is financially inadequate.

As a result, Canadian scientists may feel like they spend more time writing grant applications than doing research. The reality is that stagnant funding is holding back Canadian science.

Securing CIHR grants has become impractically competitive. Most applications require multiple revisions and resubmissions, often imposing an interval of one to two years between first submission and funding. Since funding from a CIHR project grant only lasts five years, the life of the lab — and the jobs of Canadian scientists — are recurrently in jeopardy.

Core funding issues

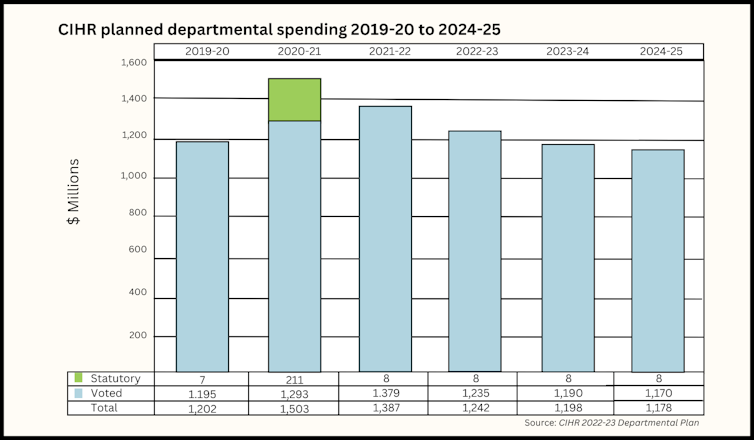
Let’s review the core problems with the funding of Canadian science. Stagnation in Canada’s biomedical grant funding reflects the fact CIHR’s funding from the Government of Canada has not increased since 2006 (in constant dollars, year 2000) and is not predicted to increase by 2025.

Two decades of stagnant funding have rendered Canada uncompetitive in biomedical research. Here’s why it matters, and how to fix it.
Graph of planned spending over time illustrates that CIHR funding is flat.
(CIHR data)

The United States is a relevant comparator because it is home to many of the world’s leading scientists. Canadian scientists, if not funded, often relocate to the U.S. Compare America’s National Institutes of Health (NIH) 2020-21 budget of US$45 billion (roughly C$60 billion) to CIHR’s C$1.2 billion. America’s NIH budget is 50-fold that of Canada’s CIHR budget, but the U.S. population is only nine-fold greater than ours.

Canada’s spending on research and development, as a percentage of gross domestic spending, is also smaller than the U.S.’s.

Grant competition success rates

The success rate in CIHR grant competitions has declined from 31 per cent in 2005 to around 15 per cent in 2020.

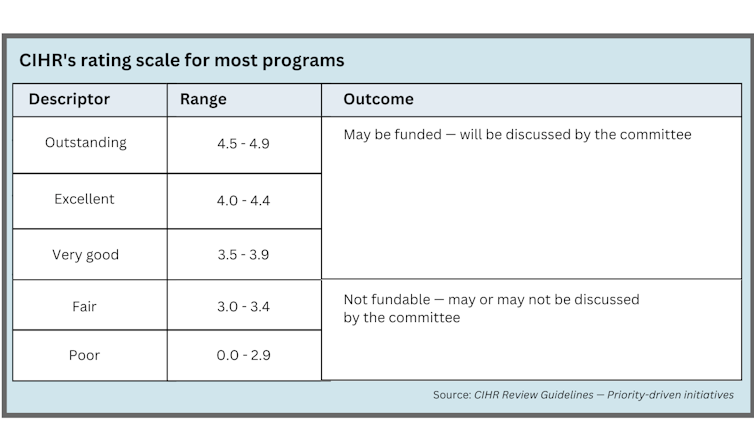
CIHR evaluates applications on a scale of zero to 4.9, corresponding to categories of poor, fair, very good, excellent and outstanding. Currently, CIHR grants are rarely funded unless the voted score is outstanding (rated 4.4 to 4.9). Usually only the top 18 per cent of all grants — fewer than one in five — are funded, and virtually all grants rated excellent are rejected.

This low-success endeavor is a demoralizing waste of time for the 82 per cent of scientists who are rejected and for the peer-review volunteers — unpaid colleagues who spent weeks reviewing the applications.

chart showing CIHR grant rating categories
Almost all grants scored by CIHR as excellent go unfunded.
(CIHR data)

Once funded, challenges remain. All CIHR awarded project grants are now subject to a 23.5 per cent across-the-board funding cut. This cut allowed CIHR to fund 87 additional grants per competition from 2018 to 2020, however the value of a five-year project grant shrank from $950,000 to $725,000.

These cuts mean scientific staff must take pay cuts or be terminated, and the approved research can only be partially completed.

Fixing funding

Canada needs to revitalize its scientific mojo and to do so must improve research funding. There are several steps that would improve science funding in Canada.

1. Implement the Fundamental Science Review recommendations

The fix for Canadian science was well enunciated by the Fundamental Science Review, also known as the Naylor Report, in 2017. This report recognized that underfunded Canadian science was falling behind.

It noted that federal underfunding is exacerbated by CIHR’s practice of earmarking substantial portions of its limited funds to targeted proposals that address governmental priorities, rather than funding research and discovery science.

The report made simple recommendations to improve Canadian research: “Rapidly increase its investment in independent, investigator-led, research to redress the imbalance caused by differential investments favouring priority-driven, targeted research.”

A group of people sitting on blue storage drawer units in a V formation.
Members of the author’s research team at the Archer laboratory at Queen’s University.
(Author provided), Author provided

It also recommended “formation of an independent advisory committee on basic research and industrial innovation, comprised of leaders in research and industry” (not government employees). Our government currently makes many top-down science funding decisions without a strategic scientific plan or an external scientific committee to advise them. An independent advisory committee would reduce political interference in science.

The Naylor report’s recommendations have not been fully implemented, but would transform Canadian research. This would require commitment of an additional 0.4 per cent of the Government of Canada’s annual budget to our science sector.

2. Fund salaries for scientists who run infrastructure

In the meantime, CFI and CIHR could each implement “researcher-centric” changes.

CFI could accompany its infrastructure grants with funding for the scientists who are needed to operate these complex research platforms.

CFI grants are used to purchase the multi-million-dollar tools needed to conduct research at the cutting-edge, such as NextGen gene sequencers and super resolution confocal microscopes. CFI has a 30 per cent funding success rate, allowing purchase of infrastructure; but it does not pay for the scientists who run these scientific infrastructure platforms.

This makes it difficult to sustain a CFI scientific platform.

3. Bring back the foundation grant program

CIHR could resurrect its very successful foundation grant program.

A woman in a white coat in a lab
Foundation grants allowed scientists to bundle all their research into a single, comprehensive application.
(Shutterstock)

CIHR understood that its most successful scientists usually required two to three project grants, and recognized the time drag that acquiring multiple project grants required.

They responded in 2014 with the foundation grant program. Foundation grants allowed scientists to bundle all their research into a single, comprehensive application which offered more funding (equivalent to two to three project grants) for a longer duration (seven years instead of five years for project grants).

This allowed researchers to spend more time on doing science and less on writing and reviewing grants. My foundation grant gave me the stability and flexibility to simultaneously study oxygen sensing, mitochondrial dynamics and to develop drugs to treat pulmonary hypertension, cancer and COVID-19.

However, the foundation grant program was unceremoniously terminated, forcing grant holders to once again, apply for two to three simultaneous project grants.


Read more:
How COVID-19 damages lungs: The virus attacks mitochondria, continuing an ancient battle that began in the primordial soup


Funding research pays off

Researchers are key to Canada’s capacity to create a high-tech economy, build the biomedical sector and seed entrepreneurial activity. Researchers also support our academic health sciences centres and universities, making them internationally competitive.

Research has a great return on investment, with an estimated 30 to 100 per cent of the expenditure on publicly funded research being returned to society. Each research laboratory is a small business creating well-paying jobs, knowledge and intellectual property, which many commercialize.

In addition to launching medical innovations, patents and spin-off companies, Canada’s researchers teach university students, and many CIHR-funded clinician-scientists provide patient care in our hospitals. In all of these ways, investment in research is critical to making Canada healthy, wealthy and wise.

