Inflation and money woes are forcing Americans to delay medical care : Shots

Inflation and money woes are forcing Americans to delay medical care : Shots

Substitute teacher Crystal Clyburn, 51, doesn’t have health insurance. She got her blood pressure checked at a health fair in Sarasota, Fla.

Stephanie Colombini/WUSF


hide caption

toggle caption

Stephanie Colombini/WUSF


Substitute teacher Crystal Clyburn, 51, doesn’t have health insurance. She got her blood pressure checked at a health fair in Sarasota, Fla.

Stephanie Colombini/WUSF

At a health-screening event in Sarasota, Florida, people milled around a parking lot waiting their turn for blood pressure or diabetes checks. The event was held in Sarasota’s Newtown neighborhood, a historically Black community.

Local resident Tracy Green, 54, joined the line outside a pink and white bus offering free mammograms.

“It’s a blessing, because some people, like me, are not fortunate and so this is what I needed,” she said.

Green said she wanted the exam because cancer runs in her family. And there’s another health concern: her breasts are large and cause her severe back pain. A doctor once recommended she get reduction surgery, she said, but she’s uninsured and can’t afford it.

In a recent Gallup poll, 38{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of Americans surveyed said they had put off medical treatment last year due to cost, up from 26{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} in 2021. The new figure is the highest since Gallup started tracking the issue in 2001.

A survey by The Kaiser Family Foundation last summer showed similar results. It found people were most likely to delay dental care, followed by vision services and doctor’s office visits. Many didn’t take medications as prescribed.

The health screening event is part of an ongoing effort provide health services to low-income Floridians who are uninsured. Attendees could have their blood pressure checked or receive screenings for diabetes. A bus also delivered mammogram services.

Stephanie Colombini/WUSF


hide caption

toggle caption

Stephanie Colombini/WUSF


The health screening event is part of an ongoing effort provide health services to low-income Floridians who are uninsured. Attendees could have their blood pressure checked or receive screenings for diabetes. A bus also delivered mammogram services.

Stephanie Colombini/WUSF

The neighborhood screening event in Newtown — organized by the non-profit Multicultural Health Institute in partnership with a local hospital and other health groups — is part of an effort to fill in the coverage gap for low-income people.

Tracy Green explained that her teeth are in bad shape too, but dental care will also have to wait. She doesn’t have health insurance or a stable job. When she can, she finds occasional work as a day laborer through a local temp office.

“I only make like $60 or $70-something a day. You know that ain’t making no money,” said Green. “And some days you go in and they don’t have work.”

If she lived in another state, Green might have been able to enroll in Medicaid. But Florida is one of eleven remaining states that haven’t expanded the program to cover more working-age adults. With rent and other bills to pay, Green says her health is taking a backseat.

“I don’t have money to go to the dentist, nothing, it’s so expensive,” she said. “Now, to get one extraction, one tooth pulled, it’s like $200-300 that you don’t have. So I don’t know what to do. It’s like fighting a losing battle right now.”

Tracy Green, 54, joined the line outside a pink and white bus that offered free mammograms. Green said she wanted the exam because cancer runs in her family.

Stephanie Colombini/WUSF


hide caption

toggle caption

Stephanie Colombini/WUSF


Tracy Green, 54, joined the line outside a pink and white bus that offered free mammograms. Green said she wanted the exam because cancer runs in her family.

Stephanie Colombini/WUSF

In the Kaiser poll, 85 percent of uninsured adults said they found it difficult to pay for health care. Nearly half of insured respondents said they struggled with affordability as well.

The U.S. experienced record high inflation rates last year, and parts of Florida, including the nearby Tampa metro area, often fared even worse.

“We see an increasing desperation,” said Dr. Lisa Merritt, executive director of the Multicultural Health Institute.

The Institute, which helps people access low-cost care, is based in Newtown. The neighborhood, inland from Sarasota’s lavish beach communities, has many residents who live below the poverty line, lack insurance and face other barriers to consistent and affordable care.

“It’s very difficult for people to be concerned about abstract things like getting screenings, getting regular health maintenance, when they’re contending with the challenges of basic survival: food, shelter, transportation often,” Merritt said.

‘Horrible’ housing costs put squeeze on health needs

Merritt and her team of volunteers work to build trust with community residents who may not be aware that support is available. They help people apply for low-cost insurance coverage, free medication programs and other resources that can reduce treatment costs.

Volunteer Bonnie Hardy said the people she serves have many financial worries, but one thing tops the list.

“Right now? A place to stay,” said Hardy. “Housing is horrible.”

High housing costs have started to ease in recent months, but data shows rent in Sarasota has gone up nearly 50 percent since the pandemic began in 2020.

Hardy helps people find housing and connects them with programs that cover costs like utilities and security deposits. The goal is to help people stabilize their day-to-day lives, and that in itself can improve health, she said.

“Because they’re more comfortable now,” she said. “They feel like, hey the rent is paid, I can let my guard down, maybe I can go get the medical attention I need.”

Dr. Lisa Merritt and her team of volunteers work to build trust with community residents who are uninsured but may not be aware that support is available.

Daylina Miller/WUSF


hide caption

toggle caption

Daylina Miller/WUSF
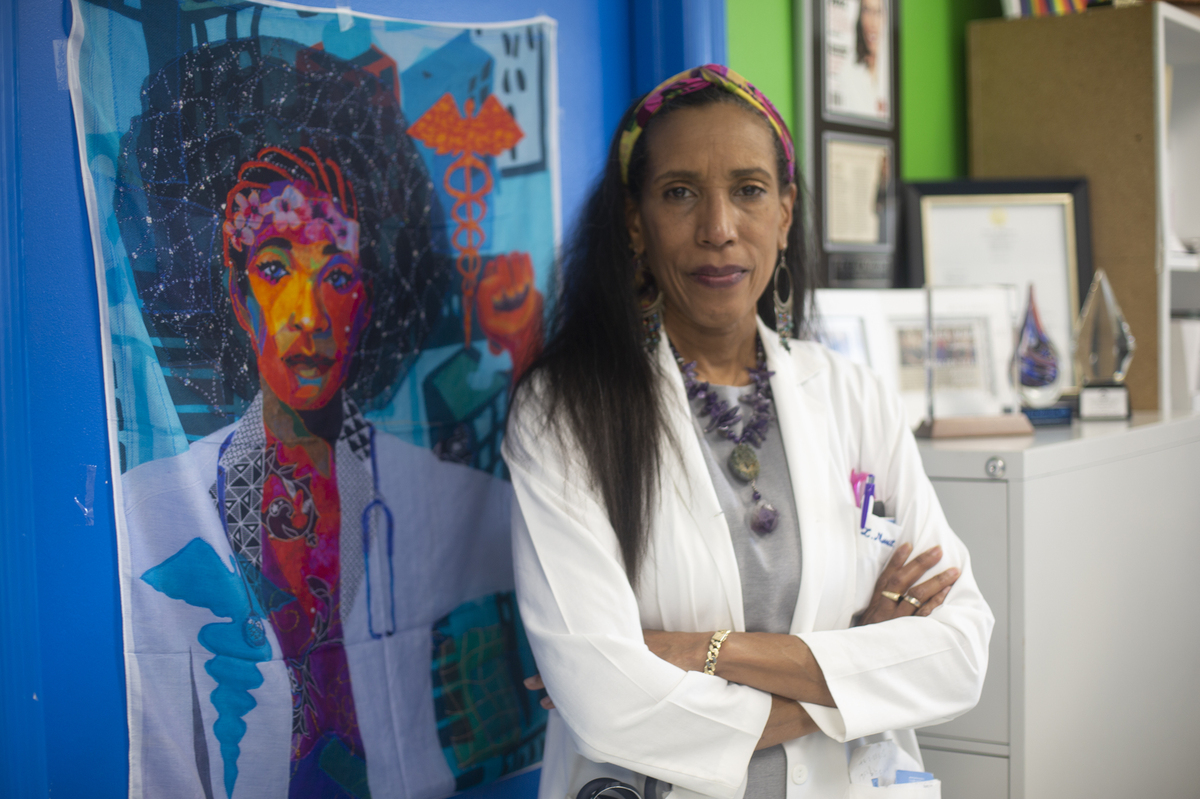

Dr. Lisa Merritt and her team of volunteers work to build trust with community residents who are uninsured but may not be aware that support is available.

Daylina Miller/WUSF

Research shows putting off health care can lead to bigger problems.

The Gallup poll found 27{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of respondents delayed treatment due to costs even for “very or somewhat serious” conditions.

Another reason people may be holding off on treating medical issues is that they already have health care debt. An investigation from NPR and Kaiser Health News found about 100 million people in America had medical debt. About 1 in 8 owe more than $10,000, according to a KFF poll.

Treating cancers or chronic conditions like diabetes early can not only save lives, it can also be less expensive than treating advanced-stage illnesses, according to the Centers for Disease Control and Prevention.

Doctors at the health screening event in Newtown said it’s critical to help residents access preventive care.

At the health fair, substitute teacher Crystal Clyburn, 51, got a mammogram on the pink-and-white mobile bus and had her blood pressure checked. Clyburn doesn’t have health insurance and she relies on events like this to stay on top of her health.

“I just try to take advantage of whatever that’s out there, whatever that’s free,” she said. “You have to take care of yourself because you can look healthy and not even know you’re sick.”

After the cuff came off, a doctor told Clyburn her blood pressure was a little high. But then the doctor kept talking, and she smiled.

Although her pressure was high, it wasn’t high enough that she needed to take medication. She thanked him and left, relieved to know that was one expense she wouldn’t have to worry about. Not yet, anyway.

Patient advocates push for aggressive crackdown on medical debt : Shots

Patient advocates push for aggressive crackdown on medical debt : Shots

Marcus and Allyson Ward were shelling out off a debt courting back again to the birth of their twins, Theo and Milo. They are between 100 million Americans with professional medical financial debt, in accordance to a KHN/NPR investigation.

Taylor Glascock for KHN and NPR


disguise caption

toggle caption

Taylor Glascock for KHN and NPR


Marcus and Allyson Ward had been shelling out off a personal debt dating back again to the beginning of their twins, Theo and Milo. They are between 100 million Us citizens with healthcare debt, according to a KHN/NPR investigation.

Taylor Glascock for KHN and NPR

Dozens of advocates for sufferers and consumers, citing popular hurt brought on by health-related financial debt, are pushing the Biden administration to choose a lot more intense steps to defend Us citizens from health care charges and credit card debt collectors.

In letters to the IRS and the Consumer Fiscal Security Bureau, the teams simply call for new federal rules that amid other factors would prohibit debt for medically essential care from appearing on client credit rating reviews.

Advocates also want the federal governing administration to bar nonprofit hospitals from selling affected individual credit card debt or denying health-related treatment to people today with previous-due expenses, techniques that continue to be popular across the U.S., KHN observed.

And the teams are pressing the IRS to crack down on nonprofit medical center techniques that withhold fiscal guidance from minimal-profits clients or make help cumbersome to get, yet another frequent obstacle KHN documented.

“Each and every working day persons are obtaining to make decisions about housing and apparel and food items mainly because of professional medical credit card debt,” says Emily Stewart, govt director of Local community Catalyst, a Boston nonprofit foremost the energy. “It is seriously urgent the Biden administration acquire motion to place protections in area.”

Amid the extra than 50 teams supporting the initiative are national advocates such as the National Buyer Law Middle, the Arthritis Foundation, and the Leukemia & Lymphoma Modern society.

Nationwide, 100 million men and women have wellness treatment personal debt, in accordance to a KHN-NPR investigation, which has documented a disaster that is driving Americans from their homes, draining their financial savings, and avoiding thousands and thousands from accessing care they need to have.

Although some of the debt appears on credit studies, a great deal of it is hidden elsewhere as credit card balances, loans from family, or payment designs to hospitals and other health care providers.

The scale of this issue and its toll have spurred numerous countrywide and state initiatives.

Last spring, the White Residence directed federal organizations to operate on relieving professional medical debts for veterans and to stop thinking of professional medical credit card debt in analyzing eligibility for some federally backed mortgages.

California, Colorado, Maryland, New York, and other states have enacted new regulations to develop client protections and demand hospitals inside of their borders to increase economic aid. And the 3 premier credit history agencies — Equifax, Experian, and Transunion — reported they would halt which include some health-related financial debt on credit experiences as of last July.

But a lot of consumer and individual advocates say the steps, though essential, continue to leave thousands and thousands of People vulnerable to economical ruin if they turn out to be ill or hurt. “It is significant that the CFPB consider added motion,” the teams compose to the federal agency established in 2010 to bolster oversight of consumer financial goods.

The key credit history ranking providers, for illustration, agreed to exclude only debts that have been paid off and unpaid debts of a lot less than $500. Sufferers with greater health-related expenditures they can not pay back may well nonetheless see their credit rating scores drop.

The groups also are asking the CFPB to eradicate deferred fascination on health-related credit history cards. This arrangement is popular for sellers this sort of as CareCredit, whose financial loans have no interest at first but can exceed 25{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} if clients don’t spend off the bank loan in time.

Assortment sector officers have lobbied against broader restrictions on credit reporting, saying limitations would acquire absent an crucial resource that hospitals, physicians’ workplaces, and other health-related suppliers want to obtain their funds and stay in enterprise.

“We recognize the worries, but a wide ban on credit score reporting could have some unintended penalties,” reported Jack Brown III, president of Florida-dependent Gulf Coastline Collection Bureau, citing the prospect of battling hospitals and other companies closing, which would lessen treatment selections.

Brown, a previous president of ACA Worldwide, the selection industry’s major trade affiliation, warned that much more healthcare suppliers would also start off demanding upfront payment, putting more tension on individuals.

To even more protect clients from out-of-pocket charges like these, lots of advocates say hospitals, especially all those that are exempt from taxes since they are meant to serve the community, must make money aid more available, a key need in the group’s letters. “For much too prolonged, nonprofit hospitals have not been behaving like nonprofits,” reported Liz Coyle, executive director of the nonprofit Georgia Look at.

Charity treatment is available at most U.S. hospitals. And nonprofit medical devices must provide assist as a problem of getting tax-exempt. But at several professional medical centers, info about this guidance is challenging or unattainable to come across.

Benchmarks also fluctuate commonly, with help at some hospitals minimal to individuals with cash flow as lower as $13,590 a calendar year. At other hospitals, individuals building five or 6 periods that substantially can get aid.

The end result is prevalent confusion that has remaining countless people who should really have been eligible for assist with huge expenses instead. A 2019 KHN analysis of healthcare facility tax filings found that virtually half of nonprofit health-related methods had been billing people with incomes lower adequate to qualify for charity care.

The groups are inquiring the IRS to situation principles that would established popular specifications for charity care and a uniform application throughout nonprofit hospitals. (Current rules for charity treatment do not use to for-revenue or general public hospitals.)

The advocates also want the federal company to reinforce limits on how considerably nonprofit hospitals can cost and to curtail aggressive collection techniques this kind of as foreclosing on patients’ homes or denying or deferring professional medical treatment.

Far more than two-thirds of hospitals sue sufferers or acquire other lawful action from them, such as garnishing wages or putting liens on property, in accordance to a recent KHN investigation. A quarter promote patients’ money owed to credit card debt collectors, who in convert can go after sufferers for many years for unpaid bills. About 1 in 5 deny nonemergency treatment to individuals with remarkable financial debt.

“Charitable institutions, which have other procedures of assortment accessible to them, should not be permitted to withhold desired clinical care as a signifies to strain patients to pay back,” the groups wrote.

KHN (Kaiser Overall health News) is a countrywide, editorially impartial application of KFF (Kaiser Spouse and children Basis).

Secrecy shrouds troubled state psychiatric hospital in Montana : Shots

Secrecy shrouds troubled state psychiatric hospital in Montana : Shots

Jennifer Mitchell thumbs through her husband’s medical records from his time at the Montana State Hospital. Records show doctors took Mitchell’s husband off some of his congestive heart failure medications. Mitchell says she was never consulted.

Aaron Bolton/Montana Public Radio


hide caption

toggle caption

Aaron Bolton/Montana Public Radio


Jennifer Mitchell thumbs through her husband’s medical records from his time at the Montana State Hospital. Records show doctors took Mitchell’s husband off some of his congestive heart failure medications. Mitchell says she was never consulted.

Aaron Bolton/Montana Public Radio

BUTTE, Mont. — Jennifer Mitchell remembered getting a call nearly two years ago that her 69-year-old husband, Bill, had crashed his car and had been committed to the Montana State Hospital, the state-run psychiatric hospital for adults about 20 miles from their home in Butte.

Physicians thought Bill Mitchell had dementia and could be a danger to himself or others, according to medical records. But once he was admitted, his wife really began to worry. She couldn’t visit him because of covid-19 restrictions, and she couldn’t get details about the care or the medicine he was receiving.

“I tried to get an idea of what he was taking, not taking. I could not get answers,” Jennifer said.

When Bill was discharged after 60 days, Jennifer discovered he had been taken off some of his congestive heart failure medications. A month later, he went into cardiac arrest and was moved to hospice care. He died on July 30, 2021, a day after his 70th birthday.

The psychiatric hospital in southwestern Montana has been under scrutiny since the federal Centers for Medicare & Medicaid Services decertified it in April 2022 following investigations into patient deaths and assaults. Federal officials found in the investigations that the hospital had failed to meet Medicare’s “basic health and safety requirements.”

Mitchell said that she was infuriated by the lack of transparency around her husband’s care and that she hoped decertification would force a change for the better. But it’s had the opposite effect. When federal oversight and funding of the Montana State Hospital was removed, so too was the ability of the public to learn details surrounding patient deaths and injuries.

Between April’s decertification and the end of December, five Montana State Hospital patients have experienced severe injuries requiring immediate medical care or hospitalization, and there have been eight substantiated abuse and neglect reports, Montana Department of Public Health and Human Services spokesperson Jon Ebelt said.

Six patients died in that period in the 174-bed hospital, though Ebelt declined to say how many deaths were investigated or if any deaths were deemed preventable.

The Montana State Hospital in Warm Springs, Montana, lost federal funding in April 2022 after an investigation into four patient deaths and a violent patient-on-patient assault.

Aaron Bolton/Montana Public Radio


hide caption

toggle caption

Aaron Bolton/Montana Public Radio


The Montana State Hospital in Warm Springs, Montana, lost federal funding in April 2022 after an investigation into four patient deaths and a violent patient-on-patient assault.

Aaron Bolton/Montana Public Radio

The circumstances surrounding all those incidents are not publicly known. That’s because, unlike federal investigations, state-level investigations are not public record.

The state health department denied a public records request for all investigations into Montana State Hospital patient deaths, injuries, and assaults since losing federal certification. Ebelt cited a Montana law that says any records about providing treatment to the seriously mentally ill are confidential and privileged.

States vary widely in what information about abuse and neglect at state-run medical facilities is made public, said David Hutt, deputy executive director for legal services for the National Disability Rights Network.

Hutt noted that the lack of transparency at the Montana State Hospital is unique because it lost federal certification and oversight, which is extremely rare.

State-hired contractors have produced public reports highlighting improvements at the Montana State Hospital, such as a reduction in falls among geriatric patients. But those reports don’t disclose information related to patient deaths, severe injuries, or substantiated abuse and neglect cases, which had led to decertification in the first place.

The lack of information frustrates some lawmakers as they consider state health officials’ and Republican Gov. Greg Gianforte’s request for a $300 million appropriation to overhaul the state’s mental health system and a nearly $20 million request for capital improvements and CMS recertification efforts at the state hospital.

“We’ve stabilized MSH since that decertification with a change in leadership and with no significant increase in deaths, serious injuries, or substantiated abuse or neglect allegations,” state health department Director Charlie Brereton told state senators during his recent confirmation hearing.

State Democratic Rep. Mary Caferro, who serves on committees considering funding requests and other legislation to reform the state hospital, likened the current level of oversight at the state hospital to the fox watching the henhouse.

“The legislature, when we have good information, thorough information, we make better policy that’s in the best interest of the people we represent,” Caferro said.

Mental health experts agree with Caferro.

“We should know the answers to whether people in the hospital are safe,” said Ben Miller, a clinical psychologist and former president of Well Being Trust, a national foundation focused on mental health care.

A bill that passed through the Montana Senate and is before the House would automatically send all abuse and neglect reports at the state hospital to Disability Rights Montana within five days of an incident. The nonprofit is the federally designated advocacy and watchdog organization for people with disabilities in the state. It recently released a report detailing how some patients were discharged to homeless shelters.

Bernie Franks-Ongoy, the organization’s executive director, said that Disability Rights Montana hopes to be able to share general information from the reports with lawmakers and the public, but noted that state law significantly limits what can be made public. Caferro said she’ll seek to amend the bill to make redacted versions of the reports available to lawmakers and the public.

The Montana Mental Disabilities Board of Visitors also has regular access to the facility and patient records, but its last inspection of the state hospital was in 2019 and the next inspection isn’t expected until next year.

Some lawmakers call the oversight adequate.

“I don’t worry so much about the administration at the hospital hiding anything because they really do have the light shown on them constantly with [Disability Rights Montana] and the Board of Visitors,” said Republican Rep. Bob Keenan, who chairs the committee considering funding requests for the state hospital and the state’s mental health system.

Jennifer Mitchell looks through pictures of travels with her husband, Bill. After Bill was discharged from the Montana State Hospital, Jennifer discovered he was taken off some of his congestive heart failure medications. He later suffered a cardiac arrest and died in hospice care.

Aaron Bolton/Montana Public Radio


hide caption

toggle caption

Aaron Bolton/Montana Public Radio


Jennifer Mitchell looks through pictures of travels with her husband, Bill. After Bill was discharged from the Montana State Hospital, Jennifer discovered he was taken off some of his congestive heart failure medications. He later suffered a cardiac arrest and died in hospice care.

Aaron Bolton/Montana Public Radio

Keenan and Gianforte blame the current conditions at the facility and loss of CMS certification at the state hospital on prior Democratic administrations. Federal officials noted serious deficiencies at the Montana State Hospital in 2017, but federal officials later deemed those issues resolved.

If lawmakers approve the mental health funding requests, the administration plans to open two lower-level mental health facilities in the coming years to reduce demand at the state hospital. However, the hospital would remain a key fixture of Montana’s mental health system, according to state health officials. Mental health advocates and many lawmakers agree the state hospital should be saved.

Jennifer Mitchell, the woman whose husband died shortly after his discharge from the state hospital, thinks the hospital is beyond repair and worries more patients will die at the facility. She reflected on how hospital officials frequently changed her husband’s medication in response to his depression and refusal to eat, and said she believes her husband would still be alive today if he hadn’t been committed there.

“There were just so many little mistakes or little things that could have been different, and it would have been a totally different outcome,” she said.

This story is from of NPR’s partnership with Montana Public Radio and KHN. KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues.

Idaho dropped Medicaid recipients instead of trying hard to track them down : Shots

Idaho dropped Medicaid recipients instead of trying hard to track them down : Shots

Idaho removed nearly 10,000 people from Medicaid in the pandemic’s first years when enrollees couldn’t be reached. The episode previews what could occur in other states after April 1, when a COVID-era coverage mandate ends.

Eric Harkleroad/KHN


hide caption

toggle caption

Eric Harkleroad/KHN


Idaho removed nearly 10,000 people from Medicaid in the pandemic’s first years when enrollees couldn’t be reached. The episode previews what could occur in other states after April 1, when a COVID-era coverage mandate ends.

Eric Harkleroad/KHN

During the first two years of the COVID-19 pandemic, while the federal government was trying to prevent people on Medicaid from losing health coverage, Idaho dropped nearly 10,000 people from the safety-net program.

Federal law generally banned states from dropping people, and federal officials said Idaho acted improperly. Idaho officials, however, said they didn’t think they did anything wrong.

The episode, revealed in documents KHN obtained through a public records request and in interviews with state officials, offers a preview of what could soon unfold across the United States for millions of people covered through Medicaid, the federal-state health insurance program for people with low incomes.

It shows how easily state bureaucracies can disenroll people they shouldn’t be disenrolling, leaving those people in financial and medical jeopardy. It also illustrates the potential for confusion and disagreement over what procedures states should follow before cutting off anyone’s benefits, particularly when enrollees can’t be reached.

Why it could happen in other states starting April 1

A COVID-19 relief law Congress enacted in 2020 prohibited states from removing people from Medicaid except in a few narrow circumstances, such as if an enrollee died or moved out of state.

On April 1 of this year, after the prohibition expires, states will resume removing people who no longer qualify or do not furnish needed information. That process has come to be known as “the unwinding.” Some states see the end of the mandate as a chance to quickly winnow Medicaid rolls that have grown to record levels.

Idaho Gov. Brad Little was among 25 Republican governors who told President Joe Biden in a December letter, that, by keeping ineligible people on the Medicaid rolls, the mandate was “negatively affecting states.”

Idaho’s Medicaid program had nearly 450,000 enrollees at the start of this month. The state said about 150,000 of them no longer qualified or had not been in contact with the program during the public health emergency.

By the time recipients notice, ‘the damage will be done’

Nationally, as disenrollments ramp up, many officials are predicting a mess. The Department of Health and Human Services has predicted that nearly 7 million people still entitled to Medicaid benefits will lose coverage because they fail to complete renewals or state governments won’t be able to contact them.

People may not realize they’ve been dropped until they seek care.

“The damage will be done,” said Tricia Brooks, a research professor with Georgetown University’s Center for Children and Families.

Idaho terminated Medicaid benefits for more than 9,800 beneficiaries during the pandemic after mail the state sent them was returned as undeliverable and other attempts to confirm that they still resided in Idaho failed, according to emails obtained by KHN between the Idaho Department of Health and Welfare and the U.S. Centers for Medicare & Medicaid Services.

The emails, sent last spring and summer, detail Idaho’s rationale for the terminations, CMS’ concerns, and the state’s efforts to restore benefits.

CMS officials maintained that, when Idaho’s mailings were returned with no forwarding address or an out-of-state forwarding address, the state didn’t do enough to make contact with the beneficiaries and ensure they no longer lived in Idaho.

“CMS appreciates the state’s efforts to come into compliance,” Sarah O’Connor, a CMS official, wrote on Aug. 18 of last year.

In meetings with CMS, Idaho officials were told the state could not kick people off if it didn’t make “physical contact,” Shane Leach, administrator of the Division of Welfare at Idaho’s Department of Health and Welfare, recounted in correspondence with CMS.

“What they were saying early on,” Leach told KHN, “is, basically, we didn’t do enough outreach to really prove that this person was no longer in Idaho and not eligible for Medicaid.”

He added: “My perspective is, we did our due diligence.”

Many calls and letters went unanswered, Idaho says

For the first two years of the pandemic, when Idaho received returned mail with an out-of-state forwarding address or no forwarding address — possibly indicating the enrollee no longer lived in Idaho — Leach said state officials would call them.

A lot of the calls went unanswered, he said.

“They’re really concerned about physically talking to the person or having them say, ‘Yes, I’m in another state,'” Leach said of CMS. “And so that’s where they said, ‘OK, well, you need to reinstate those individuals.'”

“We felt like we were following the guidance,” said Jennifer Palagi, a deputy director at the Idaho health department.

CMS guidance in August 2021 stated that returned mail alone was not reason enough to disenroll Medicaid beneficiaries during the public health emergency. But if CMS had issued a written version of the standard to which it was holding Idaho — in which disenrollments would be justified only if the state made contact with the enrollee — Medicaid consumer advocates and other specialists said they were unaware of it.

CMS declined to answer several questions about the Idaho situation.

“CMS is committed to working with states to ensure continuity of coverage for eligible individuals, including those for whom the Medicaid agency receives returned mail,” Bruce Alexander, director of CMS’ office of communications, said in a written statement to KHN.

According to the batch of emails obtained by KHN, Idaho in March 2022 did change the state’s procedures after discussions with CMS. By July, the state Medicaid agency had reinstated benefits for 6,400 people the state couldn’t get hold of.

In one of the emails the Idaho Medicaid agency sent to CMS last July, the state said it was reviewing the extent to which it needed to pay medical bills the program had originally rejected.

It’s a long-standing problem — and about to get bigger

The inability to reach Medicaid enrollees has been a long-standing problem. The paperwork that agencies send people to fill out often goes unreturned. Some ends up at the wrong address. Up-to-date phone numbers or email addresses may not be available to state and county workers.

“In a perfect situation, a member responds to give you their current address, a phone number, an email address, etc.,” said Jack Rollins, director of federal policy for the National Association of Medicaid Directors. “But that is not the case for a lot of situations.”

And that’s bound to become a larger problem, consumer advocates say, after the pandemic-era enrollment mandate ends this spring. On Jan. 27 of this year, CMS detailed to health agencies in all states the minimum they’ll need to do to reach a Medicaid recipient who hasn’t responded to a mailed form: Before ending benefits, a state must try to obtain up-to-date contact information and attempt to reach the person through at least two means, such as by mail, phone, email or text message, if those means are available.

Still, “there’s just a lot of variation in terms of what that could look like,” said Farah Erzouki, a senior health policy analyst for the Center on Budget and Policy Priorities, a think tank in Washington, D.C.

If any state isn’t following the rules, Georgetown University’s Brooks said, it can take months to fix the problems — all while people’s benefits hang in the balance.

“This is what we want to avoid,” Brooks said. “We don’t need to spend the next three years after ‘the unwinding’ trying to get people back on who should not have been disenrolled.”

KHN (Kaiser Health News) is an editorially independent, national program of KFF (Kaiser Family Foundation).

Keep close to you work friends, researchers say, for a long-term health boost : Shots

Keep close to you work friends, researchers say, for a long-term health boost : Shots
Relationships are the key to happiness and health, according to the longest running study on wellbeing. Here's advice from the study authors on how to build your relationship skills in the workplace.

The pandemic had a enormous impression on how we do the job, and our romantic relationship with our work opportunities. For several men and women who worked remotely for months (or continue to do), the dropped boundaries involving their do the job and individual life could have aided gas a increase in burnout.

Traits like “silent quitting” have taken off as numerous tried to pull back how significantly of by themselves they invested in their careers.

But if putting in added grueling hours at perform has lost its charm, investing in the other people that you operate with might be value a 2nd glimpse.

A person of the important variables that make for happier, healthier workers is how connected men and women truly feel with their colleagues, states Dr. Robert Waldinger, a professor of psychiatry at Harvard Medical College and director of the Harvard Study of Adult Improvement, one particular of the longest working experiments on what can make human beings prosper.

Waldinger explores the success of that analyze – and other experiments on the matter – in a new e-book, The Fantastic Lifetime, which he wrote with his colleague Marc Schulz. In it, the authors share results of the 85 several years of research adhering to people today from their teens in the course of their lives, evaluating components that guide to health and fitness and wellbeing.

The huge takeaway? “The folks who had the warmest connections with other persons weren’t just happier, they stayed healthier for a longer time, and they lived longer,” Waldinger claims. “We get little hits of properly-getting, if you will, from all types of interactions, from pals, spouse and children, function colleagues.”

When the analyze found that incredibly shut associations – intimate companions, siblings and pals – are vital, it also located that a entire spectrum of other relationships issue.

“All of that seems to affirm our [need for] belonging,” Waldinger claims. “That we are witnessed and recognized by many others, even the most informal call.”

And because a great deal of our waking lives are put in at get the job done, workplace bonds make a real big difference. Regretably, the deficiency of social relationship at function, is starting off to be recognized as a growing dilemma.

A modern Gallup poll located that only about a third – 32{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} – of personnel are engaged in their work, down from 36{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} in 2020. The study also discovered that the selection of actively disengaged workers has risen due to the fact the pandemic.

Yet another recent Gallup poll found that only 2 in 10 American workers say they have a “best mate at work” — which is an individual you can confide in about the own side of your lifetime. And for those underneath 35, that number dropped by a few share factors since 2019.

The 20{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} with a do the job bestie “were improved performers on the task,” Waldinger claims. “They were being substantially a lot less possible to depart their work for another a single due to the fact they had a buddy at do the job.”

And the Gallup poll also observed that possessing a near buddy at perform experienced become even more vital since the pandemic, and the increase in hybrid and distant work.

Exercising your social muscular tissues

So how can we build that perception of heat and link with your co-staff? Waldinger compares it to performing exercises often for bodily conditioning – you need to make a practice of it to experience the rewards.

He implies starting off with little techniques. For example, feel of a colleague you have not found in a though.

“You could mail them a text, or an electronic mail, or even call them on the telephone,” he implies, “and just say, ‘Hi! I was imagining of you, and wanted to hook up.'”

It really is one thing that requires scarcely 15 seconds, but those people steps usually deliver us very little doses of joy.

“A lot much more frequently than not, you will discover that one thing very favourable comes back,” he states. “What we know with strengthening your relationships is that quite small steps can guide to responses that will make you experience very good.”

And if you want to make new friends at function, Waldinger indicates leaning into your curiosity about your co-staff.

“So you could, for example, decide just to discover some thing about anyone else at work who you would like to get to know,” he says. “Recognize something they’re displaying on their desk that might be particular.”

And just ask them about it, he says.

“A single of the matters we know is that when we are curious about another person in a friendly way, it is really flattering and it engages people today in dialogue.”

These seemingly insignificant discussions can provide huge and ongoing gains to our wellbeing. In actuality, there’s investigation that reveals that modest chat, even with strangers, presents a strike of joy.

“We know that small talk has these added benefits of improving well-becoming,” states Waldinger.

But it wants to be practiced a lot, he adds.

“This is a little like a baseball game exactly where you never anticipate to hit the ball every time,” he says. “But if you consider this numerous periods, you will locate that much a lot more normally than not, you will get that constructive response to smaller communicate, to reaching out in some way.”

And these conversations can also pave the way to further discussions, and friendships.

Get out of your rut, specially if you’re remote

If you have been performing remotely, Waldinger advises coming in to work every now and then to interact with coworkers in particular person. “That practical experience of coming and observing your colleagues [will] give you this small upsurge of emotion, simply because you recognize you’ve got been deprived of that in-individual connection.”

Waldinger acknowledges all of this can be more challenging than, say, being at property and viewing Netflix.

You could have to force your self to go for satisfied hour with colleagues. “It is just a great deal much easier to do what is actually acquainted and controllable,” he states. Associations are fewer predictable.

But if you capture oneself experience that way, “discover the resistance, and then permit your self step in excess of it and get the motion. If you feel about carrying out it, do it and see what occurs.”

And he notes that it should not be up to individual staff members to do all the get the job done in forging bonds and connections at function. Leaders can do a great deal to foster a tradition of warmth and connection.

For instance, he suggests, they can deliberately create situations where individuals truly feel relaxed currently being susceptible, sharing one thing about their hobbies and life outside the house of work.

“You will need leaders to say getting personalized with each other is important, it matters, and it begins at the top rated,” he states. “When that transpires, the culture can shift in a firm exactly where people are likely to know every other far better, and then care about every other and care about the workplace.”

And that can go a extended way in creating a happier, additional engaged office.

Bringing Medicaid behind bars has wide bipartisan support : Shots

Bringing Medicaid behind bars has wide bipartisan support : Shots

When he was in prison, Lee Reed was in agonizing back pain. His doctors there told him he needed back surgery, but because he was so close to his release date, they said he’d have to get it done on the outside. Reed saw that surgery as his ticket to being able to get a job and effectively reenter society.

Amy Osborne for Tradeoffs


hide caption

toggle caption

Amy Osborne for Tradeoffs


When he was in prison, Lee Reed was in agonizing back pain. His doctors there told him he needed back surgery, but because he was so close to his release date, they said he’d have to get it done on the outside. Reed saw that surgery as his ticket to being able to get a job and effectively reenter society.

Amy Osborne for Tradeoffs

Lee Reed spent his first night after getting out of a state prison sleeping in the stairwell of a parking garage in downtown San Francisco.

Just a few days shy of his 62nd birthday, Reed had nowhere else to go. During his two decades in prison, his mom and wife had died, and he’d lost touch with most of his family.

“I had nothing. I had nobody,” Reed said.

But he wasn’t alone on that first night. He had the same companion he’d had for years: agonizing back pain.

“Imagine somebody standing on your foot, and you can’t stop that pain,” Reed said. “It’s going to be there when you wake up. It’s going to be there when you go to sleep. Half the time I never even got out of bed while I was in prison because I couldn’t stand up, it was so painful.”

Reed’s doctors in prison told him he needed back surgery, but because he was so close to his release date, they said he’d have to get it done on the outside. Reed saw that surgery as his ticket to being able to get a job and effectively reenter society.

But without health insurance or a support network, being able to do any kind of work seemed impossible as he laid down in the concrete stairwell, his prison-issued walker his only blanket.

“I was tired, and I was literally ready to give up,” Reed said.

Medicaid can be a bridge to a healthy life outside

Around 600,000 people leave prison in the U.S. every year, and another 10 million are released from county jails. Like Reed, many of them suffer from chronic physical, mental and substance use conditions. Research shows they are also at an extremely high risk of hospitalization and death; one study from Washington state found that recently incarcerated people were 12 times more likely to die in their first two weeks after release from prison than the general population.

That’s why in January, federal health officials for the first time signed off on having Medicaid pay for services for some people in state or local jails, prisons or juvenile facilities. The goal is to use the time before someone leaves a corrections facility to connect them with medical providers in the community and limit any disruption in their care as they transition out of incarceration.

Most people who are incarcerated are eligible for Medicaid based on their low income, but a provision known as the “inmate exclusion policy” prohibits federal Medicaid dollars from being spent on a person’s care while incarcerated. (The only exception is for an overnight hospital stay.) Many counties and states try to connect people to Medicaid as soon as they’re released, but it can be a bureaucratic nightmare, and even if it works, people often have other priorities like finding a job, food and a place to live.

Some states like Arizona require private Medicaid plans to connect with incarcerated people before they are released, which state officials say helps individuals get care more quickly when they get out. And small pilot programs in California and New Mexico showed offering care coordination before release led to more primary care visits, less recidivism and fewer ER trips. But the inmate exclusion policy remains a significant barrier.

In 2018, Congress directed federal health officials to help states figure out a better transition plan for people leaving incarceration. Since then, 15 states from across the political spectrum have asked the Centers for Medicare and Medicaid Services to let them test what would happen if they turned Medicaid on before people leave jail, prison and juvenile facilities. In January, California became the first state to get the green light.

“We hope that what we are approving today is an exciting model for what we are able to partner [on] with states across the country,” said Dan Tsai, deputy administrator and director of the Center for Medicaid and CHIP Services at CMS.

States are taking differing approaches

All of the proposals pending before CMS share a common goal: bridging care between incarceration and the community for the more than 10 million people who leave incarceration each year. Many policymakers also see this as a way to improve health equity — people of color are disproportionately incarcerated in the U.S.

In theory, getting people connected to care sooner and keeping them on their medications should improve health outcomes and, over time, help state Medicaid programs save money, because fewer people will end up needing expensive hospital and ER visits. But with limited previous experience to guide them, states are having to guess at the best way to use finite Medicaid dollars when it comes to who should receive these new benefits, what benefits they should receive and when those benefits should start.

“If you are providing and paying for the Medicaid services, you want to ensure that you are focused on those that truly need it,” said California Medicaid Director Jacey Cooper.

Most states, including California, would limit eligibility to incarcerated people with documented health needs, such as chronic physical and mental health conditions or substance use disorder. Cooper estimates around 70{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of people incarcerated in California meet this criteria.

In West Virginia and Kentucky, only people with a substance use disorder would be eligible, as part of those states’ broader efforts to address addiction. Research shows drug overdose is one of the most common ways people die after leaving prison, with studies suggesting returning prisoners are 40 to 129 times more likely to fatally overdose in their first two weeks after release.

Rhode Island, Vermont, Washington and Oregon would offer pre-release services to everyone in jail and prison who is eligible for Medicaid.

“The odds are so high that people in that situation are going to need the support that it didn’t seem to make sense to us to be trying to distinguish who did and who did not meet some threshold or have a particular condition,” said Amy Katzen, the director of policy and strategy for Rhode Island’s Medicaid program.

Rhode Island is one of four states — along with Massachusetts, Utah and Vermont — that would offer people soon to leave jails and state prisons the same Medicaid benefits as anyone else in the community.

“This is going to be so complicated to implement,” said Mike Levine, director of MassHealth, Massachusetts’ Medicaid program. “When we finally do, there’s something to be said for just if you are a MassHealth member, you’re getting the MassHealth benefit.”

The other 11 states would offer a more limited set of services for people in the weeks or months before they leave incarceration, focused on transitioning someone back into the community. Services would include connecting them to new doctors, making sure they can get their prescriptions filled and helping them find housing.

In most of these states’ proposals, services like addiction treatment and daily medications would continue to be provided and paid for by the jail or prison. However, Rahul Gupta, the director of the White House Office of National Drug Control Policy, said on Tuesday that states would be required at a minimum to provide mental health and drug treatment services in this pre-release period. CMS would not confirm Gupta’s statement and said the agency plans to release further guidance for states soon.

Some advocates believe Medicaid should take a larger role in health care during incarceration, pointing to numerous reports of inadequate and negligent health care behind bars.

“I’ve seen people wither away — literally, people who were 280 pounds solid, healthy-looking individuals, wither all the way down to skin and bones. And that was because something that they had was diagnosed late or was misdiagnosed in the beginning,” said Khalil Cumberbatch, who served 6½ years in a New York prison before becoming the director of strategic partnerships at the Council on Criminal Justice.

For now, states are unwilling to go that far. Most are asking for Medicaid to start paying for services 30 days before someone is released, but a few have asked for more, including California, which has been approved to start coverage 90 days pre-release. Medicaid Director Cooper said that’s a more realistic window to build a trusting clinical relationship with someone, get all their appointments set up and make sure they have everything they need before they’re released.

Medicaid experts suggested the quickest way for the other 14 states to win CMS approval may be to follow California’s lead on these questions, but they believe federal health officials might want to let states make different choices so they can gather more evidence about what works best.

Implementation challenges await

In California, the first incarcerated people won’t receive Medicaid services until April 2024, Cooper said, with full implementation expected to take until 2026. That’s in part due to the daunting task of integrating the health care and criminal justice systems. The state asked for and received $561 million from the federal government to help providers and correctional facilities build up the infrastructure to do things like share data and bill appropriately.

Massachusetts’ Mike Levine said his team has been working closely with law enforcement and corrections officials for years. “You can’t wait to engage correctional partners when it’s time to implement,” Levine said. “They have to be involved in the policy design because this is going to require so much change within their workflows and their daily business that they have to be at the table.”

Advocates insist that people who are incarcerated or formerly incarcerated need to be included in these conversations too. “If we want people to use that Medicaid card to engage in services in the community, we need to ask them, what is it you need? How can we support you best in coming home?” said Shira Shavit, a professor of family and community medicine at the University of California San Francisco and executive director of the Transitions Clinic Network, which specializes in caring for people post-incarceration.

Including those perspectives, Shavit said, could prevent unintended consequences, like people becoming less likely to engage with Medicaid because they see it as a part of a criminal justice system they don’t trust.

Help came late, but Reed has hope for the future

This entire conversation is coming too late for Lee Reed. No one reached out to him before he got out of prison. He spent two days sleeping in that parking garage stairwell before a security guard pointed him toward a nearby homeless shelter.

A few weeks later, a doctor at the shelter restarted Reed’s medications for diabetes and high blood pressure, and referred him to a specialist who scheduled his back surgery for early 2023 — more than six months after Reed had been released from prison.

Six months after he was released, Reed finally got his back surgery. He’s in less pain now, but he’s still homeless, jobless and struggling to find purpose in his life.

Amy Osborne for Tradeoffs


hide caption

toggle caption

Amy Osborne for Tradeoffs


Six months after he was released, Reed finally got his back surgery. He’s in less pain now, but he’s still homeless, jobless and struggling to find purpose in his life.

Amy Osborne for Tradeoffs

But his pain continued to get worse. The constant agony and Reed’s inability to support himself took a toll on his mental health, occasionally making him wonder if his life was worth living.

“Who would want to live this? This is horrible, man,” he said. “I can’t do anything to protect myself. I can’t do anything to feed myself. How the hell am I a man?”

The doctor at the shelter referred Reed to Shira Shavit’s Transitions program at the Southeast Family Health Center, a community clinic run by the San Francisco Department of Public Health. Shavit prescribed a medication patch for Reed’s back and scheduled follow-up appointments for his diabetes. The program also gave him a bag of groceries, a bus card and ordered him a winter coat.

“When people come out of prison, they have so many needs,” Shavit said. “[We’re] just trying to bring people to the starting line to kind of get them to where they need to be to then even start to be able to become successful in the community.”

Reed finally got his surgery at the end of January, the day after CMS approved California’s request to bring Medicaid behind bars. He’s in less pain now and dreams of moving back to Arkansas to spend time with his grandchildren.

But his challenges are far from over. He’s still living at the homeless shelter without a job and struggling to find purpose. He said if someone had reached out to him before he left prison and helped him get his surgery sooner, there’s a better chance he’d be supporting himself by now.

“I’m trying to keep a positive attitude on everything because my whole world feels like it’s falling apart,” he said a week after his surgery. “I have no control over my own life right now. I’m just like a child. I’m just helpless.”

This story comes from the health policy podcast Tradeoffs. Dan Gorenstein is Tradeoffs’ executive editor, and Ryan Levi is a reporter/producer for the show, where a version of this story first appeared.