What we’ve gained from the Affordable Care Act, 13 years later

Do you remember when some senior citizens had to ration their medications due to the fact their prescription drug expenses would triple each 12 months soon after they entered the Medicare protection gap identified as the “donut hole”? I do.

Do you recall when turning 19 intended getting kicked off your parents’ overall health insurance plan plan, regardless of your dwelling circumstance? I do.

Do you keep in mind when insurance policy firms could refuse to pay for preventive treatment options — vaccinations, mammograms, colonoscopies or a great number of other necessary products and services — for any motive, or maybe no purpose at all? I do.

Do you remember insurance plan corporations refusing coverage to pregnant females or many others with “preexisting conditions”? Or when they could cost you what they wished, for no matter what reason they wished, and you seriously had no selection but to accept that due to the fact there was no Patient’s Bill of Rights? I do.

But those times were being relegated to the dustbin of historical past on March 23, 2010, when President Obama signed the Economical Treatment Act (ACA) into regulation. Of class, as we mark the ACA’s 13th anniversary, it’s simple to ignore the political costs of that “miracle” laws. 

To start off with, it took a long time for Congress to draft and vote on the wellness treatment regulation. Then, the GOP built repealing the ACA its priority in the 2010 midterm elections. They demonized the law — labeled as “ObamaCare” — threw in a few of racist pet whistles and, with a nationwide disinformation campaign, rode a wave that received them back again manage of the Property of Associates and flipped 12 governor’s workplaces, together with Ohio, Pennsylvania, New Mexico and Michigan. This ushered in an era of obstructionism that described Congress for numerous decades.

In point, the GOP-managed Household voted a lot more than 50 times to repeal the ACA, disregarding the tens of hundreds of thousands of People in america who received health and fitness insurance coverage, and numerous others who have benefitted from the Patient’s Bill of Rights. Ironically, the one-minded devotion that won Republicans the Home greater part in 2010 would expense them that vast majority in 2018, adhering to a systematic schooling campaign that took the debate from abstract political philosophy to 1 centered on concrete truth.

A noted 13.6 million Individuals received insurance in 2021 by itself through that ACA marketplaces. Closing the prescription drug “donut hole” saved millions of Medicare recipients billions of bucks, and 2022 surveys by the Kaiser Family members Foundation and Morning Talk to uncovered that a bulk of Us citizens approve of the ACA. Staunch Republican opposition is shrinking.

It turns out that public feeling is even a lot more placing when you inquire people about distinct ACA provisions. For instance:

  • 90 per cent of People assist prohibiting wellbeing insurance policies companies from denying coverage for people today with preexisting problems
  • 89 per cent support demanding well being insurance coverage providers to deal with the cost for most preventive services
  • 88 {bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} aid prohibiting wellbeing insurance companies from denying protection to pregnant ladies
  • 87 per cent aid prohibiting wellbeing insurance coverage corporations from charging ill people today extra, and the very same share support providing states the alternative to increase Medicaid
  • 85 per cent assist providing economical enable to reduced- and average-cash flow People to buy coverage and
  • 78 per cent aid allowing younger grownups to keep on their parents’ insurance plan ideas until age 26.

Additional than 35 million Americans have well being insurance policies currently for the reason that of the ACA — guys, gals and young children who are benefiting from reduced charge and increased good quality wellbeing treatment coverage. They can thank the eyesight and bravery of leaders such as former Residence Speaker Nancy Pelosi (D-Calif.), former The vast majority Leader Steny Hoyer (D-Md.) and previous The vast majority Whip Jim Clyburn (D-S.C.), who socialized the concern and worked to safe the history-making votes in Congress.

These males and girls of conscience knew that “an ounce of avoidance is worthy of a pound of heal,” as the aged Ben Franklin declaring goes. They passed the most consequential overall health treatment legislation of my lifetime, proving that the age of heroes has not handed and that, in the words and phrases of Abraham Lincoln, our “government of the men and women, by the folks and for the people today shall not perish from the earth.”

Do you believe that in miracles? I do.

Antjuan Seawright is a Democratic political strategist, founder and CEO of Blueprint Strategy LLC, a CBS News political contributor, and a senior going to fellow at 3rd Way. Abide by him on Twitter @antjuansea.

Copyright 2023 Nexstar Media Inc. All rights reserved. This content may possibly not be published, broadcast, rewritten, or redistributed.

How to ensure social determinants of health actually improve health care

Presented 80 p.c of a person’s health is affected by non-healthcare variables, it is no surprise that the two overall health treatment companies and well being strategies are on the lookout for means to superior deal with the broader established of social and economic disorders that influence wellbeing. Emblematic of the ongoing shift from quantity to value, an escalating quantity of Medicaid-managed care contracts are requiring health plans to measure and handle the social determinants of overall health (SDoH), with the final objective of lowering well being disparities and escalating overall health and fitness. Although relocating in the suitable way, the means for wellbeing options to employ evidence-centered interventions to increase health and fitness fairness is significantly hampered by a absence of provider Z code utilization. If you can not measure it, you can’t handle it.

In 2016, diagnosis codes Z55-Z65 were launched to the healthcare coding system to permit vendors to report the presence of non-scientific factors that are recognised to affect well being results (this sort of as employment, housing, foodstuff insecurity, etcetera.). When properly documented, these Z codes are an powerful way for vendors and wellness strategies to coordinate care and to establish qualified group-centered interventions. Even so, uptake has been sluggish thanks to administrative load, a lack of benchmarks, a lack of service provider consciousness, as effectively as vendors remaining unwell-geared up to handle these wants.

Learning from Z code utilization

In Oct 2021, Centers for Medicare and Medicaid Companies (CMS) launched a report, which shown that Z codes are mostly unreported in Medicare rate-for-support promises. By 2019, homelessness was the most regularly used Z code, on the other hand Z codes have been only documented on .11 {bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of all promises.

We analyzed details by way of 2022 and observed that the use of Z codes throughout commercially insured, Medicare Edge and Medicaid populations carries on to stall. On a yearly basis, the proportion of individuals with a Z code ranges from .13 percent in 2017 to .15 per cent in 2019 and 2020. In major metropolitan parts, the proportion of sufferers with a Z code is as low as .03 p.c in Atlanta, Georgia to .17 percent in San Francisco, California.

Even with the present state of very low adoption, federal and state policy efforts go on to double down on the importance of improving upon documentation and measurement of social things, ranging from the Medicaid and CHIP Payment and Access Commission’s (MACPAC) most current recommendations to Congress, to Centers for Illness Management and Prevention’s (CDC) release of extra Z codes, which go into effect April 1, 2023. The exacerbation of well being inequities on full screen for the duration of the COVID-19 pandemic without doubt supports the rationale driving these coverage initiatives and the ongoing concentrate on enhanced measurement. Even so, policymakers keep on to overlook a significant place: Facilitating access does not guarantee adoption.

As we have witnessed numerous situations before (which include with COVID-19 telehealth growth), procedures that just make a thing obtainable, unbiased of how precious that company or item is, do not always translate to significant use or adoption. If utilization of Z Codes from 2017 to 2022 is only a tenth of a percent, what is to say that introducing more codes will increase adoption of current codes, let by yourself new codes? If the priority is to maximize measurement, and hence, provide additional qualified social care, then should not plan attempts be targeted on overcoming present barriers to use?

Driving Z code adoption

Very well-intentioned policies like The American Rescue Approach Act of 2021 involved efforts to deal with food and housing insecurity, these types of as developing a standard method to measuring and accumulating results linked to overall health equity. Having said that, equally federal and state procedures similar to this situation proceed to overlook the concentrate on — while delivering a course of action in which to obtain the intended consequence, they do not alter the system that sales opportunities to the wished-for behavior, which is greater documentation. Illustrating this disconnect, researchers have identified that even among the minority of providers that doc social needs via clinical notes, an even more compact share of all those providers are translating these notes into Z codes.

Many levers need to be pulled to meaningfully spur Z code adoption on a national stage. The aforementioned CMS report from 2021 acknowledges the absence of money incentives and providers’ perceived skill to handle SDOH-linked problems as remaining persistent limitations to greater adoption of Z coding in clinical practices.

Ultimately, screening for health and fitness-relevant social complications is essentially diverse from screening for healthcare issues, which raises the query: What policies are becoming carried out to present instruction for both equally the screening and “treatment” of SDoH? The option needs recognition of the truth that major care suppliers are at the “front lines” of wellness care and are progressively screening and dealing with patients for a lot more specialised disorders, like despair. In a well being financial state wherever supplier provide is currently substantially constrained, policymakers should consider the evolving (and at any time-expanding) responsibilities of companies and what that usually means for their capacity to get on added social screening tasks.

Policymakers will require to calibrate their investment in growing provider capability (which include social personnel) to fulfill the requires of populace-based mostly screening and documentation. Ultimately, as the health treatment industry has found with the adoption of other novel CMS steps, incentivizing the use of Z codes as a aspect of price-based mostly care arrangements may be the finest way to integrate them into a portion of day-to-day apply.

In the meantime, if the goal is to connect patients promptly and competently to social treatment methods, policymakers and payers can concentrate on non-personal steps to predict unique requires. Although not ideal, econometrics have demonstrated that Z codes are associated with a large Area Deprivation Index, and there is plenty of Zip Code-unique overall health treatment utilization, demographic and behavioral information now offered to use. If analyzed appropriately, the want for Z codes could develop into significantly less salient.

To make significant and lasting transform in well being equity, and, in turn, health outcomes, by improved coordination and connectivity in between social and professional medical care, CMS really should not simply make new prognosis codes, but thoughtfully incentivize the behaviors needed to make adoption.

Allison Oakes, Ph.D., is the director of exploration at health care analytics corporation Trilliant Wellness.

Sanjula Jain, Ph.D., is the senior vice president of market method and main exploration officer at Trilliant Health.

Copyright 2023 Nexstar Media Inc. All legal rights reserved. This content might not be published, broadcast, rewritten, or redistributed.

End of COVID public health emergency will bring changes to U.S. hospitals, nursing homes, addiction treatment and more

The Biden administration’s decision to end the COVID-19 public health emergency in May will institute sweeping changes across the health care system that go far beyond many people having to pay more for COVID tests.

In response to the pandemic, the federal government in 2020 suspended many of its rules on how care is delivered. That transformed essentially every corner of American health care — from hospitals and nursing homes to public health and treatment for people recovering from addiction.

Now, as the government prepares to reverse some of those steps, here’s a glimpse at ways patients will be affected:

Training rules for nursing home staff get stricter

The end of the emergency means nursing homes will have to meet higher standards for training workers.

Advocates for nursing home residents are eager to see the old, tougher training requirements reinstated, but the industry says that move could worsen staffing shortages plaguing facilities nationwide.

In the early days of the pandemic, to help nursing homes function under the virus’s onslaught, the federal government relaxed training requirements. The Centers for Medicare & Medicaid Services instituted a national policy saying nursing homes needn’t follow regulations requiring nurse aides to undergo at least 75 hours of state-approved training. Normally, a nursing home couldn’t employ aides for more than four months unless they met those requirements.

Last year, CMS decided the relaxed training rules would no longer apply nationwide, but states and facilities could ask for permission to be held to the lower standards. As of March, 17 states had such exemptions, according to CMS — Georgia, Indiana, Louisiana, Maryland, Massachusetts, Minnesota, Mississippi, New Jersey, New York, Oklahoma, Pennsylvania, Rhode Island, South Carolina, Tennessee, Texas, Vermont, and Washington — as did 356 individual nursing homes in Arizona, California, Delaware, Florida, Illinois, Iowa, Kansas, Kentucky, Michigan, Nebraska, New Hampshire, North Carolina, Ohio, Oregon, Virginia, Wisconsin, and Washington, D.C.

Nurse aides often provide the most direct and labor-intensive care for residents, including bathing and other hygiene-related tasks, feeding, monitoring vital signs, and keeping rooms clean. Research has shown that nursing homes with staffing instability maintain a lower quality of care.

Advocates for nursing home residents are pleased the training exceptions will end but fear that the quality of care could nevertheless deteriorate. That’s because CMS has signaled that, after the looser standards expire, some of the hours that nurse aides logged during the pandemic could count toward their 75 hours of required training. On-the-job experience, however, is not necessarily a sound substitute for the training workers missed, advocates argue.

Adequate training of aides is crucial so “they know what they’re doing before they provide care, for their own good as well as for the residents,” said Toby Edelman, a senior policy attorney for the Center for Medicare Advocacy.

The American Health Care Association, the largest nursing home lobbying group, released a December survey finding that roughly 4 in 5 facilities were dealing with moderate to high levels of staff shortages.

Treatment threatened for people recovering from addiction

A looming rollback of broader access to buprenorphine, an important medication for people in recovery from opioid addiction, is alarming patients and doctors.

During the public health emergency, the Drug Enforcement Administration said providers could prescribe certain controlled substances virtually or over the phone without first conducting an in-person medical evaluation. One of those drugs, buprenorphine, is an opioid that can prevent debilitating withdrawal symptoms for people trying to recover from addiction to other opioids. Research has shown using it more than halves the risk of overdose.

Amid a national epidemic of opioid addiction, if the expanded policy for buprenorphine ends, “thousands of people are going to die,” said Ryan Hampton, an activist who is in recovery.

The DEA in late February proposed regulations that would partly roll back the prescribing of controlled substances through telemedicine. A clinician could use telemedicine to order an initial 30-day supply of medications such as buprenorphine, Ambien, Valium, and Xanax, but patients would need an in-person evaluation to get a refill.

For another group of drugs, including Adderall, Ritalin, and oxycodone, the DEA proposal would institute tighter controls. Patients seeking those medications would need to see a doctor in person for an initial prescription.

David Herzberg, a historian of drugs at the University at Buffalo, said the DEA’s approach reflects a fundamental challenge in developing drug policy: meeting the needs of people who rely on a drug that can be abused without making that drug too readily available to others.

The DEA, he added, is “clearly seriously wrestling with this problem.”

Hospitals return to normal, somewhat

During the pandemic, CMS has tried to limit problems that could arise if there weren’t enough health care workers to treat patients — especially before there were COVID vaccines when workers were at greater risk of getting sick.

For example, CMS allowed hospitals to make broader use of nurse practitioners and physician assistants when caring for Medicare patients. And new physicians not yet credentialed to work at a particular hospital — for example, because governing bodies lacked time to conduct their reviews — could nonetheless practice there.

Other changes during the public health emergency were meant to shore up hospital capacity. Critical access hospitals, small hospitals located in rural areas, didn’t have to comply with federal rules for Medicare stating they were limited to 25 inpatient beds and patients’ stays could not exceed 96 hours, on average.

Once the emergency ends, those exceptions will disappear.

Hospitals are trying to persuade federal officials to maintain multiple COVID-era policies beyond the emergency or work with Congress to change the law.

Surveillance of infectious diseases splinters

The way state and local public health departments monitor the spread of disease will change after the emergency ends, because the Department of Health and Human Services won’t be able to require labs to report COVID testing data.

Without a uniform, federal requirement, how states and counties track the spread of the coronavirus will vary. In addition, though hospitals will still provide COVID data to the federal government, they may do so less frequently. 

Public health departments are still getting their arms around the scope of the changes, said Janet Hamilton, executive director of the Council of State and Territorial Epidemiologists.

In some ways, the end of the emergency provides public health officials an opportunity to rethink COVID surveillance. Compared with the pandemic’s early days, when at-home tests were unavailable and people relied heavily on labs to determine whether they were infected, testing data from labs now reveals less about how the virus is spreading.

Public health officials don’t think “getting all test results from all lab tests is potentially the right strategy anymore,” Hamilton said. Flu surveillance provides a potential alternative model: For influenza, public health departments seek test results from a sampling of labs.

“We’re still trying to work out what’s the best, consistent strategy. And I don’t think we have that yet,” Hamilton said.


KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

The Affordable Care Act has significantly reduced racial disparities in health care access, report says

The Affordable Care Act, passed in 2010 under former President Barack Obama, has expanded health insurance coverage across the U.S. and significantly reduced racial and ethnic disparities in access to health care, according to a new report by the Commonwealth Fund.

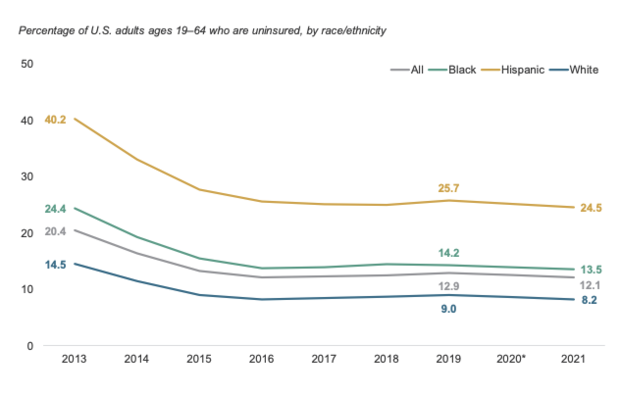
Percentage of U.S. adults ages 19–64 who are uninsured, by race/ethnicity
Coverage inequities between Black, Hispanic, and White adults have narrowed substantially since 2013. All groups reported improvements between 2019 and 2021.

The Commonwealth Fund


“Since its passage in 2010, the Affordable Care Act (ACA) has helped cut the U.S. uninsured rate nearly in half while significantly reducing racial and ethnic disparities in both insurance coverage and access to care — particularly in states that expanded their Medicaid programs,” reads the report.

Data shows that prior to the 2013 implementation of the Medicaid expansion — a provision of the ACA that made more families eligible for Medicaid coverage — 40.2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the Hispanic population, 24.4{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the Black population, and 14.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the White population were uninsured in America. However, by 2021, those numbers dropped significantly to 24.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, 13.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, and 8.2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, respectively.

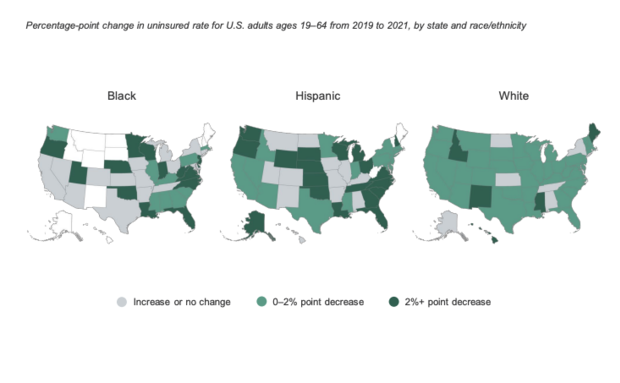
Percentage-point change in uninsured rate for U.S. adults ages 19–64 from 2019 to 2021, by state and race/ethnicity
Uninsured rates for Black and Hispanic adults improved considerably in several states between 2019 and 2021, while White adults experienced modest gains in most regions. 

The Commonwealth Fund


With more than 5 million people gaining coverage between 2020 and 2022 over the course of the pandemic, the overall uninsured rate in the U.S. dropped to just 8{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, a historic low, according to the report.

The report highlights specific ACA successes, including improved coverage rates for Black, Hispanic and White adults.

“The coverage gap between Black and White adults dropped from 9.9 to 5.3 percentage points, while the gap between Hispanic and White adults dropped from 25.7 to 16.3 points,” according to the the study. 

Additionally, the report found that adult uninsured rates for Black, Hispanic, and White people all improved during the first two years of the pandemic across all states — whether they had expanded their Medicare coverage or not —  and that Black and Hispanic adults experienced larger gains in insurance coverage than their White counterparts between from 2019 to 2021.

New report shows Medicaid expansion narrowed racial disparities in health insurance

Medicaid enlargement has not only diminished the in general variety of folks in the U.S. without having wellbeing insurance policies — it has also narrowed racial gaps in wellness insurance protection.

According to a new report from The Commonwealth Fund, well being coverage coverage for Black, Hispanic/Latino, and white older people enhanced amongst 2013 to 2021. Furthermore, the protection gap among Black and white grown ups and involving Hispanic/Latino and white older people shrank.

In 2013, in advance of Medicaid growth went into influence, 40.2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the Hispanic/Latino inhabitants, 24.4{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the Black inhabitants, and 14.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the white populace ended up uninsured. By 2021, these quantities fell to 24.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, 13.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, and 8.2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, respectively.

“A whole lot of the progress in uninsured premiums going down and these disparities narrowing [is] certainly stemming from the Inexpensive Treatment Act protection expansions,” Jesse Baumgartner, co-author of the report and senior investigation associate at The Commonwealth Fund, instructed Yahoo Finance. “Those took impact in 2014. So you see major drops concerning 2013 and 2016 as the market subsidies arrived on line, [and] a large amount of states expanded their Medicaid systems at that time. So that is of course a enormous driver for that progress then.”

Growth vs. non-growth

Medicaid was expanded in 2013 via the Inexpensive Treatment Act (ACA) — commonly known as Obamacare. The provision will allow homes whose profits falls below 138{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the federal poverty degree to grow to be suitable for Medicaid.

Following a Supreme Court ruling, nevertheless, it was left up to each and every condition to make your mind up no matter whether or not to adopt the expansion. As of March 2023, 39 states and the District of Columbia have expanded Medicaid.

According to the Commonwealth Fund report, amongst 2013 to 2021, states that adopted the Medicaid enlargement noticed greater fees of coverage coverage and wellbeing care accessibility than non-enlargement states. They also saw smaller disparities between racial and ethnic groups.

When just about every racial and ethnic team has designed significant strides in well being care protection given that 2013, the get in health treatment coverage for the Hispanic/Latino inhabitants has been specifically noteworthy: Its uninsured rate shrunk by 15.7 share factors concerning 2013 to 2021, the most of any demographic.

“There have been huge gains,” Baumgartner said, despite difficulties stemming from fewer entry to employer-sponsored insurance policy and regulations connected to immigration position that impression Medicaid eligibility.

Still, the Hispanic/Latino population has the maximum uninsured charge in the U.S., which Baumgartner claimed is “a substantial remaining inequity” and a person that “needs the most do the job shifting ahead.”

‘A apparent, huge threat to the development that’s been made’

As of October 2022, additional than 91 million Individuals had been enrolled in Medicaid and the Kid’s Overall health Insurance policy System (CHIP).

There ended up significant enhancements between 2019 to 2021, which Baumgartner attributed to federal policy steps taken in response to the coronavirus pandemic, particularly the Families Initial Coronavirus Reaction Act and American Rescue Strategy.

“What the info in this report indicates is that the federal coverage steps through the pandemic… designed a large influence in not only halting protection losses but in fact ensuing in some gains of protection for all of individuals teams through that time,” he claimed.

The Families First Coronavirus Response Act, which was signed into legislation in March 2020, allotted $3.5 trillion in funding for factors like coronavirus tests, diet expert services, and the General public Wellbeing and Social Providers Crisis Fund.

The American Rescue Strategy, passed a year afterwards, expanded the eligibility for ACA subsidies and amplified the sum of money support for those people presently eligible for the ACA. These subsidies have been prolonged right up until 2025.

“The details in this article truly speaks to the impression of those expanded subsidies and how they’ve built protection far more cost-effective,” Baumgartner explained. “Moving ahead, the issues we believe policymakers ought to continue to keep in brain is the extension of that earlier 2025 as unquestionably a different choice that this data highlights.”

Beginning on March 31, on the other hand, a provision of the federal coverage reaction to the pandemic — constant Medicaid enrollment — might occur to an conclude, removing health care coverage for millions of People.

In accordance to the Kaiser Household Foundation, “states that acknowledge the improved federal funding can resume disenrollments commencing in April but must meet up with sure reporting and other requirements for the duration of the unwinding course of action.”

That could affect some of the modern development on insurance coverage coverage, particularly for Black and Latino family members.

Among 2019 and 2021, uninsured costs for Black adults dropped by at the very least two share factors in 14 states, although fees for Hispanic/Latino adults fell by the identical total in 19 states, according to the Commonwealth Fund report.

“The even larger question is: What can states and the federal authorities do to lessen coverage decline and swap individuals who will inevitably be moved off Medicaid?” Baumgartner stated. “It’s a clear, massive chance to the progress that is been created simply because clearly these insurance policies, and the continual enrollment policies, in certain, feel to have had a really big affect.”

New report shows Medicaid expansion narrowed racial disparities in health insurance

Previous President Obama waves as he comes to provide remarks on the Very affordable Care Act and Medicaid at the White Dwelling on April 5, 2022. (Photo by MANDEL NGAN/AFP)

Until finally that distinct problem can be tackled, Baumgartner stated federal policymakers really should aim on developing a federal fallback choice for non-enlargement states.

“The problem gets to be: How are states heading to be equipped to get persons onto other coverage, to go them above to market coverage that they may possibly be qualified for, to seriously decrease the disruption and preserve the progress going and not have a backsliding?” he stated. “That’s the authentic vital.”

—

Adriana Belmonte is a reporter and editor covering politics and health treatment plan for Yahoo Finance. You can follow her on Twitter @adrianambells and arrive at her at adriana@yahoofinance.com.

Simply click here for politics news connected to business and dollars

Read the most up-to-date money and business enterprise information from Yahoo Finance

Less staff, longer delays and fewer options: Rural America confronts a health care crisis

More than 40,000 graduating medical students learned Friday where they will spend the next three to seven years of their medical training.

With the United States grappling with a simultaneous shortage of primary care physicians and a rural health care crisis, many of the graduating students are set to enter the front lines of the country’s health care shortage.

At least 136 rural hospitals and health systems closed between 2010 and 2021, and over 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of rural hospitals operate with negative profit margins. Despite billions of dollars in investment in health care, hospitals throughout the United States face the possibility of shutting down.

“I would say it is probably the worst time for health care that we ever experienced,” Joanne Conroy, the chief executive officer and president of Dartmouth Health, told ABC News. She noted that increased costs, inflation, limited housing, and workforce shortages have made running rural hospitals more challenging.

Less staff, longer delays and fewer options: Rural America confronts a health care crisis

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“We know what to do if we face another pandemic,” Conroy said. “The question is whether or not we have the financial resilience in order to survive it.”

Many hospitals that remain open have cut costs to survive, offering fewer services and beds.

In 2020, 47{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of rural community hospitals did not provide obstetric services, with 89 obstetric units closing between 2015 and 2019. Seven million women reside in counties with limited or no access to maternity care, impacting half a million newborns annually.

According to Conroy, patients can already feel the impact of the crisis, noting that some women in New Hampshire need to drive two hours to deliver their babies. Other effects include fewer available beds in emergency rooms, delays for elective surgery and longer wait times for prescriptions or ambulance pickups.

For new medical professionals entering their residency, especially those joining rural systems, the circumstances of the struggling health systems are out of their control.

PHOTO: Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“It is not my job to fix all of the problems for an entire community, that’s impossible. When you feel like that’s your responsibility, burnout is basically inevitable,” said Katie Stevenson, a Tufts medical student. “When you feel like your goal is to do the best you can with the resources you have, you are able to right-size your expectations a bit.”

An increasing number of students are entering medical school programs that focus on rural medicine. In 2019, the Health Resources and Services Administration issued grants to create 32 newly accredited rural residency programs, supplementing the preexisting programs.

This year, Tufts School of Medicine will graduate its tenth class of students from its Maine Track MD program – a partnership with Maine Medical Center that allows students to pursue a community-based curriculum and gain financial incentives to encourage primary-care specialties.

STOCK PHOTO: A teacher gestures as she lectures a class of college students.

A teacher gestures as she lectures a class of college students.

STOCK PHOTO/Getty Images

Graduating roughly 40 students annually, 27{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of Maine Track students have been matched to programs in Maine and 47{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} have been matched into primary care programs, according to Dena Whitesell, an assistant dean for students at Tufts and psychiatrist at Maine Medical Center.

“We know that students and residents who live in an area [and] who train in an area are more likely to practice in that area in the future,” Whitesell said.

Liv Fauver, a Tufts student who matched with a University of Vermont residency program, grew up in rural New Hampshire and said she felt motivated to work in a similar community where she could positively impact the local residents.

“I think for me, my goal is to live and work in the community that I serve,” she said. “So I’m really in a place where I go home or go to the grocery store and see my patients all the time, because that’s the world that I live in and work in.”

While rural hospitals have closed in record numbers, PCPs – medical professionals who patients regularly use for checkups and other routine care – face additional challenges, especially in rural areas, according to experts.

Greg Sawin, a PCP who has practiced in Massachusetts and Maine as well as Duke University School of Medicine professor, said he worries that the goals of primary and long-term preventative care can sometimes be at odds with larger health care systems.

“We get paid to do things to people. We don’t get paid to keep populations healthy,” he said.

Moreover, he believes the costs associated with medical schools – including the high cost, the likelihood of incurring debt and substantially higher pay to pursue competitive specialties like orthopedic surgery or dermatology, for example – disincentivize primary care options like family or internal medicine.

PHOTO: Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“It can be very appealing to want to go into a specialty where you’re guaranteed to make more money and pay that debt off more easily,” Stevenson said.

Owen Foster lives in rural Vermont and has felt the impact of the decreased number of available PCPs, spending six months to book an appointment with a doctor. Living in a rural area, Foster shares his dilemma with millions of Americans in rural areas impacted by the shortage of PCPs.

“You need basic things at certain intervals in your life,” he told ABC News. “If you don’t have a primary care provider, you can’t get that and you can’t get the referrals you need, so it’s really, really difficult.”

What makes Foster’s experience unique is his position as the state of Vermont’s top health care regulator. As chair of Vermont’s Green Mountain Care Board, he oversees the quality and cost of the state’s health care system.

Learning about the shortage of primary-care physicians in Vermont, Foster decided to use the opportunity to find a PCP as a chance to examine the market as a “secret shopper.”

PHOTO: Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“What I found was I was completely incapable of getting a doctor,” he said. “I called eight places and the best I got was on an indefinite wait list, which never came to fruition.”

Rural areas comprise about two-thirds of the primary care health professional shortage areas nationwide, even though only 20{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of Americans live in rural areas.

The problem is also likely to worsen over time. Projections indicate that the United States will likely suffer a shortage of between 17,800 and 48,000 PCPs by 2034.

Moreover, health care professionals believe that the shortage of PCPs can make other elements of health care more expensive and worsen overall patient outcomes. Sawin gave the example of a person getting strep throat. Without a PCP, the person might go to a local hospital emergency room, which is significantly more expensive than other treatment options.

“In terms of mismatch of resources, you know, a kid with strep throat showing up in the ER is like cutting butter with a chainsaw,” Sawin said.

Foster added that primary care providers are “critical to controlling the costs of a health care system” due to their role in the early identification of issues, their ability to diagnose mental health issues, and their approach to preventative medicine.

According to Foster, PCPs in rural areas, however, struggle to find and retain staff, negotiate with insurance companies and prevent burnout. The shortage of PCPs, combined with the increased health care needs of the older population in rural areas, creates a concerning combination.

STOCK PHOTO: A group of medical students discussing some work while huddled around a whiteboard at the lab together.

A group of medical students discussing some work while huddled around a whiteboard at the lab together.

STOCK PHOTO/Getty Images

Despite these issues, Foster said he was optimistic about some approaches to make primary care more financially feasible, including adding a floor for PCP spending within health plans and government involvement in rate setting.

A new generation of students graduating from rural track programs also has the potential to reverse the tide of the PCP shortage in rural areas, with 571 additional primary care matches this year. Stevenson, for example, matched with the Swedish Cherry Hill rural program in Washington state.

“I think we have an opportunity in this country to do a much better job of taking care of our patients if we do a better job of funding primary care and preventative care and creating healthy environments,” Stevenson said.