The Meals and Drug Administration on Wednesday authorized an in excess of-the-counter edition of the opioid overdose reversal drug naloxone, a transfer which is anticipated to improve accessibility to the lifesaving treatment.
Up until finally now, naloxone — bought by drugmaker Emergent BioSolutions under the manufacturer title Narcan — has been offered in the United States only as a prescription drug, nevertheless a lot of states have developed workarounds that let individuals to get it specifically from pharmacists. It can also frequently be found at group centers, area health and fitness departments and needle trade courses.
Creating the drug accessible more than the counter could save far more life, mentioned Dr. Scott Hadland, a pediatrician and an habit professional at MassGeneral Clinic for Small children in Boston.
“Narcan can conserve a life in minutes, which is significant,” he explained.
The around-the-counter Narcan, which will be bought as a one dose specified as a nasal spray, most probable will not be available right up until the late summer months, according to the business. Fda officers have stated that when authorised, it could be sold in spots such as convenience merchants, grocery retailers and even vending equipment.
“Today’s acceptance of OTC naloxone nasal spray will help increase obtain to naloxone, maximize the selection of places the place it’s accessible and help cut down opioid overdose deaths all through the place,” Food and drug administration Commissioner Dr. Robert Califf stated in a assertion.
Wednesday’s acceptance came a minimal more than a month following an advisory committee to the Food and drug administration unanimously recommended that the company make it possible for Emergent’s drug to be bought around the counter.
Drug overdoses — the major result in of accidental deaths in the U.S. — killed more than 107,000 folks in 2021, according to the Centers for Disease Control and Avoidance. Extra than 80,000 of people deaths involved opioids.
Hadland stated he’s noticed an uptick in adolescents and youthful adults overdosing.
Most overdose fatalities among the youthful people today manifest at home, he claimed, usually when there is another person close by who can respond.
“Yet most youthful people today who overdose under no circumstances obtain Narcan and are pulseless by the time EMS comes,” he reported. “Making it offered over the counter will present a new avenue of access, specially for youthful individuals and families who haven’t been the targets of our prevalent initiatives to distribute Narcan across the place,”
The above-the-counter model of naloxone will be packaged in a more substantial box with photographs and comprehensive recommendations to aid men and women administer the drug additional simply, in accordance to the enterprise.
Dr. Michael Barnett, an assistant professor of health plan and management at the Harvard T.H. Chan College of Public Health and fitness, reported that when building naloxone accessible in excess of the counter is a “huge phase,” he worries about how a lot it will price.
“My hope is that the price is affordable,” he said.
Emergent declined to share facts on how a great deal the around-the-counter medicine will expense, but the normal value of a two-dose box of prescription-only Narcan is around $130, in accordance to GoodRx, which tracks drug selling prices.
The Biden administration’s decision to end the COVID-19 public health emergency in May will institute sweeping changes across the health care system that go far beyond many people having to pay more for COVID tests.
In response to the pandemic, the federal government in 2020 suspended many of its rules on how care is delivered. That transformed essentially every corner of American health care — from hospitals and nursing homes to public health and treatment for people recovering from addiction.
Now, as the government prepares to reverse some of those steps, here’s a glimpse at ways patients will be affected:
Training rules for nursing home staff get stricter
The end of the emergency means nursing homes will have to meet higher standards for training workers.
Advocates for nursing home residents are eager to see the old, tougher training requirements reinstated, but the industry says that move could worsen staffing shortages plaguing facilities nationwide.
In the early days of the pandemic, to help nursing homes function under the virus’s onslaught, the federal government relaxed training requirements. The Centers for Medicare & Medicaid Services instituted a national policy saying nursing homes needn’t follow regulations requiring nurse aides to undergo at least 75 hours of state-approved training. Normally, a nursing home couldn’t employ aides for more than four months unless they met those requirements.
Last year, CMS decided the relaxed training rules would no longer apply nationwide, but states and facilities could ask for permission to be held to the lower standards. As of March, 17 states had such exemptions, according to CMS — Georgia, Indiana, Louisiana, Maryland, Massachusetts, Minnesota, Mississippi, New Jersey, New York, Oklahoma, Pennsylvania, Rhode Island, South Carolina, Tennessee, Texas, Vermont, and Washington — as did 356 individual nursing homes in Arizona, California, Delaware, Florida, Illinois, Iowa, Kansas, Kentucky, Michigan, Nebraska, New Hampshire, North Carolina, Ohio, Oregon, Virginia, Wisconsin, and Washington, D.C.
Nurse aides often provide the most direct and labor-intensive care for residents, including bathing and other hygiene-related tasks, feeding, monitoring vital signs, and keeping rooms clean. Research has shown that nursing homes with staffing instability maintain a lower quality of care.
Advocates for nursing home residents are pleased the training exceptions will end but fear that the quality of care could nevertheless deteriorate. That’s because CMS has signaled that, after the looser standards expire, some of the hours that nurse aides logged during the pandemic could count toward their 75 hours of required training. On-the-job experience, however, is not necessarily a sound substitute for the training workers missed, advocates argue.
Adequate training of aides is crucial so “they know what they’re doing before they provide care, for their own good as well as for the residents,” said Toby Edelman, a senior policy attorney for the Center for Medicare Advocacy.
The American Health Care Association, the largest nursing home lobbying group, released a December survey finding that roughly 4 in 5 facilities were dealing with moderate to high levels of staff shortages.
Treatment threatened for people recovering from addiction
A looming rollback of broader access to buprenorphine, an important medication for people in recovery from opioid addiction, is alarming patients and doctors.
During the public health emergency, the Drug Enforcement Administration said providers could prescribe certain controlled substances virtually or over the phone without first conducting an in-person medical evaluation. One of those drugs, buprenorphine, is an opioid that can prevent debilitating withdrawal symptoms for people trying to recover from addiction to other opioids. Research has shown using it more than halves the risk of overdose.
Amid a national epidemic of opioid addiction, if the expanded policy for buprenorphine ends, “thousands of people are going to die,” said Ryan Hampton, an activist who is in recovery.
The DEA in late February proposed regulations that would partly roll back the prescribing of controlled substances through telemedicine. A clinician could use telemedicine to order an initial 30-day supply of medications such as buprenorphine, Ambien, Valium, and Xanax, but patients would need an in-person evaluation to get a refill.
For another group of drugs, including Adderall, Ritalin, and oxycodone, the DEA proposal would institute tighter controls. Patients seeking those medications would need to see a doctor in person for an initial prescription.
David Herzberg, a historian of drugs at the University at Buffalo, said the DEA’s approach reflects a fundamental challenge in developing drug policy: meeting the needs of people who rely on a drug that can be abused without making that drug too readily available to others.
The DEA, he added, is “clearly seriously wrestling with this problem.”
Hospitals return to normal, somewhat
During the pandemic, CMS has tried to limit problems that could arise if there weren’t enough health care workers to treat patients — especially before there were COVID vaccines when workers were at greater risk of getting sick.
For example, CMS allowed hospitals to make broader use of nurse practitioners and physician assistants when caring for Medicare patients. And new physicians not yet credentialed to work at a particular hospital — for example, because governing bodies lacked time to conduct their reviews — could nonetheless practice there.
Other changes during the public health emergency were meant to shore up hospital capacity. Critical access hospitals, small hospitals located in rural areas, didn’t have to comply with federal rules for Medicare stating they were limited to 25 inpatient beds and patients’ stays could not exceed 96 hours, on average.
Once the emergency ends, those exceptions will disappear.
Hospitals are trying to persuade federal officials to maintain multiple COVID-era policies beyond the emergency or work with Congress to change the law.
Surveillance of infectious diseases splinters
The way state and local public health departments monitor the spread of disease will change after the emergency ends, because the Department of Health and Human Services won’t be able to require labs to report COVID testing data.
Without a uniform, federal requirement, how states and counties track the spread of the coronavirus will vary. In addition, though hospitals will still provide COVID data to the federal government, they may do so less frequently.
Public health departments are still getting their arms around the scope of the changes, said Janet Hamilton, executive director of the Council of State and Territorial Epidemiologists.
In some ways, the end of the emergency provides public health officials an opportunity to rethink COVID surveillance. Compared with the pandemic’s early days, when at-home tests were unavailable and people relied heavily on labs to determine whether they were infected, testing data from labs now reveals less about how the virus is spreading.
Public health officials don’t think “getting all test results from all lab tests is potentially the right strategy anymore,” Hamilton said. Flu surveillance provides a potential alternative model: For influenza, public health departments seek test results from a sampling of labs.
“We’re still trying to work out what’s the best, consistent strategy. And I don’t think we have that yet,” Hamilton said.
KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.
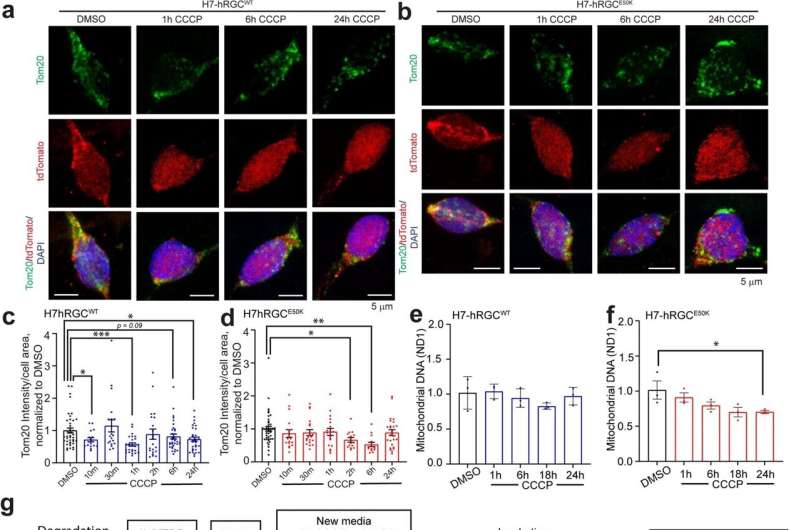
hRGCs maintain mitochondrial mass by simultaneous degradation and biogenesis of mitochondria under damage. a, b Representative confocal immunofluorescence images of H7-hRGCs against mitochondrial Tom20, tdTomato, and DAPI after indicated 10 μM CCCP treatment timepoints. Scale bars are 5 μm. c, d Quantification of Tom20 intensity per cell area from sum projections of confocal z-stacks, normalized to corresponding DMSO. n = 14–42 cells per condition. e, f Mitochondrial DNA copy number analyzed by qPCR for mitochondrial ND1 gene relative to nuclear RNase P. Results shown as ΔΔCt fold changes relative to DMSO control for different times points of 10 μM CCCP treatment. n = 3, 3 technical repeats averaged for each biological repeat. g Schematic of MTDR flow experiments for tracking degrading versus newly synthesized mitochondria. h Mitochondrial mass in single cells at different CCCP (10 μM) treatment time points for degradation or m different timepoints post CCCP (10 μM) wash for biogenesis were measured by flow cytometer, and the average fluorescence intensity normalized to DMSO was plotted. n = 3. i, k Representative western blot images of LC3B and actin from i hRGCWT and k hRGCE50K treated with CCCP (10 μM) for the indicated timepoints. j, l Quantification of the ratio of LC3B-II to corresponding LC3B-I for each condition. n = 3. ٭p-value < 0.05, ٭٭p-value < 0.01, ٭٭٭p-value < 0.001, ٭٭٭٭p-value < 0.0001. Unpaired student’s t-test between independent datasets. Error bars are SEM. Credit: Communications Biology (2023). DOI: 10.1038/s42003-023-04576-w
Indiana University School of Medicine researchers have identified a new therapeutic target that could lead to more effective treatment of glaucoma.
Glaucoma is a neurodegenerative disease that causes vision loss and blindness due to a damaged optic nerve. More than 200,000 people are affected by glaucoma in the United States each year. Unfortunately, there is currently no treatment. In a newly published paper in Communications Biology, researchers found neurons use mitochondria for a steady source of energy, and restoring mitochondrial homeostasis in the diseased neurons can protect the optic nerve cells from being damaged.
“Age-related neurodegenerative disease, which includes glaucoma, Parkinson’s disease, and amyotrophic lateral sclerosis (ALS), is the biggest global health problem,” said Arupratan Das, Ph.D., assistant professor of ophthalmology and principal investigator of the study.
“The fundamental mechanisms that we discovered can be used to protect neurons in glaucoma and be tested for the other diseases. We have identified a critical step of complex mitochondrial homeostasis process, which rejuvenates the dying neuron, similar to giving a lifeline to a dying person.”
The research team, led by Michelle Surma and Kavitha Anbarasu from the Department of Ophthalmology, used induced pluripotent stem cells (iPSCs) from patients with and without glaucoma as well as clustered regularly interspaced short palindromic repeats (CRISPR) engineered human embryonic stem cells with glaucoma mutation.
Using stem cell differentiated retinal ganglion cells (hRGCs) of the optic nerve, electron microscopy and metabolic analysis, researchers identified glaucomatous retinal ganglion cells suffer mitochondrial deficiency with more metabolic burden on each mitochondrion. This leads to mitochondrial damage and degeneration. Mitochondria are the tube like structures in cells which produce adenosine triphosphate, cell’s energy source.
However, the process could be reversed by enhancing mitochondrial biogenesis by a pharmacological agent. The team showed retinal ganglion cells are highly efficient in degrading bad mitochondria, but at the same time producing more to maintain homeostasis.
“Finding that retinal ganglion cells with glaucoma produce more adenosine triphosphate even with less mitochondria was astonishing,” Das said. “However, when triggered to produce more mitochondria, the adenosine triphosphate production load was distributed among more mitochondrion which restored the organelle physiology. It is similar to a situation where a heavy stone is carried by fewer people versus a greater number of people—each person will have less pain and injury, just like each mitochondrion will have less difficulty and damage.”
In the future, Das would like to test if these mechanisms protect the optic nerve in animal models under injury before testing in humans to hopefully lead to new clinical interventions.
More information:
Michelle Surma et al, Enhanced mitochondrial biogenesis promotes neuroprotection in human pluripotent stem cell derived retinal ganglion cells, Communications Biology (2023). DOI: 10.1038/s42003-023-04576-w
Provided by
Indiana University School of Medicine
Citation:
Researchers discover therapeutic target to aid in glaucoma treatment (2023, March 10)
retrieved 11 March 2023
from https://medicalxpress.com/news/2023-03-therapeutic-aid-glaucoma-treatment.html
This document is subject to copyright. Apart from any fair dealing for the purpose of private study or research, no
part may be reproduced without the written permission. The content is provided for information purposes only.
In June 2021, 32-year-old Alyssa Maness was diagnosed with POTS, a nervous system disorder that her doctors believe was triggered by Covid.
POTS, or postural orthostatic tachycardia syndrome, caused numbness throughout her arms and legs, a pins-and-needles sensation and sudden drops in her heart rate.
Because her heart problems didn’t go away, in early 2022 her doctors began conducting a series of lab tests in an attempt to better understand her long Covid symptoms.
When Maness submitted the testing to her insurance — Anthem Blue Cross — the provider deemed the testing medically unnecessary and declined to cover the cost. She’s now on the hook for the medical bills, which have already cost her more than $10,000 out of pocket.
“I’m kind of at the point sadly where I’ve just given up,” said Maness, a Ph.D. student in Sacramento, California. Many of her insurance appeals have been denied. “I don’t have the mental bandwidth to even battle this anymore, because it’s become clear that it is most likely going to be unsuccessful.”
Maness is among several long Covid patients in the United States interviewed by NBC News who say their insurance providers are declining to provide coverage related to their illness.
Alyssa Maness.Courtesy Alyssa Maness
But there are likely many more. Up to 4 million full-time workers are out of the labor force due to long Covid, according to research from the Brookings Institution, a Washington-based think tank.
NBC News has asked insurance providers for comment.
For some, the care they need to manage their chronic illness has left them in medical debt, which can easily balloon into the thousands or even tens of thousands of dollars, experts say. It’s unclear how many are being denied coverage, but a paperpublished in May in JAMA Health Forum estimated that the individual medical costs of long Covid could come to roughly $9,000 a year.
Part of the problem, experts say, is the ambiguity of long Covid symptoms, which can range from extreme fatigue to loss of taste and smell to debilitating heart palpitations. There’s no official test to diagnose the condition, nor is there any specific recommended treatment. That makes it more difficult for doctors to come up with a proper treatment.
Before they pay, insurance companies often want to know if the treatment is proven to work.
Long Covid patients can fight the denied claims through appeals or going to court — a time-consuming and draining approach for any patient, let alone those who may suffer from fatigue and brain fog, said Michele Johnson, the executive director of the Tennessee Justice Center, a legal aid group that has helped long Covid patients get health coverage.
“They’re trying to keep their job or keep caring for their family,” she said, “and there’s so much bureaucracy and red tape that they’re just drowning in it.”
‘Medical necessity’
Experts say insurance companies will often deny claims for care related to long Covid because they don’t see it as a “medical necessity.”
The termis what insurance companies use to assess whether they should approve or deny a claim, said Linda Bergthold, a former health policy researcher at Stanford University’s Center for Health Policy.
The term has been thrown around by insurance companies for decades, but it wasn’t given a formal framework until the late 1990s, which Bergthold helped develop.
In order for the care a patient receives to be deemed medically necessary by an insurance provider, there has to be substantial research or evidence that shows that it works, she said.
That’s “a key issue for long Covid,” she said, because the illness is so new and still poorly understood.
“Research, just like everything with Covid, is all new,” she said. “Nobody really quite knows what works and nobody really understands why some people have it longer than others.”
To be sure, as of 2021, there are diagnostic codes for long Covid — key tools used by doctors to characterize medical diagnoses for insurance coverage, said Dr. Alan Kwan, a cardiologist at Cedars-Sinai Medical Center in Los Angeles. Those codes, however, don’t always cover the myriad health problems linked to long Covid, he said.
POTS, for example, does not have a standardized diagnostic code and has only recently been linked to Covid.
Doctors may work hard to get a patient a formal diagnosis for long Covid to help with insurance, though there isn’t an official test for long Covid and the testing that is done may not be covered by insurance.
Some patients may eventually get coverage after submitting an appeal to their insurance, but usually not before shelling out hundreds of dollars, Kwan said.
Others may not be so lucky and may be forced to pay for most of their care out of pocket.
That’s what happened to Amy Cook, 51, of Orange County, California.
Amy Cook.Courtesy Amy Cook
In May, she got Covid, which caused her multiple long-term health problems including chest congestion, erratic heart rate, headaches and visual impairment.
Cook, who works a full-time job as a chief operating officer for a consulting agency, said she was bedbound for four months because of her long Covid symptoms.
Around October, her doctor recommended that she try naltrexone, a drug used for opioid addiction that has shown promise in lifting long Covid symptoms, as well as hyperbaric oxygen. Both therapies are being tested in clinical trials as potential treatments for the condition, though neither is approved by the Food and Drug Administration for the illness.
Aetna, her insurance provider, declined to cover most of the cost of the treatments.
“I’m at $28,000 to date and I have more treatments coming up,” Cook said of her out-of-pocket expenses.
Cook said she’s currently in a financial position to be able to self-fund the treatments, although she still hasn’t recovered from her illness and the expenses could easily grow.
“I don’t know when I’ll be able to stop,” she said.
In a statement, Alex Kepnes, a spokesperson for Aetna, said there is no single definition for long Covid and that coverage decisions “are based on medical necessity and evidence-based guidelines.”
“We are focused and committed to providing our members with access to care and treatments for medically necessary services to help them address their conditions and improve their health,” he said.
What can be done?
Johnson, of the Tennessee Justice Center, said a patient can improve their chances of insurance approving their claim by making sure they have a plan before they even enter the doctor’s office.
Her guidance:
Ask how much the care will cost.
Ask the doctor to explain clearly on insurance paperwork exactly why the care was needed.
Working with a doctor can be “very effective,” Johnson said, as they are usually trained to know what meets insurance providers’ standards for coverage.
“The idea that you could deny services without an opportunity for appeal is no longer true,” she said.
If still unsuccessful at this point, patients may begin to panic, Johnson said, because the outstanding bill can be taken to collections and patients can take a hit on their credit score. Providers often provide a very short time window for payment, and appeals often take months.
Maness, of California, said she’s panicked at least once when her insurance provider took too long to get back to her on an appeal and ended up shelling out hundreds of dollars toward her bill.
What a patient does after that will depend on their health insurance, Johnson said.
People with Medicaid, for example, can take the claim to court if they feel the denial was unjustified. For people on private insurance, it’s less clear what they can do, but one option is to contact the state’s Department of Commerce and Insurance, which regulates insurance companies.
Johnson suggested patients frame their complaint saying, “You’ve licensed this insurance to do this in our state and they’re denying essential benefits consistently.”
With a sizable federal grant, UNC hospitals will soon be a selected procedure centre for clients with extremely infectious disorders in the location.
UNC and Emory University are the only two Regional Rising Distinctive Pathogen Treatment Facilities in the Southeast. There are 13 remedy centers in the United States after the U.S. Department of Wellbeing and Human Solutions appointed 3 new centers, such as UNC, past month.
The heart will be operate by Dr. William Fischer and Dr. David Wohl, who the two research infectious ailments at the UNC University of Medication.
UNC-Chapel Hill Medical practitioners David Wohl, left, and William Fischer II at the clinic in Monrovia, Liberia. They were being amongst the infectious disease medical practitioners who answered the World Wellbeing Organization’s get in touch with to react to ebola in Africa. COURTESY OF DAVID WOHL
Wohl mentioned grants to build these remedy centers arrived out of the realization that infectious conditions like COVID-19, ebola and monkeypox could pop up extra often thanks to world wide local weather modify.
“There was a realization that this could materialize in the foreseeable future with this or other pathogens,” he explained.
New infectious condition emergencies could be specifically likely in North Carolina. The point out has a significant military and migrant populace who travel from overseas, where new pathogens have traditionally emerged, Wohl said. There are also a number of big interstate highways that carry likely pathogen-carrying men and women through the point out.
“You put all these items alongside one another — as we did in this application — to make a case that essentially this could be a spot the place one thing like this could be simply detected,” Wohl said.
With a $3 million grant from the federal govt, the centre will train and teach personnel at UNC Hospitals, other hospitals, and clinics throughout the Southeast how to take care of an infectious illness unexpected emergency.
That instruction incorporates drills outlining the basics of recognizing infectious conditions, how to adequately don and doff PPE, and how to thoroughly notify health and fitness officers of a circumstance.
Teddy Rosenbluth addresses science and health care for The News & Observer in a posture funded by Duke Health and fitness and the Burroughs Wellcome Fund. The N&O maintains comprehensive editorial control of the function.
Connected tales from Raleigh News & Observer
Teddy Rosenbluth handles science for The Information & Observer in a position funded by Duke Wellness and the Burroughs Wellcome Fund. She has coated science and health treatment for Los Angeles Magazine, the Santa Monica Day by day Press, and the Harmony Keep track of. Her investigative reporting has introduced her almost everywhere from the streets of Los Angeles to the hospitals of New Delhi. She graduated from UCLA with a bachelor’s diploma in psychobiology.