Navigating the complexities of mobile medical app development from idea to launch, a guide for clinicians and biomedical researchers | BMC Medicine

Misconceptions in mobile medical app development

Despite the advances in medical technology and the increased availability of mobile app solutions in medicine, there are major misconceptions among clinicians involved in building a mobile app (Fig. 1).

Fig. 1
figure 1

Common misconceptions of medical mobile app development

Misconception #1—the investigator fully understands the problem they are trying to solve and the users they intend to help

Reality

Before the development process can start, the competitive landscape should be assessed to confirm that there is not already an identical or similar goal solution. Next, the intended users must be interviewed to ensure that the solution solves a relevant problem for them. This user research should be incorporated throughout the development process to assure that the users are continually being considered. An effective team must also be formed with the required expertise to handle every phase of the development lifecycle, from clinical problem identification, user research, design, development, and product release. Finally, a strategy must be developed to market the product so that users discover and adopt the app.

Misconception #2—app development does not require much effort

Reality

Reality

A common phrase we hear among our clinical colleagues when we are approached with an idea for a mobile medical solution is “…and I’d like to build an app.” This statement can be interpreted as, “I would like to hire a contractor to turn my idea into an app.” This line of reasoning underestimates the investigator commitment required to turn an idea into a mobile app. Throughout the development process, the investigator must play an active role in the development team. This process frequently takes months of user research, design, development, and testing in an iterative fashion.

Misconception #3—the app should easily integrate into the electronic health records (EHR) system

Reality

The electronic medical records in the USA and many countries are highly fragmented, with individual hospital systems using their own 3rd party vendors to manage their records [11, 12]. Accessing a single institution’s EHR requires multiple levels of approvals at the principal investigator and administrative levels and then requires significant technical collaboration with the institution’s information technology department to connect. While Fast Healthcare Interoperability Resources (FHIR) standard has been adopted to facilitate a consistent format of healthcare information for simple transmission and sharing of data, the lack of a consistent EHR framework significantly impacts the ability of a 3rd party app to integrate into the EHR’s of a geographically diverse user base [13].

Misconception #4—app development is a single-step “one and done” process

Reality

The development process is not complete when the app is launched. A continuity plan must be in place to maintain and update the app throughout its lifecycle. Technology changes rapidly, operating systems update, and smartphone manufacturers develop and release multiple new phone models annually. An app must be maintained to adapt to these advancements. The request to “build an app” does not accurately convey that app development is a process that does not end with an app launch.

These misconceptions underscore a clear need for a liaison between clinicians and the app development community to facilitate the development of robust, maintainable, mobile apps. To address these misconceptions, we set up an academic sub-unit within the Georgia Clinical and Translational Science Alliance (Georgia CTSA), which we call the AppHatchery, with the goal of supporting clinical investigators in their endeavors to create and clinically translate their mobile medical app ideas. Care was taken to structure the AppHatchery to enable this end goal, with a mix of relevant expertise and experience. This initiative is led by a physician scientist who runs a laboratory that has a proven track record of developing and publishing medical apps as well as conducting clinical research using apps. We hired a product manager from the industry with expertise in managing mobile app development teams for a large organization. We have a designer on the team who specializes in user research and design thinking. Finally, we have multiple full-time developers to carry out mobile development work. We structured the group this way to ensure that we had members of the team with expertise in each phase of medical app development, specifically (1) clinical research expertise, (2) design, and (3) mobile app development. Given these diverse skillsets with every team member having some exposure to both clinical science and app development, we have created the perfect team to bridge the skillset gap between clinicians and software developers and develop mobile medical apps. Furthermore, the existence of team members fully dedicated to this initiative allows us to maintain continuity throughout each stage of the project at hand.

We first rely on internal marketing for project solicitations. When a project is onboarded, we perform a multi-disciplinary research process where we identify and explore the clinical and practical need for the given solution and its place within the current regulatory landscape and market. We use a combination of design thinking (DT) and human-centered design (HCD) framework to tackle app development challenges [14] from ideation through delivery. The design research process begins by conducting a deep dive into the problem as it pertains to end users and key stakeholders. Target users are interviewed to better understand their challenges, and we identify and/or verify the important features and aspects of the proposed app and get feedback on the design requirements that our research has identified. Simultaneously, we begin working with the principal investigator (PI) to craft the research study that will determine the efficacy of the tool we develop. Next, we begin the app development process, beginning with the design of wireframes and culminating with software development, where we conduct user research throughout the process to iteratively improve the app. We finally transition to launch and support, where we work with the principal investigator to release the app and support the clinical validation study. In this manuscript, we will describe the lessons learned from our journey and make recommendations for how other medical app developers should operate to successfully develop and translate clinical app ideas.

App development principles and structure

Design approach

What makes our approach to building digital tools unique in the clinical space is our emphasis on both DT and HCD (Fig. 2). We use DT to focus on understanding who the users are, uncovering their needs, and empathizing with their situation first before kicking off the product design and development process [15]. In addition, we strategically consider user needs in relation to clinical objectives to form design recommendations [16, 17]. We then kick off the development phase which incorporates HCD fundamentals, bringing the end user’s voice and opinions into the development process. Collaborative strategies are noted as vital to sustaining growth in mobile health applications [18]. HCD has been demonstrated to be an effective innovation tool in the digital clinical and health space where a focus on end users (patients, clinicians, or others) during the design process improves adoption rates [19,20,21] as well as patient engagement and satisfaction [22].

Fig. 2
figure 2

Design thinking framework

A recent narrative review of 82 health innovation papers mentioning HCD found most (70{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}) discussed using an HCD approach and all included a focus on users’ needs and the participatory and iterative nature of the design process [14]. More salient limitations to the HCD approach include sampling bias and small sample size as users must opt into the research to participate in the design process and are not necessarily the profile of users who may need the app the most. This may lead to a misalignment of the design with the intended user’s needs. Finally, few apps have been tested in randomized controlled trials, and so limited evidence is available on the long-term benefits of app products arising from HCD approaches [23]. Specifically, in using HCD, there are instances where the approach did not lead to significant improvement in the intervention outcomes. For example, Gallagher et al. conducted a study using a game-based app that was co-designed to improve cardiovascular risk factors and lifestyle behaviors and found no improvement after the intervention [24]. Similarly, Haque et al. evaluated a user-centered mHealth app in promoting physical activity and found very low compliance at the end of the study which limits the generalizability of the results [25]. Furthermore, alternatives to DT and HCD such as user experience (UX) design frequently focus on the way users interact with apps and strive to provide the most convenient use for the people who actually use the app, rather than the ideal users that HCD and DT strive for [26]. In light of these findings, it is important to note that HCD methodology allows for subjectivity in terms of which aspects of user experience to prioritize, which can result in varied outcomes. Additionally, as previously discussed in the literature, HCD is susceptible to sampling bias, which can impact the apparent effectiveness of an intervention. Thus, it is crucial to consider both the strengths, limitations, and alternatives to DT and HCD and to employ a multi-disciplinary approach that considers various perspectives and factors in the design and evaluation process. This design strategy accurately defines the user, their needs, the problem most important to solve for that user, how those needs intersect with research goals, and which design directions are most effective at maintaining engagement and delivering results. It provides the foundation for the team who then focuses on the users and their needs throughout the app project development process.

Building a team

A development team must be created to begin the development process. A software development team has three distinct yet overlapping roles, the product manager, the designer, and the developer. In addition to these key roles, multiple supporting roles may be created for handling regulatory requirements necessary in medical app development.

Product manager

The product manager is responsible for the overall strategy of the mobile app. This includes the macro strategy of why and how to build the app in the first place as well as a more detailed strategy about which features to build, what order to build these features, and how to measure if the features are a success. The product manager is also responsible for creating the requirements in sufficient detail so the remainder of the team can execute their jobs effectively. These might be technical requirements, design requirements, or requirements from the clinical team. The product manager is also responsible for the lifecycle of the mobile app. This includes releasing the app through testing platforms, releasing the app publicly, working through approval processes at the institution, and maintaining the app’s public information on the app stores.

The product manager is responsible for ensuring the app meets guidelines. This is important especially for medical apps that may need to comply with the Health Insurance Portability and Accountability Act of 1996 (HIPAA) [27]. In our experience, projects are hindered at the beginning stages by focusing on these compliance issues instead of focusing on the core value of the mobile app. Compliance needs to be addressed at the beginning of a project when architecture is being designed and before the app is released publicly to ensure it meets all the required standards for privacy and security. The product manager is responsible for analytics and measuring the mobile app experience. These analytics are tied to the goals and objectives of the app (e.g., reducing missed follow-up visits) but also user experience metrics such as app crashes, screen views, and user interactions.

Software developer

The developer is responsible for writing the software code that will control the mobile app. This role is critical as there will be no software created without team members who can code the mobile app.

Designer

The designer is the empathizer in chief; it is their responsibility to always be the voice of the user throughout the app development process. This is a critical role as academic medical apps are often conceived without direct consultation of patients or users.

Other team roles

Developing mobile apps within an academic medical center requires knowledge of how Institutional Review Boards (IRB) review requests to conduct clinical research. It is useful to have an IRB expert on the team to answer nuanced questions about data collection and privacy that may differ from IRB to IRB and can be unique to clinical research involving mobile apps. While not critical in the early clinical research phases, it can be useful to have a regulatory expert on the team who is familiar with the relevant regulation, specifically around HIPAA and managing protected health information (PHI).

Full time vs part-time staff

Many academic medical centers operate on a shared time model where the staff dedicate a portion of their time to projects. While this can work, we have found it is better to have full-time staff dedicated to the development of mobile apps. Likewise, many software development projects are outsourced to other groups. While this can work, we have found it is best to work cohesively as a team throughout the development process to streamline communication and align expectations throughout.

Applying the app development process

Competitive and regulatory landscape survey and literature review

Before accepting any new project, it is important to meet with the PI to understand their clinical and application vision before conducting an extensive search of the major app stores to see what similar apps currently exist, as well as related platforms, tools, books, and/or educational materials in the space. After the search is completed, the list of these competing resources should then be presented to the PI to discuss how or if the value proposition of their idea merits the effort to build a homegrown solution. If the concept meets the acceptance criteria set by the team (i.e., is novel, addresses a real need, and the development team has capacity and knowledge), the project can proceed (Fig. 3).

Fig. 3
figure 3

App project development process

When researching and deciding the intended use case of the app, research into the regulatory pathway required to market the product must be conducted. In the United States of America (USA), the US Food and Drug Administration (FDA) approves medical devices for sale in the US market. FDA guidance regarding software as a medical device (which includes medical apps) is governed specifically by the 21st Century Cures Act [28]. Section 3060 of this legislation defines what software the FDA considers to be a medical device that requires regulatory approval via the 510(k) premarket notification pathway, versus lifestyle tools that can immediately enter the market [28]. Ultimately, the distinction is determined based on the function and intended use of the software. Software becomes a medical device when the intention and function are to diagnose, cure, treat, prevent, or mitigate a specific disease or condition [28].

Should the app require premarket notification, multiple steps must be taken to satisfy the complex risk management strategies and regulatory requirements set by the FDA to release the app publicly. Rigorous clinical testing must be conducted to ensure that the device performance (1) is in line with the claimed performance and use case and (2) is similar in performance to the most analogous device currently approved and on the market (the claimed predicate device that must be identified for FDA submission). In addition to performance, the app must apply appropriate human factors and usability engineering processes, which must be assessed in standalone usability studies with at least 15 users in the desired user population [29]. Finally, a quality management system (QMS) must be in place to ensure that procedures and processes enable a reliable, safe, and effective software tool [30]. The QMS begins with the leadership and management plan to ensure that relevant stakeholders manage the medical app throughout its lifecycle. The support plans for the system must also be defined, with appropriate documentation of all development and design, disaster recovery plans, and processes for regularly updating the app for performance, usability, cybersecurity, and technology modernization. The implementation must be then considered, with regular validation, cybersecurity monitoring, and maintenance of all key infrastructure, to ensure that end users can interact with a stable version of the medical app throughout the duration of its lifecycle as a medical device.

Design strategy

Once engaged on a project, a development team should schedule a design strategy session with the investigator and project team to gain a full understanding of the desired goal of the app from the perspective of all stakeholders (Fig. 4). While investigators often have a passionate idea about what problem they wish to solve with their app, additional examination can help dial into precisely who will use their tool and what problems their app user(s) seek to solve. To prepare for this session, which is usually 1–2 h, the team conducts secondary research from published academic papers, review articles, and meta-analyses to familiarize themselves with the outcome goals of the project and specific aims of the research. The team generates clarifying questions for the investigator and research team to respond to. Sample questions may include the following:

  • Who will use this app? Is the patient or a family member the primary user?

  • What benefit will the user get out of using this app?

  • What data (if any) do you expect the app to collect?

Fig. 4
figure 4

Collaborative design strategy discussions set the parameters of the project. Left: a design strategy session in person. Right: results of a design strategy session using an online collaboration tool like Miro

Post-It notes or a collaborative whiteboard digital tool such as Miro (Miro, Inc., San Francisco, CA) may be used to capture ideas that can be sorted and prioritized as seen in the image below. This allows the team to gather insights from the session to form a user research approach to test assumptions, write and vet a discussion guide, and then recruit 5–15 individuals from the intended user group to interview. Insights across all interviews are pooled together and sorted to surface themes and areas of importance for the user. As the themes and key features emerge from the insights, the team can refine the insights into design recommendations.

App design

Once the research team has a clear idea of the needs and wants of the users, designs for the app should be created (Fig. 5). It is very important that these designs come from actual user insights, rather than from pre-conceptions the research team had prior to beginning the work, unless these pre-conceptions had been validated by the user research.

Fig. 5
figure 5

From sketches to wireframes. Left: pictures of preliminary sketches of the layout of the application. Right: functional (clickable) wireframes of an app

Given the number of apps that exist already, it is worth spending some effort looking to find similar apps that incorporate design patterns that could be implemented in the app. This is a separate step from the competitive analysis where rather than looking at apps that perform a similar function, you are looking for individual features (i.e., how search functions, how do other apps offer content layout).

Taking from the design recommendations generated in the prior phase. The designer can begin creating low-fidelity sketches, which they can turn into generalized flows and wireframes of the app (Fig. 5, left). The key is the use of wireframing and prototyping as an early way to evaluate whether the tool being created meets users’ expectations. To evaluate those wireframes, standard usability testing techniques can be used such as remote or in-person unmoderated observation sessions or task-based evaluations where the user is given tasks within the app to accomplish.

App development

The most common app development methodologies are the waterfall and agile methods [31]. The agile methodology is an iterative approach that leverages frequent releases that provide incremental functionality improvements that can be tested and refined in the production environment. The waterfall methodology completes the holistic build which then moves into a testing phase and then a launch phase, yielding a polished product. We prefer to utilize the agile methodology as the iterative development process enables more testing and feedback, which matches our design philosophy.

When an app development methodology has been selected, there are 2 major mobile app development frameworks: natively on each of the major operating system software tools (iOS or Android), or cross-platform (i.e., using React Native (Meta Platforms Inc., Menlo Park, CA), Flutter (Google LLC, Mountain View, CA), etc.) which supports one code base for both iOS and Android platforms (Table 1). The decision on what to use will largely depend on the expertise of the available developers in the team. This is the fundamental choice an app developer must make before developing an app.

Table 1 Overview of the development styles and platforms available

Native development has the advantages of dedicated functions and features specific to the hardware you are developing for (iOS vs Android), with the downside that effort must be duplicated to support both iOS and Android devices. Also, native development tends to be more well-maintained, as it is linked directly to the mobile devices operating system. This skillset is also much more readily available in the software developer talent pool. While cross-platform development is typically much faster and more efficient with respect to developer resources, it also relies on a much smaller developer community. Furthermore, many 3rd party tools common in app development (e.g., analytics, advertisements) have limited support for cross-platform development. The development framework should be chosen to suit the needs of the specific project.

Throughout the development process, it is generally good practice to beta test the app to ensure that what is being built is meeting the user’s expectations. To do this, it is best to test in a controlled environment to monitor who is using your app. To do this you will use either TestFlight for iOS (Apple In., Cupertino, CA) or Google Play Store Internal Testing for Android (Google LLC, Mountain View, CA).

Launch

Once the app is launched, it must be closely monitored for bugs, unforeseen issues for users, and ever-increasing software versions. Both iOS and Android release beta versions of the updates in advance of a public release so that developers have a chance to test the compatibility of their apps against these updates. Nevertheless, there are many apps that are no longer supported by new OS versions that plague the app stores, a situation that should certainly be avoided by a medical app developer! Some thought should be put towards maintaining support for the users that may not have updated to newer operating system (OS) versions. It is typical to set a supported version that dates back at least a few years to give users time to upgrade their devices.

Updates and maintenance

Finally, app maintenance must be considered. Funds must be allocated to support the continuity of the app development project before it begins. As described by Siegel et al. [10], there are a multitude of unsupported apps on the app stores that are born out of research projects and then abandoned, likely due to the lack of personnel to support them, lack of funds, or poor design and execution leading to a lack of traction to justify a larger time/monetary investment.

Simultaneously with the design thinking process, it is important to work with the PI to help design a research study and secure IRB approval for the study protocol that will be used to clinically validate the app upon release. This validation study typically occurs in 2 phases: Phase 1 is focused on usability and feasibility. In this phase, user feedback of the app is collected and used to iteratively improve the app. This can be done by identifying users to enroll in the clinical study and conducting a rolling enrollment process where a version of the app is developed and given to the users to collect their feedback, adjust the app, and then repeat. Phase 2 is a clinical trial where the app’s performance is analyzed in terms of a clinical endpoint. In this phase, a randomly controlled trial should be planned to assess the app in terms of a clinical endpoint of interest, i.e., a control (no app) and test (has the app). These results can then be published in a medical journal to provide credibility to the app as a medical tool.

Lessons learned: roadblocks, pivots, and best practices

App development costs

Funding for academic biomedical mobile apps can be difficult in our experience. The most common source of funding is through traditional National Institutes of Health (NIH) grants. These grants allow for setting aside resources in the budget to support mobile app development but do have some pitfalls. First, grants typically have a very long application and funding cycle, in the order of 12–18 months, which can delay a project. Second, funding amounts set aside for development tend to be small. In our experience, this has been $10,000–25,000 which is insufficient for the necessary costs associated with designing and developing an application (Tables 2 and 3). Beyond grants, academic medical centers often offer access to other seed or startup funds in the form of innovation awards, local organizations that offer awards or seed funds, and, as a last resort, projects can be funded through department funds if the funds and scope of the project are aligned.

Table 2 Personnel costs for mobile app development
Table 3 App development cost breakdown by stage

Staffing an academic medical center app development project is very different from a commercial software development project. The key differences are (1) the budget of the project is typically far lower (by an order of magnitude, typically), (2) the goal of the app is often non-commercial (e.g., it does not have a business model attached), and (3) the goals of the PI may include education and training for the full team, beyond only executing on the creation of the software. Therefore, staffing for mobile app projects will use a mix of resources available within academic medical centers and their affiliates. These include graduate or undergraduate students who may work on a project for free as part of a classroom learning experience, students who are hired outright or work through graduate research assistant positions, shared staff with other programs (e.g., bioinformatics), and partnership with other campus-based groups who are funded to support clinical research.

Managing investigator expectations

We often encounter requests that are in essence to “just build an app” from clinical PIs. It is important to diagnose this way of thinking early as it could reveal the propensity of a PI to disengage from the project prematurely, as it becomes clear the amount of effort and collaboration it takes to foster a successful partnership. PIs must be engaged often and richly with the team. The cadence of meetings will be project dependent, but we have found a weekly update, whether a meeting or email, maintain project members active and engaged.

Having a disengaged PI can lead to multiple points where the project can fail: (1) the problem is not defined appropriately, (2) the appropriate user research is not conducted (which can lead to the app not addressing all relevant user needs thus impacting adoption and use), and (3) usability/feasibility testing is not conducted in a robust and iterative fashion (which can lead to usability issues that will prevent users from adopting the app, even if the app has a strong value proposition that could significantly improve the life of the user). In addition, it taxes the rest of the team who must make clinical research decisions and navigate an unfamiliar research structure.

Understanding the users

It can be challenging to identify and access users to solicit feedback from. Clinician investigators typically have frequent interactions with the target user population. They have familiarity and a relationship built already (which is how the ideas for projects usually originate). However, they usually lack the time to conduct thorough user research that goes beyond the problem discovery. On the other hand, developers and designers do have the time and knowledge to conduct user research, albeit they lack access to patients. Bridging this gap, often by facilitating access to clinics and hospitals for the design team, can drastically improve a project’s chance of success. In one of our projects with Grady Memorial Hospital, we established a cadence of going to the hospital twice a week to enroll new subjects and check in on existing subjects. Furthermore, fostering a relationship with the clinical care teams of the subjects facilitates subject enrollment, a process that is much slower when only investigators are involved in subject recruitment. Additionally, by fostering that relationship with the clinical care of the subjects, it is possible to conduct user research with stakeholders through observation sessions and contextual inquiry. Which can help mitigate some of the overreliance on user input [32].

Beta testing recruitment

Recruitment can take place in person or virtually. Online recruitment tends to require less apparent overhead (although depending on the clinic setting it may be hard to capture patients online) while in-person recruitment has a higher overhead but tends to yield more numbers and more upfront engagement. Most of the recruitment that we have done has taken place in person at the hospital. Interestingly, we have found that subjects recruited in a clinical setting will remember everything about the app and the study until they leave the hospital/clinic, when study participation significantly wanes. To increase the chances of success, you must find the best method to follow up with your subject/users which could be via email, text, or phone calls so that you can maintain engagement with your study. This will be very study specific and dependent on the app you build. This is one area where sampling bias can impact the project as subjects who are more interested are more likely to respond and be engaged. That was our experience with that project, and we had very low compliance from the users we were trying to target, those who leave the hospital and do not return.

Beta testing process

Testing an app with users frequently is crucial to ensure the best possible version of the app is developed. In an in-patient setting, we have found it necessary to introduce users to the app in one session, and then follow up within a week, to see if the patient interacted with the app after the visit. There are multiple steps that can be taken to foster engagement:

  1. a.

    Delay the follow-up: A week might not be enough time for the user to have a need to open the app.

  2. b.

    Include push notifications: This system allows researchers to send messages through the app to specific segments of the study group (i.e., users who have not opened the app recently).

The goal of beta testing is to find encounter any bugs and errors and more importantly if the intended user audience finds the app useful. It is very challenging to design a research study surrounding a tool that will fit into a user’s life outside of the study. This is because study coordinators are actively looking for subjects to enroll, creating unnatural motivators to utilize the tool (i.e., participate in research, monetary compensation, curiosity), as opposed to an organic app search where users are looking for something. Thus, it is important to design an app such that the app fills a clearly defined and currently unmet need for a group of people (i.e., a medical reference guide, an appointment booking system, a prescribed training program). Otherwise, you run the risk of aiming to change a given behavior which has been identified as a limitation of traditional HCD and follows a different design process [32].

Furthermore, mobile apps have standardized evaluation frameworks such as the System Usability Scale (SUS) which provide a quantitative evaluation of the usability of a software tool. Note the difference between usability: Can somebody use the app without encountering errors that worsen their experience, and feasibility? Does the app effectively cover an unmet need for a user? Usability is an easier metric to quantify, and mobile apps for research should follow industry standards to validate the tools created are usable. These frameworks can be employed to glean valuable feedback during the beta testing process.

Cleveland Clinic Gets Its Own IBM Quantum Processor For Advanced Biomedical Research

This appears to be the year that IBM’s Quantum Computing program reaches the tipping point. IBM and the Cleveland Clinic Foundation just announced the first deployment of an onsite, private sector, IBM-managed quantum computer in the United States. However, beyond the placement of a 127-qubit IBM Eagle quantum processor in a cafeteria at Cleveland Clinic’s main campus, this announcement signals a major leap forward for quantum computing applications.

Of course, the most immediate question is, why install a quantum computer in a cafeteria? Although this may seem like a frivolous question, it gets to a major point of this article. The IBM Eagle class quantum processor has been installed in a highly visible location in the Cleveland Clinic so that biomedical researchers and physicians can start thinking about the most productive ways to use this resource. These are very early days for the development of quantum computing applications, so installing the IBM Eagle quantum processor in the cafeteria, visited daily by nearly everyone working at the Cleveland Clinic, seems like an extremely creative way of keeping the machine ever present in the minds of people working at the facility.

Dr Lara Jehi, who became Cleveland Clinic’s first Chief Research Information Officer in 2020, said that there are many areas of interest in medical research with computational ceilings that block further advances. Quantum processing may help break through those ceilings. Researchers at Cleveland Clinic, working with IBM data scientists, combed through the possible avenues for research, discipline by discipline, to identify the projects most likely to bear fruit when matched to quantum processing’s current capabilities. “Quantum is still a nascent technology,” said Jehi.

Jehi divides the current quantum-based biomedical research into two broad groups: quantum chemistry (drug discovery) and quantum machine learning (ML). The quantum chemistry projects focus on finding new drugs or new purposes for existing drugs. These projects are staggeringly complex due to the sheer size of the data sets that need processing. The core tasks in these projects are simulating cell site binding by the candidate drug molecules. These problems have a very large number of dimensions, and quantum processing is known to be extremely well suited to these sorts of problems.

Current quantum chemistry research projects at Cleveland Clinic include:

  • Identifying protein targets by mapping the complex interplay of proteins and solving the foundational challenge of form-changing protein surfaces in structural biology.
  • Accelerating the prediction of molecular docking between drug candidates and proteins.
  • Exploring protein-drug interactions and protein ligand binding through quantum chemistry algorithms to accelerate drug discovery.

Quantum-assisted ML, an extension of classical artificial intelligence (AI) techniques, seeks to find ways to simplify massive data sets, which consist of patient data from cohorts as large as 150,000 patients, by winnowing the features or dimensions of the data sets that are important to a specific research problem from the features or dimensions that are not important. Current quantum ML research projects at Cleveland Clinic include:

  • Developing a quantum-based physician scheduling algorithm that efficiently and most effectively takes advantage of a physician’s time, expertise, and resources.
  • Exploring the assembly of large genomes through preliminary benchmarking studies to develop a foundational technology for discovery and translation of natural products.
  • Creating optimized radiation therapy treatment plans for individual patients based on patient data.
  • Developing a deeper understanding of cardiovascular risk for non-cardiac surgery patients using perioperative morbidity and mortality data to improve clinical and patient outcomes.
  • Developing optimized clinical trials with accelerated timelines while reducing the number of trial participants and associated costs.

Cleveland Clinic has additional quantum chemistry and quantum ML research projects in the planning stage. “It’s not just about quantum processing being faster; it’s about doing what has been impossible” said Jehi.

IBM currently has six quantum computing centers located around the globe. The quantum processor installation at Cleveland Clinic is the first to be exclusively devoted to biomedical and healthcare research, which is the focus of one of four IBM quantum processing working groups. The other three quantum processing working groups are focused on high-energy physics, high-performance computing (HPC), and finance. IBM is partnering with different companies and institutions for each of these quantum processing working groups.

Aparna Prabhakar, Vice President, IBM Quantum Partner & Alliances, says that IBM has been partnering with Cleveland Clinic for a while now. According to Prabhakar, the goal of the 10-year Cleveland Clinic-IBM Discovery Accelerator partnership, which was announced in 2021, is two-fold. One goal is to identify real-world problems that may benefit from quantum processing. The second goal is to find ways to make the unique abilities of quantum processing available to researchers working in various disciplines without requiring them to understand the underlying quantum technology.

These working groups and partnerships help IBM develop the quantum-based programming tools that data scientists and researchers need to attack many challenges in their respective disciplines. These quantum programming tools abstract away the complexities of quantum processing in the same way that high-level programming languages abstract away the machine instructions, registers, and memory spaces of conventional von Neumann processor architectures.

IBM announced the 127-qubit Eagle quantum processor a year and a half ago. This is the quantum processor that’s been installed at the Cleveland Clinic. At its Quantum Summit late last year, IBM unveiled its 433-qubit Osprey quantum processor and plans to have the first of these processors online by the end of this year. (See “IBM Prepares For Quantum Computing Inflection Point.”) While the company is developing these bigger and faster quantum processors, IBM’s quantum processing working groups are helping to make quantum processing a practical computing tool for multiple disciplines.

Roy and Diana Vagelos Institute for Biomedical Research Education Launched at Columbia University with $175 Million Gift

With the COVID-19 pandemic highlighting the critical importance of biomedical research and new questions being raised about society’s capacity to generate world-changing scientific breakthroughs1, Roy and Diana Vagelos have made a $175 million gift to Columbia University to address this need. The Vagelos Institute for Biomedical Research Education created with this gift will be home to PhD students pursuing the most creative, potentially disruptive ideas in biomedical science, and will spur the training of more physician-scientists able to translate the latest paradigm-shifting discoveries into revolutionary new methods in patient care.  

logo

The gift will enable Columbia to create a new academic model that encourages and accelerates the intellectual risk-taking needed to make historic advances in health science research. Supportive career pathways, promising stability and academic freedom, are being developed to attract more students and junior faculty to this essential endeavor. Currently in the United States, PhD students, MDs in training, residents, fellows, and early-career physician-scientists who pursue a career in basic, translational or clinical research must contend with both financial challenges and professional uncertainty2.

By directly addressing and mitigating these obstacles, the Vagelos gift seeks to create an academic research environment conducive to bold experimentation and a sustained commitment to solving longstanding medical problems. Reducing the disproportionate financial burdens that deter historically marginalized groups from pursuing a career in science is a central pillar of this program.

“The financial support provided by Roy and Diana Vagelos to Columbia has been extraordinary, and so too is the leadership they provide through the values embodied in their philanthropy,” said Katrina Armstrong, Dean of the Columbia University Vagelos College of Physicians and Surgeons, and EVP for Health and Biomedical Sciences. “The Vagelos Institute for Biomedical Research Education will have an enormous impact in harnessing the power of science to transform clinical care, and I believe we will see similar initiatives started at other university medical schools. The reward for this effort will be unprecedented strides forward in curing disease and treating illness. It’s an opportunity—and a responsibility—we must embrace.”

The largest portion of the gift—$125 million—will establish an endowment to transform the prevailing approach for funding PhD students. This will provide Columbia trainees with greater freedom to explore different interests at the start of their careers. The remaining $50 million of the gift will support aspiring physician-scientists seeking to develop expertise in both fundamental biology and clinical medicine.

An external scientific advisory board of seasoned scientists and experts in graduate biomedical education will guide the development of these programs and of the new graduate biomedical curriculum tracks. The board is tasked with ensuring that Columbia University creates the optimal environment to nurture the growth of scientists who will shape the future of medicine. The initial group of board members includes Enrique M. De La Cruz, PhD, of the Yale School of Medicine; Tracy Johnson, PhD, of UCLA; William Kaelin Jr., MD, of the Dana-Farber Cancer Institute; and Shirley M. Tilghman, PhD, of Princeton University.

“This extraordinary generosity from Roy and Diana Vagelos continues their visionary support of education at the Vagelos College of Physicians and Surgeons, which so appropriately bears their name,” said Columbia University President Lee C. Bollinger. “It also continues their trailblazing efforts to rethink and strengthen the future of science and medical education at Columbia and around the world. For all of this, and so much more, we are extremely grateful.”

Roy and Diana Vagelos have been trailblazers in rethinking and strengthening the future of science and medical education at Columbia and around the world. Together with scholarship support from countless VP&S alumni, friends, and faculty, their transformative $250 million gift in 2017 made it possible for Columbia’s medical school to become the first in the nation to offer debt-free education to students. Their leadership precipitated a national movement among medical schools to eliminate student debt. The medical school was renamed the Vagelos College of Physicians and Surgeons as a tribute to their impact. This second transformational gift reflects the couple’s remarkable generosity and their deeply held values. It builds on a shared lifetime of charitable and compassionate action, particularly in their efforts to advance science, medical education, and better health care for all. For more information about Roy and Diana Vagelos, their respective professional accomplishments, and their prior giving to Columbia, please visit this page.

“We all know that continued scientific progress is the foundation for solving our most pressing medical problems,” said Dr. Vagelos. “Diana and I each vividly recall the difference that financial support made in creating a sense of freedom and instilling the confidence to pursue our passions early in our lives. We want to give others this same freedom by removing the obstacles facing researchers and scientists in training. The larger the number of talented researchers who are able to explore areas of discovery that capture their imaginations, the greater the impact they will have in changing medicine and improving health. It is our honor to give back.”

The Seven Deadly Sins of Biomedical Research

The risks of gain-of-function research on pandemic potential pathogens such as SARS and MERS outweigh the benefits. Greater oversight of biosafety, biosecurity, and biorisk management in laboratories must be done by an independent national agency that doesn’t perform or fund research.


Like Icarus flying too close to the sun, some scientists working in laboratories have been pushing the fates by creating pathogens (i.e., microbes that make people sick) that are more dangerous than those occurring in nature. Other scientists and policy experts, myself included, have joined forces to call for improved oversight, and, in some cases, the banning of “gain-of-function” research on pandemic potential pathogens also called “enhanced potential pandemic pathogens research” (ePPP). Gain-of-function research involves giving microbes such as bacteria and viruses enhanced capabilities that they might not normally possess in nature. This research currently receives almost no national or international oversight. Not all gain-of-function research is dangerous—for example, turning harmless bacteria into insulin-making machines is beneficial and cost-effective for treating diabetes and most biomedical research has resulted in substantial improvements in medicine and public health. However, the subfraction of gain-of-function research that enhances the risks posed by pandemic potential pathogens such as avian influenza (H5N1) virus or SARS-CoV deserves closer scrutiny and oversight.

With a case fatality rate of approximately 56 percent, the H5N1 avian influenza virus is much deadlier than SARS-CoV-2, which has an estimated case fatality rate below 2 percent. The H5N1 avian influenza virus first emerged in Hong Kong in 1997 from infected birds, but it was unable to spread readily from mammal-to-mammal.

Once a pathogen gains the ability to spread easily from mammal-to-mammal, the risks of it spreading to humans increases. Enter Ron Fouchier, a virologist from Erasmus Medical Center in the Netherlands. In 2011, he and his colleagues decided to give the H5N1 avian influenza virus the enhanced capability of airborne spread between mammals. Fouchier wanted to see what mutations the virus might need to acquire to start a pandemic. He chose ferrets as the experimental animal, because they are susceptible to influenza viruses and develop influenza respiratory disease like humans. The experiments were performed in a Biosafety Level 3 (BSL-3) laboratory, one step below the highest containment laboratories (BSL 4) that feature containment rooms and spacesuits. After introducing mutations into the virus, Fouchier performed serial passages: a form of selective breeding of the virus in ferrets to obtain novel mutant viruses that are efficiently transmitted by aerosol from mammal to mammal.

The most prevalent reason asserted for conducting gain-of-function research on pandemic potential pathogens is to be able to predict future pandemics. In other words, by creating novel pandemic potential pathogens in laboratories, scientists like Fouchier would be able to recognize them in the wild before they spilled over from animals into humans.

That’s the theoretical argument, anyway.

In practice, their reasoning is flawed. To more clearly illustrate this analysis, let’s examine weather forecasting. Predicting hurricanes is a purely observational exercise that implements satellite data. Scientists don’t manipulate clouds to see what conditions are needed to start hurricanes. They use atmospheric and climate models instead. In a similar fashion, scientists could employ artificial intelligence and machine learning tools to predict viral evolution instead of manipulating viruses in laboratories. This entails that risky gain-of-function research on pandemic potential pathogens is not a necessity in predicting future pandemics.

Concerns about risky research prompted the National Academy of Sciences (NAS) to issue a report in 2004 titled “Biotechnology Research in an Age of Terrorism,” listing seven “experiments of concern,” recognized as the “seven deadly sins,” that should not be pursued if they could create pathogens that are not already present in nature.

These experiments include:

  1. Demonstrating how to make a vaccine ineffective
  2. Developing a pathogen’s resistance to antibiotics or antiviral agents
  3. Enhancing a pathogen’s virulence (i.e., lethality) or making a non-lethal microbe lethal
  4. Increasing the transmissibility of a pathogen (e.g., making a non-airborne pathogen airborne)
  5. Altering the host range of a pathogen by increasing the number of species it can infect
  6. Enabling a pathogen to evade diagnostic testing
  7. Enabling a biological agent or toxin to be weaponized

The avian influenza (H5N1) virus studies involving ferrets involved experiments 4 and 5 in the list. According to the NAS, these experiments should not have been done.

In the case of SARS-CoV-2, the causative agent of the COVID-19 pandemic, the jury is still out regarding how the virus developed and how it spread from animals to humans. But understanding the origins of the virus is imperative to the development of effective policies and procedures that can reduce the likelihood of such a catastrophe from happening again. Both SARS and MERS, which emerged in 2003 and 2012, respectively, had extensive clinical specimen evidence (i.e., bodily fluids) from animals and humans demonstrating natural spillover events. Clinical specimen evidence includes either the virus itself or antibodies that bodies make to attack the virus, like microscopic missiles.

For example, palm civets (i.e., exotic mammals eaten as delicacies) sold at an animal market in Guangdong, China were found to harbor viruses that were 99.8 percent identical to the SARS virus found in humans; and 80 percent of palm civets tested positive with antibodies to the SARS virus. Blood tests of almost 800 people in the Guangdong Province found that individuals who traded palm civets had the highest antibody positivity rates to SARS compared to everyone else.

Similarly with MERS, archived blood specimens from dromedary camels dating back decades throughout the Middle East, parts of Asia, and North and East Africa tested positive for MERS antibodies, providing the evidence that the virus had been circulating in the animals for a long time. From 2012 to 2013, a study of over 10,000 healthy adults from all thirteen provinces of Saudi Arabia found MERS antibodies in 0.15 percent of the samples. People who worked with camels had much higher rates of MERS antibodies compared to the general population. Specifically, camel shepherds had MERS antibody rates fifteen times higher, and for slaughterhouse workers, a whopping twenty-three times higher rate than the public.

In other words, the key evidence for natural spillover for both SARS and MERS was clinical specimens from occupational exposures. Working with animals that harbor zoonotic pathogens (microbes that can spread from animals to humans) increased spillover risk in the animal workers. A One Health approach integrating human, animal, and environmental surveillance is essential for monitoring future natural spillover events.

In contrast to SARS and MERS, neither the SARS-CoV-2 virus nor antibodies to the virus have been reported in animals or animal workers. No studies involving clinical specimens have been published in the medical literature that fulfills the criteria for a natural spillover event. In early 2020, George Gao, a former director of the Chinese Center for Disease Control and Prevention, and his colleagues conducted a non-peer reviewed study that found 0 out of 457 clinical specimens taken from 18 species of animals in the live animal market in Wuhan contained the virus. The Chinese conducted surveys of thousands of people to assess the rates of antibody prevalence to SARS-CoV-2 in the general population. Unfortunately, none of these studies included occupational data, eliminating a critical factor in determining natural spillover risk. In addition, no studies have been published examining SARS-CoV-2 antibody rates in laboratory workers at the Wuhan Institute of Virology (WIV). The window to assess differences in rates between the laboratory workers and the public when such differences would still exist closed in early 2020.

The public record, however, indicates that SARS-CoV-2 was genetically manipulated at the Wuhan Institute of Virology. In 2016–17, researchers at WIV constructed novel chimeric SARS-related coronaviruses that combined the spike genes of different SARS-related coronaviruses. A chimera possesses genetic material from two different organisms. The spike protein of SARS-CoV-2, which is used like a key to enter cells, has a highly unusual feature called a “furin cleavage site” that is not present in the more than 200 other known SARS-related (e.g., Sarbeco) coronaviruses, making it highly infectious. While furin cleavage sites occur naturally in many other coronaviruses, the SARS-CoV-2 furin cleavage site has a particularly unique sequence of amino acids. This feature has been the subject of much debate with some scientists demanding a full investigation into possible laboratory origins, while others stress that there is no evidence.

Science must be transparent to maintain its legitimacy. An immense debate such as this warrants a full investigation into the virus’ origins, especially since there is no compelling evidence for a natural spillover event. Stonewalling such an investigation engenders suspicion.

To prevent future catastrophic pandemics, my colleagues and I propose improvements in protections at national and international levels in biosafety, biosecurity, and biorisk management. Biosafety and biosecurity protect against accidental and deliberate release of pathogens in laboratories, respectively. In the United States there are currently no regulations, only guidelines pertaining to biosafety. There is a law for biosecurity called the Select Agent Rule, but this legislation only applies to several dozen human, livestock, and crop pathogens and biological toxins that are considered high risk for bioweapon use.

Biorisk management involves risk-benefit assessments of proposed high-risk research on dangerous pathogens that might qualify as one of the “seven experiments of concern.” From 2014 to 2016, the US government imposed a pause in federal funding for gain-of-function research on SARS, MERS, and influenza viruses. As with biosafety and biosecurity, the same federal agencies that perform and fund gain-of-function research of pandemic potential pathogens are also in charge of biorisk management. An inherent conflict of interest exists, and the system is opaque without public scrutiny or input.

In all three cases—biosafety, biosecurity, and biorisk management—oversight must be conducted by an independent national agency that does not perform or fund research. Oversight regulations should be transparent, enforced, and harmonized at the international level. Given the uncertainty surrounding the origins of SARS-CoV-2, it is prudent to cover all bases in developing policies to prevent another catastrophic COVID-19 pandemic.

. . .

Laura H. Kahn is a physician, author, educator, and consultant. For almost twenty years she was a research scholar at the Program in Science and Global Security at Princeton University. She is currently completing a book using a One Health framework to examine coronaviruses.

Image Credits: Wikimedia, NIAID Integrated Research Facility

Two decades of stagnant funding have rendered Canada uncompetitive in biomedical research. Here’s why it matters, and how to fix it.

You may imagine that the hard part of being a Canadian scientist is having a bright idea. However, while curiosity, persistence and inventiveness are prerequisites for scientific success, the major obstacle to being a biomedical scientist in Canada is obtaining research funding.

Canadian biomedical scientists receive funding to hire scientific staff and buy experimental materials by applying for federally funded grants from the Canadian Institutes of Health Research (CIHR).

To purchase their high-tech tools (infrastructure), researchers apply for grants from the Canada Foundation for Innovation (CFI). These grant agencies are underfunded, and some of their programs are poorly designed, with funding success rates so low scientists must apply repeatedly to obtain funding that is financially inadequate.

As a result, Canadian scientists may feel like they spend more time writing grant applications than doing research. The reality is that stagnant funding is holding back Canadian science.

Securing CIHR grants has become impractically competitive. Most applications require multiple revisions and resubmissions, often imposing an interval of one to two years between first submission and funding. Since funding from a CIHR project grant only lasts five years, the life of the lab — and the jobs of Canadian scientists — are recurrently in jeopardy.

Core funding issues

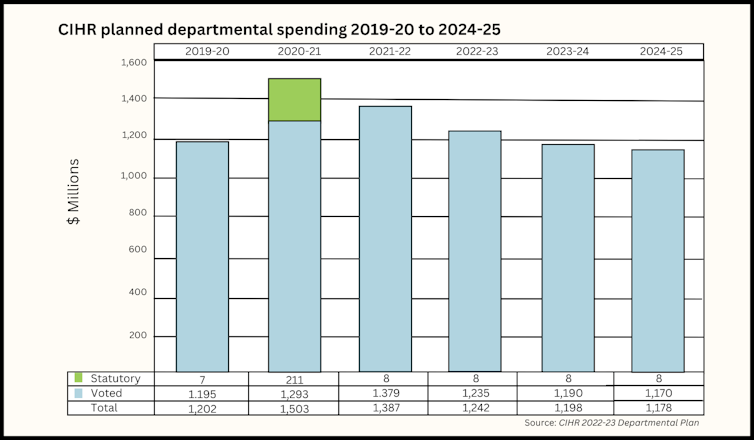
Let’s review the core problems with the funding of Canadian science. Stagnation in Canada’s biomedical grant funding reflects the fact CIHR’s funding from the Government of Canada has not increased since 2006 (in constant dollars, year 2000) and is not predicted to increase by 2025.

Two decades of stagnant funding have rendered Canada uncompetitive in biomedical research. Here’s why it matters, and how to fix it.
Graph of planned spending over time illustrates that CIHR funding is flat.
(CIHR data)

The United States is a relevant comparator because it is home to many of the world’s leading scientists. Canadian scientists, if not funded, often relocate to the U.S. Compare America’s National Institutes of Health (NIH) 2020-21 budget of US$45 billion (roughly C$60 billion) to CIHR’s C$1.2 billion. America’s NIH budget is 50-fold that of Canada’s CIHR budget, but the U.S. population is only nine-fold greater than ours.

Canada’s spending on research and development, as a percentage of gross domestic spending, is also smaller than the U.S.’s.

Grant competition success rates

The success rate in CIHR grant competitions has declined from 31 per cent in 2005 to around 15 per cent in 2020.

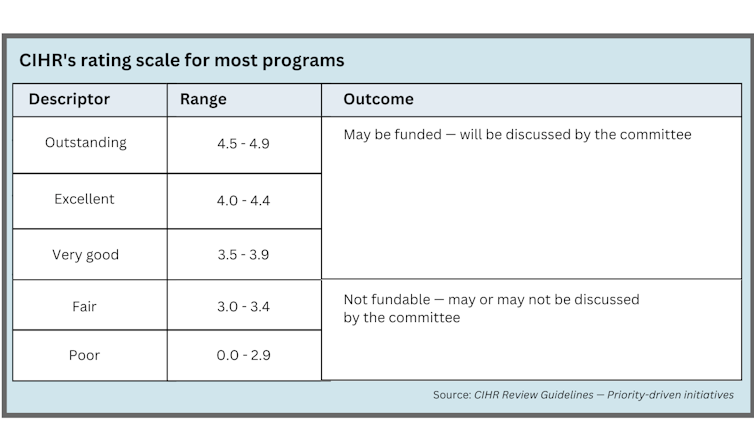
CIHR evaluates applications on a scale of zero to 4.9, corresponding to categories of poor, fair, very good, excellent and outstanding. Currently, CIHR grants are rarely funded unless the voted score is outstanding (rated 4.4 to 4.9). Usually only the top 18 per cent of all grants — fewer than one in five — are funded, and virtually all grants rated excellent are rejected.

This low-success endeavor is a demoralizing waste of time for the 82 per cent of scientists who are rejected and for the peer-review volunteers — unpaid colleagues who spent weeks reviewing the applications.

chart showing CIHR grant rating categories
Almost all grants scored by CIHR as excellent go unfunded.
(CIHR data)

Once funded, challenges remain. All CIHR awarded project grants are now subject to a 23.5 per cent across-the-board funding cut. This cut allowed CIHR to fund 87 additional grants per competition from 2018 to 2020, however the value of a five-year project grant shrank from $950,000 to $725,000.

These cuts mean scientific staff must take pay cuts or be terminated, and the approved research can only be partially completed.

Fixing funding

Canada needs to revitalize its scientific mojo and to do so must improve research funding. There are several steps that would improve science funding in Canada.

1. Implement the Fundamental Science Review recommendations

The fix for Canadian science was well enunciated by the Fundamental Science Review, also known as the Naylor Report, in 2017. This report recognized that underfunded Canadian science was falling behind.

It noted that federal underfunding is exacerbated by CIHR’s practice of earmarking substantial portions of its limited funds to targeted proposals that address governmental priorities, rather than funding research and discovery science.

The report made simple recommendations to improve Canadian research: “Rapidly increase its investment in independent, investigator-led, research to redress the imbalance caused by differential investments favouring priority-driven, targeted research.”

A group of people sitting on blue storage drawer units in a V formation.
Members of the author’s research team at the Archer laboratory at Queen’s University.
(Author provided), Author provided

It also recommended “formation of an independent advisory committee on basic research and industrial innovation, comprised of leaders in research and industry” (not government employees). Our government currently makes many top-down science funding decisions without a strategic scientific plan or an external scientific committee to advise them. An independent advisory committee would reduce political interference in science.

The Naylor report’s recommendations have not been fully implemented, but would transform Canadian research. This would require commitment of an additional 0.4 per cent of the Government of Canada’s annual budget to our science sector.

2. Fund salaries for scientists who run infrastructure

In the meantime, CFI and CIHR could each implement “researcher-centric” changes.

CFI could accompany its infrastructure grants with funding for the scientists who are needed to operate these complex research platforms.

CFI grants are used to purchase the multi-million-dollar tools needed to conduct research at the cutting-edge, such as NextGen gene sequencers and super resolution confocal microscopes. CFI has a 30 per cent funding success rate, allowing purchase of infrastructure; but it does not pay for the scientists who run these scientific infrastructure platforms.

This makes it difficult to sustain a CFI scientific platform.

3. Bring back the foundation grant program

CIHR could resurrect its very successful foundation grant program.

A woman in a white coat in a lab
Foundation grants allowed scientists to bundle all their research into a single, comprehensive application.
(Shutterstock)

CIHR understood that its most successful scientists usually required two to three project grants, and recognized the time drag that acquiring multiple project grants required.

They responded in 2014 with the foundation grant program. Foundation grants allowed scientists to bundle all their research into a single, comprehensive application which offered more funding (equivalent to two to three project grants) for a longer duration (seven years instead of five years for project grants).

This allowed researchers to spend more time on doing science and less on writing and reviewing grants. My foundation grant gave me the stability and flexibility to simultaneously study oxygen sensing, mitochondrial dynamics and to develop drugs to treat pulmonary hypertension, cancer and COVID-19.

However, the foundation grant program was unceremoniously terminated, forcing grant holders to once again, apply for two to three simultaneous project grants.


Read more:
How COVID-19 damages lungs: The virus attacks mitochondria, continuing an ancient battle that began in the primordial soup


Funding research pays off

Researchers are key to Canada’s capacity to create a high-tech economy, build the biomedical sector and seed entrepreneurial activity. Researchers also support our academic health sciences centres and universities, making them internationally competitive.

Research has a great return on investment, with an estimated 30 to 100 per cent of the expenditure on publicly funded research being returned to society. Each research laboratory is a small business creating well-paying jobs, knowledge and intellectual property, which many commercialize.

In addition to launching medical innovations, patents and spin-off companies, Canada’s researchers teach university students, and many CIHR-funded clinician-scientists provide patient care in our hospitals. In all of these ways, investment in research is critical to making Canada healthy, wealthy and wise.

Top Pharmacology Researcher to Oversee School of Medicine’s Pioneering Biomedical Research

Top Pharmacology Researcher to Oversee School of Medicine’s Pioneering Biomedical Research

The University of Virginia School of Medicine has named Jeffrey R. Martens, PhD, an internationally recognized pharmacology researcher, leader, and educator, as the new Senior Associate Dean for Research. Martens will assume his new role on May 15, 2023. 

“Professor Martens will be a key contributor in the transformation of the School of Medicine and UVA Health medical research program, while also managing a rapidly growing portfolio of resources, innovative projects, and talent for the School of Medicine and the greater University,” said Melina R. Kibbe, MD, the dean of the UVA School of Medicine and chief health affairs officer for UVA Health.

Martens comes to UVA from the University of Florida College of Medicine, where he has served as chair of the Department of Pharmacology and Therapeutics for the past eight years. He has driven a 10-fold increase in outside research funding during his tenure. He also spearheaded collaboration within the College of Medicine as well as with research centers and institutes across the University of Florida. In addition, the academic and scientific achievements of his faculty resulted in U.S. News & World Report ranking for Pharmacology and Toxicology at UF in the top 17 nationally, the top nine among public universities and 50th internationally.

The impact of Martens’ research is demonstrated through his long list of peer-reviewed publications and the fact that his research has been continuously funded by the National Institutes of Health, National Science Foundation and the American Heart Association, among others, since 1990. Dr. Martens’ research is focused in two areas of pharmacology and therapeutics, including sensory neuropharmacology and cardiovascular pharmacology, with work in both the heart and olfactory systems.

Martens holds longstanding memberships in several professional societies, including the American Society for Pharmacology and Experimental Therapeutics and the Association of Chemoreception Sciences. He also has served in several editorial board positions for scientific publications, most recently as an editorial advisory board member for Molecular Pharmacology.

Martens earned his bachelor’s degree and doctorate from the University of Florida and did his post-doctoral training at Colorado State University. Before joining the faculty at the University of Florida, Martens was a faculty member at Oregon Health & Science University and the University of Michigan.

“This position at UVA is a new and different opportunity to lead across department boundaries and integrate the School of Medicine’s excellent clinical, translational and basic science efforts,” Martens said. “I am excited to collaborate with the School of Medicine’s world-class faculty and join a respected leadership team at a time of transformational growth.”

He succeeds Linda Duska, MD, MPH, who has served as interim Senior Associate Dean for Research since March 15, 2021. “The strategic guidance, leadership and program oversight Dr. Duska has provided to the School of Medicine has been invaluable,” Kibbe said. “I have extraordinary gratitude for her dedication and commitment to the School of Medicine and UVA Health.”

Duska will continue in her roles as Associate Dean for Clinical Research in the School of Medicine, Vice Chair for Research in the Department of Obstetrics and Gynecology, and as a gynecologic oncologist at the UVA Cancer Center.