How to improve health: Tips for better sleep and diet

When it arrives to wellness advice, a lot of people today have extremely distinct opinions. From time to time you are going to hear people today say to take in keto and elevate weights, while other periods people today will say that you should do cardio and count energy. With the litany of unique tips, it can be complicated to come across a program that performs for you.

Lots of individuals want to increase their wellbeing and are not absolutely sure which spots subject the most — ought to slumber and food plan be the most important emphasis or must it be physical exercise? The actual solution is focusing on establishing a more healthy lifestyle and improving various areas of your lifestyle that can have a constructive impact on health.

Some of the most evident types are rest, food plan, work out, daylight and associations. Here’s how you can make minor improvements in each and every of these regions.

How to increase your sleep

Improving upon sleep might feel like an extremely hard process. Soon after obtaining property from university or function, time can just fly by. There are a few factors to do to assist you have greater snooze. Initial, ditch the blue light-weight before slumber. As tempting as it is to scroll through social media or textual content with your friends correct before heading to mattress, wanting at blue gentle can negatively effect your snooze. According to the Cleveland Clinic, scrolling on your cell phone can also retain your mind energetic, which will make it more challenging to tumble asleep.

Test turning off your electronics a couple of hrs in advance of bed and executing other pursuits, like reading a reserve or meditating prior to mattress, which can assist you to take it easy. Make confident to established your alarm in advance of you place your telephone down.

Another matter that can boost your rest is keeping away from caffeine prior to bed, for each the CDC. Consider to end drinking caffeine at noon each and every working day, so that way when you go to slumber, the results of it have worn off. Increasing snooze is about producing small improvements that will profit you in the prolonged run. Superior rest is essential for hormonal regulation and all round overall health, and it can set you up to make good decisions in the lengthy operate.

How to improve your diet program

Strengthening your diet plan can feel like a daunting job. One particular uncomplicated way to make alterations is to believe about earning uncomplicated switches. If you take in chips with lunch, take into consideration swapping them for carrots and celery. If you’re cooking a pasta dish, take into consideration switching the white flour pasta for a chickpea or pink lentil pasta. If you love fried chicken, attempt producing a baked version.

A handful of of these switches can be valuable in generating incremental, beneficial variations toward wellness. Also take into account what you can include to foods that you love. Say you seriously like mashed potatoes — take into account undertaking 50 percent potato and then fifty percent cauliflower. Or believe about a pasta dish you like, these kinds of as baked ziti. Imagine about how you can add broccoli and spinach to it. If your food plan could use some enhancement, odds are if you quickly switch to salads all the time, you won’t be earning sustainable adjustments.

There are other modest modifications you can make. Healthline indicates that you pay out interest to protein ingestion and continue to be hydrated through the day. A further tip is to remain away from diet plan meals. Assume about feeding on full food items when trying to strengthen your food plan.

How to begin working out

If you have stopped doing exercises, it’s not too late to get started doing it again. Genuine Basic indicates that when you’re trying to get again into the swing of exercising, start off compact. Instead of immediately striving to go back to wherever you were when you were exercising the most, get back into the behavior of accomplishing some motion every day.

The ideal exercise to do is the 1 that you will do continually and that you like. Experiment with health lessons or going to the health and fitness center or doing exercises at household or exterior. Finding a routine that you like can be beneficial to start off doing exercises.

A further way to get started doing exercises is to make accountability for by yourself. Communicate to a friend about finding again into a regime and build an accountability strategy. Even if you begin out compact, undertaking a small little bit of workout each week can help you to truly feel improved.

Why sunlight matters for pressure administration

Tension management can be a difficult issue to do. In accordance to the Stanford Life-style Medication Plan, taking care of pressure can be done by pinpointing the cause of the strain and then responding accordingly. Sunlight also can be an significant part of pressure management.

According to The Wellesley Information, sunlight can make us sense much less pressured. There’s just a thing about the solar that allows us sense better. According to a review posted in the journal Environmental Overall health Perspectives, daylight boosts the sum of vitamin D that you take in — numerous folks are deficient in this, so finding ample light-weight each individual working day can assistance your wellness.

When operating a 9 to 5, it can be tough to discover the time to go outside. Consider taking your lunch crack outdoors. This is a wonderful time to go for a quick, brisk wander as effectively, which can aid you get some movement in. Your temper may possibly also be positively impacted by expending much more time in the sunlight.

How to focus on relationships

Concentrating on relationships can enhance your total health. If you are pleased with your relationships, you may perhaps also be additional inclined to shell out more time increasing your overall health in other strategies, also.

Bettering associations is additional of an artwork than it is a science. Paying time with the people today you like can assistance you improve your relationships. When you are with a individual you love, acquire time to pay attention to them — really listen to them — and believe about what they’re stating. Make positive to let men and women in your lifetime know that you benefit them. It can boost your overall temper and well being to have strong interactions.


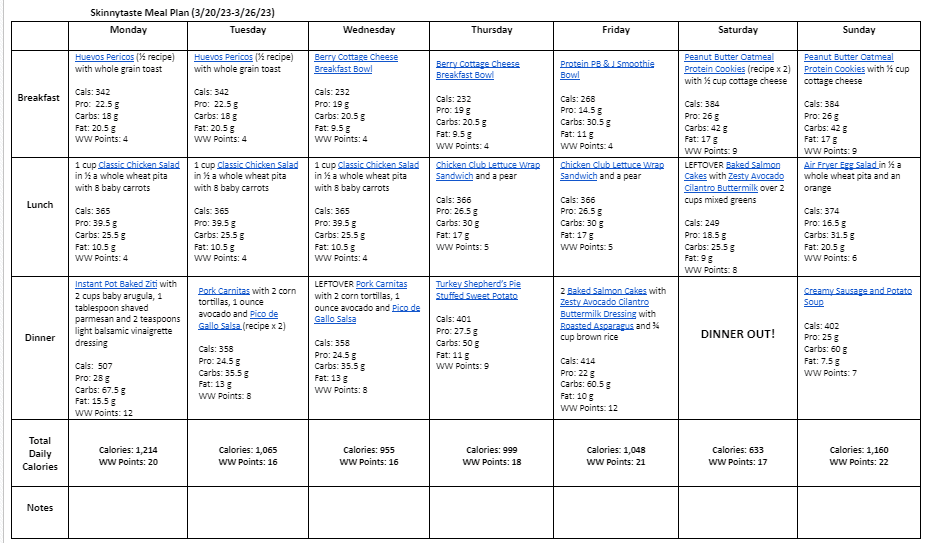
7 Day Healthy Meal Plan (March 20-26)

This post may contain affiliate links. Read my disclosure policy.

A free 7-day, flexible weight loss meal plan including breakfast, lunch and dinner ideas and a shopping list. All recipes include macros and WW points.

Spring finally arrives this week! I love this season of rebirth and renewal and I’m ready to see green grass and blooms! I want to thank everyone for their kind words and excitement on my new book- Skinnytaste Simple: Easy, Healthy recipes with 7 Ingredients or Fewer, which you can pre-order here on Amazon or wherever books are sold.

With grocery prices soaring, many of us are having to adjust, scale back and/or get more creative with our meals. One of the absolute BEST ways to stay within a budget and maintain healthy eating habits is to MEAL PLAN. You can get more 5-day Budget Friendly Meal Plans by signing up for Relish+ (get a 14-day free trial here!)

Ultimate Skinnytaste Meal Planner

Skinnytaste Ultimate Meal Planner

Get the Skinnytaste Ultimate Meal Planner! The 52 week spiral bound meal planner has weekly meal planning grids you can tear out and put on your fridge if you wish, a 12-week meal plan, 30 (15 new) recipes, and tear-out grocery lists. I love starting my week with gratitude, affirmations and intentions, so I included a space for that as well. I hope you will love this as much as I do!

Skinnytaste Ultimate Meal Planner

Buy the Skinnytaste meal planner here:

A note about WW Points

All recipe points have been updated to reflect the new WW program, points will display under the recipe title. I will keep the ww button in the recipe card, click on that and it takes you to the Weight Watchers website where you can see the recipe builder used to determine those points and add it to your day (US only, you must be logged into your account). All cookbook recipes in the cookbook index are also updated!

About The Meal Plan

If you’re new to my meal plans, I’ve been sharing these free, 7-day flexible healthy meal plans (you can see my previous meal plans here) that are meant as a guide, with plenty of wiggle room for you to add more food, coffee, beverages, fruits, snacks, dessert, wine, etc. or swap recipes out for meals you prefer, you can search for recipes by course in the index. Depending on your goals, you should aim for at least 1500 calories* per day. There’s no one size fits all, this will range by your goals, your age, weight, etc.

There’s also a precise, organized grocery list that will make grocery shopping so much easier and much less stressful. Save you money and time. You’ll dine out less often, waste less food and you’ll have everything you need on hand to help keep you on track.

Lastly, if you’re on Facebook join my Skinnytaste Facebook Community where everyone’s sharing photos of recipes they are making, you can join here. I’m loving all the ideas everyone’s sharing! If you wish to get on the email list, you can subscribe here so you never miss a meal plan!

Meal Plan:

Breakfast and lunch Monday-Friday, are designed to serve 1 while dinners and all meals on Saturday and Sunday are designed to serve a family of 4. Some recipes make enough leftovers for two nights or lunch the next day. The grocery list is comprehensive and includes everything you need to make all meals on the plan.

MONDAY (3/20)
B: Huevos Pericos (½ recipe) with whole grain toast
L: 1 cup Classic Chicken Salad  in ½ a whole wheat pita with 8 baby carrots
D: Instant Pot Baked Ziti with 2 cups baby arugula, 1 tablespoon shaved parmesan and 2 teaspoons light balsamic vinaigrette dressing

Total Calories: 1,214*

TUESDAY (3/21)
B: Huevos Pericos (½ recipe) with whole grain toast
L: 1 cup Classic Chicken Salad  in ½ a whole wheat pita with 8 baby carrots
D: Pork Carnitas with 2 corn tortillas, 1 ounce avocado and Pico de Gallo Salsa (recipe x 2)

Total Calories: 1,065*

WEDNESDAY (3/22)
B: Berry Cottage Cheese Breakfast Bowl
L: 1 cup Classic Chicken Salad  in ½ a whole wheat pita with 8 baby carrots
D: Pork Carnitas with 2 corn tortillas, 1 ounce avocado and Pico de Gallo Salsa
Total Calories: 955*

THURSDAY (3/23)
B: Berry Cottage Cheese Breakfast Bowl
L: Chicken Club Lettuce Wrap Sandwich and a pear
D: Turkey Shepherd’s Pie Stuffed Sweet Potato

Total Calories: 999*

FRIDAY (3/24)
B: Protein PB & J Smoothie Bowl
L: Chicken Club Lettuce Wrap Sandwich and a pear
D: 2 Baked Salmon Cakes with Zesty Avocado Cilantro Buttermilk Dressing with Roasted Asparagus and ¾ cup brown rice

Total Calories: 1,048*

SATURDAY (3/25)
B: Peanut Butter Oatmeal Protein Cookies (recipe x 2) with ½ cup cottage cheese
L: LEFTOVER Baked Salmon Cakes with Zesty Avocado Cilantro Buttermilk over 2 cups mixed greens
D: DINNER OUT

Total Calories: 633*

SUNDAY (3/26)
B: Peanut Butter Oatmeal Protein Cookies with ½ cup cottage cheese
L: Air Fryer Egg Salad in ½ a whole wheat pita and an orange
D: Creamy Sausage and Potato Soup

Total Calories: 1,160*

*This is just a guide, women should aim for around 1500 calories per day. Here’s a helpful calculator to estimate your calorie needs. I’ve left plenty of wiggle room for you to add more food such as coffee, beverages, fruits, snacks, dessert, wine, etc.

*Google doc

Mobile clinics, launched to help with COVID, now fill gaps in rural health care : Shots

Mobile clinics, launched to help with COVID, now fill gaps in rural health care : Shots

Clinics in rural areas with fewer doctors, dentists and nurses are turning to mobile health care clinics to take care to where it’s most needed. The Healthy Communities Coalition organizes a few mobile dental events each year in Lyon County, Nev.

Wendy Madson/KHN


hide caption

toggle caption

Wendy Madson/KHN


Clinics in rural areas with fewer doctors, dentists and nurses are turning to mobile health care clinics to take care to where it’s most needed. The Healthy Communities Coalition organizes a few mobile dental events each year in Lyon County, Nev.

Wendy Madson/KHN

Nearly 12 years ago, a nonprofit centered on substance abuse prevention in Lyon County, Nev., broadened its services to dental care.

Leaders with the Healthy Communities Coalition were shocked into action after two of their food pantry volunteers used pliers to pull each other’s abscessed teeth. The volunteers saw no other option to relieve their overwhelming pain in the small town where they lived, 40 miles southeast of Reno, because of a dearth of dental care providers.

That drastic act, said Wendy Madson, executive director for the coalition, prompted her organization to use mobile clinics to offer health and dental services in rural communities where there aren’t enough patients to support brick-and-mortar offices.

The coalition now sends a van outfitted with dental equipment to county schools to treat hundreds of students per stop a few times each year. They also host events providing free care for adults in the region. The response has been overwhelming.

“Dental is the hot ticket,” Madson said. “Everybody wants dental. Availability of those services is what runs out first in those large mobile events.”

The coalition’s mobile programs mirror efforts nationwide to dispatch services to patients experiencing gaps in the health care system, especially in rural areas.

Rural residents face more significant health care provider shortages, including dentists, compared with their counterparts in larger cities. Since the beginning of the pandemic, mobile clinics have increased access to a range of services in hard-to-reach places with sparse populations.

A recently passed law, which makes it easier for rural communities to pay for new mobile clinics, could expand this trend. In the past, clinics that serve low-income rural residents couldn’t spend federal grant money — called new access point grants — on mobile services in communities where they didn’t already have facilities.

Then last fall, Congress passed the MOBILE Health Care Act, sponsored by Sens. Jacky Rosen, D-Nev., and Susan Collins, R-Maine, which gives federally qualified health centers – health clinics serving medically underserved areas — greater flexibility to use federal funding to create and operate mobile units.

Healthy Communities Coalition executive director Wendy Madson says mobile dental clinics in Lyon County, Nevada, help reach young students whose parents might otherwise lack the means or insurance to schedule regular visits.

Wendy Madson/KHN


hide caption

toggle caption

Wendy Madson/KHN

Since 2019, the number of mobile clinics on the road has expanded, according to the National Association of Community Health Centers. Many were used for COVID-19 testing and vaccinations. And health and community organizations started using mobile units to bring primary care, behavioral health, and reproductive services to out-of-the-way patients. The new funding pathway could soon put even more mobile health vans on the road.

For now, the law is dependent on congressional funding, and experts predict it could be at least a year before health centers can access the grant money.

Freed from brick-and-mortar requirements, health centers can roll out the vans

Once funded, the regulatory shift will allow health centers to collaborate with independent organizations like Madson’s Health Communities Coalition in Nevada to expand services in underserved regions. Because the coalition is not a federally qualified health center, it has relied on a mix of other federal and state grants.

Nearly 1,400 federally qualified health centers nationwide receive federal funding for providing comprehensive health services in underserved areas. The previous requirement that health centers establish brick-and-mortar clinics before expanding mobile clinics prevented many from applying, said Steve Messinger, policy director for the Nevada Primary Care Association. It was burdensome and costly for health centers.

But in rural areas with small populations, served well by mobile clinics, it wouldn’t make sense to first establish a building with a full-time provider, he said. That could eat up the budget of a federally qualified health center.

While health center advocates lobby Congress for base funding, the Healthy Communities Coalition is forging ahead with three dental events this year funded by a grant from the Health Resources and Services Administration, part of the Department of Health and Human Services.

At the first medical outreach event the coalition organized in 2012 in Lyon County, where 61,400 residents are spread across more than 2,000 square miles, more than 200 people showed up to receive free care and 150 teeth were pulled, Madson said. Since then, the organization has hosted several events a year — except in 2020, when the pandemic paused work.

Mobile dental clinics organized by the Healthy Communi(Wendy Madson) ties Coalition help ensure Lyon County, Nev., students receive cleanings, screenings, X-rays, and more.

Wendy Madson/KHN


hide caption

toggle caption

Wendy Madson/KHN

Many of the dental events are school-focused and provide children with such services as screenings, X-rays, sealings, varnish, and cleanings. But an overwhelming need for care also exists among area adults, said Madson, because Medicare and Nevada’s Medicaid do not include comprehensive dental coverage for adults. It’s harder to fund those events, she said.

Of the five communities in Lyon County, at least one, Silver Springs, does not have a single dentist. There are 10 dentists total in Fernley and Dayton, communities with a combined population of 38,600 people, but only two of those practices accept Medicaid, which covers low-income people younger than 21 and limited dental services for adults.

Filling a desperate need for dental and health services

Traci Rothman, who manages the coalition’s food pantries, said the dental outreach events made a difference for her 29-year-old son, who moved to Silver Springs last year. He went to two mobile clinics to receive free care, which Rothman said was a big relief because he’s uninsured and needed dental care badly.

“Otherwise, you’re going to somebody that you’re paying cash,” she said. “Oftentimes I cannot pay, honestly; it’s just out of reach for some people, or most people … in rural areas.”

Madson said the coalition stepped in to help a young student in desperate need of a root canal. The coalition is helping the girl’s family apply for Medicaid or Nevada Check Up, the state Children’s Health Insurance Program, and is paying $1,600 to cover the service with federal grant money. Another student had to be referred to several specialists before she had her decayed baby teeth surgically removed and received restorative treatment for adult teeth that had begun to decay.

“Her mom was so thankful, she was in tears,” Madson said. “She told me that her daughter woke up without instant pain for the first time in years.”

Madson said her organization has enough grant funding for three events through May, but she hopes the MOBILE Health Care Act will help expand services. Besides dental care, the group provides primary care mobile clinics for immigrant workers in Yerington, a small town in an agricultural region about 70 miles southeast of Reno.

Sara Rich, CEO of Choptank Community Health in Maryland, said she shares Madson’s hope.

Choptank serves five counties in Maryland, including small towns between the Chesapeake Bay and the Delmarva Peninsula. Amid the pandemic, the health organization struck an unlikely partnership with a car dealership and used federal COVID relief money to buy a Ford Transit cargo van for mobile clinics.

Choptank used its new van to provide vaccines but has since started using it to provide primary care to immigrant workers and dental services to children at 36 schools. The mobile clinics have been so successful that the health center is working on purchasing more vans to expand its services.

Rich said the mobile clinics are “breaking down barriers that a lot of us have been working on for a long time.”

Among the new services Choptank seeks to provide are behavioral health, preventing and treating substance use disorders, and skin screenings for people working on the shores of Maryland.

“Flexibility has been a theme over the last few years,” Rich said. “I think this MOBILE Health Care Act will help us do that even more into the future.”

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

Leading American medical journal continues to omit Black research, reinforcing a legacy of racism in medical knowledge

The leading U.S. medical journal, read regularly by doctors of all specialties, systematically ignores an equally reputable and rigorous body of medical research that focuses on Black Americans’ health.

The American Medical Association created a segregated “whites only” environment more than 100 years ago to prohibit Black physicians from joining their ranks. This exclusionary and racist policy prompted the creation in 1895 of the National Medical Association, a professional membership group that supported African American physicians and the patients they served. Today, the NMA represents more than 30,000 medical professionals.

In 2008, the AMA publicly apologized and pledged to right the wrongs that were done through decades of racism within its organization. Yet our research shows that despite that public reckoning 15 years ago, the opinion column of the AMA’s leading medical journal does not reflect the research and editorial contributions by NMA members.

Invisibility in the opinion column of one of the most prominent medical journals in the U.S. is another form of subtle racism that continues to lessen the importance of equitable medical care and health issues for Black and underserved communities.

As rhetoricians and researchers who study scientific communication, we look at the ways scientific writing perpetuates or addresses racial inequity. Our recent study traced how research is referenced by medical professionals and colleagues, known as citations, of flagship journals of the NMA and AMA: the Journal of the National American Association and the Journal of the American Medical Association.

Invisible research

Our research began with a question: Has the AMA’s 2008 apology had any effect on the frequency with which JAMA opinion writers draw on insights and research of JNMA scholars and authors?

We studied opinion columns, also referred to as editorials, precisely because they are useful indicators of current and future research as well as priorities and agendas. The purpose of editorials is to critically analyze and sift through various opinions and evidence. Effective editorials in scientific journals are especially rich forums for debate within the medical community.

Medical publications like JNMA and JAMA do not simply convey knowledge. They also establish professional community values through the topics that are studied and who is credited for ideas related to research. When writers choose to reference or cite another scholar, they are acknowledging and highlighting that expertise.

Leading American medical journal continues to omit Black research, reinforcing a legacy of racism in medical knowledge
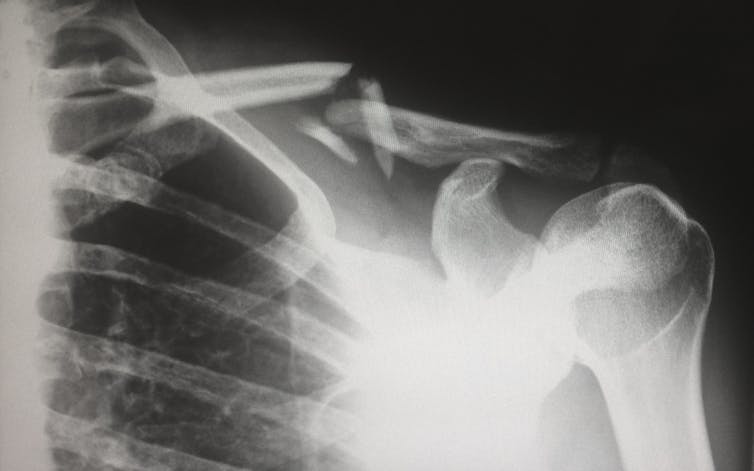
Influential medical journals serve to inform and shape health care.
Harlie Raethel for Unsplash

As such, citations play an important role in the visibility of research. Articles and authors with more citations are more likely to have a greater effect on the scientific community and patient care. Opinion pieces can shape the broader conversation among medical professionals, and citations can widen that circle of communication.

Invisible racism

We traced how frequently JAMA and JNMA opinion writers referenced one another from 2008 to 2021 by reviewing the 117 opinion pieces published in JNMA and 1,425 published in JAMA during this 13-year period. We found that JAMA opinion columns have continued to, in effect, uphold racial bias and segregation by ignoring JNMA findings.

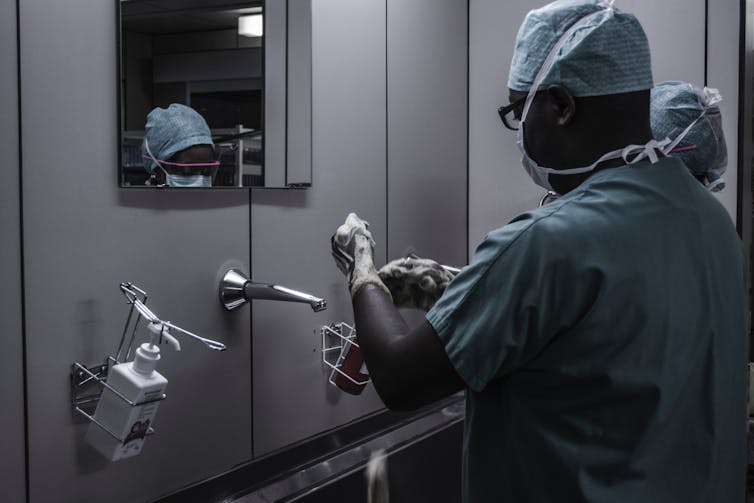
A Black medical professional adjusts gloves in front of a mirror.
The work of Black medical proessionals is being overlooked in national medical journals.
Piron Guillaume for Unsplash, CC BY-ND

Even when focusing on race, racism and health disparities, topics that JNMA has explored in great detail, JAMA opinion columns did not reference JNMA colleagues or research. Only two JNMA articles were credited and referenced in the 1,425 JAMA opinion pieces that we reviewed.

Editors at JAMA did not respond to our requests for their comments on our analysis.

Racial equity in medicine

The story of the AMA and NMA is not only a reminder of the racist history of medicine. It demonstrates how the expertise of Black professionals and researchers continues to be ignored today. The lack of JNMA citations in JAMA research undercuts the AMA’s own work on racial equity and potentially compromises the quality of medical knowledge published in its journals.

For example, a recent study in the Proceedings of the National Academy of Sciences found that scientists from underrepresented groups innovate, or contribute novel scientific findings, at a higher rate than those from majority groups.

An article published in the weekly medical journal of the Public Library of Science noted that diverse research teams are often more successful in developing new knowledge to help treat women and underrepresented patients with greater precision.

Dissolving systemic bias

One way to intentionally tackle racial bias and segregation in medical knowledge is by deliberately referencing Black researchers and their work. To change this dynamic of racial bias, medical journals must pay attention to how much and how often the Black medical establishment is referenced. Health issues in underserved communities would likely become more visible and achieve greater quality of care in keeping with the AMA’s commitment to social justice.

Journal editors could tell writers and editorial staff to prioritize citation practices. Individual authors might conduct research and evaluate their reading habits to intentionally include research from the Black medical community.

However, this work must go beyond individuals. Undoing decades of collective habits and embedded racism requires collaborations that work across systems, institutions and disciplines.

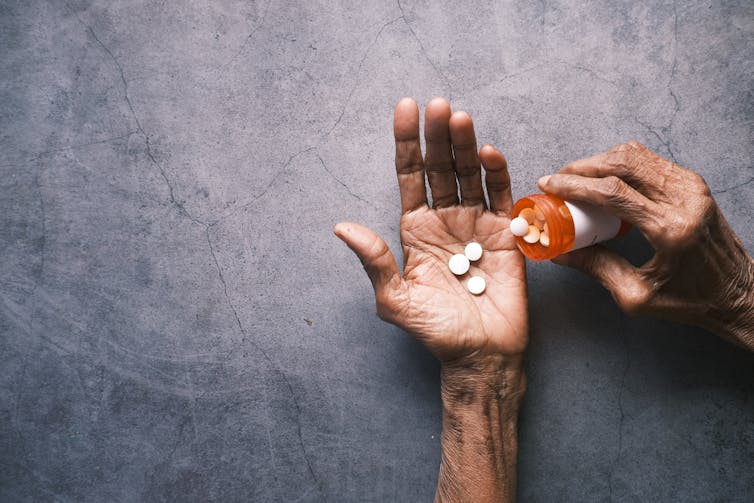
One hand holds a bottle of pills and the other hand holds three white pills.
Racial disparities in health care often result in lower-quality medical treatment and worse health care outcomes for Black Americans.
Towfiqu Barbhuiya for Unsplash, CC BY-ND

For example, libraries, databases, and search engines that help researchers find and evaluate medical publications might review today’s research tools. It is hard to contribute to a research conversation if your work is invisible or can’t be found.

Many tools, like impact factors, rank research according to how influential it is. If research begins in a category of less importance, it can be harder for the technology to rank it equitably. JNMA’s work was already marginalized when the tools that rank research were developed.

Thus, search results can hinder efforts of individual authors to work toward equitable citation practices. Black researchers and their research of Black health were excluded from the beginning, and existing systems of sharing knowledge and drawing attention to important studies incorporate that structural racism.

The AMA apology in 2008 and its recent progress on addressing racism in its publication process are promising steps. Influential medical journals serve to inform and shape health care. Who is referenced in these journals matters to the medical establishment, research funders and, ultimately, to the patients that are served by innovations in medicine.

Attention to citation can help reduce systemic bias in medical knowledge to achieve greater fairness in health care and, in the long run, help increase attention and resources that will help solve health issues in underserved communities.

Senators ponder more federal actions on health care cybersecurity

While there are experts and resources available, health care systems across the nation could use more help from the federal government to strengthen their computer networks against malicious attacks.

The U.S. Senate Committee on Homeland Security & Governmental Affairs joined the public discourse over health care cybersecurity – and the urgency of threats – on March 16. The hearing, titled “In Need of a Checkup: Examining the Cybersecurity Risks to the Healthcare Sector,” included testimony from four industry experts.

They did not suggest an easy, quick, one-size-fits-all solution to bolster protections for the computer networks physicians, clinicians, and support staff use to record patient information.

But the four panelists described the nature of the problem and why health care information is so valuable to online thieves who can sell the data, hold it for ransom, or threaten disclosure to patients. There are security measures health care workers and their supporters in government can do right now, and possible solutions that could help in the future.

Speaking to senators

The witnesses included:

  • Scott Dresen, senior vice president for information security and chief information security officer for Corewell Health
  • Kate Pierce, senior virtual information security officer for Fortified Health Security
  • Greg Garcia, executive director for cybersecurity for the Healthcare and Public Health Sector Coordinating Council
  • Stirling Martin, senior vice president and chief privacy and security officer for Epic Systems

Size matters

Large health care systems have dedicated staff who can monitor the computer networks, sometimes 24 hours a day. The experts agreed small and medium-sized health care systems don’t have enough workers to do the same.

What’s more, if an urban hospital has to shut down systems due to a cyberattack, patients usually have other nearby options to seek care. That’s not the case in rural areas, Pierce said.

“The impact on our rural communities during an attack is hard to overstate,” Pierce said. “The impact on patient safety is easy to comprehend. Delays in care can directly contribute to negative outcomes for many high-risk conditions. Facilities that continue to treat patients are challenged to provide high levels of patient care without access to patient information, safety alerts, delays in results, and other key tools.”

She suggested at least four changes that could help:

  • Create minimum, reasonable, achievable standards for cybersecurity, instead of recommendation that by necessity lag when physicians and staff must prioritize patient care.
  • Make money available, especially for small and rural hospitals.
  • The government needs better coordination of its cybersecurity efforts.
  • An emergency cyber disaster relief program would help small and rural hospitals recover more quickly from attacks.

Collaboration can help

Dresen offered two examples of collaboration and training new workers to strengthen cybersecurity.

The Michigan Health Care Cybersecurity Council convened health care organizations 10 years ago under the governor’s sponsorship to share best practices.

“It connected large systems with small systems so that you gave that connectivity and access to expertise to everybody in the state to help improve the state of the healthcare sector overall,” Dresen said. The West Michigan Center for Arts and Technology, which Peters visited last year, also offers free computer training and certifications for students to provide new talent in the health care sector, Dresen said.

Resources available

There are at least two publicly available resources for health care leaders and information technology professionals to use in developing cybersecurity plans, Garcia said.

In the Cybersecurity Information Sharing Act of 2015 Congress directed the U.S. Department of Health and Human Services (HHS), with other agencies, to develop a series of cybersecurity best practices for health systems. That work is known as the 405(d) program for the section of law, and as the Health Industry Cybersecurity Practice: Managing Threat and Protecting Patients, with 10 best practices to protect health care computer networks. An updated set of best practices is due soon this year, Garcia said.

“So this is this is partnership at its at its best, where there is consensus about what health systems need to do in cybersecurity, some of the basic blocking and tackling, not necessarily expensive, no high investment level,” Garcia said. “But some of the foundational elements of good cybersecurity practices.”

The Healthcare and Public Health Sector Critical Infrastructure Security and Resilience Partnership, an industry partner with HHS, also offers free resources to enhance cybersecurity, Garcia said.

Standards are needed

Martin agreed there is no shortage of recommendations and guidance, but taking stock of those resources and deciding what to do is another thing. He agreed a key thing is for the federal government to establish minimum thresholds for security best practices, and those thresholds must change over time.

He agreed with Pierce that, whether large or small, health care organizations are balancing lots of different competing priorities. “Trying to balance all of those different competing priorities is incredibly challenging and having that minimum target to shoot for will help make sure everyone is marching towards that target, and ultimately raise the security posture of everyone in the community,” Martin said.

The witnesses’ opening testimony is posted online. After those statements, they answered questions by Peters and committee members Sen. Kyrsten Sinema, I-Arizona; Sen. Thomas R. Carper, D-Delaware; Sen. Margaret Hassan, D-New Hampshire; Sen. Jacky Rosen, D-Nevada; Sen. Alex Padilla, D-California; Sen. Josh Hawley, R-Missouri; Sen. Richard Blumenthal, D-Connecticut. The full Committee hearing is available online.

How Fitness Trainer Erin Oprea Changed Her Body Composition At 44

After a lifetime dedicated to fitness—27 years of personal training, nine years in the Marine Corps, and two years in Iraq—I never thought my personal strength transformation journey would start at 45.

I started personal training at 18 years old (I am a Nashville-based celebrity personal trainer and founder of Pretty Muscles fitness app), and my fitness philosophy has been pretty simple: Learn to live a healthy, balanced lifestyle that you can maintain forever. Health is not a crash course. You can learn to love life while working on creating the best you. Slow and steady wins the race.

I’ve always stayed steady. I’ve never competed in fitness competitions. I never had a goal to change my own body—that is, until a series of injuries led me to start a big strength transformation journey.


How Fitness Trainer Erin Oprea Changed Her Body Composition At 44

In November 2020, I had surgery on my left heel pad, which had suddenly separated down the middle on my foot with no explanation.

It was horrible. To treat it, I went to stem cell therapy and did three platelet-rich plasma (PRP) therapy sessions. Fat was injected into the heel pad to help, as well. Then, in June 2021, I tore my ACL for the third time. In September of the same year, I tore my ACL while rehabbing from my earlier surgery. However, this time I also broke my knee cap in two. I was going from surgery, to surgery, to surgery. (Plus, I also had a boob lift!)

For about a year, my many injuries meant I had done no cardio. I was still weight training six days a week, but I was also going through perimenopause (the phase before menopause as your body starts to transition)—so my body was going through a lot. But I didn’t decide to make a big change until I was spurred by a question my son, Hunter, asked me one night. It was a question that would jump start my personal strength journey, challenging me to build lean, strong muscle and get back to where I was pre-injury.

My son asked me a simple question: whether I wanted to run a half marathon with him. I knew I couldn’t live with an answer of “no.”

After four ACL tears, a broken knee cap, and pins in my knee, I was told I would never run again. I was in physical therapy (and probably always will be) when I decided to start my journey. My 22-year-old son came to me in late June 2022 and asked if I wanted to run a half marathon with him, I said, “Man, I can’t run anymore. I’m out.”

But later that night, I couldn’t stop thinking about how I had told him, “I can’t run.” I used to be a runner, I used to do marathons. Running had always been a huge part of my life.

I have never been a big scale person and prefer to focus on how I look and feel, but I wanted to be able to run that half marathon with my son, I wanted to get back to where I was before, and I wanted to get stronger and leaner too.

So, the next morning I got up, and I got on a treadmill. “Let’s just see if I can’t run,” I said. I told myself I’d run three-fourths of a mile and just see how it felt. I finished that short jog, and I felt amazing.

I kept things slow and steady but didn’t give up.

I took a day off before attempting to run a full mile. Then, I ran 1.5 miles, then two miles…I told myself, “If I can hit seven miles and still feel good, then I’m going to do the half marathon.”

Once I realized I could conquer these shorter runs, I was on a mission. To prepare, I built up to running six to 10-mile runs, five days per week while continuing my strength training 6 days a week. I wasn’t running for time, I was running for distance.

In October of 2022, I ran my first half marathon in years.

After I accomplished my race, I wanted a new goal to zero in on. So I started a strength journey, where I also adjusted my diet to shift my body composition.

That meant, for me personally, going from an average of about 3,000 calories per day to between 2,000 and 2,100 calories—but I still made sure I had *plenty* of fuel for my workouts. (USDA guidelines recommended a range for women between 1,600 and 2,400 calories per day). I also cut my starch intake by half. (Work with a nutritionist to figure out a calorie consumption that fits your needs.)

While I don’t use anything specific to track what I’m eating, I eat the same thing pretty much 99.9 percent of the time. Breakfast, lunch, dinner—everything is exactly the same.

Pre-breakfast:

  • 20-30 ounces of water
  • AG1 supplement powder
  • Black coffee with almond milk, cinnamon, and 2 scoops of collagen
  • 1/2 peanut butter protein bar.

Breakfast:

  • Crockpot steel cut oats made with water, and topped with blueberries, strawberries and cinnamon
  • 6 egg whites

Morning snack:

  • Chocolate protein shake with water and PB2

Lunch:

Afternoon snack:

  • Veggies (peppers, mushrooms, broccoli)
  • Jalapeño honey hummus

Dinner:

  • Sweet Green Kale Mix
  • Poppyseed dressing
  • Walnuts
  • ½ pound ground turkey

Late-night snack:

  • ¼ pound ground turkey with coconut aminos
erin oprea

Erin Oprea has been on a body transformation journey.

CARLA LYNN
PHOTOGRAPHY

Since I’ve leaned out, my muscles aren’t necessarily bigger, but you can see them in a more defined way. And I can run like a MOFO—that’s what I’m really proud of.

I’m seeing results in my running time. I’ve decreased my mileage, and either run three to four miles a day, or I do 30 to 45 minutes of jump rope. Now, my goal is to get my speed back and to hit my Marine Corp running time.

I test myself every week, and last week, I hit 21 minutes and 20 seconds during a three-mile run. For context, when I first started running again, I was doing three miles in 29 minutes— I’m really proud of how far I’ve come already! My goal is 20 minutes and 15 to 20 seconds, so I’m getting there.

Living a very structured life has helped me hit my goals.

Everything is on a schedule, and I love it. I stay super active throughout the day, from 4 am until bedtime (which is usually around 8:30 p.m., but lately has been closer to 10 p.m.). I usually fit in 20,000 to 25,000 steps each day. I’ve also always been big on stretching and foam rolling, and I always use my Theragun.

For fun, my husband and I go dancing from 4 p.m. to 6 p.m. on Saturdays. One of my favorite DJs plays at a bar on Broadway, and we’re home before it’s dark.

My strength transformation helped with my health and perimenopause journey.

The coolest thing about my transformation has been the impact on my perimenopause journey. I used to have massive, puke-inducing cramps. But three months into my journey, I recognized that I was getting regular periods without side effects, which is amazing. I have had zero boob soreness and zero cramps.

I’ve also noticed reduced inflammation. I’ve struggled with tendonitis in both elbows–sometimes I can’t even hold my phone because my elbows hurt so badly. I credit this with cutting down on starches and being more disciplined about my food sensitivities like yeast (which I had tested). My body just feels good. In fact, my joints feel better now than they did when I was 30.

This content is imported from poll. You may be able to find the same content in another format, or you may be able to find more information, at their web site.

Moving forward, I’d like to maintain where I am—I feel like a million bucks right now.

My energy levels are high—and everything is great. I’ve even rediscovered my love of rollerblading!

I want other women to realize that if you want it badly enough, you can do it. And at *any* age. People are quick to find excuses and then they don’t get results. Is it easy? No. But is it worth it? Absolutely.