7 Day Healthy Meal Plan (April 10-16)

This post may contain affiliate links. Read my disclosure policy.

A free 7-day, flexible weight loss meal plan including breakfast, lunch and dinner ideas and a shopping list. All recipes include macros and Weight Watchers points.

7 Day Healthy Meal Plan (April 10-16)

Asparagus always makes me think of spring! In case you missed my post earlier this week, check out these 23 Easy Asparagus Recipes which has some of my favorites like Cream of Asparagus Soup and this Asparagus Bacon Salad. If you have an air fryer, you will love this Air Fryer Rotisserie Chicken (which can also be baked in the oven)!

With grocery prices soaring, many of us are having to adjust, scale back and/or get more creative with our meals. One of the absolute BEST ways to stay within a budget and maintain healthy eating habits is to MEAL PLAN. You can get more 5-day Budget Friendly Meal Plans by signing up for Relish+ (get a 14-day free trial here!)

Ultimate Skinnytaste Meal Planner

Skinnytaste Ultimate Meal Planner

Get the Skinnytaste Ultimate Meal Planner! The 52 week spiral bound meal planner has weekly meal planning grids you can tear out and put on your fridge if you wish, a 12-week meal plan, 30 (15 new) recipes, and tear-out grocery lists. I love starting my week with gratitude, affirmations and intentions, so I included a space for that as well. I hope you will love this as much as I do!

Skinnytaste Ultimate Meal Planner

Buy the Skinnytaste meal planner here:

A note about WW Points

All recipe points have been updated to reflect the new WW program, points will display under the recipe title. I will keep the ww button in the recipe card, click on that and it takes you to the Weight Watchers website where you can see the recipe builder used to determine those points and add it to your day (US only, you must be logged into your account). All cookbook recipes in the cookbook index are also updated!

About The Meal Plan

If you’re new to my meal plans, I’ve been sharing these free, 7-day flexible healthy meal plans (you can see my previous meal plans here) that are meant as a guide, with plenty of wiggle room for you to add more food, coffee, beverages, fruits, snacks, dessert, wine, etc. or swap recipes out for meals you prefer, you can search for recipes by course in the index. Depending on your goals, you should aim for at least 1500 calories* per day. There’s no one size fits all, this will range by your goals, your age, weight, etc.

There’s also a precise, organized grocery list that will make grocery shopping so much easier and much less stressful. Save you money and time. You’ll dine out less often, waste less food and you’ll have everything you need on hand to help keep you on track.

Lastly, if you’re on Facebook join my Skinnytaste Facebook Community where everyone’s sharing photos of recipes they are making, you can join here. I’m loving all the ideas everyone’s sharing! If you wish to get on the email list, you can subscribe here so you never miss a meal plan!

Meal Plan:

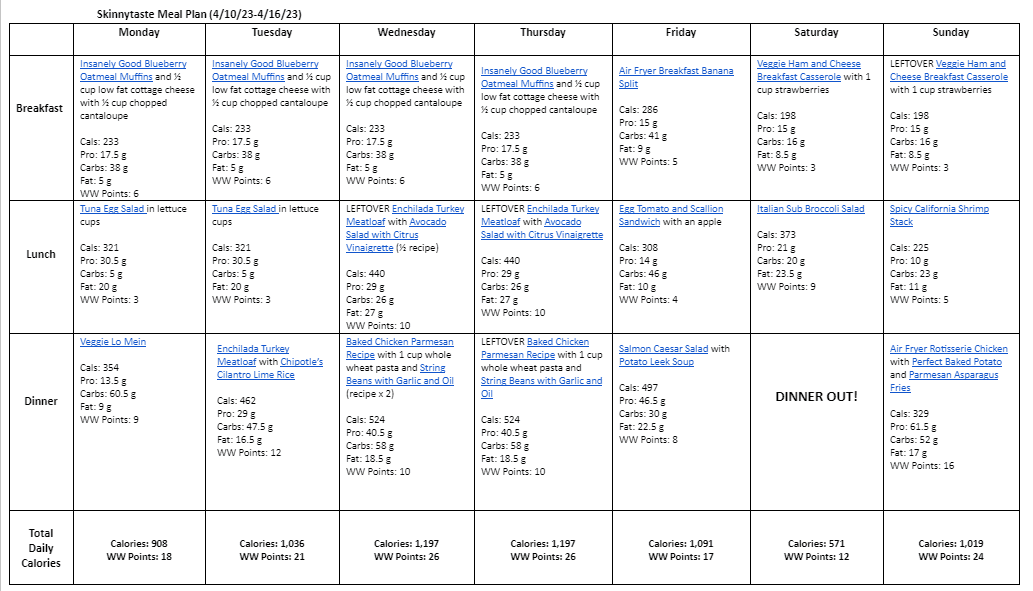
Breakfast and lunch Monday-Friday, are designed to serve 1 while dinners and all meals on Saturday and Sunday are designed to serve a family of 4. Some recipes make enough leftovers for two nights or lunch the next day. The grocery list is comprehensive and includes everything you need to make all meals on the plan.

MONDAY (4/10)
B: Blueberry Oatmeal Muffins and ½ cup low fat cottage cheese with ½ cup chopped cantaloupe
L: Tuna Egg Salad in lettuce cups
D: Veggie Lo Mein

Total Calories: 908*

TUESDAY (4/11)
B: Blueberry Oatmeal Muffins and ½ cup low fat cottage cheese with ½ cup chopped cantaloupe
L: Tuna Egg Salad in lettuce cups
D: Enchilada Turkey Meatloaf with Cilantro Lime Rice
Total Calories: 1,036*

WEDNESDAY (4/12)
B: Blueberry Oatmeal Muffins and ½ cup low fat cottage cheese with ½ cup chopped cantaloupe
L: LEFTOVER Enchilada Turkey Meatloaf with Avocado Salad with Citrus Vinaigrette (½ recipe)
D: Chicken Parmesan with 1 cup whole wheat pasta and String Beans with Garlic and Oil (recipe x 2)

Total Calories: 1,197*

THURSDAY (4/13)
B: Blueberry Oatmeal Muffins and ½ cup low fat cottage cheese with ½ cup chopped cantaloupe
L: LEFTOVER Enchilada Turkey Meatloaf with Avocado Salad with Citrus Vinaigrette
D: LEFTOVER Baked Chicken Parmesan Recipe with 1 cup whole wheat pasta and String Beans with Garlic and Oil

Total Calories: 1,197*

FRIDAY (4/14)
B: Air Fryer Breakfast Banana Split
L: Egg Tomato and Scallion Sandwich with an apple
D: Salmon Caesar Salad with Potato Leek Soup

Total Calories: 1,091*

SATURDAY (4/15)
B: Veggie Ham and Cheese Breakfast Casserole with 1 cup strawberries
L: Italian Sub Broccoli Salad
D: DINNER OUT

Total Calories: 571*

SUNDAY (4/16)
B: LEFTOVER Veggie Ham and Cheese Breakfast Casserole with 1 cup strawberries
L: Spicy California Shrimp Stack
D: Air Fryer Rotisserie Chicken with Perfect Baked Potato and Parmesan Asparagus Fries

Total Calories: 1,019*

*This is just a guide, women should aim for around 1500 calories per day. Here’s a helpful calculator to estimate your calorie needs. I’ve left plenty of wiggle room for you to add more food such as coffee, beverages, fruits, snacks, dessert, wine, etc.

*Google doc

Some ACA health insurance plans have lots of enrollees, few providers : Shots

Some ACA health insurance plans have lots of enrollees, few providers : Shots

The Affordable Care Act saw a record number of sign ups this year, but some people are having trouble finding doctors in their health plan networks.

Getty Images


hide caption

toggle caption

Getty Images


The Affordable Care Act saw a record number of sign ups this year, but some people are having trouble finding doctors in their health plan networks.

Getty Images

The Affordable Care Act may be struggling with its own success.

Record enrollment over the last two years brought more consumers into the health insurance market. At the same time, many insurers began offering smaller networks of doctors and hospitals, partly to be price competitive.

That combination left some patients scrambling to find an available in-network physician or medical facility. That can be a challenge, especially when enrollees must rely on inaccurate provider lists from their insurance company. A recent federal report found that 243 out of 375 insurance company plans reviewed by regulators failed to meet network standards.

‘The last thing she needed’

Take what happened to a central Pennsylvania policyholder, who in January fell and broke her arm and a bone near her eye.

She was directed by the hospital that provided her emergency care to follow up with an orthopedist, recounted Kelly Althouse, the patient’s insurance agent, who works near Reading, Pa. Althouse’s client spent hours calling orthopedic doctors listed in the provider directory of her new health plan from insurer Ambetter Health, a national carrier that in 2019 started offering ACA plans in Pennsylvania. Several doctors said they weren’t part of the network, despite being listed by the company, Althouse said. It took about 15 tries before her client found an in-network doctor who would see her.

That “was the last thing she needed when she was already feeling terrible,” said Althouse.

It’s a story that has been repeated to her multiple times since January, when the new plan year began. Her clients have “bombarded” her with calls, saying a range of physicians and other providers were not accepting the insurance, even if that provider was listed in the plan’s own directory. “The thing that shocked me was how many offices told my clients, ‘We have never heard of this company,'” Althouse said.

For its part, Ambetter officials said in a written statement to KHN that their network in Pennsylvania “meets or exceeds regulatory standards.”

The size of insurers’ networks of contracted doctors and hospitals, particularly in ACA plans, has long drawn concern. In recent years, insurers have trended toward offering smaller networks, in part to cut costs and keep premiums in check.

Problems arise when patients cannot find local in-network providers and must either pay more, for out-of-network care, if that’s even an option in their plans, or travel farther for in-network care.

It wasn’t supposed to be that way anymore, after new rules kicked in this year to address such issues.

More oversight, but is it enough?

For one, federal regulators are again checking whether insurers have enough providers. That comes after a 2021 court ruling that reversed a Trump administration move to eliminate such federal oversight.

In addition, new “time and distance” standards went into effect, requiring insurers to make available, within certain driving distances, at least one provider for each of a variety of physician specialties. For example, a large metro area must have enough endocrinologists for at least 90 percent of enrollees to be able to find one within 15 miles or a 30-minute drive.

Yet insurance brokers in multiple states told KHN that many clients are having trouble finding in-network providers across a variety of health plans. Even when they do, patients on some plans face “a four- to five-month wait to see a primary care doctor,” said Tracy McMillan, president of Marketplace Insurance Exchange, an insurance brokerage in the Dallas-Fort Worth area.

Under the Affordable Care Act, insurers must “ensure a sufficient choice of providers.” But there is no single nationwide standard on what to measure to determine network adequacy, and both federal and state regulators have authority to oversee the plans.

“These exchange networks have never had much rigorous oversight,” said Karen Pollitz, a senior fellow at KFF.

But access is still limited in some areas and even the standards themselves may not be tough enough, say policy experts and brokers.

“We have insurers that don’t even have a hospital in some counties,” said Lauren Jenkins, owner of Native Oklahoma Insurance, a brokerage based near Tulsa. “How do they even get approved to be in these counties?”

In a metro area no more than 40 miles across, a plan could theoretically have as few as 10 doctors and three facilities in network and still meet these standards, Pollitz said.

In Texas, North Carolina, and other parts of the country, new companies, often charging lower premiums, have entered the ACA market. Some have networks “that are very, very tiny,” said Don Hilke, owner of ClearBenefits Group in Durham, N.C. Even larger carriers are either squeezing their networks to compete on price or enrolling so many customers that they are stretching their existing networks.

‘Everyone in a pickle’

In Texas, two smaller insurance companies left the market, leaving the remaining insurers without enough doctors to absorb the policyholders who had to find other coverage, said Ronnell Nolan, president and CEO of Health Agents for America, a membership association for independent brokers. “It left everyone in a pickle.”

Federal regulators propose more changes for next year, including requiring insurers to meet appointment wait-time standards.

More has been done this year too, including reviewing insurer networks, said Ellen Montz, deputy administrator and director of the federal Center for Consumer Information and Insurance Oversight, part of the Centers for Medicare & Medicaid Services.

Insurers pegged as having a shortfall in their networks must now report monthly to CMS their “good faith efforts to fill those gaps” and how many complaints they get from consumers about access, she wrote.

Montz did not say how many insurers have fallen short, but the December report from the U.S. Government Accountability Office noted that CMS found the majority of insurance companies whose medical or dental plans were reviewed by federal regulators in August failed to meet network adequacy standards. CMS told the GAO that all plans eventually satisfied the requirements or provided “an acceptable justification as to why they were unable to meet the standards.”

Creating networks and keeping lists of participating providers up to date pose ongoing challenges, said Jeanette Thornton, executive vice president of policy and strategy at AHIP, the health insurance industry’s leading lobbying group. Those include the need to rely on providers to inform insurers when they move, retire, or stop accepting new patients.

Questions about the accuracy of provider directories persist. Dr. Neel Butala, an assistant professor at the University of Colorado School of Medicine, found that fewer than 20{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of more than 449,000 physician listings had consistent address and specialty area information across five large insurers’ directories, according to a research letter published in the Journal of the American Medical Association on March 14.

A lawsuit filed in August 2022 in the U.S. District Court for the Northern District of Illinois alleges the provider networks for Centene’s Ambetter plans “are simply false and are often just copies of physician directories from other sources.”

Without accurate directories, the lawsuit alleges, patients face “delays in treatment, inability to get treatment, traveling to see an in-network provider who is hundreds of miles away, and paying out-of-pocket for out-of-network providers.” Similar allegations are included in ongoing lawsuits first filed in 2021 by the San Diego City Attorney against three California insurers.

The “No Surprises Act,” which went into effect more than a year ago, requires insurers to update their provider directories every 90 days. No insurers have yet been penalized for failing to update theirs, said CMS’s Montz. The law also stipulates that if patients get hit with an out-of-network charge because they relied on inaccurate information, the insurer can charge the patient only the in-network rate.

In October, CMS published an official query asking for comment on whether the federal government should create its own national database of in-network medical providers, an inquiry that drew hundreds of responses, both for and against.

There has been no indication whether such a plan will move forward.

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

High-quality data enables medical research

While our focus on the pandemic has now subsided, our health data quality problems remain. We’re swimming in health data—by some estimates, one-third of all data generated in the world is related to health and health care, and that amount increases more than 30{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} every year.

With all that data, then, why can’t we answer our most pressing heath questions? Which of the five top diabetes drugs (if any) will be best for me? Will back surgery be more effective than physical therapy for my spine? What are the chances that I will need chemotherapy in addition to radiation to make my tumor go away?

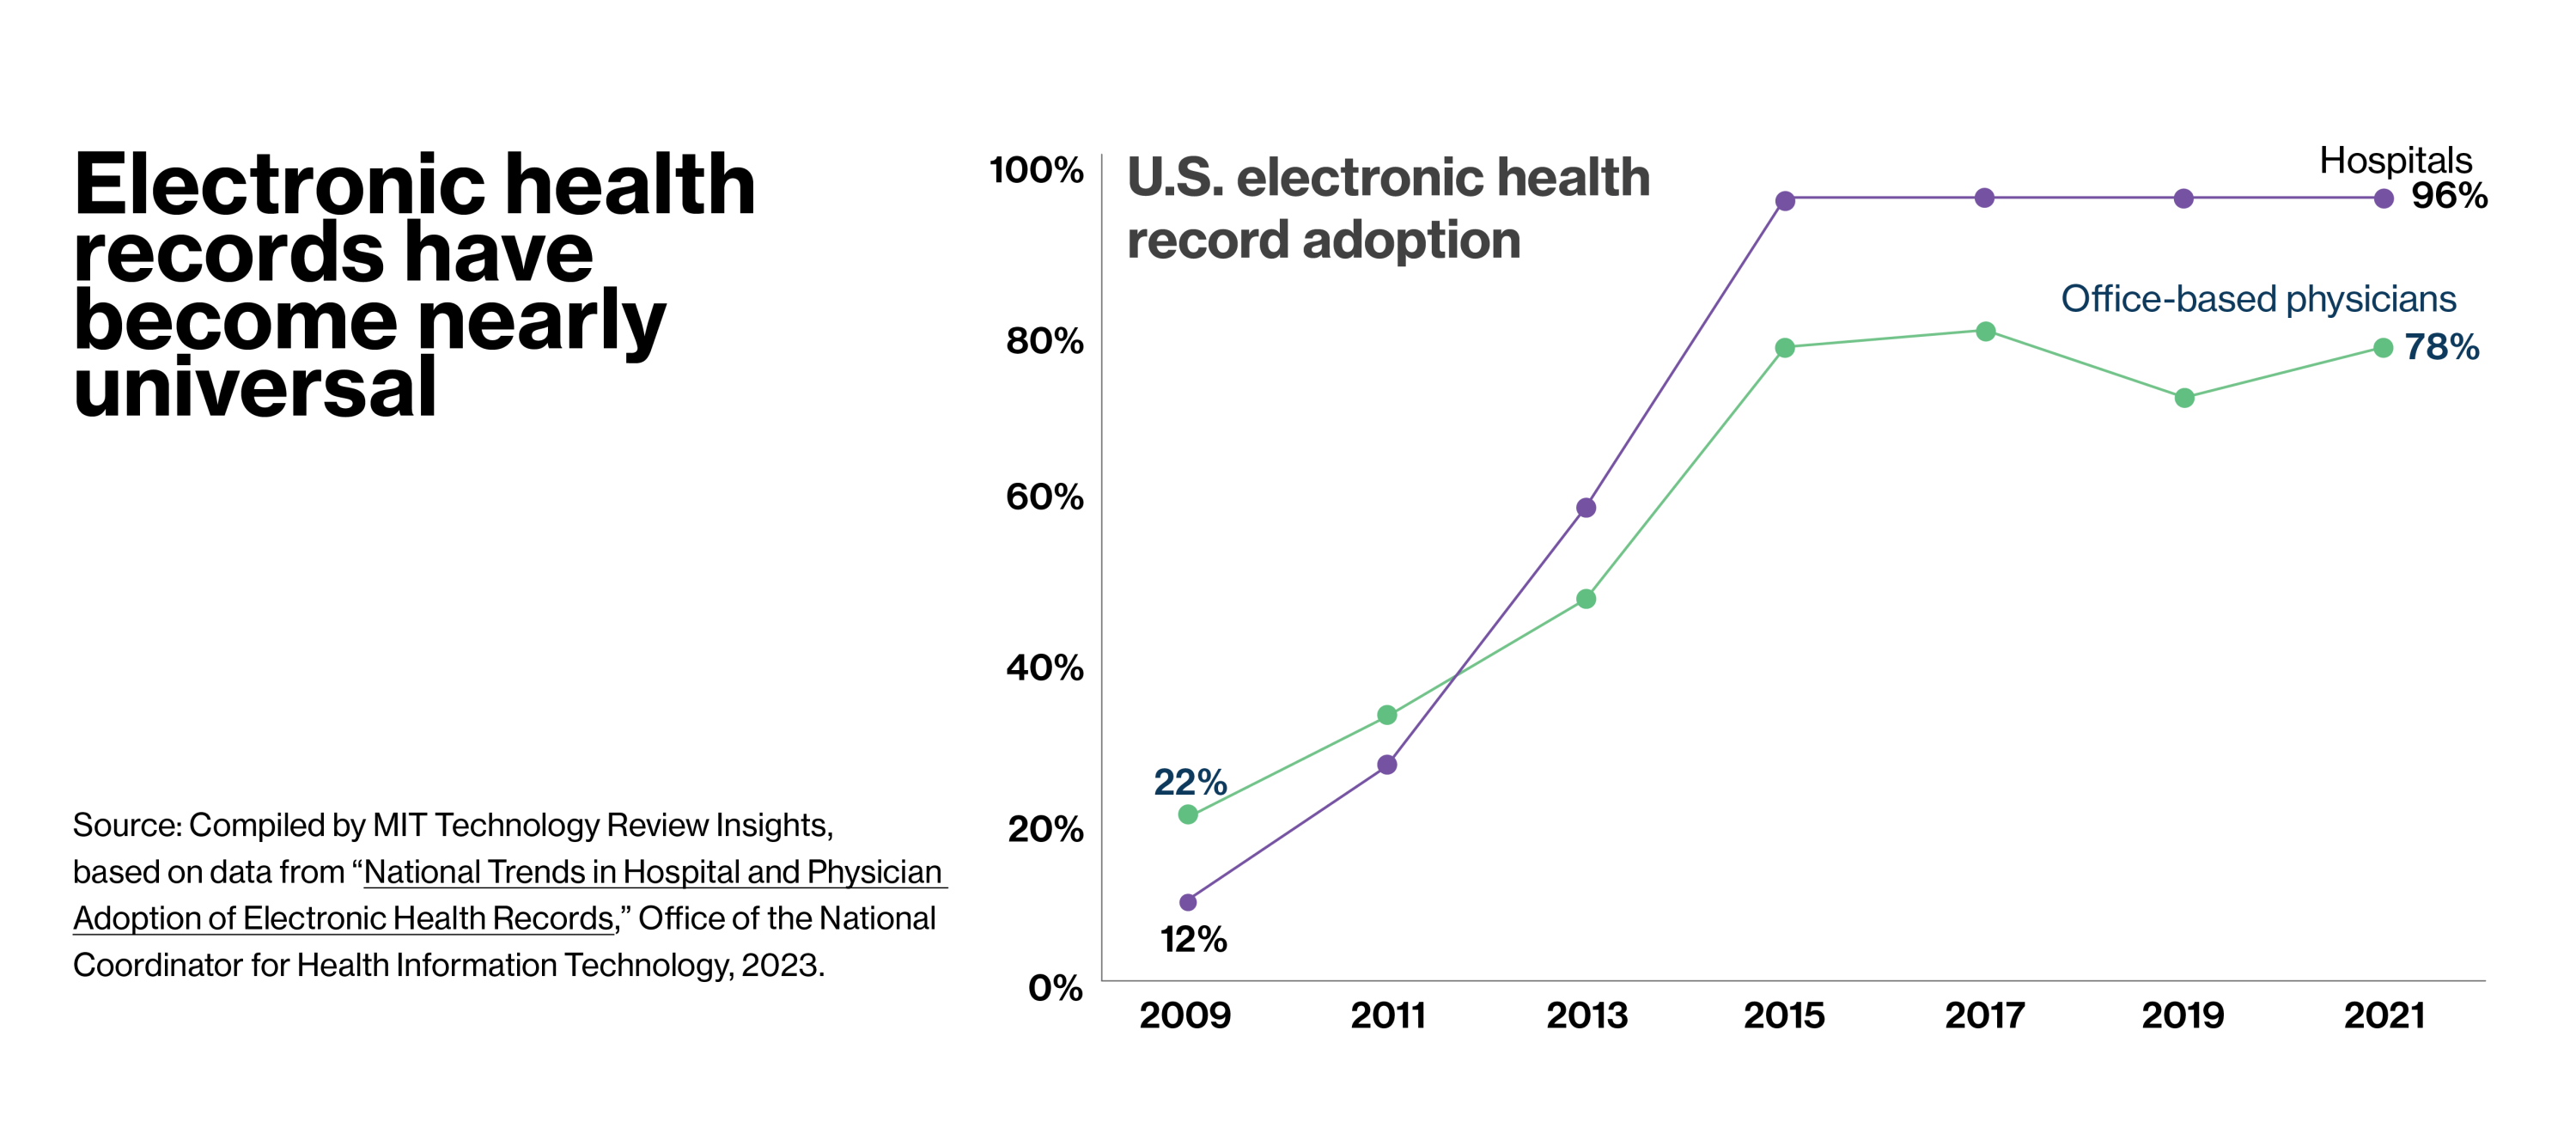
EHRs have become ubiquitous

Electronic health records (EHRs) have become pervasive in the U.S., largely thanks to a multi-billion-dollar federal initiative that made interoperable EHRs a national goal. The 2009 HITECH Act provided incentives for healthcare providers who computerized and penalties for those who did not. In addition to the improved patient care this would enable, the millions of digitized health records would create opportunities to transform medical research.

High-quality data enables medical research

“Prior to EHRs, clinical research was all on paper,” says Dale Sanders, chief strategy officer at Intelligent Medical Objects (IMO), a healthcare data enablement company that offers clinical terminology and tooling to improve the quality of medical data. “You would transfer that paper-based data to spreadsheets and do your own data analysis in a very small local environment. It didn’t give a broader view of a patient’s life, and it certainly didn’t enable any kind of broader population analysis.”

Theoretically, EHRs should make it possible to aggregate, analyze, and search through information collected from millions of patients to discover patterns that aren’t evident on a smaller scale—as well as to track a single patient’s health status methodically over time. Imagine being able to quickly compare and analyze the cases of the few thousand people who have a particular rare condition or to follow users of a certain drug over a set period of time to observe long-term side effects that weren’t obvious in trials.

Of course, it’s not that easy. “There’s a lot of raw data [in EHRs] and it’s very, very dirty,” explains John Lee, MD, an emergency physician and clinical informaticist who has served as chief medical information officer for several health systems. “Some of it isn’t accurate, and the stuff that is accurate isn’t packaged up in a way that’s usable and scalable. There is an opportunity tantalizingly at our fingertips if we could get out of our own way.”

Sanders concurs. “Covid made us all realize that the data that we’re collecting with EHRs is not very good for clinical research, or for reacting to pandemics and public health challenges. It’s time to evolve the way we’re using them.”

Download the report.

This content was produced by Insights, the custom content arm of MIT Technology Review. It was not written by MIT Technology Review’s editorial staff.

Advocates in Mass. are pushing to keep masking in health care settings

Health

Massachusetts’s COVID-19 public health emergency runs out on May 11, ending state masking requirements in health care facilities.

Advocates in Mass. are pushing to keep masking in health care settings
Public health advocates are urging Massachusetts health officials to keep universal masking in place at health care facilities. John Tlumacki / The Boston Globe, File

A coalition of public health advocates is urging Massachusetts to keep masking requirements in place in health care settings, even after the state’s COVID-19 emergency declaration runs out in early May. 

“Without universal masking precautions in healthcare, vulnerable people face substantial risk of being exposed in waiting rooms or clinical settings against their will, violating their autonomy, and deterring many from seeking much-needed care,” the Massachusetts Coalition for Health Equity wrote in an open letter last week. 

Coalition co-founder Dr. Lara Jirmanus, a family physician and Harvard Medical School instructor, explained in a virtual press conference Wednesday that removing masking requirements from health care settings will be especially risky for babies and children who can’t mask. 

“People can bring these infections home to their loved ones and hurt them,” Jirmanus said. “And I will say personally, as a parent of a 16-month-old baby, this is part of my calculation.”

In September, the Centers for Disease Control and Prevention revised its guidelines to relax masking requirements for health care facilities in parts of the country with lower levels of community transmission. (In Massachusetts, state masking requirements remained in health care settings even after the CDC change.)

Relying on community transmission data to dictate masking is flawed, Jirmanus asserted, citing underreported cases. 

According to the coalition’s letter, “far fewer people are testing for COVID-19 as much required routine testing has ended, federal funding for COVID-19 testing has diminished, and most rapid tests are not reported. Further, most low-wage workers don’t have paid sick time, and many are incentivized or compelled to go to work with COVID-19, or to avoid testing.”

The group cited data from the Institute for Health Metrics and Evaluation, whose director estimated in September that only 4{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} to 5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of COVID-19 infections are actually reported. 

Even when transmission rates are low, clinics and hospitals will still be an epicenter for COVID-19 patient care, creating opportunities for the virus to spread, according to the coalition’s letter. Removing masks from health care settings also puts providers at risk at a time when the health care system is overrun with staffing shortages, the group argued.

A spokesperson for the state’s Executive Office of Health and Human Services told The Boston Globe that the state health department will continue to track COVID-19 cases and make adjustments as circumstances change. 

The spokesperson also told the Globe that infection control leaders at several of the largest hospital systems in Massachusetts have repeatedly asked state health officials to end the mask mandate.

The Massachusetts Coalition for Health Equity remains unconvinced. 

“We are wondering, when we take a look at that Globe article, why have hospital administrators been lobbying to remove masks? Is this about the money?” Jirmanus asked. “It doesn’t make sense. Removing masks in health care … is going to cause health worker outbreaks and it’s going to exacerbate existing staffing shortages and thereby exacerbate the budget crisis.”

She added: “We all have a loved one in our lives who could be hurt by a COVID infection. … and we could all be harmed by long COVID. So let’s be safer together.”

Tocabe Co-Founder Ben Jacobs Appointed to President Biden’s Council on Sports, Fitness, & Nutrition

It’s already been a busy year for Ben Jacobs, co-founder of Tocabe: An American Indian Eatery. Early in 2023, he helped launch a direct-to-tribe ready meal program in partnership with Spirit Lakes Nation in North Dakota; and now Jacobs has been appointed to President Joe Biden’s Council on Sports, Fitness & Nutrition (PCSFN).

“I am still in so much shock, and I am trying to understand what they want to see out of the mission,” Jacobs says. “I can say, on a surface level, I want to help support getting Native foods from Native producers and make those ingredients accessible to our members.”

Bringing nutritious and Native foods to American Indian tribes has long been a goal for Jacobs, an Osage Nation member, who started the fast-casual Native American eatery Tocabe in 2008 with his partner, Matt Chandra. Not only are the nutrient-rich ingredients on the menu such as bison, tepary beans, wild rice and Indian blue corn sourced from Native American farmers, but Tocabe also hosts an online marketplace, selling the foods to those who can’t get to the restaurant’s locations in the Berkeley neighborhood and in Greenwood Village.

As for this latest move, Jacobs says the PCSFN advisory position came down through the grapevine thanks to Daron Carreiro, a citizen of the Chicksaw Nation serving as the Senior Policy Advisor for Native Affairs on the White House Policy Council.

click to enlarge Tocabe Co-Founder Ben Jacobs Appointed to President Biden’s Council on Sports, Fitness, & Nutrition

The buffalo at Tocabe comes from Native American farmers.

Rachel Greiman

“I looked at the names and thought it was fun to have my name thrown in, because it’s all professional athletes and coaches,” notes Jacobs, who shares the job with former MLB player Ryan Howard, Olympian gold medalist Chloe Kim, basketball player Stephen Curry and his wife, actress Ayesha Curry. “I thought it was neat they were bringing people in from the culinary world, too, not just sports and fitness, so we are hearing the voices not just of professional athletes, but those on a more grassroots outlook too.”

Overall, Jacobs says the process happened pretty quickly, explaining that he’d almost forgotten he was a contender before getting an email asking for more information about himself. Two days later, on March 24, he learned that he’d made the team. He’s still filling out paperwork and waiting to find out more information on what he can do and what’s expected of him in the role, which officially starts sometime in May or June, according to Jacobs.

“‘Excited’ isn’t the term, but I think, just because it feels like there are so many things I want to see, I have to figure out where I should start in order to make this [position] genuinely impactful and not just an image-based position for myself,” says Jacobs. “I am excited to expand the network of opportunity to make significant change.”

The President’s Council on Sports, Fitness & Nutrition is a federal advisory committee aimed at promoting healthy eating and physical activity for all Americans, regardless of background or ability. The first iteration of the program started in 1956 under President Dwight Eisenhower, when it was called the President’s Council on Youth Fitness.

“The fact that my name was thrown in the mix shows the work we try to do at Tocabe is impactful,” adds Jacobs. “It doesn’t go unnoticed, even if we don’t see [the outcome] every day.”

Tocabe is located at 3536 West 44th Avenue and 8181 East Arapahoe Road in Greenwood Village. For more information, visit tocabe.com.

COVID-19 Related Medical Devices: FDA Finalizes Transition Plan Guidance

On March 27, 2023, the U.S. Food & Drug Administration (FDA) released two final guidance documents to assist with transitioning medical devices: (i) that were subject to certain enforcement policies issued during the COVID-19 Public Health Emergency (PHE), and (ii) that were issued emergency use authorizations (EUAs). These guidance documents finalize the corresponding draft guidance documents that were issued on December 23, 2021. In a previous post, we discussed several key takeaways from the draft versions of these transition guidance documents.

“Transition Plan for Medical Devices That Fall Within Enforcement Policies Issued During the Coronavirus Disease 2019 (COVID-19) Public Health Emergency” Final Guidance

In the “Transition Plan for Medical Devices That Fall Within Enforcement Policies Issued During the Coronavirus Disease 2019 (COVID-19) Public Health Emergency” final guidance, the FDA discusses the transition plan for medical devices that were subject to certain enforcement policies issued during the PHE. FDA confirms that the policies listed in the guidance, which are set forth in List 1 thereto, will remain in effect until 180 days after the end of the PHE. The PHE declaration is scheduled to expire on May 11, 2023. Therefore, the enforcement policies identified in List 1 will no longer be in effect after November 7, 2023.

In the guidance, the FDA provides recommendations for a “phased transition process” with respect to devices that fall within the expiring COVID-19 PHE enforcement policies. The FDA summarizes the three phases of the 180-day transition plan as follows:

  • Phase 1 (May 11, 2023): Manufacturers should follow adverse event reporting requirements as described in 21 C.F.R. § 803.
  • Phase 2 (August 9, 2023): If planning to continue to distribute their devices after Phase 2, manufacturers need to adhere to registration and listing requirements (21 C.F.R. § 807 Subparts B-D) and should adhere to requirements associated with reports of corrections and removals (21 C.F.R § 806).
  • Phase 3 (November 7, 2023): In Phase 3 the enforcement policies identified in List 1 will no longer be in effect. FDA states it does not intend to object to continued distribution of devices where a required marketing submission has been submitted and accepted by FDA before the start of Phase 3, and FDA has not taken a final action on the marketing submission. FDA further indicates that it does not intend to object to the devices not complying with certain unique device identification (UDI) systems requirements and other applicable labeling requirements described in 21 C.F.R. § 801.

FDA recommends manufacturers submit a “Transition Implementation Plan” with their marketing submissions (if needed) that addresses the manufacturer’s plans for addressing devices already distributed, which plans need to include actions to be taken in the event either a positive or negative decision by the FDA on the marketing submission. Furthermore, FDA strongly encourages manufacturers to complete and submit these submissions well in advance of the start of Phase 3. This is recommended to avoid potential delays created by a large influx of new submissions.

“Transition Plan for Medical Devices Issued Emergency Use Authorizations (EUAs) Related to Coronavirus Disease 2019 (COVID-19)” Final Guidance

In the “Transition Plan for Medical Devices Issued Emergency Use Authorizations (EUAs) Related to Coronavirus Disease 2019 (COVID-19)” final guidance (“EUA Guidance”), the FDA confirms that the end of the PHE will not automatically terminate EUAs. Instead, these EUAs will remain in effect until the relevant EUA declaration is terminated, or the FDA otherwise revokes a specific EUA. 

The EUA Guidance includes recommendations for certain reusable life-supporting or life-sustaining devices, devices distributed after the EUA termination date, laboratory developed tests, and EUA-authorized in vitro diagnostics subject to Clinical Laboratory Improvement Amendments of 1988 categorization and waivers. With respect to certain reusable life-supporting or life-sustaining devices, FDA requests manufacturers of such devices to submit information regarding whether or not they intend to submit marketing submissions to continue distributing the device(s) after the applicable EUA termination date.

Furthermore, FDA states in the EUA Guidance that it will not object to the continued distribution of devices after the device’s applicable EUA termination date if (1) the manufacturer has submitted a marketing submission that is accepted by FDA prior to the EUA termination date, and (2) FDA has not taken final action on the marketing submission. Therefore, it is recommended that manufacturers of these devices submit marketing submissions well in advance of the EUA termination date.

Foley is here to help you address the short- and long-term impacts in the wake of regulatory changes. We have the resources to help you navigate these and other important legal considerations related to business operations and industry-specific issues. Please reach out to the authors, your Foley relationship partner, or to our Health Care Practice Group with any questions.