While our focus on the pandemic has now subsided, our health data quality problems remain. We’re swimming in health data—by some estimates, one-third of all data generated in the world is related to health and health care, and that amount increases more than 30{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} every year.
With all that data, then, why can’t we answer our most pressing heath questions? Which of the five top diabetes drugs (if any) will be best for me? Will back surgery be more effective than physical therapy for my spine? What are the chances that I will need chemotherapy in addition to radiation to make my tumor go away?
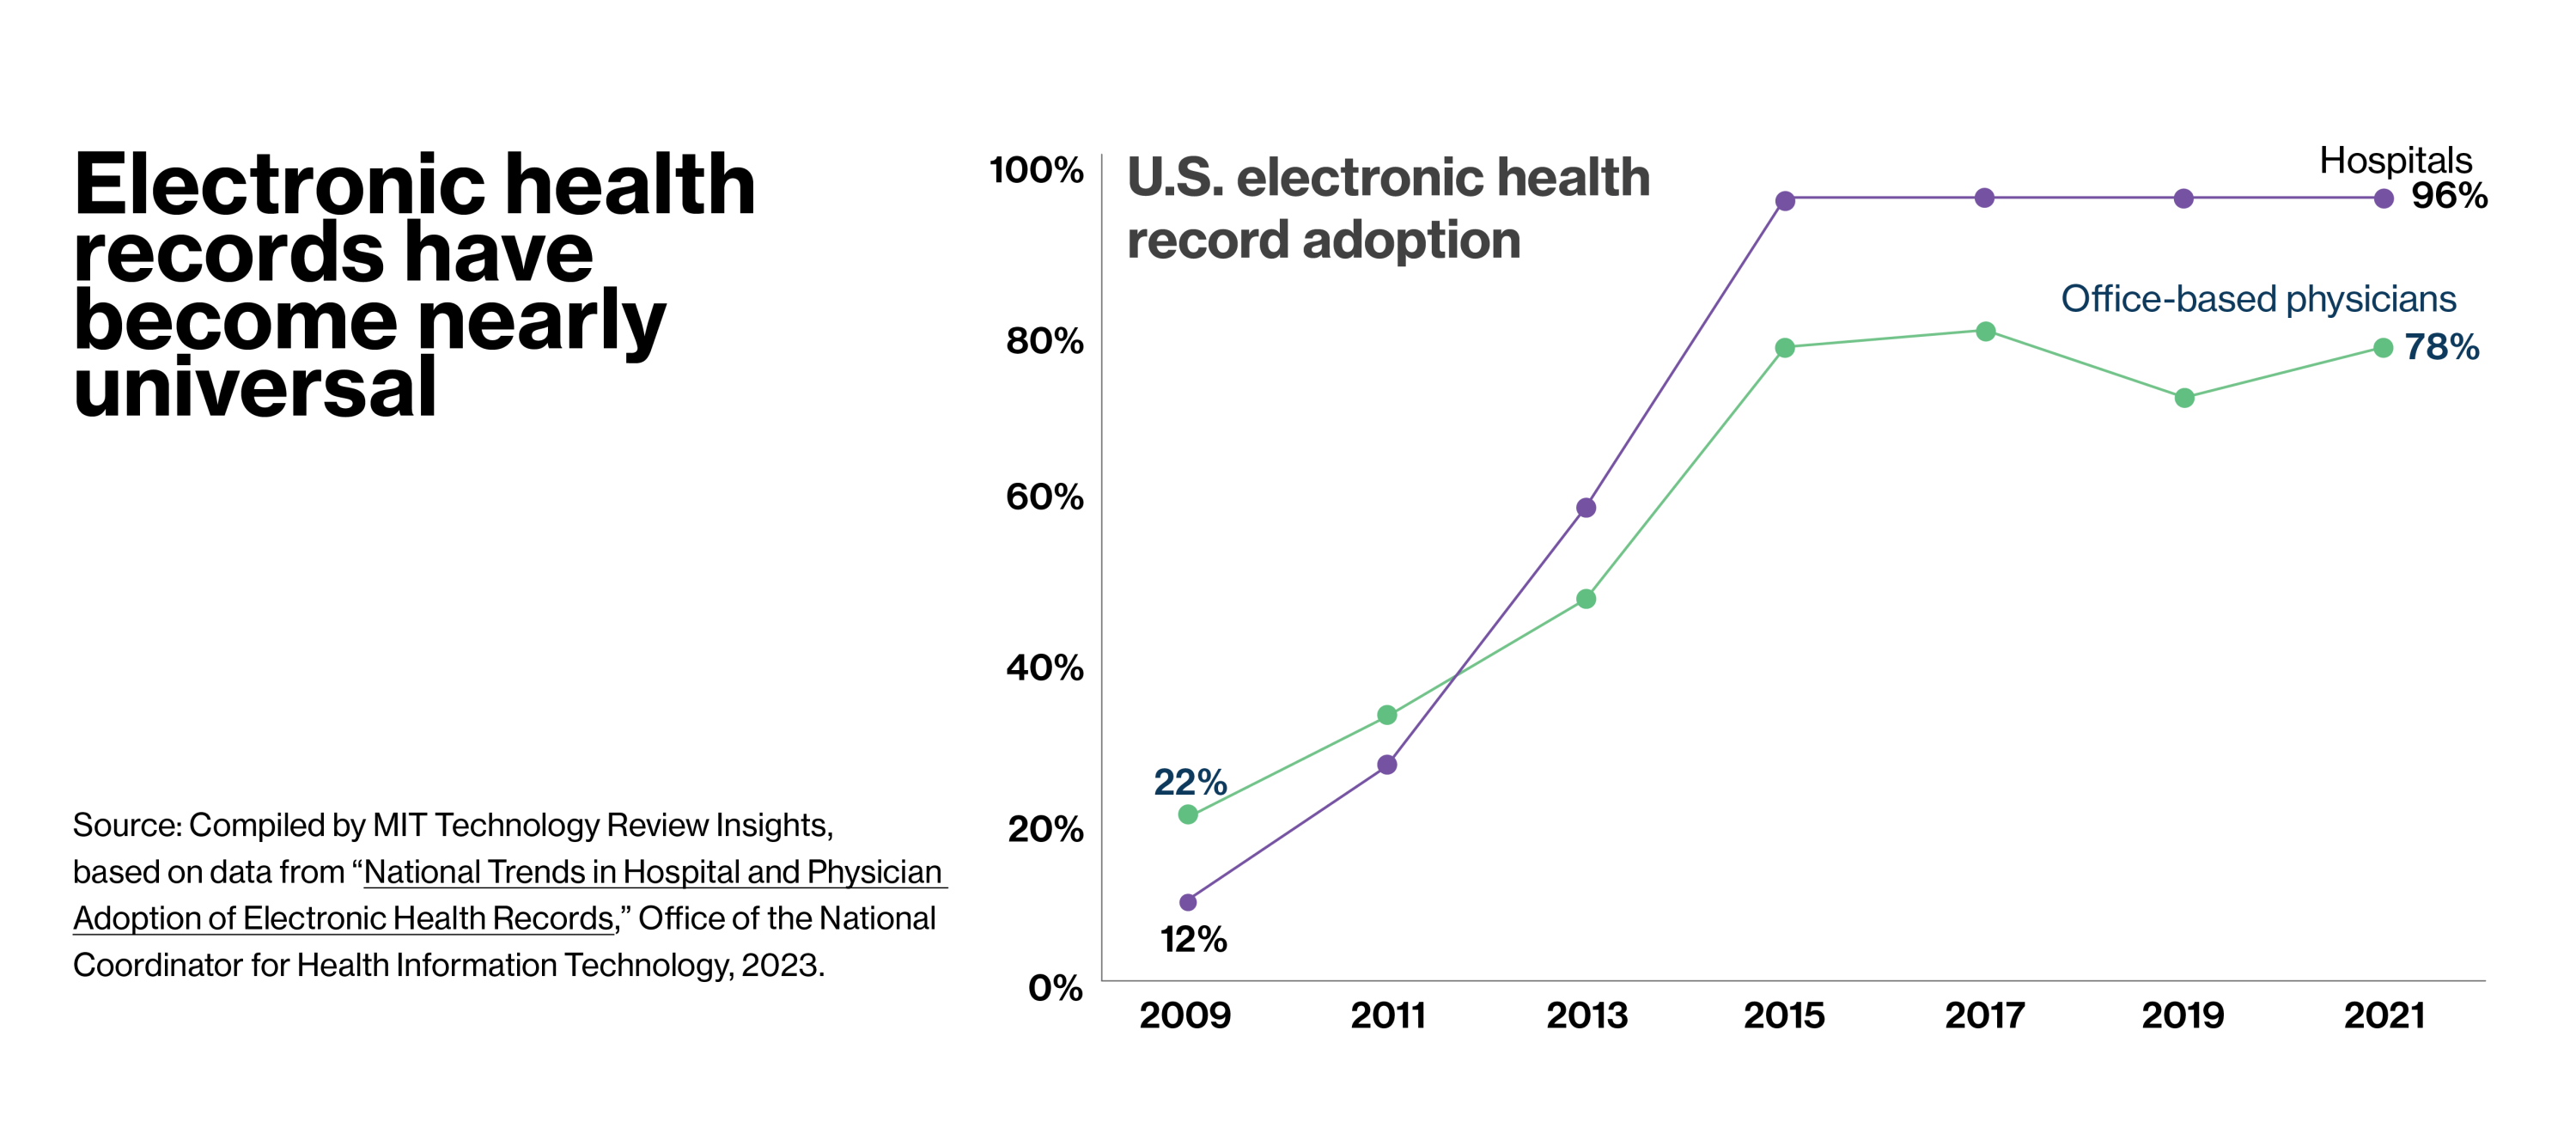
EHRs have become ubiquitous
Electronic health records (EHRs) have become pervasive in the U.S., largely thanks to a multi-billion-dollar federal initiative that made interoperable EHRs a national goal. The 2009 HITECH Act provided incentives for healthcare providers who computerized and penalties for those who did not. In addition to the improved patient care this would enable, the millions of digitized health records would create opportunities to transform medical research.
“Prior to EHRs, clinical research was all on paper,” says Dale Sanders, chief strategy officer at Intelligent Medical Objects (IMO), a healthcare data enablement company that offers clinical terminology and tooling to improve the quality of medical data. “You would transfer that paper-based data to spreadsheets and do your own data analysis in a very small local environment. It didn’t give a broader view of a patient’s life, and it certainly didn’t enable any kind of broader population analysis.”
Theoretically, EHRs should make it possible to aggregate, analyze, and search through information collected from millions of patients to discover patterns that aren’t evident on a smaller scale—as well as to track a single patient’s health status methodically over time. Imagine being able to quickly compare and analyze the cases of the few thousand people who have a particular rare condition or to follow users of a certain drug over a set period of time to observe long-term side effects that weren’t obvious in trials.
Of course, it’s not that easy. “There’s a lot of raw data [in EHRs] and it’s very, very dirty,” explains John Lee, MD, an emergency physician and clinical informaticist who has served as chief medical information officer for several health systems. “Some of it isn’t accurate, and the stuff that is accurate isn’t packaged up in a way that’s usable and scalable. There is an opportunity tantalizingly at our fingertips if we could get out of our own way.”
Sanders concurs. “Covid made us all realize that the data that we’re collecting with EHRs is not very good for clinical research, or for reacting to pandemics and public health challenges. It’s time to evolve the way we’re using them.”
Makers, via a loophole in federal regulation, can use an unsafe professional medical product as a basis for authorization by the U.S. Food stuff and Drug Administration (Fda) to bring new, associated products and solutions to market place, a Yale-led analyze finds.
Fda authorization for most health-related products is dependent on the products’ similarity to devices previously on the industry, and brands are normally allowed to bypass medical testing by setting up on prior Fda approvals. Nevertheless, the new review located that some medical equipment get to the sector based on their similarity to equipment that have been recalled, including products that had been topic to what is acknowledged as a Course 1 remember, a Food and drug administration designation that warns that use of the gadget may possibly trigger clients harm or demise. Earlier investigate has discovered illustrations of significant affected person hurt from products that had been licensed utilizing flawed equipment.
For the review, investigators from Yale, Harvard, and the University of California-San Francisco, reconstructed the regulatory record of all medical equipment that ended up subject matter to Class 1 recalls from 2017 via 2021 and located that safety troubles were being pervasive. Notably, they uncovered that 44{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of recalled equipment were being associated to older gadgets that had been topic to before Course 1 remembers, and somewhere around 1 in 4 of these earlier units have been recalled right before the Food and drug administration accepted the following era of devices.
Moreover, these new products generally supported the authorization of more devices which also have been afterwards recalled.
Some recalled products that had obtained authorization dependent, in portion, on formerly recalled products include things like an infusion pump utilized to management the shipping and delivery of IV fluids and medication for medical center clients an synthetic shoulder machine, utilized in shoulder replacements, that cited seven former units that have been issue to some kind of remember and an intra-aortic balloon pump, used briefly in patients hospitalized for coronary heart failure, that was connected to an previously products which was subject to a number of recollects — including a Class 1 remember just two months right before the new product was accepted.
“Whilst regulators have been aware of this loophole for several years, our review is the very first to systematically characterize the harms to affected person basic safety,” mentioned Dr. Harlan Krumholz, the Harold H. Hines Jr. Professor of Medication (Cardiology) and director of the Yale Heart for Outcomes Investigation and Evaluation (Main) at Yale College of Medication (YSM). “To be apparent, this is not an Fda difficulty, but is about the regulation that governs Fda actions.”
To illustrate the effect of preceding recollects on long run recollects, the staff when compared the remember prices amid gadgets related to recalled gadgets with recall costs amid units relevant to products that ended up recall-cost-free. They found that units authorised working with recalled devices were being a lot more than 6 times as probably to be topic to a Course I remember.
“Numerous individuals and clinicians may perhaps be unaware that Food and drug administration rules allow new gadgets to use recalled predicates. This loophole has severe effects,” explained Harvard Healthcare School’s Kushal Kadakia. “Our effects clearly show how working with unsafe products as the foundation for a new approval raises upcoming risks to affected person security.”
David Goldhill is the chief executive of SesameCare.com, a digital marketplace for discounted health services.
The United States spends twice as much per person as other wealthy countries on health care. This fact is well-known, and when it is mentioned, people often point out that the governments of other developed countries leverage purchasing power to drive cheaper, more universal care. So why doesn’t the United States do the same thing?
Because we can’t. In fact, the do-what-everyone-else-does option is uniquely unavailable to us.
The world’s other health-care systems survive only because they receive a massive and ongoing, but hidden, subsidy courtesy of the inefficient U.S. system. Two unique features of our arrangement — the absence of price controls and the profit drive of doctors and hospitals — allow other countries to transfer the risk and cost of medical innovation to Americans.
And unlike in any other industry, once Americans have borne the costs of lifesaving breakthroughs as well as incremental improvements in tools and techniques, these can be used elsewhere at little extra cost. American exorbitance allows other nations to offer price-controlled universal care with none of the decline in quality, technology or productivity that would otherwise result from central planning.
A similar complaint has been made about the country’s defense alliance: U.S. allies ride free on American defense spending. Health care, indeed, is a kind of second NATO.
The United States can’t lower its costs by doing what other countries do, because what others do depends on our unique system remaining as is. Our only hope is to put in place more sensible economic structures that could introduce the competition that’s necessary to bring prices down.
The size of the U.S. health-care system is almost impossible to overstate. With barely four percent of the world’s population, the United States accounts for almost half of the world’s $8 trillion health-care economy. England’s National Health Service is tiny by comparison — barely bigger than U.S. Veterans Affairs health system funding. Canada’s total spending is comparable to the revenue of a single American company, United Health. Free-market star Singapore spends only as much as New Jersey’s Medicaid program.
The world’s top 10 spenders in pharmaceutical products
In 2020, the United States spent more on pharmaceutical products than all other nine spenders in the ranking combined.
All other top 9
countries combined
Notes: Prices are reported at the ex-manufacturer level (price when sold from manufacturer to wholesaler or direct to pharmacies). * Hospital market only. **Pharmacy market only.
The world’s top 10 spenders in pharmaceutical products
In 2020, the United States spent more on pharmaceutical products than all other nine spenders in the ranking combined.
All other top 9 countries combined
Notes: Prices are reported at the ex-manufacturer level (price when sold from manufacturer to wholesaler or direct to pharmacies). * Hospital market only. **Pharmacy market only.
This is why all health-care innovators — makers of drugs, devices, diagnostics, medical software — share the same business plan: Make money in the United States and take whatever scraps you can get in the other markets.
The pharmaceutical industry earns almost 50 percent of its worldwide revenue here, as do medical information-technology firms. Device makers earn 40 percent of their money in the United States. And this understates things, because U.S. revenue is generated from higher prices, so margins are greater. If the United States accounts for half of a company’s revenue, it probably contributes at least 75 percent of its profits.
America’s domination might not seem obvious. After all, high-tech health care exists everywhere in the world. Even in emerging economies, brilliant researchers, great universities and advanced companies perform cutting-edge research. Many have close relationships with their countries’ health-care systems, and some innovations are introduced in other nations. But the profit opportunity — the reason to invest — is always generated in the United States.
Consider the well-known miracle drug Gleevec. Before it came along in 2001, less than 30 percent of patients diagnosed with chronic myelogenous leukemia survived at least five years; today, 90 percent do.
Gleevec is also a poster drug for American dysfunction. Novartis steadily raised its price in the United States — even after its patent expired — to eventually reaching more than $123,000 per year in 2020. Yet, in Canada, Gleevec was priced at $38,000. A generic version in India now costs just $400.
Drugmakers and their opponents argue over the “fair” returns on innovation that companies need to maintain their incentive to invest in new medicines. Critics point to the share of pharma’s profits that come from barely legal anticompetitive behavior or from drugs created with heavy public support — such as the U.S. government’s $12 billion investment in coronavirus vaccines.
But enormous returns on a few blockbuster drugs compensate for drugmakers’ many unsuccessful products. That’s the business model, and these big, “unfair” returns are available only in the United States.
If the world’s largest health economy limited drug companies to “fair” returns — as other countries try to — then few new drugs would be created. The United States doesn’t pay $123,000 a year for Gleevec despite Canada paying only $38,000; Canada can pay $38,000 only because the United States pays $140,000.
And while pharmaceuticals might be the most obvious area in which the U.S. economy drives innovation, the $3.5 trillion we spend on care other than drugs makes an even greater contribution to world health-care advances.
In 2000, Intuitive Surgical Systems introduced the first commercially successful robotic surgery system. The company’s da Vinci robots carry $2 million price tags plus costly service contracts. In the first 20 years, 6,000 of the robots were sold worldwide, and American hospitals purchased roughly two-thirds of them.
Why? In the United States, the prices charged by hospitals and doctors are unrestricted. American physicians earn roughly two to three times as much as their counterparts in western Europe. Hospitals charge two to five times as much for their services.
The obvious, if rarely asked, question is: Why doesn’t competition bring U.S. health-care prices down? The answer: America’s stagnant third-party payment system allows hospitals and doctors to avoid competing on price. Instead, they compete on innovation. This is why hospitals advertise advanced, high-tech cancer therapies; surgeons build reputations for cutting-edge procedures; and even your family physician must invest to keep up.
Right now, we’re stuck. We want what every other country has. American reformers believe we’re just one clever policy tweak away from getting it — perhaps by instituting accountable care or “value-based” care.
But the only way to lower U.S. health-care costs is to rethink the system’s top-down policy structures that rely on huge, centralized payers.
What’s needed is a way to separate the safety net function that insurance provides from consumer decision-making. If insurance covered only major and unanticipated health problems, a consumer economy could drive competition in the rest of the system. This would give doctors and hospitals an economic incentive to bundle services, enhance efficiency, reduce waste and offer genuinely “value-driven” care.
In this century, the world has seen the democratization of many services considered “too complicated” for consumers — computers, finance, international travel, furniture construction, you name it. All this happened because people had enough control over their own spending to drive competition among innovators. It’s how industry managed to put supercomputer power in everyone’s pocket, while reducing price by 99 percent.
Until the same kind of competition is introduced in health care, the U.S. system will continue to subsidize the world — and cost us a fortune.