At least for those manufacturers that struggled for a long time printing Instructions for Use (IFU’s) without seeing the benefit. Manufacturers of devices such as medical device software, medical devices fitted with a built-in system visually able to display the IFU visually, fixed installed medical devices and implantable and active implantable medical devices.
But what is expected from the manufacturer to comply with this regulation and the medical device regulation (EU) 2017/745?
What do they mean by accessories?
Who is defined as a professional user?
Clarifying these questions is essential for manufacturers who want to stay on the right side of the rules.
Regulation 2021/2226 highlights
The regulation 2021/2226 specifies which medical devices an e-IFU is approved to be the sole IFU – meaning no paper IFU is required. The goal is to decrease the environmental burden and reduce costs linked to paper IFU’s. It also aims to retain and improve levels of safety, with users still able to receive a paper IFU upon request.
Article 3 is the most interesting. It specifies which devices can benefit from the paper IFU exemption.
Implantable and active implantable medical devices and their accessories (cfr. MDR) are covered. But only under the following conditions:
Devices and accessories are used by professionals
The use by other persons is not reasonably foreseeable
An e-IFU is only allowed if the risk assessment covers elements including knowledge and experience, the environment in which the device is used and protection against tampering.
Medical device regulation (EU) 2017/745 highlights
What is the link with the MDR?
The MDR is the umbrella under which regulation 2021/2226 falls. It gives the manufacturer detailed explanations on the different definitions. In addition, it provides insights on the elements needed in the IFU and e-IFU (MDR, annex I, chapter III).
Those definitions are as follows:
‘Instructions for use’ means the information provided by the manufacturer to inform the user of a device’s intended purpose, proper use and of any precautions to be taken;
“Implantable device” means any device – including a partially or wholly absorbed one – intended either for introduction into the human body or for replacement of an epithelial surface or the surface of the eye. An implantable device is introduced via clinical intervention and remains in place after the procedure. Devices that are partially introduced by clinical intervention and remain in place for a month or more also meet the definition.”
‘Active device’ means any device the operation of which depends on a source of energy other than that generated by the human body for that purpose, or by gravity, and which acts by changing the density of or converting that energy. However, devices that transmit energy or substances between an active device and the patient without any significant change do not meet the definition. Software is also deemed to be an active device.
An accessory for a medical device is defined in relation to true medical devices: it must be used together with one or more medical devices to enable their use, in accordance with their intended purpose. It may also specifically and directly assist the medical functionality of the medical device in terms of its intended purpose.
For many manufacturers though, the definition of ‘accessory for a medical device’ causes much confusion for a number of important reasons.
First of all, not every instrument that is used during an implant surgery is automatically an accessory. It must enable or assist the device in its intended purpose. For example, a trial model, used during surgery, in order for the surgeon to check whether or not the proposed implant will fit inside the body. This model is used prior to placing the implant itself, for sterility reasons. Although this model is a medical device, and briefly an invasive one, it does not enable or assist the implant itself.
Tools used during the surgery such as saws, drills and guides to position the screws are another example. Although used in assisting the surgery, they do not enable or assist the implant in its intended purpose.
However, the screws used to place the implant do not have any other function aside from enabling the implant to stay in its place – and are therefore an accessory for an implant. It is the intended purpose of the screws that means they are defined as accessories for an implant, or a medical device on its own. This definition and the explanation of it must be clearly defined in a definition statement or classification rationale, as part of the technical documentation.
Dental implants have many accessories such as rings, caps, housings.
Clear examples, which the MDCG notes, are accessories for cochlear implants.
Accessories to active implantable devices, with or without contact to the heart, are another example, whether or not they are implantable:
· torque wrench for pulse generators and cardioverter defibrillators
· cables for programmer / pacing system analyser
· magnets for pulse generators and cardioverter generators
· programmers to control an implantable device
· implantable pacemaker leads
If it is clear that your device is an accessory for a medical device, it must also comply with the whole of the MDR in the same way as a medical device. This means it also needs full technical documentation – including an IFU. The manufacturer should have a clear definition statement, including a classification rationale, to clearly identify why it is an accessory for a medical device.
Additionally, the manufacturer should have a written rationale if they are opting purely for an e-IFU. It is important to note that a rationale on its own is insufficient; a thorough risk analysis on the use of an e-IFU and lack of paper IFU is required.
Conclusion
Even though the new regulation on e-IFU is clear, it is not always clear for manufacturers if their device meets the definitions. The medical device regulation sheds some light on the definitions, but it is up to the manufacturer to make sure their devices meet these definitions. It is a requirement to have a rationale on the definition of medical device and accessory for a medical device.
So making sure that the device meets the correct definition is the first step forward. The second step is to rationalise the exemption for having a mandatory paper IFU.
Qarad is an expert in e-IFU. And for regulatory related questions, QbD has a team of regulatory experts to guide you through the regulations. Download the whitepaper on this page to find out more.
Despite the advances in medical technology and the increased availability of mobile app solutions in medicine, there are major misconceptions among clinicians involved in building a mobile app (Fig. 1).
Fig. 1
Common misconceptions of medical mobile app development
Misconception #1—the investigator fully understands the problem they are trying to solve and the users they intend to help
Reality
Before the development process can start, the competitive landscape should be assessed to confirm that there is not already an identical or similar goal solution. Next, the intended users must be interviewed to ensure that the solution solves a relevant problem for them. This user research should be incorporated throughout the development process to assure that the users are continually being considered. An effective team must also be formed with the required expertise to handle every phase of the development lifecycle, from clinical problem identification, user research, design, development, and product release. Finally, a strategy must be developed to market the product so that users discover and adopt the app.
Misconception #2—app development does not require much effort
Reality
Reality
A common phrase we hear among our clinical colleagues when we are approached with an idea for a mobile medical solution is “…and I’d like to build an app.” This statement can be interpreted as, “I would like to hire a contractor to turn my idea into an app.” This line of reasoning underestimates the investigator commitment required to turn an idea into a mobile app. Throughout the development process, the investigator must play an active role in the development team. This process frequently takes months of user research, design, development, and testing in an iterative fashion.
Misconception #3—the app should easily integrate into the electronic health records (EHR) system
Reality
The electronic medical records in the USA and many countries are highly fragmented, with individual hospital systems using their own 3rd party vendors to manage their records [11, 12]. Accessing a single institution’s EHR requires multiple levels of approvals at the principal investigator and administrative levels and then requires significant technical collaboration with the institution’s information technology department to connect. While Fast Healthcare Interoperability Resources (FHIR) standard has been adopted to facilitate a consistent format of healthcare information for simple transmission and sharing of data, the lack of a consistent EHR framework significantly impacts the ability of a 3rd party app to integrate into the EHR’s of a geographically diverse user base [13].
Misconception #4—app development is a single-step “one and done” process
Reality
The development process is not complete when the app is launched. A continuity plan must be in place to maintain and update the app throughout its lifecycle. Technology changes rapidly, operating systems update, and smartphone manufacturers develop and release multiple new phone models annually. An app must be maintained to adapt to these advancements. The request to “build an app” does not accurately convey that app development is a process that does not end with an app launch.
These misconceptions underscore a clear need for a liaison between clinicians and the app development community to facilitate the development of robust, maintainable, mobile apps. To address these misconceptions, we set up an academic sub-unit within the Georgia Clinical and Translational Science Alliance (Georgia CTSA), which we call the AppHatchery, with the goal of supporting clinical investigators in their endeavors to create and clinically translate their mobile medical app ideas. Care was taken to structure the AppHatchery to enable this end goal, with a mix of relevant expertise and experience. This initiative is led by a physician scientist who runs a laboratory that has a proven track record of developing and publishing medical apps as well as conducting clinical research using apps. We hired a product manager from the industry with expertise in managing mobile app development teams for a large organization. We have a designer on the team who specializes in user research and design thinking. Finally, we have multiple full-time developers to carry out mobile development work. We structured the group this way to ensure that we had members of the team with expertise in each phase of medical app development, specifically (1) clinical research expertise, (2) design, and (3) mobile app development. Given these diverse skillsets with every team member having some exposure to both clinical science and app development, we have created the perfect team to bridge the skillset gap between clinicians and software developers and develop mobile medical apps. Furthermore, the existence of team members fully dedicated to this initiative allows us to maintain continuity throughout each stage of the project at hand.
We first rely on internal marketing for project solicitations. When a project is onboarded, we perform a multi-disciplinary research process where we identify and explore the clinical and practical need for the given solution and its place within the current regulatory landscape and market. We use a combination of design thinking (DT) and human-centered design (HCD) framework to tackle app development challenges [14] from ideation through delivery. The design research process begins by conducting a deep dive into the problem as it pertains to end users and key stakeholders. Target users are interviewed to better understand their challenges, and we identify and/or verify the important features and aspects of the proposed app and get feedback on the design requirements that our research has identified. Simultaneously, we begin working with the principal investigator (PI) to craft the research study that will determine the efficacy of the tool we develop. Next, we begin the app development process, beginning with the design of wireframes and culminating with software development, where we conduct user research throughout the process to iteratively improve the app. We finally transition to launch and support, where we work with the principal investigator to release the app and support the clinical validation study. In this manuscript, we will describe the lessons learned from our journey and make recommendations for how other medical app developers should operate to successfully develop and translate clinical app ideas.
App development principles and structure
Design approach
What makes our approach to building digital tools unique in the clinical space is our emphasis on both DT and HCD (Fig. 2). We use DT to focus on understanding who the users are, uncovering their needs, and empathizing with their situation first before kicking off the product design and development process [15]. In addition, we strategically consider user needs in relation to clinical objectives to form design recommendations [16, 17]. We then kick off the development phase which incorporates HCD fundamentals, bringing the end user’s voice and opinions into the development process. Collaborative strategies are noted as vital to sustaining growth in mobile health applications [18]. HCD has been demonstrated to be an effective innovation tool in the digital clinical and health space where a focus on end users (patients, clinicians, or others) during the design process improves adoption rates [19,20,21] as well as patient engagement and satisfaction [22].
Fig. 2
Design thinking framework
A recent narrative review of 82 health innovation papers mentioning HCD found most (70{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}) discussed using an HCD approach and all included a focus on users’ needs and the participatory and iterative nature of the design process [14]. More salient limitations to the HCD approach include sampling bias and small sample size as users must opt into the research to participate in the design process and are not necessarily the profile of users who may need the app the most. This may lead to a misalignment of the design with the intended user’s needs. Finally, few apps have been tested in randomized controlled trials, and so limited evidence is available on the long-term benefits of app products arising from HCD approaches [23]. Specifically, in using HCD, there are instances where the approach did not lead to significant improvement in the intervention outcomes. For example, Gallagher et al. conducted a study using a game-based app that was co-designed to improve cardiovascular risk factors and lifestyle behaviors and found no improvement after the intervention [24]. Similarly, Haque et al. evaluated a user-centered mHealth app in promoting physical activity and found very low compliance at the end of the study which limits the generalizability of the results [25]. Furthermore, alternatives to DT and HCD such as user experience (UX) design frequently focus on the way users interact with apps and strive to provide the most convenient use for the people who actually use the app, rather than the ideal users that HCD and DT strive for [26]. In light of these findings, it is important to note that HCD methodology allows for subjectivity in terms of which aspects of user experience to prioritize, which can result in varied outcomes. Additionally, as previously discussed in the literature, HCD is susceptible to sampling bias, which can impact the apparent effectiveness of an intervention. Thus, it is crucial to consider both the strengths, limitations, and alternatives to DT and HCD and to employ a multi-disciplinary approach that considers various perspectives and factors in the design and evaluation process. This design strategy accurately defines the user, their needs, the problem most important to solve for that user, how those needs intersect with research goals, and which design directions are most effective at maintaining engagement and delivering results. It provides the foundation for the team who then focuses on the users and their needs throughout the app project development process.
Building a team
A development team must be created to begin the development process. A software development team has three distinct yet overlapping roles, the product manager, the designer, and the developer. In addition to these key roles, multiple supporting roles may be created for handling regulatory requirements necessary in medical app development.
Product manager
The product manager is responsible for the overall strategy of the mobile app. This includes the macro strategy of why and how to build the app in the first place as well as a more detailed strategy about which features to build, what order to build these features, and how to measure if the features are a success. The product manager is also responsible for creating the requirements in sufficient detail so the remainder of the team can execute their jobs effectively. These might be technical requirements, design requirements, or requirements from the clinical team. The product manager is also responsible for the lifecycle of the mobile app. This includes releasing the app through testing platforms, releasing the app publicly, working through approval processes at the institution, and maintaining the app’s public information on the app stores.
The product manager is responsible for ensuring the app meets guidelines. This is important especially for medical apps that may need to comply with the Health Insurance Portability and Accountability Act of 1996 (HIPAA) [27]. In our experience, projects are hindered at the beginning stages by focusing on these compliance issues instead of focusing on the core value of the mobile app. Compliance needs to be addressed at the beginning of a project when architecture is being designed and before the app is released publicly to ensure it meets all the required standards for privacy and security. The product manager is responsible for analytics and measuring the mobile app experience. These analytics are tied to the goals and objectives of the app (e.g., reducing missed follow-up visits) but also user experience metrics such as app crashes, screen views, and user interactions.
Software developer
The developer is responsible for writing the software code that will control the mobile app. This role is critical as there will be no software created without team members who can code the mobile app.
Designer
The designer is the empathizer in chief; it is their responsibility to always be the voice of the user throughout the app development process. This is a critical role as academic medical apps are often conceived without direct consultation of patients or users.
Other team roles
Developing mobile apps within an academic medical center requires knowledge of how Institutional Review Boards (IRB) review requests to conduct clinical research. It is useful to have an IRB expert on the team to answer nuanced questions about data collection and privacy that may differ from IRB to IRB and can be unique to clinical research involving mobile apps. While not critical in the early clinical research phases, it can be useful to have a regulatory expert on the team who is familiar with the relevant regulation, specifically around HIPAA and managing protected health information (PHI).
Full time vs part-time staff
Many academic medical centers operate on a shared time model where the staff dedicate a portion of their time to projects. While this can work, we have found it is better to have full-time staff dedicated to the development of mobile apps. Likewise, many software development projects are outsourced to other groups. While this can work, we have found it is best to work cohesively as a team throughout the development process to streamline communication and align expectations throughout.
Applying the app development process
Competitive and regulatory landscape survey and literature review
Before accepting any new project, it is important to meet with the PI to understand their clinical and application vision before conducting an extensive search of the major app stores to see what similar apps currently exist, as well as related platforms, tools, books, and/or educational materials in the space. After the search is completed, the list of these competing resources should then be presented to the PI to discuss how or if the value proposition of their idea merits the effort to build a homegrown solution. If the concept meets the acceptance criteria set by the team (i.e., is novel, addresses a real need, and the development team has capacity and knowledge), the project can proceed (Fig. 3).
Fig. 3
App project development process
When researching and deciding the intended use case of the app, research into the regulatory pathway required to market the product must be conducted. In the United States of America (USA), the US Food and Drug Administration (FDA) approves medical devices for sale in the US market. FDA guidance regarding software as a medical device (which includes medical apps) is governed specifically by the 21st Century Cures Act [28]. Section 3060 of this legislation defines what software the FDA considers to be a medical device that requires regulatory approval via the 510(k) premarket notification pathway, versus lifestyle tools that can immediately enter the market [28]. Ultimately, the distinction is determined based on the function and intended use of the software. Software becomes a medical device when the intention and function are to diagnose, cure, treat, prevent, or mitigate a specific disease or condition [28].
Should the app require premarket notification, multiple steps must be taken to satisfy the complex risk management strategies and regulatory requirements set by the FDA to release the app publicly. Rigorous clinical testing must be conducted to ensure that the device performance (1) is in line with the claimed performance and use case and (2) is similar in performance to the most analogous device currently approved and on the market (the claimed predicate device that must be identified for FDA submission). In addition to performance, the app must apply appropriate human factors and usability engineering processes, which must be assessed in standalone usability studies with at least 15 users in the desired user population [29]. Finally, a quality management system (QMS) must be in place to ensure that procedures and processes enable a reliable, safe, and effective software tool [30]. The QMS begins with the leadership and management plan to ensure that relevant stakeholders manage the medical app throughout its lifecycle. The support plans for the system must also be defined, with appropriate documentation of all development and design, disaster recovery plans, and processes for regularly updating the app for performance, usability, cybersecurity, and technology modernization. The implementation must be then considered, with regular validation, cybersecurity monitoring, and maintenance of all key infrastructure, to ensure that end users can interact with a stable version of the medical app throughout the duration of its lifecycle as a medical device.
Design strategy
Once engaged on a project, a development team should schedule a design strategy session with the investigator and project team to gain a full understanding of the desired goal of the app from the perspective of all stakeholders (Fig. 4). While investigators often have a passionate idea about what problem they wish to solve with their app, additional examination can help dial into precisely who will use their tool and what problems their app user(s) seek to solve. To prepare for this session, which is usually 1–2 h, the team conducts secondary research from published academic papers, review articles, and meta-analyses to familiarize themselves with the outcome goals of the project and specific aims of the research. The team generates clarifying questions for the investigator and research team to respond to. Sample questions may include the following:
Who will use this app? Is the patient or a family member the primary user?
What benefit will the user get out of using this app?
What data (if any) do you expect the app to collect?
Fig. 4
Collaborative design strategy discussions set the parameters of the project. Left: a design strategy session in person. Right: results of a design strategy session using an online collaboration tool like Miro
Post-It notes or a collaborative whiteboard digital tool such as Miro (Miro, Inc., San Francisco, CA) may be used to capture ideas that can be sorted and prioritized as seen in the image below. This allows the team to gather insights from the session to form a user research approach to test assumptions, write and vet a discussion guide, and then recruit 5–15 individuals from the intended user group to interview. Insights across all interviews are pooled together and sorted to surface themes and areas of importance for the user. As the themes and key features emerge from the insights, the team can refine the insights into design recommendations.
App design
Once the research team has a clear idea of the needs and wants of the users, designs for the app should be created (Fig. 5). It is very important that these designs come from actual user insights, rather than from pre-conceptions the research team had prior to beginning the work, unless these pre-conceptions had been validated by the user research.
Fig. 5
From sketches to wireframes. Left: pictures of preliminary sketches of the layout of the application. Right: functional (clickable) wireframes of an app
Given the number of apps that exist already, it is worth spending some effort looking to find similar apps that incorporate design patterns that could be implemented in the app. This is a separate step from the competitive analysis where rather than looking at apps that perform a similar function, you are looking for individual features (i.e., how search functions, how do other apps offer content layout).
Taking from the design recommendations generated in the prior phase. The designer can begin creating low-fidelity sketches, which they can turn into generalized flows and wireframes of the app (Fig. 5, left). The key is the use of wireframing and prototyping as an early way to evaluate whether the tool being created meets users’ expectations. To evaluate those wireframes, standard usability testing techniques can be used such as remote or in-person unmoderated observation sessions or task-based evaluations where the user is given tasks within the app to accomplish.
App development
The most common app development methodologies are the waterfall and agile methods [31]. The agile methodology is an iterative approach that leverages frequent releases that provide incremental functionality improvements that can be tested and refined in the production environment. The waterfall methodology completes the holistic build which then moves into a testing phase and then a launch phase, yielding a polished product. We prefer to utilize the agile methodology as the iterative development process enables more testing and feedback, which matches our design philosophy.
When an app development methodology has been selected, there are 2 major mobile app development frameworks: natively on each of the major operating system software tools (iOS or Android), or cross-platform (i.e., using React Native (Meta Platforms Inc., Menlo Park, CA), Flutter (Google LLC, Mountain View, CA), etc.) which supports one code base for both iOS and Android platforms (Table 1). The decision on what to use will largely depend on the expertise of the available developers in the team. This is the fundamental choice an app developer must make before developing an app.
Table 1 Overview of the development styles and platforms available
Native development has the advantages of dedicated functions and features specific to the hardware you are developing for (iOS vs Android), with the downside that effort must be duplicated to support both iOS and Android devices. Also, native development tends to be more well-maintained, as it is linked directly to the mobile devices operating system. This skillset is also much more readily available in the software developer talent pool. While cross-platform development is typically much faster and more efficient with respect to developer resources, it also relies on a much smaller developer community. Furthermore, many 3rd party tools common in app development (e.g., analytics, advertisements) have limited support for cross-platform development. The development framework should be chosen to suit the needs of the specific project.
Throughout the development process, it is generally good practice to beta test the app to ensure that what is being built is meeting the user’s expectations. To do this, it is best to test in a controlled environment to monitor who is using your app. To do this you will use either TestFlight for iOS (Apple In., Cupertino, CA) or Google Play Store Internal Testing for Android (Google LLC, Mountain View, CA).
Launch
Once the app is launched, it must be closely monitored for bugs, unforeseen issues for users, and ever-increasing software versions. Both iOS and Android release beta versions of the updates in advance of a public release so that developers have a chance to test the compatibility of their apps against these updates. Nevertheless, there are many apps that are no longer supported by new OS versions that plague the app stores, a situation that should certainly be avoided by a medical app developer! Some thought should be put towards maintaining support for the users that may not have updated to newer operating system (OS) versions. It is typical to set a supported version that dates back at least a few years to give users time to upgrade their devices.
Updates and maintenance
Finally, app maintenance must be considered. Funds must be allocated to support the continuity of the app development project before it begins. As described by Siegel et al. [10], there are a multitude of unsupported apps on the app stores that are born out of research projects and then abandoned, likely due to the lack of personnel to support them, lack of funds, or poor design and execution leading to a lack of traction to justify a larger time/monetary investment.
Simultaneously with the design thinking process, it is important to work with the PI to help design a research study and secure IRB approval for the study protocol that will be used to clinically validate the app upon release. This validation study typically occurs in 2 phases: Phase 1 is focused on usability and feasibility. In this phase, user feedback of the app is collected and used to iteratively improve the app. This can be done by identifying users to enroll in the clinical study and conducting a rolling enrollment process where a version of the app is developed and given to the users to collect their feedback, adjust the app, and then repeat. Phase 2 is a clinical trial where the app’s performance is analyzed in terms of a clinical endpoint. In this phase, a randomly controlled trial should be planned to assess the app in terms of a clinical endpoint of interest, i.e., a control (no app) and test (has the app). These results can then be published in a medical journal to provide credibility to the app as a medical tool.
Lessons learned: roadblocks, pivots, and best practices
App development costs
Funding for academic biomedical mobile apps can be difficult in our experience. The most common source of funding is through traditional National Institutes of Health (NIH) grants. These grants allow for setting aside resources in the budget to support mobile app development but do have some pitfalls. First, grants typically have a very long application and funding cycle, in the order of 12–18 months, which can delay a project. Second, funding amounts set aside for development tend to be small. In our experience, this has been $10,000–25,000 which is insufficient for the necessary costs associated with designing and developing an application (Tables 2 and 3). Beyond grants, academic medical centers often offer access to other seed or startup funds in the form of innovation awards, local organizations that offer awards or seed funds, and, as a last resort, projects can be funded through department funds if the funds and scope of the project are aligned.
Table 2 Personnel costs for mobile app development
Table 3 App development cost breakdown by stage
Staffing an academic medical center app development project is very different from a commercial software development project. The key differences are (1) the budget of the project is typically far lower (by an order of magnitude, typically), (2) the goal of the app is often non-commercial (e.g., it does not have a business model attached), and (3) the goals of the PI may include education and training for the full team, beyond only executing on the creation of the software. Therefore, staffing for mobile app projects will use a mix of resources available within academic medical centers and their affiliates. These include graduate or undergraduate students who may work on a project for free as part of a classroom learning experience, students who are hired outright or work through graduate research assistant positions, shared staff with other programs (e.g., bioinformatics), and partnership with other campus-based groups who are funded to support clinical research.
Managing investigator expectations
We often encounter requests that are in essence to “just build an app” from clinical PIs. It is important to diagnose this way of thinking early as it could reveal the propensity of a PI to disengage from the project prematurely, as it becomes clear the amount of effort and collaboration it takes to foster a successful partnership. PIs must be engaged often and richly with the team. The cadence of meetings will be project dependent, but we have found a weekly update, whether a meeting or email, maintain project members active and engaged.
Having a disengaged PI can lead to multiple points where the project can fail: (1) the problem is not defined appropriately, (2) the appropriate user research is not conducted (which can lead to the app not addressing all relevant user needs thus impacting adoption and use), and (3) usability/feasibility testing is not conducted in a robust and iterative fashion (which can lead to usability issues that will prevent users from adopting the app, even if the app has a strong value proposition that could significantly improve the life of the user). In addition, it taxes the rest of the team who must make clinical research decisions and navigate an unfamiliar research structure.
Understanding the users
It can be challenging to identify and access users to solicit feedback from. Clinician investigators typically have frequent interactions with the target user population. They have familiarity and a relationship built already (which is how the ideas for projects usually originate). However, they usually lack the time to conduct thorough user research that goes beyond the problem discovery. On the other hand, developers and designers do have the time and knowledge to conduct user research, albeit they lack access to patients. Bridging this gap, often by facilitating access to clinics and hospitals for the design team, can drastically improve a project’s chance of success. In one of our projects with Grady Memorial Hospital, we established a cadence of going to the hospital twice a week to enroll new subjects and check in on existing subjects. Furthermore, fostering a relationship with the clinical care teams of the subjects facilitates subject enrollment, a process that is much slower when only investigators are involved in subject recruitment. Additionally, by fostering that relationship with the clinical care of the subjects, it is possible to conduct user research with stakeholders through observation sessions and contextual inquiry. Which can help mitigate some of the overreliance on user input [32].
Beta testing recruitment
Recruitment can take place in person or virtually. Online recruitment tends to require less apparent overhead (although depending on the clinic setting it may be hard to capture patients online) while in-person recruitment has a higher overhead but tends to yield more numbers and more upfront engagement. Most of the recruitment that we have done has taken place in person at the hospital. Interestingly, we have found that subjects recruited in a clinical setting will remember everything about the app and the study until they leave the hospital/clinic, when study participation significantly wanes. To increase the chances of success, you must find the best method to follow up with your subject/users which could be via email, text, or phone calls so that you can maintain engagement with your study. This will be very study specific and dependent on the app you build. This is one area where sampling bias can impact the project as subjects who are more interested are more likely to respond and be engaged. That was our experience with that project, and we had very low compliance from the users we were trying to target, those who leave the hospital and do not return.
Beta testing process
Testing an app with users frequently is crucial to ensure the best possible version of the app is developed. In an in-patient setting, we have found it necessary to introduce users to the app in one session, and then follow up within a week, to see if the patient interacted with the app after the visit. There are multiple steps that can be taken to foster engagement:
a.
Delay the follow-up: A week might not be enough time for the user to have a need to open the app.
b.
Include push notifications: This system allows researchers to send messages through the app to specific segments of the study group (i.e., users who have not opened the app recently).
The goal of beta testing is to find encounter any bugs and errors and more importantly if the intended user audience finds the app useful. It is very challenging to design a research study surrounding a tool that will fit into a user’s life outside of the study. This is because study coordinators are actively looking for subjects to enroll, creating unnatural motivators to utilize the tool (i.e., participate in research, monetary compensation, curiosity), as opposed to an organic app search where users are looking for something. Thus, it is important to design an app such that the app fills a clearly defined and currently unmet need for a group of people (i.e., a medical reference guide, an appointment booking system, a prescribed training program). Otherwise, you run the risk of aiming to change a given behavior which has been identified as a limitation of traditional HCD and follows a different design process [32].
Furthermore, mobile apps have standardized evaluation frameworks such as the System Usability Scale (SUS) which provide a quantitative evaluation of the usability of a software tool. Note the difference between usability: Can somebody use the app without encountering errors that worsen their experience, and feasibility? Does the app effectively cover an unmet need for a user? Usability is an easier metric to quantify, and mobile apps for research should follow industry standards to validate the tools created are usable. These frameworks can be employed to glean valuable feedback during the beta testing process.
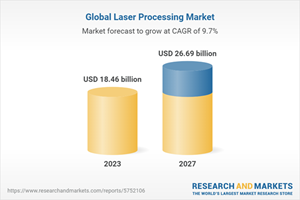
The global laser processing market grew from $16.57 billion in 2022 to $18.46 billion in 2023 at a compound annual growth rate (CAGR) of 11.4{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}. The laser processing market is expected to grow to $26.69 billion in 2027 at a CAGR of 9.7{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}.
Asia-Pacific was the largest region in the laser processing market in 2022, and it is also expected to be the fastest-growing region in the forecast period. The regions covered in the laser processing market report are Asia-Pacific, Western Europe, Eastern Europe, North America, South America, Middle East and Africa.
The increasing applications of lasers in medical devices and surgeries are significantly contributing to the growth of the laser processing market. Medical lasers are utilized in medical procedures in various specialties, including ophthalmology, dermatology, plastic surgery, and dental surgeries, as well as in intraabdominal, cardiothoracic, neurologic, gynecologic, and urologic procedures. Lasers facilitate a source of focused, coherent light capable of transmitting intense energy to a precise location.
For instance, in 2022, according to a report published by Biospace, a leading online source for biotechnology jobs, cataract statistics in the U.K., 330,000 cataract operations are conducted every year in the country. Moreover, 30{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of people aged 65 years and above are expected to have a cataract in one or both eyes. In 2020, in the U.S., around 718,000 surgeries are projected to be performed. In Europe, around 757,000 laser eye surgeries are likely to be performed by 2020. Therefore, the increasing usage of laser in medical devices and surgeries is expected to boost the demand for laser processing solutions during the forecast period.
Technological advancements are a key trend gaining popularity in the laser processing market. Many companies operating in laser processing are developing new products or new technologies to meet industry demand and strengthen their market position across the globe. For instance, in September 2021, TRUMPF, a German-based industrial machine manufacturing company launched 2D laser cutting machine, TruLaser 1000 which guaranteed up to 70{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} feed rate and with its effective cooling, it produces with high processing quality. Due to its ease of use and a wide variety of materials, it is ideal for beginners and companies who want to increase their production capacity.
In 2022, TRUMPF, a German-based industrial machinery manufacturing company acquired an 80{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} stake in Active Fiber Systems GmbH (AFS) for an undisclosed amount. With this acquisition, TRUMPF can leverage AFS’s laser systems to generate extremely short-wavelength light with high coherence, as well as for biomedical imaging and materials processing. Active Fiber Systems GmbH German-based manufacturer of ultrashort-pulse laser systems and fiber laser systems for science and research applications.
Reasons to Purchase
Gain a truly global perspective with the most comprehensive report available on this market covering 50+ geographies.
Understand how the market has been affected by the COVID-19 and how it is responding as the impact of the virus abates.
Assess the Russia – Ukraine war’s impact on agriculture, energy and mineral commodity supply and its direct and indirect impact on the market.
Measure the impact of high global inflation on market growth.
Create regional and country strategies on the basis of local data and analysis.
Identify growth segments for investment.
Outperform competitors using forecast data and the drivers and trends shaping the market.
Understand customers based on the latest market shares.
Benchmark performance against key competitors.
Suitable for supporting your internal and external presentations with reliable high quality data and analysis
Scope Markets Covered:
1) By Type: Gas Laser; Liquid Laser; Solid Laser; Other Types 2) By Application: Cutting; Welding; Drilling; Microprocessing; Marking and Engraving; Other Applications 3) By End-Use Industry: Aerospace and Defense; Automotive; Healthcare; Machine Tools; Architecture; Electronics and Microelectronics; Other End User Industries
About ResearchAndMarkets.com ResearchAndMarkets.com is the world’s leading source for international market research reports and market data. We provide you with the latest data on international and regional markets, key industries, the top companies, new products and the latest trends.
Attachment
CONTACT: CONTACT: ResearchAndMarkets.com Laura Wood,Senior Press Manager press@researchandmarkets.com For E.S.T Office Hours Call 1-917-300-0470 For U.S./ CAN Toll Free Call 1-800-526-8630 For GMT Office Hours Call +353-1-416-8900
Dr. Leah Rethy is an internal medicine resident with Penn Medicine.
Kimberly Paynter/WHYY
hide caption
toggle caption
Kimberly Paynter/WHYY
Dr. Leah Rethy is an internal medicine resident with Penn Medicine.
Kimberly Paynter/WHYY
Dr. Leah Rethy was pregnant during the first year of her internal medicine residency at the Hospital of the University of Pennsylvania in Philadelphia. She gave birth during her second year. She worked through her 40th week of pregnancy so she could save her time off and spend more time with her newborn.
Now she’s back at work and needs child care. A lot of child care. Medical residents often work long and irregular hours, sometimes as many as 80 hours a week. And child care is one of the main issues motivating Rethy to push for a union at her hospital.
If successful, these residents would join the Committee of Interns and Residents, the union for medical residents. According to the union’s figures, the number of campaigns spiked from two in 2021, to eight in 2022, an unprecedented increase.
Child care challenges
Rethy says her problem with child care is not unusual — residency follows undergraduate education, and usually four years of medical school, so it overlaps with childbearing years for most people.
“I know a lot of people who’ve delayed having children,” she says. “And I also have heard a number of stories of people delaying having children and then, ultimately, having real challenges getting pregnant because of being older and various factors.”
Dr. Leah Rethy, an internal medicine resident with Penn Medicine, holds her 17 month-old son, Peter.
Kimberly Paynter/WHYY
hide caption
toggle caption
Kimberly Paynter/WHYY
Dr. Leah Rethy, an internal medicine resident with Penn Medicine, holds her 17 month-old son, Peter.
Kimberly Paynter/WHYY
Rethy laments the waiting lists for child care affiliated with Penn Medicine, and says finding her own child care is prohibitively expensive.
“The cost of day care … in a month is about half of my salary in total, and the cost of a nanny is essentially the entirety of my salary,” says Rethy.
She says this experience led her to believe unionizing is the best way for residents to demand better working conditions and higher pay, which would lead to better patient care.
A workforce that can’t leave
Sunyata Altenor is the communications director of Committee of Interns and Residents, or CIR, as the union is known. She says residents who want to unionize understand the program is supposed to be hard work, with long hours. But they want to be treated fairly for their efforts, at a workplace they cannot just choose to leave, as it’s a required part of their training.
“It’s easy to exploit physicians during this time in their career,” Altenor says. “They’re only going to be there for a few years. It’s sort of expected that you go through this hard, hazing culture, and then you come out at the other end an attending physician.”
Prominently, Stanford Medicine did not include residents in their COVID-19 vaccination plans in 2020, leading to protests, and later, a successful unionization drive.
Dr. Chantal Tapé, a third-year resident in family medicine at Penn Medicine, said residents expect challenging work and long shifts, but they would also like to be able to be healthy and financially stable so they can focus on taking care of patients.
She said it is “frustrating as someone who is a prenatal care provider,” to watch colleagues struggle during pregnancy make it to prenatal care appointments and during early parenthood to afford child care. Her colleagues can’t follow advice she recommends for her patients.
Parking, mice and roaches, too
Penn Medicine residents cite many issues for their decision to form a union, such as: the upcoming loss of parking benefits that would lead to an extra $200 monthly cost for residents; and dirty call rooms, which are rooms where residents stay and rest if they have to work overnight.
Residents say some current call rooms have mice and cockroaches.
Dr. Madison Sharp, a third-year OB-GYN resident, recalls not even having a call room to sleep in during a 24-hour rotation.
“So I tried to sleep in a dialysis chair that didn’t lie flat in a conference room off to the side,” she said. “Two years later, residents on that same rotation still don’t have a place to sleep for a few hours on a 24-hour call shift … keep in mind that Penn just opened a billion-dollar hospital but neglected to create physical space for us.”
Medical residents at Penn Medicine say cockroaches and mice have been seen in the “call rooms” where doctors rest during 24-hour shifts.
Resident at Penn Medicine
hide caption
toggle caption
Resident at Penn Medicine
Medical residents at Penn Medicine say cockroaches and mice have been seen in the “call rooms” where doctors rest during 24-hour shifts.
Resident at Penn Medicine
In a prepared statement, Penn Medicine says it values residents and is “proud of the ways in which we have sought to continually improve resident life and wellness.” The statement maintains it provides benefits and increased salaries to offer competitive working conditions. Starting July 1, resident salaries will start at a little more than $69,000 a year, according to Penn Medicine. They also say “trainees” should bring their concerns to administrators through an existing advisory council.
“I was the president of this council last year, and I can tell you firsthand that the House staff governing council is extremely limited in what we could accomplish,” Sharp said. “It was incredibly frustrating to advocate for residents and fellows and not be heard or have our concerns brushed aside or dismissed.”
Residents at the University of Vermont Medical Center voted to form a union last year. Following the successful union vote for residents, support staff including maintenance workers and technicians are unionizing as well.
The union for residents at Jersey City Medical Center has already argued for a better work environment in the years since they’ve organized, said Dr. Andrea Attenasio, a fourth-year resident in orthopedic surgery. For instance, she said they recently managed to ask the hospital to provide food for residents who work after hours; to provide bedsheets for the rooms where residents stay if they work overnight; and to stop tying salary increases for residents to overall hospital performance, a major concern with rising inflation and cost of living.
Attenasio said the bargaining power and strength in numbers that comes from being a union member makes a difference for residents:.
“It’s an automatic support system and it allows you to go to your hospital administration as a united front.”
Medical equipment or instruments utilized to diagnose or take care of diseases and difficulties in young children under the age of 21 are referred to as pediatric gadgets. Infants, young children, and adolescents are the emphasis of the clinical specialty recognized as pediatrics, which offers with their wellbeing and healthcare treatment.
New York, March 23, 2023 (World NEWSWIRE) — Reportlinker.com announces the launch of the report “World-wide Pediatric Professional medical Gadgets Industry Dimension, Share & Market Tendencies Assessment Report By Product, By Conclusion Consumer, By Regional Outlook and Forecast, 2022 – 2028” – https://www.reportlinker.com/p06435108/?utm_source=GNW Due to the fact small children are much more lively and bodily lesser than adults, these health care units are crafted exclusively with their demands in mind.
1 of the key components propelling the development of the pediatric professional medical gadgets industry is the increase in the prevalence of serious diseases and infectious ailments among the the pediatric inhabitants. The demand for pediatric clinical products is also motivated by the enhanced need for anesthetic and respiratory products due to their effectiveness in treating ailments like asthma and the rising prevalence of preterm births worldwide. Also, in modern times technical developments and new product or service launches in the discipline has developed noticeably owing to the high demand.
Regulatory and legislative developments have aided in the advancement of pediatric health-related products, outcomes of which are also found in the enhancement of products. As a outcome, the Fda receives a quantity of applications for health care gadgets each individual calendar year. For illustration, prior to 2018, only greater-sized valves could be used for heart medical procedures, which is routinely inappropriate for children’s hearts. Even so, the tiniest gadget that allows surgeons to recover infants and neonates needing mitral or aortic valve replacement was authorised by the U.S. Food and drug administration in 2018 and is a rotatable prosthetic mechanical coronary heart valve of dimensions 15 mm.
In accordance to a UNICEF report, somewhere around 700,000 young children beneath the age of 5 die from pneumonia just about every calendar year, surpassing any other infectious ailment. Also, there have been much more regulatory organization initiatives, much more pediatric hospitals all over the world, technological improvements in pediatric devices, and increasing parental recognition strategies. The most significant gamers in the marketplace have launched new goods with increased abilities. For illustration, Medtronic launched a new pediatric keep an eye on that warns clinical industry experts when a patient’s airways may be blocked during breathing.
COVID-19 Influence Investigation
The Food and drug administration supported sponsors who wanted to make sure that these devices were being established up to specially cater to pediatric patients’ requires. For instance, the Food and drug administration granted a EUA for a device that delivers steady renal alternative treatment method and can be utilized in sufferers with decrease blood volumes or people with acute renal failure, fluid overload, or the two. These people have been unable stand up to a greater extracorporeal circuit quantity in an acute treatment environment and weigh 8 to 20 kilograms. Even with the COVID-19 outbreak, the Fda emphasized how vital it is to hold in head the requires of pediatric individuals. As a result, the COVID-19 pandemic experienced a favorable affect on the pediatric medical gadgets market.
Current market Expansion Things
Soaring respiratory dysfunction and cancer incidences in little ones
According to the American Academy of Pediatrics, 15.4 million kids in the US examined COVID-19 beneficial in February 2023. As a outcome, the expansion of the pediatric healthcare equipment market is driven by the raising frequency of cancer and respiratory ailments amongst youngsters. In addition, the increase in the number of untimely toddlers is a further significant component driving the expansion of this field. All these components are endorsing the development of the industry in the coming many years.
Raising delivery charge and NICU availability
A lot of children call for NICU amenities upon beginning. Small children who will need NICU care are typically transferred there in just 24 hours of delivery thanks to problems during early beginning, delivery, or wellness complications adhering to delivery. If a boy or girl is born prior to 37 weeks of being pregnant, it is deemed preterm. Premature infants are much more vulnerable to disorders like pneumonia, sepsis, etcetera. As a final result, sector contributors have launched a amount of devices that would broaden the collection of merchandise obtainable in the neonatal ICU. For this reason, the growing delivery amount and NICU units are promoting the expansion of the industry.
Industry Restraining Factors
Absence of clinical trials and issues in system manufacture
The danger to a manufacturer’s track record when pediatric health-related products malfunction may perhaps be much too large for the small business to bear. Even if the failure level is very low and mom and dad or other carers are completely ready to get the chance in the hopes that their kid will gain, this threat may possibly acts as a major barrier to entry into the sector. In rising markets, pediatric imaging, screening, and respiratory gear are significantly less prevalent. Consequently, the leading gamers are boosting the market’s profile during the forecast time period. Nevertheless, the lack of industry recognition for the duration of the forecast period impacts the market’s full need. All these things substantially hamper the growth of the sector.
Products Outlook
Dependent on solution, the pediatric professional medical equipment marketplace is classified into cardiology equipment, in vitro diagnostic (IVD) gadgets, diagnostic imaging devices, anesthesia & respiratory care devices, neonatal ICU gadgets, and other people. The neonatal ICU products section procured a appreciable growth level in the pediatric health care products market place in 2021. For the special requirements of minimal infants, sophisticated instruments and units are used in neonatal intensive treatment models (NICUs). The growing need for NICU are accountable for the enlargement of the section. Coronary heart or cardiorespiratory screens, blood pressure monitors, temperature displays, and pulse oximeters are a handful of of the instruments commonly utilized in the NICU.
Conclude User Outlook
On the foundation of close user, the pediatric professional medical devices current market is divided into hospitals, clinics, ambulatory surgical facilities, and some others. The clinics section witnessed a significant earnings share in the pediatric healthcare equipment market in 2021. The point that these clinics are mostly devoted to offering treatment for children can be accountable for the increase. The pediatric clinics offer the most modern clinical information on children’s and adolescents’ health and fitness situations. It offers a wide vary of methods to promise a child’s healthy upbringing. These clinics also present a extensive schedule of verify-ups, vaccines, and a child’s typical advancement.
Regional Outlook
Based mostly on location, the pediatric health-related products market is analyzed throughout North The usa, Europe, Asia Pacific, and LAMEA. The North The us section garnered the most earnings share in the pediatric professional medical units marketplace in 2021. Highly developed health care devices and the rising prevalence of pediatric chronic ailments this sort of as leukemia, asthma, cancer, and congenital heart disease are driving the market’s expansion in this region. In The us, far more than 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of adolescents and young children in faculty have at least one particular chronic affliction, in accordance to figures from the Facilities for Illness Regulate and Prevention (CDC).
The market analysis report covers the examination of vital stake holders of the market place. Key providers profiled in the report contain Medtronic PLC, Abbott Laboratories, Cardinal Health and fitness, Inc., GE Healthcare Systems, Inc., Hamilton Medical AG (Hamilton Bonaduz AG), TSE spol. s.r.o. (TSE Clinical), Fritz Stephan GmbH, Phoenix Healthcare Systems Pvt. Ltd., Trimpeks, and Atom Medical Corporation.
Methods Deployed in Pediatric Medical Units Industry
Sep-2022: Medtronic been given an expanded Food and drug administration clearance for pediatric use of the LINQ II technique, a wi-fi, tiny Insertable Cardiac Keep track of procedure. The broadened sign consists of children aged two a long time and above, who have heart rhythm abnormalities and require constant checking for a very long period of time.
Apr-2022: Cardinal Wellness collaborated with Innara Health, a corporation engaged in feeding growth for newborns and infants born prematurely. Underneath this collaboration, both equally businesses would redesign the Ntrainer method. The Ntrainer program is an Food and drug administration-permitted professional medical gadget for better prefeeding expertise in newborns and preterm infants. Furthermore, Cardinal Well being would aid the enhancement and commercialization of the subsequent-era NTrainer.
Feb-2022: Medtronic plc bought Food and drug administration acceptance for Freezor™ and Freezor™ Xtra Cardiac Cryoablation Focal Catheters, an ablation catheter to handle the expanding prevalence of pediatric Atrioventricular Nodal Reentrant Tachycardia. The products and solutions are solitary-use, adaptable products utilised to block avoidable electrical alerts and freeze cardiac tissue inside the coronary heart.
Might-2021: Medtronic released SonarMed™ airway monitoring method, a product that makes use of acoustic technological innovation to look at for endotracheal tube obstruction and affirm placement at the exact same time, delivering clinicians significant info wanted to make a improved determination for the smallest individuals. Furthermore, the products is an Food and drug administration-permitted airway checking process that provides in-time notifications and unique measurements that enable make it possible for a structured reaction to address possible very important gatherings such as migration and ETT movement.
Dec-2020: Medtronic unveiled Carpedim, a cardio-renal pediatric dialysis crisis equipment, across the United States. The Carpedim device would deliver continual renal substitute treatment (CRRT) to clients amongst 2.5 kg and 10 kg. Also, the product or service is supposed to deal with problems connected with present equipment for neonatal clients.
Jan-2019: Abbott received Food and drug administration acceptance for The Amplatzer Piccolo Occluder, a healthcare device that can be implanted in infants weighing as tiny as 700 gm. The product’s measurement is smaller than a pea, which offers hope to untimely newborns and infants for corrective therapy. Moreover, the solution is made to enable the doctor to place it by the pulmonary or aortic artery and also to redeploy or retrieve the system for great placement.
Mar-2018: Abott got Fda acceptance for the Masters HPTM 15mm rotatable mechanical coronary heart valve, the world’s smallest mechanical coronary heart valve. The Masters HPTM 15mm rotatable mechanical heart valve would enable medical practitioners to address toddlers and babies in require of aortic or mitral valve alternative.
Scope of the Analyze
Market Segments protected in the Report:
By Solution
• In Vitro Diagnostic (IVD) Devices
• Anesthesia & Respiratory Treatment Units
• Cardiology Devices
• Diagnostic Imaging Equipment
• Neonatal ICU Gadgets
• Others
By Finish Person
• Hospitals
• Clinics
• Ambulatory Surgical treatment Centers
• Other individuals
By Geography
• North The usa
o US
o Canada
o Mexico
o Rest of North America
• Europe
o Germany
o Uk
o France
o Russia
o Spain
o Italy
o Rest of Europe
• Asia Pacific
o China
o Japan
o India
o South Korea
o Singapore
o Malaysia
o Relaxation of Asia Pacific
• LAMEA
o Brazil
o Argentina
o UAE
o Saudi Arabia
o South Africa
o Nigeria
o Rest of LAMEA
Firms Profiled
• Medtronic PLC
• Abbott Laboratories
• Cardinal Overall health, Inc.
• GE Health care Systems, Inc.
• Hamilton Health care AG (Hamilton Bonaduz AG)
• TSE spol. s.r.o. (TSE Health care)
• Fritz Stephan GmbH
• Phoenix Professional medical Devices Pvt. Ltd.
• Trimpeks
• Atom Health-related Company
Exclusive Choices
• Exhaustive coverage
• Best selection of current market tables and figures
• Membership based design out there
• Assured most effective price
• Assured publish profits study assist with 10{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} customization totally free Examine the entire report: https://www.reportlinker.com/p06435108/?utm_source=GNW
About Reportlinker ReportLinker is an award-profitable current market investigate answer. Reportlinker finds and organizes the most recent field knowledge so you get all the sector investigation you need to have – right away, in a person location.
Rutgers University has cemented its approach for a new healthcare faculty and research facility in the coronary heart of New Brunswick.
Rutgers Overall health at the HELIX will be the new one-campus home to Rutgers Robert Wooden Johnson Medical University and a Rutgers translational investigation facility equipped with a range of labs to progress the perform of 80 study groups.
Construction will start out this spring on the very first of a few structures in the New Jersey Wellbeing + Everyday living Science Trade, or HELIX, a general public-private improvement prepared in downtown New Brunswick, following approval Tuesday by the Rutgers University Board of Trustees.
The trustees’ consent adopted the Rutgers Board of Governors’ Feb. 27 approval of a tentative funding system for Rutgers’ part of the HELIX, an believed $567 million.
“Rutgers Health at the HELIX will renovate and affirm to the world the main benefit of Rutgers’ investigation and professional medical schooling company,” Rutgers President Jonathan Holloway claimed in a statement. “Imagine: We will be educating new generations of healthcare students along with reducing-edge laboratories and researchers – in the exact room where we collaborate with our colleagues at Princeton and businesses, which includes the two greatest medical center systems in the state. It will be an epicenter of well being innovation.”
The Rutgers’ portion of the $732 million 1st HELIX making will be paid out mostly via $200 million of federal American Rescue Approach cash delivered by the condition and close to $190 million in tax credits administered by the New Jersey Economic Enhancement Authority Aspire method, in accordance to university officials. Rutgers will finance the remaining $180 million of the value by means of tax-exempt and taxable bonds, university officials claimed.
The HELIX, formerly known as the New Jersey Innovation and Technology Hub, will be developed by the New Brunswick Improvement Company on a internet site across from the New Brunswick prepare station and is built as an innovation heart supplying firms, universities and scientists crucial area to get the job done, study, experiment and collaborate. State-of-the art laboratories, workplaces, function and learning areas will arrive collectively in the 1st, 12-tale setting up to foster investigate, procedure and organization breakthroughs.
Preparing for the sophisticated commenced numerous years back when Gov. Phil Murphy to start with proposed in 2017 a hub to invigorate the state’s innovation financial system. Officials broke ground at the website in October 2021 and introduced the relocation of Rutgers’ clinical college. Princeton University, RWJBarnabas Health and Hackensack Meridian Overall health also have fully commited to the website.
Since then, the pandemic strengthened the need for ongoing groundbreaking well being and professional medical study whilst a Rutgers Biomedical and Health Sciences learn system set a new regular for excellence in wellness sciences training, analysis and individual treatment, mentioned Antonio Calcado, Rutgers executive vice president and main functioning officer.
“We have arrived at a spot that not only will provide the New Jersey innovation hub to fruition, but we will also significantly increase Rutgers’ standing in the shipping and delivery of medical education though reworking what translational research seems to be like,” Calcado claimed in a assertion.
Translational analysis, often referred to as bench-to-bedside analysis, turns laboratory discoveries into new approaches to boost health care and clinical remedy.
The a few-year development job will aid more than 7,000 jobs and create about $83 million in community, county and state tax revenues, according to college officials. After concluded, the HELIX is projected to produce approximately $880 million in financial exercise annually in the condition, which include supporting about 4,500 work opportunities, according to an economic effects report on the challenge.
“With the boards’ acceptance, we will begin to carry alongside one another larger instruction institutions, overall health techniques and the existence sciences industry to revolutionize scientific and translational analysis – turning our groundbreaking investigate into treatment and cures,” claimed Rutgers Biomedical and Health and fitness Sciences Chancellor Brian Strom in a statement.
“Moving the Robert Wood Johnson Medical College into 1 point out-of-the-art campus will boost health care students’ working experience by holistic clinical instruction and prospects for scientific activities in all four a long time of clinical school,” Strom included.