The Affordable Care Act has significantly reduced racial disparities in health care access, report says

The Affordable Care Act, passed in 2010 under former President Barack Obama, has expanded health insurance coverage across the U.S. and significantly reduced racial and ethnic disparities in access to health care, according to a new report by the Commonwealth Fund.

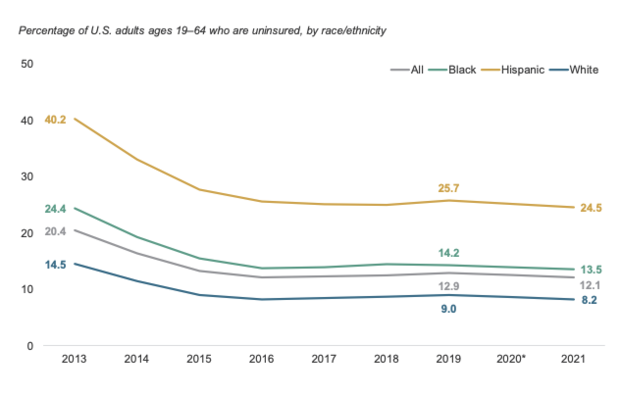
Percentage of U.S. adults ages 19–64 who are uninsured, by race/ethnicity
Coverage inequities between Black, Hispanic, and White adults have narrowed substantially since 2013. All groups reported improvements between 2019 and 2021.

The Commonwealth Fund


“Since its passage in 2010, the Affordable Care Act (ACA) has helped cut the U.S. uninsured rate nearly in half while significantly reducing racial and ethnic disparities in both insurance coverage and access to care — particularly in states that expanded their Medicaid programs,” reads the report.

Data shows that prior to the 2013 implementation of the Medicaid expansion — a provision of the ACA that made more families eligible for Medicaid coverage — 40.2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the Hispanic population, 24.4{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the Black population, and 14.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the White population were uninsured in America. However, by 2021, those numbers dropped significantly to 24.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, 13.5{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, and 8.2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, respectively.

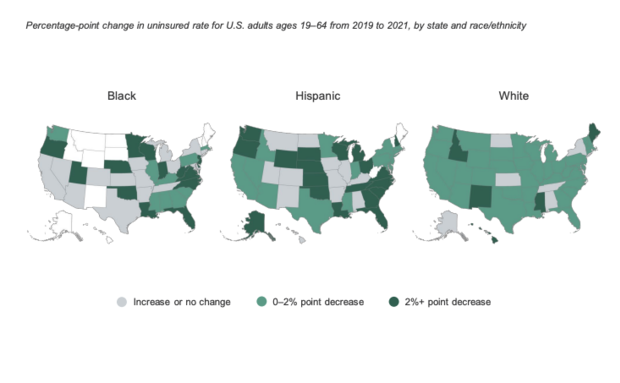
Percentage-point change in uninsured rate for U.S. adults ages 19–64 from 2019 to 2021, by state and race/ethnicity
Uninsured rates for Black and Hispanic adults improved considerably in several states between 2019 and 2021, while White adults experienced modest gains in most regions. 

The Commonwealth Fund


With more than 5 million people gaining coverage between 2020 and 2022 over the course of the pandemic, the overall uninsured rate in the U.S. dropped to just 8{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, a historic low, according to the report.

The report highlights specific ACA successes, including improved coverage rates for Black, Hispanic and White adults.

“The coverage gap between Black and White adults dropped from 9.9 to 5.3 percentage points, while the gap between Hispanic and White adults dropped from 25.7 to 16.3 points,” according to the the study. 

Additionally, the report found that adult uninsured rates for Black, Hispanic, and White people all improved during the first two years of the pandemic across all states — whether they had expanded their Medicare coverage or not —  and that Black and Hispanic adults experienced larger gains in insurance coverage than their White counterparts between from 2019 to 2021.

Less staff, longer delays and fewer options: Rural America confronts a health care crisis

More than 40,000 graduating medical students learned Friday where they will spend the next three to seven years of their medical training.

With the United States grappling with a simultaneous shortage of primary care physicians and a rural health care crisis, many of the graduating students are set to enter the front lines of the country’s health care shortage.

At least 136 rural hospitals and health systems closed between 2010 and 2021, and over 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of rural hospitals operate with negative profit margins. Despite billions of dollars in investment in health care, hospitals throughout the United States face the possibility of shutting down.

“I would say it is probably the worst time for health care that we ever experienced,” Joanne Conroy, the chief executive officer and president of Dartmouth Health, told ABC News. She noted that increased costs, inflation, limited housing, and workforce shortages have made running rural hospitals more challenging.

Less staff, longer delays and fewer options: Rural America confronts a health care crisis

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“We know what to do if we face another pandemic,” Conroy said. “The question is whether or not we have the financial resilience in order to survive it.”

Many hospitals that remain open have cut costs to survive, offering fewer services and beds.

In 2020, 47{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of rural community hospitals did not provide obstetric services, with 89 obstetric units closing between 2015 and 2019. Seven million women reside in counties with limited or no access to maternity care, impacting half a million newborns annually.

According to Conroy, patients can already feel the impact of the crisis, noting that some women in New Hampshire need to drive two hours to deliver their babies. Other effects include fewer available beds in emergency rooms, delays for elective surgery and longer wait times for prescriptions or ambulance pickups.

For new medical professionals entering their residency, especially those joining rural systems, the circumstances of the struggling health systems are out of their control.

PHOTO: Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“It is not my job to fix all of the problems for an entire community, that’s impossible. When you feel like that’s your responsibility, burnout is basically inevitable,” said Katie Stevenson, a Tufts medical student. “When you feel like your goal is to do the best you can with the resources you have, you are able to right-size your expectations a bit.”

An increasing number of students are entering medical school programs that focus on rural medicine. In 2019, the Health Resources and Services Administration issued grants to create 32 newly accredited rural residency programs, supplementing the preexisting programs.

This year, Tufts School of Medicine will graduate its tenth class of students from its Maine Track MD program – a partnership with Maine Medical Center that allows students to pursue a community-based curriculum and gain financial incentives to encourage primary-care specialties.

STOCK PHOTO: A teacher gestures as she lectures a class of college students.

A teacher gestures as she lectures a class of college students.

STOCK PHOTO/Getty Images

Graduating roughly 40 students annually, 27{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of Maine Track students have been matched to programs in Maine and 47{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} have been matched into primary care programs, according to Dena Whitesell, an assistant dean for students at Tufts and psychiatrist at Maine Medical Center.

“We know that students and residents who live in an area [and] who train in an area are more likely to practice in that area in the future,” Whitesell said.

Liv Fauver, a Tufts student who matched with a University of Vermont residency program, grew up in rural New Hampshire and said she felt motivated to work in a similar community where she could positively impact the local residents.

“I think for me, my goal is to live and work in the community that I serve,” she said. “So I’m really in a place where I go home or go to the grocery store and see my patients all the time, because that’s the world that I live in and work in.”

While rural hospitals have closed in record numbers, PCPs – medical professionals who patients regularly use for checkups and other routine care – face additional challenges, especially in rural areas, according to experts.

Greg Sawin, a PCP who has practiced in Massachusetts and Maine as well as Duke University School of Medicine professor, said he worries that the goals of primary and long-term preventative care can sometimes be at odds with larger health care systems.

“We get paid to do things to people. We don’t get paid to keep populations healthy,” he said.

Moreover, he believes the costs associated with medical schools – including the high cost, the likelihood of incurring debt and substantially higher pay to pursue competitive specialties like orthopedic surgery or dermatology, for example – disincentivize primary care options like family or internal medicine.

PHOTO: Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“It can be very appealing to want to go into a specialty where you’re guaranteed to make more money and pay that debt off more easily,” Stevenson said.

Owen Foster lives in rural Vermont and has felt the impact of the decreased number of available PCPs, spending six months to book an appointment with a doctor. Living in a rural area, Foster shares his dilemma with millions of Americans in rural areas impacted by the shortage of PCPs.

“You need basic things at certain intervals in your life,” he told ABC News. “If you don’t have a primary care provider, you can’t get that and you can’t get the referrals you need, so it’s really, really difficult.”

What makes Foster’s experience unique is his position as the state of Vermont’s top health care regulator. As chair of Vermont’s Green Mountain Care Board, he oversees the quality and cost of the state’s health care system.

Learning about the shortage of primary-care physicians in Vermont, Foster decided to use the opportunity to find a PCP as a chance to examine the market as a “secret shopper.”

PHOTO: Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke students express joy on Match Day learning where they would spend the next three to seven years for their residency program.

Duke University School of Medicine

“What I found was I was completely incapable of getting a doctor,” he said. “I called eight places and the best I got was on an indefinite wait list, which never came to fruition.”

Rural areas comprise about two-thirds of the primary care health professional shortage areas nationwide, even though only 20{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of Americans live in rural areas.

The problem is also likely to worsen over time. Projections indicate that the United States will likely suffer a shortage of between 17,800 and 48,000 PCPs by 2034.

Moreover, health care professionals believe that the shortage of PCPs can make other elements of health care more expensive and worsen overall patient outcomes. Sawin gave the example of a person getting strep throat. Without a PCP, the person might go to a local hospital emergency room, which is significantly more expensive than other treatment options.

“In terms of mismatch of resources, you know, a kid with strep throat showing up in the ER is like cutting butter with a chainsaw,” Sawin said.

Foster added that primary care providers are “critical to controlling the costs of a health care system” due to their role in the early identification of issues, their ability to diagnose mental health issues, and their approach to preventative medicine.

According to Foster, PCPs in rural areas, however, struggle to find and retain staff, negotiate with insurance companies and prevent burnout. The shortage of PCPs, combined with the increased health care needs of the older population in rural areas, creates a concerning combination.

STOCK PHOTO: A group of medical students discussing some work while huddled around a whiteboard at the lab together.

A group of medical students discussing some work while huddled around a whiteboard at the lab together.

STOCK PHOTO/Getty Images

Despite these issues, Foster said he was optimistic about some approaches to make primary care more financially feasible, including adding a floor for PCP spending within health plans and government involvement in rate setting.

A new generation of students graduating from rural track programs also has the potential to reverse the tide of the PCP shortage in rural areas, with 571 additional primary care matches this year. Stevenson, for example, matched with the Swedish Cherry Hill rural program in Washington state.

“I think we have an opportunity in this country to do a much better job of taking care of our patients if we do a better job of funding primary care and preventative care and creating healthy environments,” Stevenson said.

Mobile clinics, launched to help with COVID, now fill gaps in rural health care : Shots

Mobile clinics, launched to help with COVID, now fill gaps in rural health care : Shots

Clinics in rural areas with fewer doctors, dentists and nurses are turning to mobile health care clinics to take care to where it’s most needed. The Healthy Communities Coalition organizes a few mobile dental events each year in Lyon County, Nev.

Wendy Madson/KHN


hide caption

toggle caption

Wendy Madson/KHN


Clinics in rural areas with fewer doctors, dentists and nurses are turning to mobile health care clinics to take care to where it’s most needed. The Healthy Communities Coalition organizes a few mobile dental events each year in Lyon County, Nev.

Wendy Madson/KHN

Nearly 12 years ago, a nonprofit centered on substance abuse prevention in Lyon County, Nev., broadened its services to dental care.

Leaders with the Healthy Communities Coalition were shocked into action after two of their food pantry volunteers used pliers to pull each other’s abscessed teeth. The volunteers saw no other option to relieve their overwhelming pain in the small town where they lived, 40 miles southeast of Reno, because of a dearth of dental care providers.

That drastic act, said Wendy Madson, executive director for the coalition, prompted her organization to use mobile clinics to offer health and dental services in rural communities where there aren’t enough patients to support brick-and-mortar offices.

The coalition now sends a van outfitted with dental equipment to county schools to treat hundreds of students per stop a few times each year. They also host events providing free care for adults in the region. The response has been overwhelming.

“Dental is the hot ticket,” Madson said. “Everybody wants dental. Availability of those services is what runs out first in those large mobile events.”

The coalition’s mobile programs mirror efforts nationwide to dispatch services to patients experiencing gaps in the health care system, especially in rural areas.

Rural residents face more significant health care provider shortages, including dentists, compared with their counterparts in larger cities. Since the beginning of the pandemic, mobile clinics have increased access to a range of services in hard-to-reach places with sparse populations.

A recently passed law, which makes it easier for rural communities to pay for new mobile clinics, could expand this trend. In the past, clinics that serve low-income rural residents couldn’t spend federal grant money — called new access point grants — on mobile services in communities where they didn’t already have facilities.

Then last fall, Congress passed the MOBILE Health Care Act, sponsored by Sens. Jacky Rosen, D-Nev., and Susan Collins, R-Maine, which gives federally qualified health centers – health clinics serving medically underserved areas — greater flexibility to use federal funding to create and operate mobile units.

Healthy Communities Coalition executive director Wendy Madson says mobile dental clinics in Lyon County, Nevada, help reach young students whose parents might otherwise lack the means or insurance to schedule regular visits.

Wendy Madson/KHN


hide caption

toggle caption

Wendy Madson/KHN

Since 2019, the number of mobile clinics on the road has expanded, according to the National Association of Community Health Centers. Many were used for COVID-19 testing and vaccinations. And health and community organizations started using mobile units to bring primary care, behavioral health, and reproductive services to out-of-the-way patients. The new funding pathway could soon put even more mobile health vans on the road.

For now, the law is dependent on congressional funding, and experts predict it could be at least a year before health centers can access the grant money.

Freed from brick-and-mortar requirements, health centers can roll out the vans

Once funded, the regulatory shift will allow health centers to collaborate with independent organizations like Madson’s Health Communities Coalition in Nevada to expand services in underserved regions. Because the coalition is not a federally qualified health center, it has relied on a mix of other federal and state grants.

Nearly 1,400 federally qualified health centers nationwide receive federal funding for providing comprehensive health services in underserved areas. The previous requirement that health centers establish brick-and-mortar clinics before expanding mobile clinics prevented many from applying, said Steve Messinger, policy director for the Nevada Primary Care Association. It was burdensome and costly for health centers.

But in rural areas with small populations, served well by mobile clinics, it wouldn’t make sense to first establish a building with a full-time provider, he said. That could eat up the budget of a federally qualified health center.

While health center advocates lobby Congress for base funding, the Healthy Communities Coalition is forging ahead with three dental events this year funded by a grant from the Health Resources and Services Administration, part of the Department of Health and Human Services.

At the first medical outreach event the coalition organized in 2012 in Lyon County, where 61,400 residents are spread across more than 2,000 square miles, more than 200 people showed up to receive free care and 150 teeth were pulled, Madson said. Since then, the organization has hosted several events a year — except in 2020, when the pandemic paused work.

Mobile dental clinics organized by the Healthy Communi(Wendy Madson) ties Coalition help ensure Lyon County, Nev., students receive cleanings, screenings, X-rays, and more.

Wendy Madson/KHN


hide caption

toggle caption

Wendy Madson/KHN

Many of the dental events are school-focused and provide children with such services as screenings, X-rays, sealings, varnish, and cleanings. But an overwhelming need for care also exists among area adults, said Madson, because Medicare and Nevada’s Medicaid do not include comprehensive dental coverage for adults. It’s harder to fund those events, she said.

Of the five communities in Lyon County, at least one, Silver Springs, does not have a single dentist. There are 10 dentists total in Fernley and Dayton, communities with a combined population of 38,600 people, but only two of those practices accept Medicaid, which covers low-income people younger than 21 and limited dental services for adults.

Filling a desperate need for dental and health services

Traci Rothman, who manages the coalition’s food pantries, said the dental outreach events made a difference for her 29-year-old son, who moved to Silver Springs last year. He went to two mobile clinics to receive free care, which Rothman said was a big relief because he’s uninsured and needed dental care badly.

“Otherwise, you’re going to somebody that you’re paying cash,” she said. “Oftentimes I cannot pay, honestly; it’s just out of reach for some people, or most people … in rural areas.”

Madson said the coalition stepped in to help a young student in desperate need of a root canal. The coalition is helping the girl’s family apply for Medicaid or Nevada Check Up, the state Children’s Health Insurance Program, and is paying $1,600 to cover the service with federal grant money. Another student had to be referred to several specialists before she had her decayed baby teeth surgically removed and received restorative treatment for adult teeth that had begun to decay.

“Her mom was so thankful, she was in tears,” Madson said. “She told me that her daughter woke up without instant pain for the first time in years.”

Madson said her organization has enough grant funding for three events through May, but she hopes the MOBILE Health Care Act will help expand services. Besides dental care, the group provides primary care mobile clinics for immigrant workers in Yerington, a small town in an agricultural region about 70 miles southeast of Reno.

Sara Rich, CEO of Choptank Community Health in Maryland, said she shares Madson’s hope.

Choptank serves five counties in Maryland, including small towns between the Chesapeake Bay and the Delmarva Peninsula. Amid the pandemic, the health organization struck an unlikely partnership with a car dealership and used federal COVID relief money to buy a Ford Transit cargo van for mobile clinics.

Choptank used its new van to provide vaccines but has since started using it to provide primary care to immigrant workers and dental services to children at 36 schools. The mobile clinics have been so successful that the health center is working on purchasing more vans to expand its services.

Rich said the mobile clinics are “breaking down barriers that a lot of us have been working on for a long time.”

Among the new services Choptank seeks to provide are behavioral health, preventing and treating substance use disorders, and skin screenings for people working on the shores of Maryland.

“Flexibility has been a theme over the last few years,” Rich said. “I think this MOBILE Health Care Act will help us do that even more into the future.”

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

Senators ponder more federal actions on health care cybersecurity

While there are experts and resources available, health care systems across the nation could use more help from the federal government to strengthen their computer networks against malicious attacks.

The U.S. Senate Committee on Homeland Security & Governmental Affairs joined the public discourse over health care cybersecurity – and the urgency of threats – on March 16. The hearing, titled “In Need of a Checkup: Examining the Cybersecurity Risks to the Healthcare Sector,” included testimony from four industry experts.

They did not suggest an easy, quick, one-size-fits-all solution to bolster protections for the computer networks physicians, clinicians, and support staff use to record patient information.

But the four panelists described the nature of the problem and why health care information is so valuable to online thieves who can sell the data, hold it for ransom, or threaten disclosure to patients. There are security measures health care workers and their supporters in government can do right now, and possible solutions that could help in the future.

Speaking to senators

The witnesses included:

  • Scott Dresen, senior vice president for information security and chief information security officer for Corewell Health
  • Kate Pierce, senior virtual information security officer for Fortified Health Security
  • Greg Garcia, executive director for cybersecurity for the Healthcare and Public Health Sector Coordinating Council
  • Stirling Martin, senior vice president and chief privacy and security officer for Epic Systems

Size matters

Large health care systems have dedicated staff who can monitor the computer networks, sometimes 24 hours a day. The experts agreed small and medium-sized health care systems don’t have enough workers to do the same.

What’s more, if an urban hospital has to shut down systems due to a cyberattack, patients usually have other nearby options to seek care. That’s not the case in rural areas, Pierce said.

“The impact on our rural communities during an attack is hard to overstate,” Pierce said. “The impact on patient safety is easy to comprehend. Delays in care can directly contribute to negative outcomes for many high-risk conditions. Facilities that continue to treat patients are challenged to provide high levels of patient care without access to patient information, safety alerts, delays in results, and other key tools.”

She suggested at least four changes that could help:

  • Create minimum, reasonable, achievable standards for cybersecurity, instead of recommendation that by necessity lag when physicians and staff must prioritize patient care.
  • Make money available, especially for small and rural hospitals.
  • The government needs better coordination of its cybersecurity efforts.
  • An emergency cyber disaster relief program would help small and rural hospitals recover more quickly from attacks.

Collaboration can help

Dresen offered two examples of collaboration and training new workers to strengthen cybersecurity.

The Michigan Health Care Cybersecurity Council convened health care organizations 10 years ago under the governor’s sponsorship to share best practices.

“It connected large systems with small systems so that you gave that connectivity and access to expertise to everybody in the state to help improve the state of the healthcare sector overall,” Dresen said. The West Michigan Center for Arts and Technology, which Peters visited last year, also offers free computer training and certifications for students to provide new talent in the health care sector, Dresen said.

Resources available

There are at least two publicly available resources for health care leaders and information technology professionals to use in developing cybersecurity plans, Garcia said.

In the Cybersecurity Information Sharing Act of 2015 Congress directed the U.S. Department of Health and Human Services (HHS), with other agencies, to develop a series of cybersecurity best practices for health systems. That work is known as the 405(d) program for the section of law, and as the Health Industry Cybersecurity Practice: Managing Threat and Protecting Patients, with 10 best practices to protect health care computer networks. An updated set of best practices is due soon this year, Garcia said.

“So this is this is partnership at its at its best, where there is consensus about what health systems need to do in cybersecurity, some of the basic blocking and tackling, not necessarily expensive, no high investment level,” Garcia said. “But some of the foundational elements of good cybersecurity practices.”

The Healthcare and Public Health Sector Critical Infrastructure Security and Resilience Partnership, an industry partner with HHS, also offers free resources to enhance cybersecurity, Garcia said.

Standards are needed

Martin agreed there is no shortage of recommendations and guidance, but taking stock of those resources and deciding what to do is another thing. He agreed a key thing is for the federal government to establish minimum thresholds for security best practices, and those thresholds must change over time.

He agreed with Pierce that, whether large or small, health care organizations are balancing lots of different competing priorities. “Trying to balance all of those different competing priorities is incredibly challenging and having that minimum target to shoot for will help make sure everyone is marching towards that target, and ultimately raise the security posture of everyone in the community,” Martin said.

The witnesses’ opening testimony is posted online. After those statements, they answered questions by Peters and committee members Sen. Kyrsten Sinema, I-Arizona; Sen. Thomas R. Carper, D-Delaware; Sen. Margaret Hassan, D-New Hampshire; Sen. Jacky Rosen, D-Nevada; Sen. Alex Padilla, D-California; Sen. Josh Hawley, R-Missouri; Sen. Richard Blumenthal, D-Connecticut. The full Committee hearing is available online.

Rural Texans must travel long distances for basic health care needs


Rural Texans must travel long distances for basic health care needs

A truck passes a county road in Bailey Co. on March. 6, 2023.

A truck drives down Highway 84 towards Muleshoe. The town is closer to New Mexico than it is to Lubbock, the nearest city.


Google flexes its health care AI muscle

Illustration of a robot arm lifting a medical cross

Illustration: Annelise Capossela/Axios

Google showed off an array of new artificial intelligence (AI)-driven health care tools on Tuesday, from a souped-up chatbot that can shed light on your medical symptoms to enhanced search features that tell you if a doctor takes Medicaid.

Why it matters: There’s an arms race among big tech companies to infuse their products with AI — but the results, particularly in health care, can have unwanted consequences or pitfalls, like racial bias, privacy concerns and ethical problems.

Driving the news: The “large language model” that Google has been building for the medical world — an AI chatbot called Med-PaLM 2 — now consistently passes medical exam questions with a score of 85{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, placing it at “expert” doctor level, the company said.

  • That’s an 18{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} improvement from the system’s previous performance, per the company, and “far surpasses similar AI models.”
  • A rival generative AI tool, ChatGPT, also passed the medical exams — but just barely. (ChatGPT’s creator, OpenAI, just released a new, more powerful version of its underlying tech.)
  • Google’s system is being trained to “retrieve medical knowledge, accurately answer medical questions, and provide reasoning,” the company says.

Yes, but: Google acknowledges AI’s shortcomings in the medical realm.

  • “There’s still a lot of work to be done to make sure [Med-PaLM 2] can work in real-world settings,” reads a blog post from Yossi Matias, a Google vice president of engineering and research, and Greg Corrado, its head of health AI.
  • Google found “significant gaps” when the tool was “tested against 14 criteria — including scientific factuality, precision, medical consensus, reasoning, bias and harm,” per the post.
  • “We look forward to working with researchers and the global medical community to close these gaps and understand how this technology can help improve health delivery.”

Meanwhile: Google’s conversational AI technology Duplex has called hundreds of thousands of U.S. health care providers to see if they accept Medicaid. The results are being displayed in Google Search, ahead of a March 31 re-enrollment deadline.

  • Google Search results will also soon highlight “providers that identify as community health centers offering free or low-cost care,” the company said.
  • And an improved version of Fitbit’s health metrics dashboard will soon be available — in some cases without a subscription — to help people map changes and trends in their breathing rate, skin temperature and blood oxygen.

What they’re saying: “The future of health is consumer-driven,” Karen DeSalvo, Google’s chief health officer, told reporters.

  • “People will expect a mobile-first experience with more personalized insights, services and care.”

Zoom out: Google is also deploying AI tools to help offer high-quality, low-cost medical diagnostics globally.

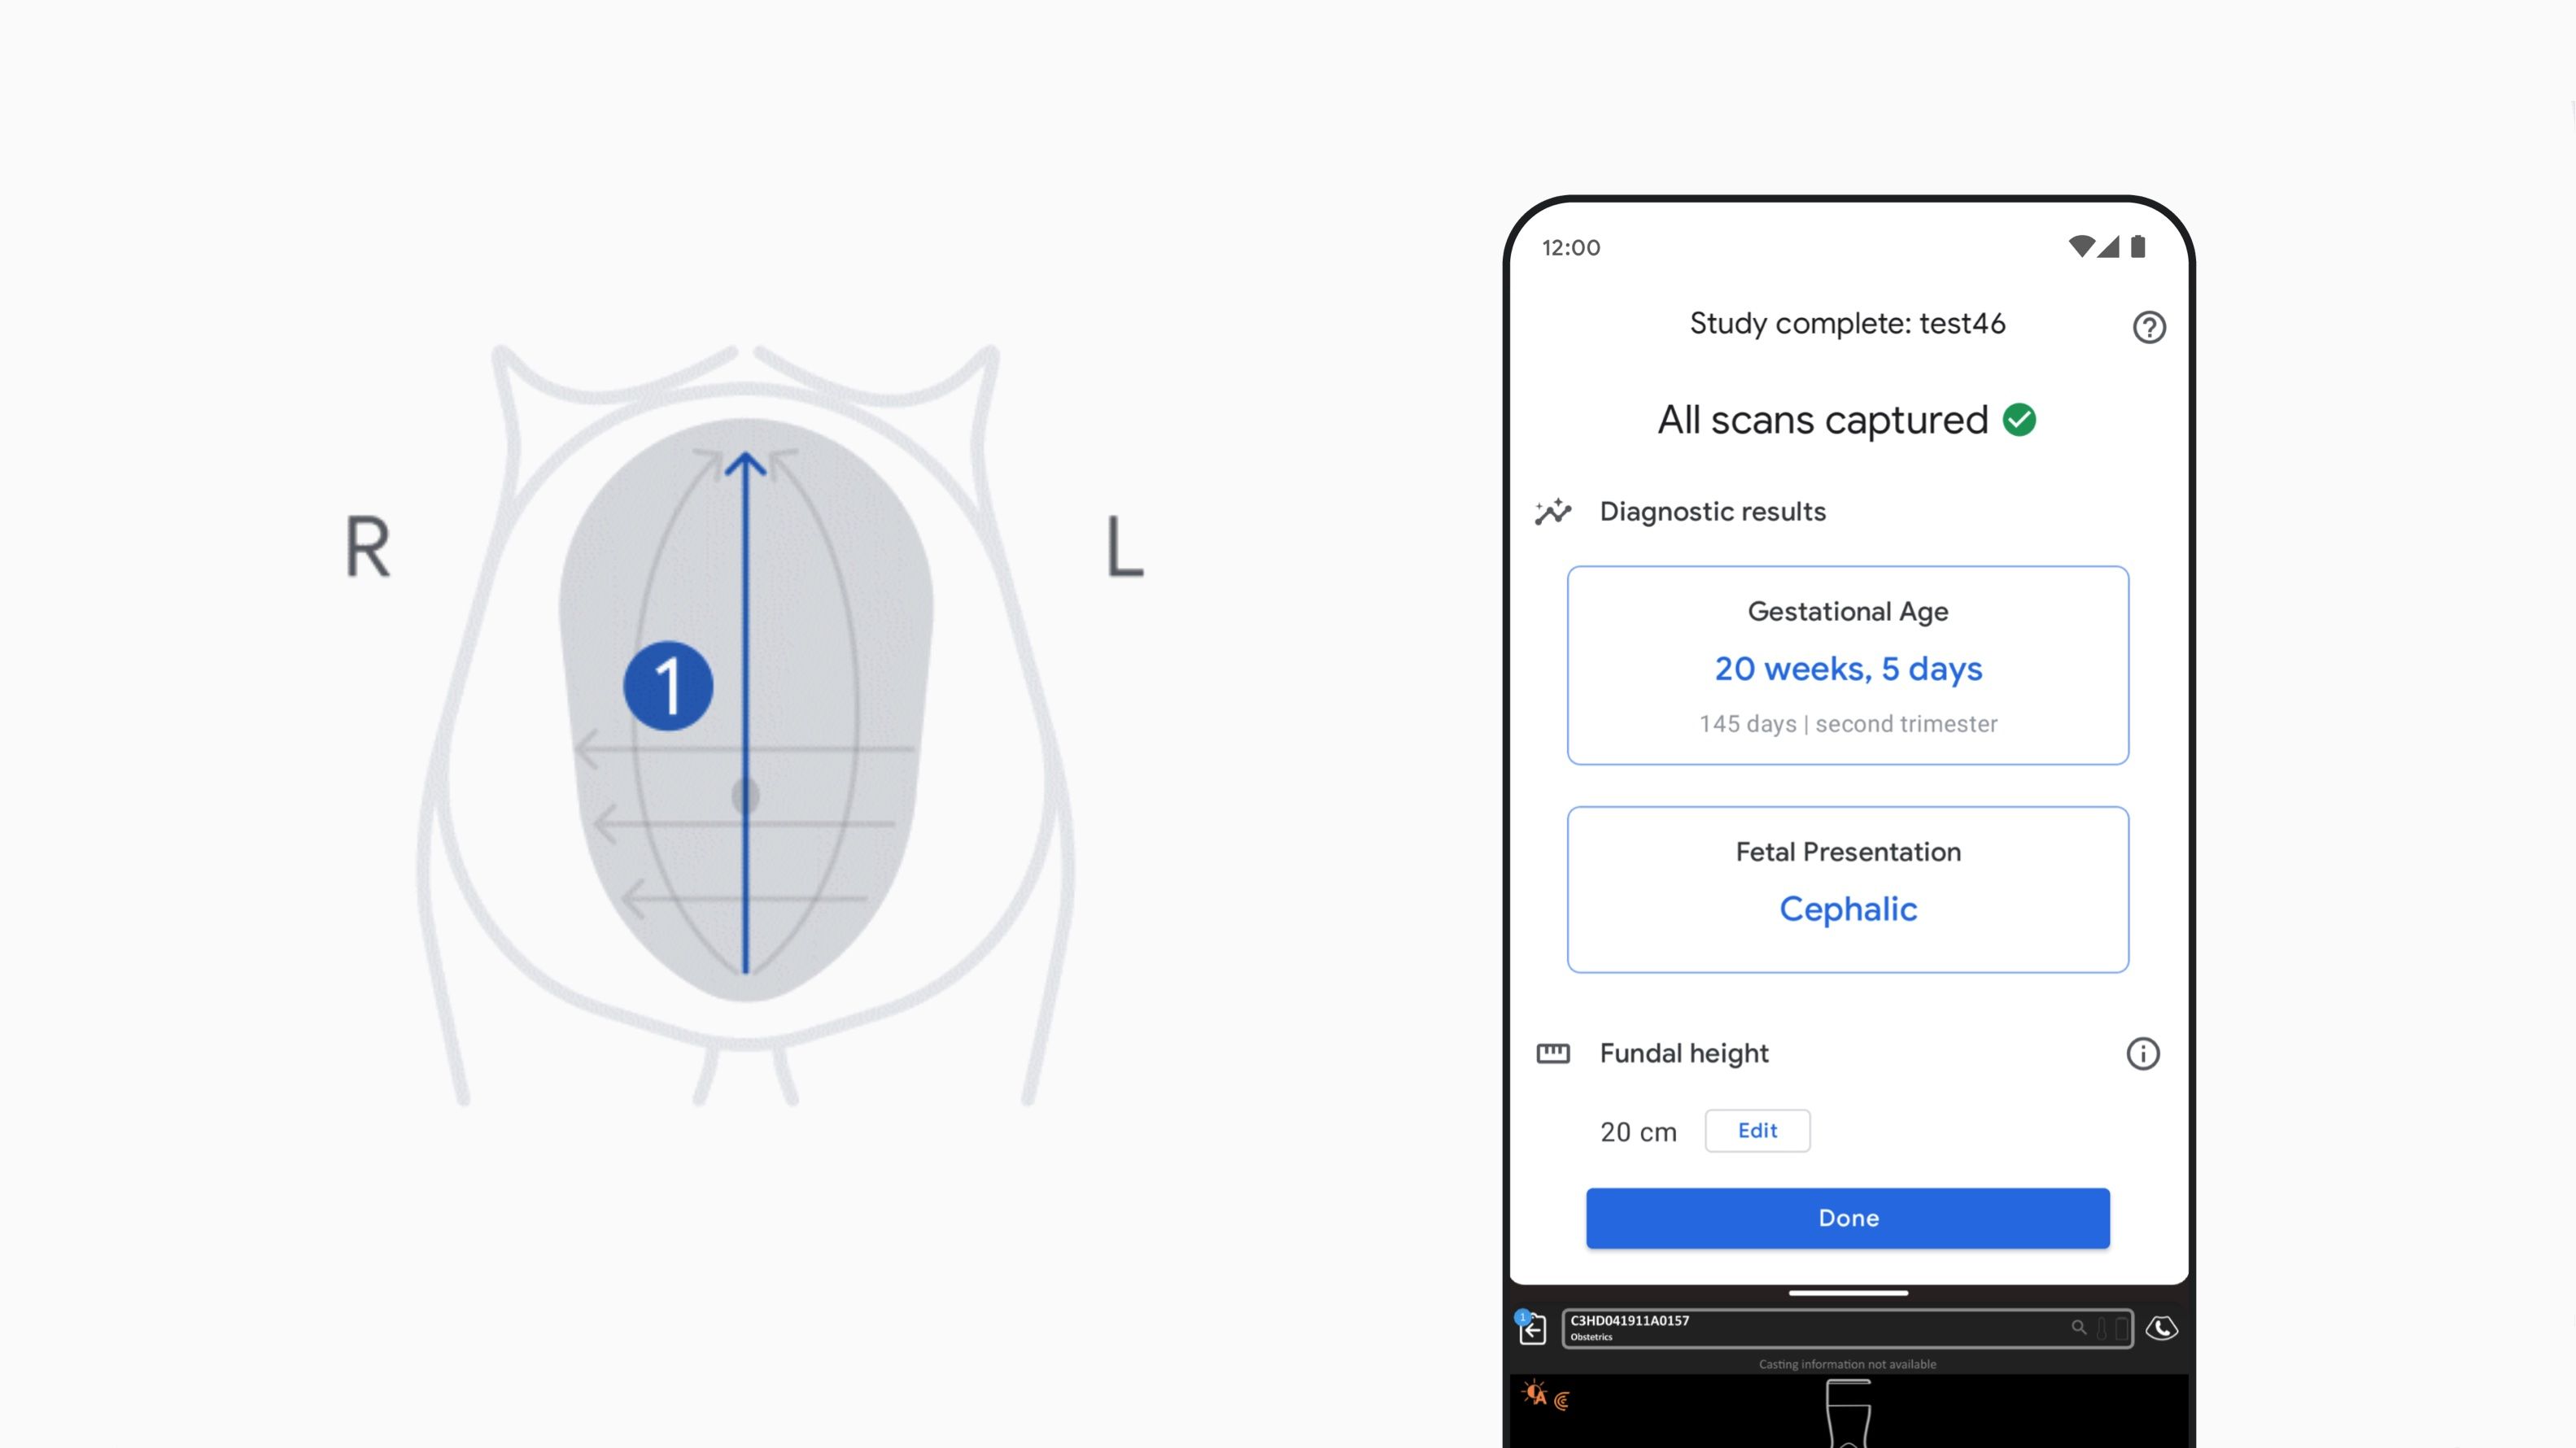
  • Ultrasound devices with Google AI are being used to detect breast cancer in Taiwan and determine gestational age in expectant mothers in Kenya.
  • Another Google AI tool that checks chest X-rays for signs of tuberculosis is being rolled out in Sub-Saharan Africa.
A schematic image of an ultrasound of a pregnant uterus and a screen that shows gestational age.
Google’s AI-powered ultrasound system. Image: Courtesy of Google

Between the lines: The company is acutely aware of criticisms that “Dr. Google” can sometimes lead users to misleading or dangerous health guidance.

  • Another new YouTube feature helps people “find human answers” to their health questions, said Garth Graham, director and head of health care and public health at Google/YouTube.

Google also announced a partnership with ThroughLine, which connects users to free mental health crisis support in more than 100 countries.

  • “This will increase the number of crisis helplines that appear at the top of search results,” reads a blog post from DeSalvo. The feature is aimed at “searches related to suicide, domestic violence and other personal crisis topics.”

The big picture: Even as they take breathtaking strides toward improving health care with AI, tech companies and others have been stumbling with what they’ve unleashed.

  • Older people covered by Medicare Advantage are finding their benefits cut off by AI algorithms no matter how dire their medical needs, a Stat News investigation found.
  • Verily Life Sciences, a unit of Google parent company Alphabet that focuses on treatment personalization, started laying off staff in January, per the Wall Street Journal.

On the plus side, AI is starting to detect breast cancers that radiologists miss, as the New York Times reports.

  • The development is “one of the most tangible signs to date of how AI can improve public health,” per the Times — yet the technology produces too many false positives and still needs to “show it can produce accurate results on women of all ages, ethnicities and body types.”

The bottom line: Medicine will always need to rely on a healthy mix of technology and human know-how.

  • “AI on its own cannot solve all of health care’s problems,” Alan Karthikesalingam, the surgeon-scientist who leads Google Health’s machine learning research group, said Tuesday.
  • “Medicine, after all, is about caring for people.”