Massachusetts’s COVID-19 public health emergency runs out on May 11, ending state masking requirements in health care facilities.
Public health advocates are urging Massachusetts health officials to keep universal masking in place at health care facilities. John Tlumacki / The Boston Globe, File
A coalition of public health advocates is urging Massachusetts to keep masking requirements in place in health care settings, even after the state’s COVID-19 emergency declaration runs out in early May.
“Without universal masking precautions in healthcare, vulnerable people face substantial risk of being exposed in waiting rooms or clinical settings against their will, violating their autonomy, and deterring many from seeking much-needed care,” the Massachusetts Coalition for Health Equity wrote in an open letter last week.
Coalition co-founder Dr. Lara Jirmanus, a family physician and Harvard Medical School instructor, explained in a virtual press conference Wednesday that removing masking requirements from health care settings will be especially risky for babies and children who can’t mask.
“People can bring these infections home to their loved ones and hurt them,” Jirmanus said. “And I will say personally, as a parent of a 16-month-old baby, this is part of my calculation.”
In September, the Centers for Disease Control and Prevention revised its guidelines to relax masking requirements for health care facilities in parts of the country with lower levels of community transmission. (In Massachusetts, state masking requirements remained in health care settings even after the CDC change.)
Relying on community transmission data to dictate masking is flawed, Jirmanus asserted, citing underreported cases.
According to the coalition’s letter, “far fewer people are testing for COVID-19 as much required routine testing has ended, federal funding for COVID-19 testing has diminished, and most rapid tests are not reported. Further, most low-wage workers don’t have paid sick time, and many are incentivized or compelled to go to work with COVID-19, or to avoid testing.”
Even when transmission rates are low, clinics and hospitals will still be an epicenter for COVID-19 patient care, creating opportunities for the virus to spread, according to the coalition’s letter. Removing masks from health care settings also puts providers at risk at a time when the health care system is overrun with staffing shortages, the group argued.
A spokesperson for the state’s Executive Office of Health and Human Services told The Boston Globe that the state health department will continue to track COVID-19 cases and make adjustments as circumstances change.
The spokesperson also told the Globe that infection control leaders at several of the largest hospital systems in Massachusetts have repeatedly asked state health officials to end the mask mandate.
The Massachusetts Coalition for Health Equity remains unconvinced.
“We are wondering, when we take a look at that Globe article, why have hospital administrators been lobbying to remove masks? Is this about the money?” Jirmanus asked. “It doesn’t make sense. Removing masks in health care … is going to cause health worker outbreaks and it’s going to exacerbate existing staffing shortages and thereby exacerbate the budget crisis.”
She added: “We all have a loved one in our lives who could be hurt by a COVID infection. … and we could all be harmed by long COVID. So let’s be safer together.”
Newsletter Signup
Stay up to date on all the latest news from Boston.com
Physicians, nurses and other front-line providers know firsthand the health impacts of climate change. Air pollution exacerbates asthma and emphysema; extreme heat worsens heart and kidney conditions; and rising temperatures increase the occurrence of a wide range of illnesses, including mosquito-borne infections and depression.
That’s why it’s so shocking to learn that health care itself is a major contributor to climate change.
In the United States, the health sector is responsible for nearly 9 percent of the nation’s greenhouse gases. Researchers estimate that the environmental harm caused by medical care ultimately costs as many lives as preventable medical errors, which are responsible for as many as 98,000 deaths annually. This is in direct conflict with the mission of the healing professions.
Brian Chesebro, an Oregon-based anesthesiologist who serves as medical director of environmental stewardship at Providence, had this “aha” moment in 2016. At the time, he told me, he was going through a period of “eco-grief” about the state of the Earth.
Sign up for The Checkup With Dr. Wen, a newsletter on how to navigate the pandemic and other public health challenges
“Instead of spiraling down, I realized that my greatest opportunity to advance environmental stewardship was through my job as a physician,” he said. “I could address it in my own practice, then, as a physician-leader in my hospital, inspire change in my colleagues.”
His work as an anesthesiologist turned out to be the right launchpad. That is because some anesthetic gases commonly used in operating rooms are extremely potent greenhouse gases.
As Emily Mediate from the nonprofit organization Health Care Without Harm told me, the elimination of one specific gas, desflurane, could make a profound impact. “Desflurane has the global warming potential of over 3,700 equivalents of carbon dioxide,” she told me. “It lasts for 14 years in the atmosphere.” Her organization is among those that have been urging health-care systems to move away from desflurane and switch to sevoflurane and isoflurane, anesthetics that are clinically equivalent but have a small fraction of the environmental consequence of desflurane.
Chesebro took on this challenge. He began by educating fellow clinicians. “We weren’t taught to think in terms of environmental impact in residency,” he said, noting that the response from other physicians was primarily “surprise, interest and curiosity.”
He also measured and documented each anesthesiologist’s desflurane use. When Chesebro informed a colleague that his use of desflurane was equivalent to driving a fleet of 12 Hummers, the colleague sputtered in defense, “But I drive a Prius!”
“He was trying so hard to make wise stewardship choices, but he didn’t realize that his environmental impact as an anesthesiologist far outstripped any other facet of his life,” Chesebro said. “He changed his practice that day and has never used desflurane since.”
Over time, Chesebro redesigned systems so that desflurane was less easily accessible than other inhaled gases. “We still keep one or two desflurane vaporizers so someone could use it if they really need it, but it is no longer at arm’s reach in every operating room,” he said. He believes this was more effective than banning the gas. “Instead creating adversaries, we created an army of advocates who are eager to partner with us” on other efforts.
Before this intervention, the Providence system’s eight Oregon hospitals used desflurane 42 percent of the time, according to Chesebro. Now, he says, the rate is 0.07 percent. “We’ve cut emissions related to anesthetic use by 95 percent, and, because desflurane is a more expensive option, we’ve also cut the financial cost by 80 percent.”
Providence is not alone. Mediate shared success stories from around the country. Virginia Mason Medical Center eliminated desflurane use, thanks to the advocacy of an anesthesiologist and an anesthesia tech there. This resulted in an estimated 60 percent decrease annually in its operating room greenhouse emissions and saved the hospital more than $30,000 each year. Advocate Aurora Health, in a nurse-led effort, also cut its use of desflurane. Since 2017, the health system has reduced its anesthetic gas emissions by 75 percent and saved $1.6 million.
There is still a lot more work to be done. While the U.S. health system accounts for about a quarter of all global health sector-related emissions, it is far behind many peer countries in tackling this problem. In fact, many political leaders are actively trying to block sustainability initiatives.
I was heartened to learn that Health Care Without Harm’s Climate Council includes 21 health systems representing more than 600 hospitals across 43 states. In addition to health sector-specific reforms, they are encouraging others to join them in addressing building emissions, switching to renewable energy and limiting single-use plastics, among other efforts to reduce their carbon footprint.
“Health-system leaders understand that the climate crisis is a health crisis,” Mediate said. “Better care is low-carbon care.”
That’s a perspective on medical care that I wasn’t aware of before. Now, I’m convinced that clinicians’ obligation to “first do no harm” should extend to our responsibility to reduce the effects of climate change caused by the health-care sector itself.
Indication up for the On Position newsletter here.
The United States has the biggest for-financial gain wellbeing treatment system in the earth.
Extra and more wellness care pros say that they’re remaining compelled to make decisions that are terrible for sufferers.
“We not only sense that we are unable to offer what we know the affected individual requirements. But we truly feel complicit in a revenue-1st process which is asking us to act in techniques that put gain higher than what’s ideal for the affected individual.”
And that sales opportunities medical doctors to experience from ethical accidents.
Today, On Level: Ethical injuries in contemporary medication.
Dr. Elena Perea, healthcare facility psychiatrist in western North Carolina.
Job interview Highlights
On initially signals of moral injury in modern day drugs
Dr. Wendy Dean: “I felt these from the time that I entered into medication, but actually in excess of the previous 10 years or so, it would seem to have intensified. And I feel the only reason that I could see that so evidently was mainly because I was no for a longer period training. So I had a little bit of means to phase away and to consider a broader look at. And so I could check out my colleagues throughout the country who had been struggling and claimed, like Jessica, I continue to enjoy my individuals, I really like the medication I exercise, but it is really almost everything else that is acquiring in the way that is definitely grinding me down.”
What’s producing ethical harm in wellness treatment?
Dr. Wendy Dean: “Each individual time that we are questioned to attend to a thing that is not our patients’ finest fascination. So, for instance, when we have to transform away, we have to transform our backs in order to fill in the digital health-related document. That feels like a compact turning away from our sufferers, taking treatment of our corporation instead of having care of them. When we have to invest an hour obtaining a prior authorization for treatment that we know they ought to have. That feels like we’re turning in direction of the enterprise of drugs and having treatment of it instead than using treatment of our patients. It really is not any a single significant egregious issue. It can be many, a lot of lesser. Cuts, shall we say, loss of life by a thousand cuts, not one massive damage.”
On the troubles for health and fitness treatment pros
Dr. Wendy Dean: “The expenditures of wellness treatment and turning into effective are section of what drives this. But the other problem for clinicians as a total is that the corporatization of care has led to a change in the place decisions are built rather than becoming built by clinicians who perform at the bedside, irrespective of whether they’re nurses or physicians, they’re becoming shifted into administration, higher administration or into the C-suite. And it is not infrequent that the folks who are at those people stages could not at any time have been a clinician. And so, striving to make choices for individuals on the front strains gets more challenging. And it could be much less closely linked to what will perform for them.”
Are any of these selections practical or even on the horizon?
Dr. Wendy Dean: “There are locations that are that are using some of individuals actions. And, for illustration, the FTC has presently started having action on health and fitness care process consolidation. They’re hunting at it not just from the affected individual perspective and irrespective of whether or not it will be much less expensive for them to receive care in the procedure. But also searching at it from a workforce point of view, what will be the effect on the staff in the place?
“So, for instance, in Albany, New York, lots of of the crisis rooms there are contracted with just one single health-related team, one particular for profit unexpected emergency doctor team, an unexpected emergency doctor who is not happy there, won’t be able to move without the need of actually going themselves and their family due to the fact there is a monopoly on crisis care there.
“So breaking that monopoly, breaking the noncompete clauses that preserve medical professionals from going throughout town, they have to go across the county or throughout the state. There are a large amount of alternatives that we can choose, but we have to be eager to make those people adjustments.”
Ebook Excerpt
Excerpt from If I Betray These Terms by Dr. Wendy Dean. All legal rights reserved. Not to be republished without the need of authorization of the publisher, Steerforth Push.
A recent study offers up a trove of data on dog cancer health outcomes from targeted therapies that could help improve care for people.
A company that pairs dogs with cancer care, The One Health Company, has sequenced genetic mutations in more than 1,000 dogs with cancer and then treated them with medicines targeted to specific genes or proteins available to humans. Both the genetic mutations and the doggie patient outcomes were similar to that of humans. Researchers believe this data, which is pulled from veterinary clinics, can help lead research into better treating some canine cancers, which in turn could help pharmaceutical companies develop human drugs for harder-to-treat cancers.
“Some of the most common predictive biomarkers that we’re seeing in the dogs are also some of the most common for human non-small cell lung cancer, breast cancer — some of the big tumor types,” One Health CEO Christina Lopes told Ruth.
Researchers know dogs and humans have a lot of genetic similarities that can be mined to better understand cancer. Dogs and humans share the BRCA1 gene mutation most associated with breast cancer, for example. The National Institutes of Health has run a comparative oncology program with dogs for 20 years.
But studying dog patients is expensive and obtaining large-scale data, particularly genomic data, can be difficult. One Health has been able to get that data by erecting a veterinary business around it. The company charges pet owners for the sequencing and medicine, which they try to keep lower than chemotherapy costs (on average $4,317 in the U.S., according to medical expense credit card company CareCredit).
Why it matters: Instead of forcing researchers to hunt for grant dollars to cover the cost of sequencing and medications for dog clinical trial patients, dog owners pay for it. Pet insurance can cover the cost of One Health’s precision medicine product, the company said. But not all pet owners have pet insurance, which can be expensive compared with typical veterinary treatments.
On the regulatory front: The FDA has pushed for a shift away from using cheaper lab animals. That could make veterinary patients more promising prospects for clinical trials.
The pitch from One Health is that pharmaceutical companies could use its insights to inform future cancer research in humans. Lopes said that pharmaceutical researchers might have a signal in their human data they want to see replicated in One Health’s canine data. Alternatively: “Do we have a signal in our data set that they can then interrogate in their data set?”
For example, dogs suffer from a cancer called hemangiosarcoma, which is associated with the genetic mutation PIK3CA. This mutation correlates to a rare form of cancer in humans known as angiosarcoma. Hemangiosarcoma makes up a significant chunk of dog cancer cases. Lopes wonders whether testing drugs targeted to PIK3CA in dogs might help give researchers some answers on how to treat angiosarcoma.
There’s also an opportunity for research into drug repurposing. In the study, researchers found that dogs with BCRA1 mutations had better outcomes when treated with dasatinib — a drug used to treat certain types of blood cancer in humans, and considered a potential breast cancer treatment.
“Human biopharma companies want to de-risk drugs,” said Lopes. Her platform could help them do that, she added.
This is where we explore the ideas and innovators shaping health care.
Mosquitoes carrying yellow fever first hitched rides on slave ships to the Americas some 500 years ago. A new study also hints at when mosquitoes evolved to transmit the virus: some 5,000 years ago, during a period of natural climate change at the southern border of the Sahara desert.
Share any thoughts, news, tips and feedback with Ben Leonard at [email protected], Ruth Reader at [email protected], Carmen Paun at [email protected] or Erin Schumaker at [email protected].
Send tips securely through SecureDrop, Signal, Telegram or WhatsApp.
Today on ourPulse Checkpodcast, host Katherine Ellen Foley talks with Alice Miranda Ollstein about internal divisions that are splitting the abortion-rights movement over their efforts to keep abortion legal by putting it to a popular vote.
Walgreens-backed VillageMD is forging a primary and urgent care mashup that may rejigger what care looks like for millions in the Northeast and beyond.
VillageMD wants to expand into rural America and has already acquired one of the biggest urgent care chains in the New York City area, moving closer to that goal.
Last month, VillageMD finalized its $8.9 billion acquisition of Summit Health-CityMD. It also announced a deal with Connecticut-based Starling Physicians, which offers primary, specialty and urgent care.
The acquisitions are an extension of VillageMD’s value-focused health care model, Tim Barry, co-founder and CEO of VillageMD, told Erin. They’re also a counterbalance to the current U.S. health care system, which Barry says is too hospital-centric.
Barry’s vision is to offer 24-hours-a-day, seven-days-a-week accessibility for patients — no ER visits, no hospitalizations. “We want to make sure you get access wherever you need it, whenever you need it – period,” Barry said.
What that looks like: In New York City, a VillageMD patient who lives in New Jersey and commutes into Manhattan could stop at a CityMD clinic near their office to get treatment for a sinus infection.
“That doctor is gonna have access to their medical record and know their whole health history,” Barry said.
The strategy works in reverse, too. If a new patient who has a chronic disease visits a CityMD, the team can connect them with one of its primary care doctors in the broader New York area. “We know that the best thing for that patient would be to have a relationship with a primary care doc,” Barry said.
RuralMD: True to its name, CityMD operates primarily in the greater New York City metro area.
But that’s slated to change, Barry says. Post-merger, the organization has its sights set on moving CityMD into dense metro areas VillageMD already operates in, like Houston, Phoenix and Atlanta.
Then it will turn its sights on the last frontier: rural America.
While health care in rural areas is known for being expensive and difficult to access, Barry, who grew up in Sturgeon Bay, Wis., noted that people who live in rural America are used to driving farther to get care, especially if there’s a dearth of options. “You either have the doctor’s office open or the hospital’s open, and there’s nothing really in between,” he said.
VillageMD could create an in-between option for those communities, Barry added.
Barry’s bottom line: More in-person health care touches, fewer ER visits, lower costs.
“We’re bankrupting more and more people every year because of medical debt,” he said. “People aren’t getting bankrupted in the health care system because they had a $60 PCP visit. They get bankrupted because they had a $30,000 hospital bill that they didn’t expect.”
To be eligible for Medicaid and Medicare’s Programs of All-Inclusive Care for the Elderly, individuals must be 55 or older, need nursing home–level care and be capable of living safely in their community with assistance.
Almost 90 percent of participants are dual eligibles, who qualify for both Medicare and Medicaid by virtue of their age or disability and low incomes.
The committee found that PACE programs met five key criteria: improved patient experience, better outcomes, lower costs, clinician well-being and health equity.
“Healthy aging that includes aging in place is not currently a feasible option in many rural communities,” the report concluded. “PACE is uniquely situated to adapt and meet the complex needs of rural older adults.”
But the program faces some challenges before states and CMS can implement it rural areas:
— PACE can’t charge co-pays or deductibles, and PACE participants can’t enroll in other Medicare prescription drug plans, meaning higher costs for patients.
— Rural areas tend to have small populations so it’s harder to spread costs across the group if there are fewer patients.
— Patients in rural areas have less access to broadband than those in more populated areas.
— More than 140 rural hospitals closed between 2010 and 2023, and others are financially distressed, putting them at risk of closing, which could lead to a shortage of facilities where PACE can be implemented.
— Medicare and Medicaid patients in rural areas have limited awareness of PACE.
Why it matters: In the U.S., 1 in 5 adults older than 65 lives in a rural area, according to the Kaiser Family Foundation. Rural Americans are more likely to be elderly, have a disability and live in poverty. At the same time, they typically travel farther for health services, receive lower quality services than their urban counterparts and pay more for the services they get.
PACE programs, which include doctors, nurses, physical therapists, social workers, dietitians and transportation drivers, aim to improve health care access for older adults and maintain low costs by keeping participants out of hospitals and nursing facilities as long as possible.
What’s next: There are 149 PACE programs operating in 32 states, according to the report, with a number of program applications under consideration.
The committee offered a series of policy recommendations to the FCC, Congress and the White House to overcome rural-specific challenges to starting PACE programs, including making PACE sites eligible for broadband funding resources, providing start-up grants to new rural PACE sites, considering public-private partnerships and encouraging state Medicaid directors to send letters to long-term care providers to increase awareness of the program.
This week in 1927, the curtain fell on a Broadway creation of George Bernard Shaw’s medical drama, “The Doctor’s Predicament.” Shaw – who is most well known for writing “Pygmalion” – was an Irishman by birth, a socialist by challenging expertise and a firmly dedicated Londoner. He wrote the engage in in 1905, while peeved at his individual physicians and the professional medical occupation in basic.
“The Doctor’s Dilemma” advocates for a socialized technique of wellbeing care shipping and a removing of the gain motive from health care observe. The engage in dramatizes a predicament professional by posh medical doctor Sir Colenso Ridgeon, who has a one dose of a curative elixir and two clients who could gain from it. On the a person hand is a gifted artist named Louis Dubedat who grifts income from his acquaintances and cheats on his loving wife Jennifer on the other, a devoted but poor medical doctor who serves the underprivileged irrespective of their capability to pay out. To make ethical matters even worse, Colenso falls hopelessly in like with Jennifer.
Shaw pulls out all the stops with a comic condition that poses a considerably further problem: How does one particular quantify the value of yet another person’s lifestyle and who is even skilled to do so reasonably and justly?
Study A lot more: How ‘Raisin in the Sun’ creator Lorraine Hansberry described what it meant to be ‘young, gifted and black’
“The Doctor’s Dilemma” first hit the boards at the Royal Court Theatre in London’s storied West End on Nov. 20, 1906. The engage in ran for only 50 performances, at a time when a Shaw byline did not however guarantee very long strains of ticket-consumers.
Two German actors in “The Doctor’s Dilemma” in 1938. Photo by Imagno/ Getty Visuals
Just 21 many years afterwards, when saying the 1927-28 revival, The New York Situations opined: “One should bear in mind that Mr. Shaw then was not rated as he is now. His status has grown with the gradual whitening of his nice crimson beard his fame in equally England and The usa is now so wonderful that any enjoy of his is just about confirmed a run. It was not usually as a result.”
When Shaw complained about the commodification of wellness care, he was crafting about cottage industries of incompetent and impotent non-public practitioners who did far better monetarily by offering ineffective nostrums and incompetent theories. Today we see commodification in all the strategies that health care is run by large industries.
Study Much more: The unsuccessful Broadway musical I want each and every professional medical university student could see
Cautious of doctors of all stripes, Shaw was a strict vegetarian and vociferous wellbeing nut. Coming out of the fog of the most substantial and highly-priced pandemic of our lifetimes, we might ponder how Shaw predicted the value of globalizing community well being, combating infectious ailments, and educating men and women to dwell much healthier lives, including far better more sustainable, calorie-helpful, tobacco-, liquor-, toxin- and drug-cost-free eating plans. However, even he was not immune to the entice of a famous medical professional promoting his possess wellness merchandise.
When on a voyage around the environment in 1936, Shaw manufactured a unique end to Dr. John Harvey Kellogg’s sanitarium in Miami Springs, Florida. The two gentlemen — a single famous for producing a healthier way of living he called “biologic living” and co-creator of Corn Flakes, and the other the world’s most renowned living playwright — sat down for lunch, followed by a lengthy consultation and health-related assessment. Amid the flashes of photographers’ cameras, the two men sipped freshly squeezed orange juice.
The next day, Kellogg described that he was involved about the playwright’s lower purple blood mobile count (40 percent significantly less than regular, at 3,000,000) and hemoglobin (30 percent deficient at 71 mg/dl).
Dr. John Harvey Kellogg in dialogue with IGeorge Bernard Shaw in Miami in 1936. Photo by Archive Pics/ Getty Images
These conclusions were being the result of Shaw’s diet program excluding red meat (and, that’s why, ample iron) in his diet plan. Even though an improve in iron-prosperous, environmentally friendly, leafy veggies, these as spinach, would without doubt assist Shaw reach a usual blood stability and truly feel superior, the medical professional suggested a different, marginally shady, way to obtain people finishes.
Go through Much more: How Dr. Kellogg’s entire world-renowned health spa created him a wellness titan
He prescribed his newest foodstuff invention, a product he identified as “Food Ferrin,” which was a concentrated extract of spinach that supplied a day’s worthy of of iron in a teaspoonful or two. The option would be to ingest a pound of spinach each day. “I am sending you a bottle of this,” Kellogg wrote Shaw, “and if you think worthwhile to make use of it, I will gladly see that you have a larger offer.”
The check out — and the plug for Food items Ferrin — was broadly described in publications ranging from the Miami Herald to The New York Occasions and the Literary Digest. The medical professional stroked Shaw’s moi with a prediction that he would very easily dwell to be 100 (Shaw died in 1950 at the age of 94).
Kellogg further more pontificated to the reporters recording his each individual word that he sincerely hoped that “my tips may possibly establish of some company to the most distinguished of living Englishmen,” hence presenting a new doctor’s predicament: the most marketable health practitioner in America giving free samples of his latest foray into fortified foods to the profession’s finest critic.
As the worst of the COVID-19 pandemic appears to fade in the rearview mirror, public health departments are already preparing for the next threat, noting that they have built better operational infrastructure, but caution that budget cutbacks and a health care worker shortage may be putting the country at risk.
The World Health Organization has warned that the accelerating pace of climate change, deforestation and globalization means that it isn’t a matter of if, but when the next pandemic will strike. Even in the midst of the COVID-19 pandemic, state and local health departments were forced to grapple with yet another emergency last summer, with the emergence of the monkeypox (now known as mpox), outbreak.
At least 13 state health departments and 11 hospital associations told ABC News that chronic staffing shortages and new threats to funding may undermine their ability to swiftly respond to future pandemic threats.
“Without the personnel to do the hard work of analyzing data, interviewing cases, tracing contacts, testing specimens, and performing other essential public health activities, our nation is less prepared in some ways than it was before 2020,” Dr. Jay Varma, director of the Cornell Center for Pandemic Prevention and Response told ABC News.
The American Hospital Association has called federal lawmakers to reauthorize the Pandemic and All Hazards Preparedness Act to strengthen the Strategic National Stockpile, to fund the Hospital Preparedness Program, and require more collaboration between the federal government and stakeholders to build national data infrastructure.
Health care worker shortage
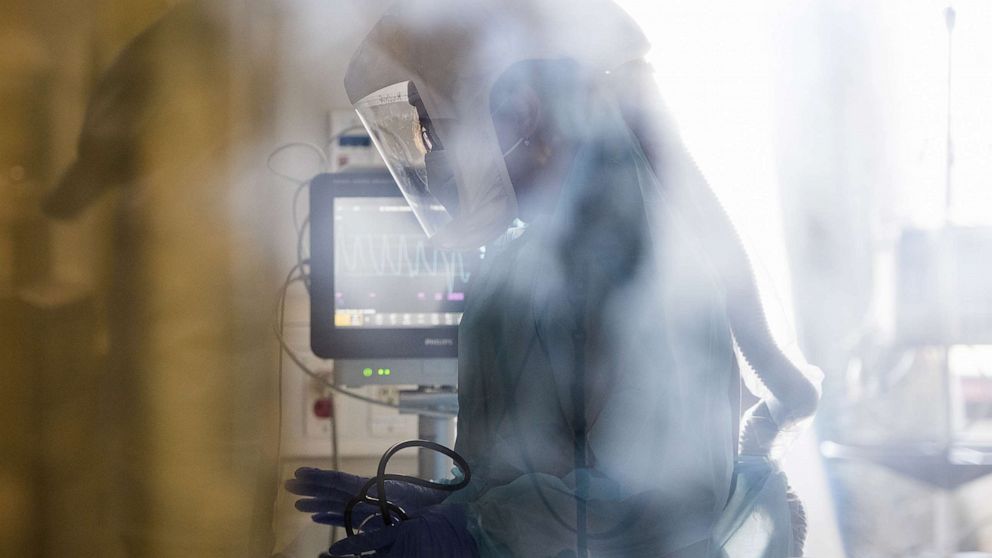
After a grueling three years caring for patients on the front lines of the COVID-19 pandemic, nurses continue to leave the health care sector en masse, according to state health departments and state hospital associations, sparking widespread shortages nationwide that states warn may lead to an inability to care for patients during a new outbreak.
Before the pandemic, Georgia was already dealing with a nursing staffing shortage. Now, with not enough nurses graduating in the state, the governor has created a statewide healthcare workforce commission to increase the hospital workforce, according to Anna Adams, the executive vice president, external affairs of the Georgia Hospital Association, a nonprofit trade group.
A nurse tends to a patient inside the COVID-19 unit of Salinas Valley Memorial Hospital in Salinas, Calif., Sept. 2, 2021.
Bloomberg via Getty Images, FILE
Part of the issue, health and hospital association officials from several states told ABC News, was the recurring cycle of worker shortages leading to increased labor costs – with turnover driving higher expenses to hire and recruit new staff.
“Now, nurses and others are leaving health care altogether, to companies that have signing bonuses and very high hourly rates. And so all of a sudden, hospitals are in a position where the only way we’re going to have an adequate nursing force is to work with the nurse traveler agencies,” said Brian Peters, CEO of the Michigan Health & Hospital Association.
In addition, some hospitals are experiencing negative profit margins, making less money in relation to their own expenses compared to before the pandemic. California health officials, for example, noted that over half of hospitals in the state already had unsustainable margins before the pandemic. This worsened during the COVID-19 pandemic as the state’s total hospital expenses rose 15{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} in just one year. According to state officials, California hospitals are losing money on operations.
Funding in flux
Early in the COVID crisis, as case counts exploded and deaths began to creep up, public health departments received hundreds of billions of dollars in funding from the federal government to support their work. But most of that money was earmarked to respond to the emergency — not to shore up public health permanently. Now, many are warning that the flood of money could transition to a trickle without renewal of some of the federal funds, which could lead them to cut contractual employees and reduce some of their initiatives.
“Funding comes in on specific diseases,” said Susan Kansagra, North Carolina’s state health officer. “When that disease goes away, funding goes away. We’re left rebuilding.”
Most state public health departments significantly expanded their workforce in the early days of the pandemic, and they have larger staffs now than in 2019. But many of those hires were temporary positions, including some epidemiologists and behavioral scientists. Washington, for example, stated that even now, 30{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of its current workforce were in time-limited positions.
There is also high turnover in the public health sector. The Virginia Department of Health noted that about a third of its workforce had minimal work experience prior to 2019, whereas now 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} has less than two years of know-how on the job. Many experienced public health workers left their jobs in the past few years, often because of the political blowback and pressures from far-right groups opposed to things like masks and vaccines, state health officials told ABC News.
While most state health officials interviewed by ABC News shared they may need to tighten their ranks amid lower funding support, some felt confident in being able to revamp their workforce should another crisis arise.
“The takeaway for us is that we have worked through rapid hiring, onboarding, and training processes, so that we could do it again if needed,” the Utah Department of Health and Human Services said to ABC News in a statement.
Identifying the next threat
With the rise of at-home tests and dwindling contact-tracing programs, public health departments have shifted their attention to different methods of identifying where COVID-19 is spreading most and detecting any new diseases that may pose a threat.
Wastewater has become a key tool for epidemiologists to quickly identify where pockets of the community may be experiencing a greater number of COVID-19 cases than usual. Most state health departments contacted by ABC News noted they had integrated a wastewater surveillance system and were tracking old and new threats.
An employee collects a wastewater sample to monitor COVID-19 in Tucson, Ariz., Aug. 31, 2020.
Bloomberg via Getty Images, FILE
Nevada officials shared that the state built “a viral respiratory surveillance program to expand upon influenza surveillance efforts to help understand what respiratory viruses are circulating, the magnitude of these viruses within communities, and the overall severity of the viral illnesses” with a team set to monitor data for early detection for potential surges.
Most states also developed dashboards to inform the public of case numbers and hospitalizations statistics as well as avenues to collect vaccine data or notify contacts of someone sick of an exposure. Those tools are in place and ready for future disease threats, so health department wouldn’t have to start from scratch.
“We’ve created forums for sharing information throughout the three years to ensure that we can continue to respond to COVID-19, and also that we will be ready in the future,” said Nicole Stallings, chief external affairs officer at the Maryland Hospital Association.
Experience counts, say health departments
State health department officials reached by ABC News overwhelmingly said their experience responding to COVID-19 means they are better prepared to react to a new health threat than in 2019.
“We’re better trained, better staff, better equipped and managed, more responsive, and experienced personnel, our information systems are much more robust. So, I think, at this point, and recognizing that all capabilities atrophied over time, but at this point, we’re much better prepared than we were in 2019,” said Robert Mauskapf, director of the office of emergency preparedness at the Virginia Department of Health.
Still, some public health experts remained skeptical, noting that budget and staffing problems — and even cultural shifts — will make it harder to respond to future threats.
Many states, for example, have passed or are considering laws that would prohibit mask mandates or vaccine requirements — both tools that helped protect people against the spread of COVID-19.
A discarded surgical mask, April 26, 2022, in Chicago.
Chicago Tribune via Getty Images, FILE
So even though health departments know the strategies that helped during the COVID-19 pandemic, they might not have the ability to implement them as successfully going forward.
“Federal, state, and local health departments have far fewer personnel today than they did before [the pandemic]. This is a consequence of public health staff being chronically over-worked and underpaid, public health officials being verbally attacked on social media, including by elected officials, and a broad national narrative that public health is somehow incompetent,” Varma said.
ABC’s John Brownstein, Ph.D., Sony Salzman, John Santucci, Nicole Wetsman, Emma Egan, Sara Avery, Alexandra Myers and Soorin Kim contributed to this report.