The state of clinical trials in the NHS is “much worse than it has been in years” with patients losing access to cutting-edge cancer and dementia treatments, one of the UK’s most senior clinicians has warned.
Sir John Bell, the regius professor of medicine at the University of Oxford and a government life sciences adviser, said the UK’s approach needed “a full overhaul, top to bottom” to prevent a collapse in the number of clinical trials being conducted in the NHS.
“I don’t think there’s any doubt that companies are choosing not to evaluate their drugs in the UK,” he said. “The risks [to patients] are much bigger than have been alluded to.”
The intervention comes after the government launched an independent review led by the former health minister James O’Shaughnessy into why the NHS had seen a 44{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} drop in participants recruited to commercial clinical trials in the past five years. The UK is rapidly losing ground to countries such as Spain, Poland and Australia, falling from fourth to 10th internationally for phase III trials.
Prof John Bell says patients get access to groundbreaking treatments and the NHS makes money from conducting commercial trials. Photograph: Sophia Evans/The Observer
Reduced access to trials is particularly concerning for patients with limited routine treatment options, such as the roughly 3.5 million people living with rare diseases and patients with dementia and advanced cancer.
Beyond clinical benefits, the NHS makes money from conducting commercial trials. “You get the drugs for free, you get the treatment for the control arm for free, the NHS rides for free for everyone in the trial and pharma pays pretty well to get these trials done,” said Bell.
However, Bell said bureaucracy that had been simplified during the pandemic to fast-track trials had “crept back into the system and ossified” and the overstretched NHS workforce was losing capacity for research. “The system needs a pretty serious revamp,” said Bell. “[The government] is not going to fix this by just turning the handle a bit harder.”
Official figures show just 52{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of trials in the NHS are running to schedule – a significant improvement in recent months but still some way from the target the Department of Health has set for 80{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} trials being delivered to time and target by June.
The department has directed funders to shut down any trials that have missed their target to start recruiting by more than 90 days, with one in 10 trials being monitored under its Reset Research programme set to close prematurely. Five hundred trials have been closed under the initiative since May last year.
Other senior clinicians also raised concerns. Prof James Rowe, a senior dementia researcher at the University of Cambridge and consultant neurologist, said the UK’s lengthy approvals process could leave clinicians and their patients frozen out of international multicentre trials.
“If it’s going to take you 12 months to get started in the UK, by the time you get the green light the trial is effectively closing for recruitment internationally. It could be futile to begin the work to set up,” he said.
“It’s a great pity as there’s fantastic progress in the dementia world. There are 300 clinical trials for dementia worldwide. The UK should be at the forefront of this, not putting up barriers.”
Prof Paul Stewart, the vice-president (clinical) of the Academy of Medical Sciences and of the University of Leeds, said research tended to be viewed as a luxury rather than an integral part of the NHS’s mission.
“As I reflect on my 40-year career in the NHS, there have always been challenges, but now the crisis has come to a head in terms of a research capacity issue. The current environment is extremely challenging,” he said.
Dr Ian Walker, of Cancer Research UK, said the pandemic continued to “cast a long shadow” over clinical research. “As backlogs for diagnosis and treatment grow, NHS staff face more pressures and protecting time for research is increasingly difficult,” he said. “If this pattern continues, it means slower progress towards brand new treatments for cancer.”
George Freeman, the minister at the Department for Science, Innovation and Technology, said: “Commercial clinical trials are absolutely vital to both our UK life sciences sector and widening NHS patient access to innovative medicines all across the UK. The UK has traditionally been a strong global location for trials, as demonstrated most recently through the groundbreaking Covid recovery trial which was set up in record time and was the world’s largest randomised controlled trial for Covid-19.
“However, our life sciences sector has reported a 44{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} fall in recruitment of patients to commercial clinical trials between 2017 and 2021 – so it is vital that we act to rebuild competitiveness.”
The sanctity of the doctor-patient marriage is the cornerstone of the healthcare career. This guarded space is steeped in custom – the Hippocratic oath, healthcare ethics, professional codes of carry out and legislation. But all of these are poised for disruption by digitisation, rising technologies and “artificial” intelligence (AI).
Innovation, robotics, digital technological innovation and improved diagnostics, prevention and therapeutics can alter healthcare for the far better. They also increase ethical, authorized and social problems.
Considering that the floodgates were opened on ChatGPT (Generative Pertaining Transformer) in 2022, bioethicists like us have been considering the part this new “chatbot” could play in healthcare and health analysis.
Chat GPT is a language product that has been qualified on massive volumes of world-wide-web texts. It attempts to imitate human text and can execute numerous roles in health care and well being investigate.
Early adopters have started off applying ChatGPT to guide with mundane tasks like crafting sick certificates, patient letters and letters asking medical insurers to pay out for particular costly prescription drugs for people. In other words and phrases, it is like obtaining a high-level own assistant to pace up bureaucratic duties and raise time for client interaction.
But it could also guide in a lot more really serious health-related routines such as triage (deciding on which individuals can get accessibility to kidney dialysis or intensive treatment beds), which is significant in options where methods are minimal. And it could be utilised to enrol individuals in scientific trials.
Incorporating this advanced chatbot in affected person care and clinical investigation raises a selection of moral problems. Using it could guide to unintended and unwelcome penalties. These fears relate to confidentiality, consent, excellent of treatment, trustworthiness and inequity.
It is way too early to know all the ethical implications of the adoption of ChatGPT in health care and investigate. The additional this engineering is utilized, the clearer the implications will get. But thoughts relating to potential threats and governance of ChatGPT in drugs will inevitably be aspect of long run discussions, and we concentrate on these briefly below.
Potential ethical risks
Initial of all, use of ChatGPT operates the risk of committing privateness breaches. Productive and economical AI depends on device discovering. This needs that knowledge are continuously fed again into the neural networks of chatbots. If identifiable patient facts is fed into ChatGPT, it types part of the data that the chatbot employs in long run. In other words, delicate data is “out there” and susceptible to disclosure to third get-togethers. The extent to which these types of info can be safeguarded is not very clear.
Confidentiality of affected person details forms the basis of believe in in the health care provider-patient romance. ChatGPT threatens this privateness – a hazard that vulnerable people may perhaps not completely fully grasp. Consent to AI assisted health care could be suboptimal. People could possibly not realize what they are consenting to. Some may possibly not even be requested for consent. As a result professional medical practitioners and institutions might expose them selves to litigation.
A further bioethics issue relates to the provision of large top quality healthcare. This is historically based on robust scientific proof. Employing ChatGPT to make proof has the prospective to accelerate analysis and scientific publications. On the other hand, ChatGPT in its present-day format is static – there is an stop date to its databases. It does not supply the most recent references in serious time. At this stage, “human” scientists are accomplishing a much more precise position of producing proof. Extra stressing are stories that it fabricates references, compromising the integrity of the evidence-primarily based strategy to excellent healthcare. Inaccurate information and facts could compromise the basic safety of healthcare.
Superior high quality proof is the foundation of professional medical treatment method and professional medical suggestions. In the era of democratised healthcare, vendors and individuals use various platforms to accessibility info that guides their conclusion-producing. But ChatGPT may well not be sufficiently resourced or configured at this point in its enhancement to deliver accurate and impartial data.
Technological innovation that uses biased details dependent on beneath-represented details from persons of colour, women and little ones is hazardous. Inaccurate readings from some makes of pulse oximeters made use of to measure oxygen concentrations in the course of the new COVID-19 pandemic taught us this.
It is also truly worth thinking about what ChatGPT could imply for minimal- and middle-earnings countries. The concern of obtain is the most clear. The rewards and hazards of rising systems have a tendency to be unevenly dispersed concerning countries.
At present, accessibility to ChatGPT is absolutely free, but this will not previous. Monetised obtain to highly developed versions of this language chatbot is a likely danger to source-weak environments. It could entrench the electronic divide and worldwide health and fitness inequalities.
Governance of AI
Unequal access, likely for exploitation and doable hurt-by-info underlines the importance of obtaining certain rules to govern the overall health takes advantage of of ChatGPT in minimal- and middle-profits international locations.
International suggestions are rising to make certain governance in AI. But a lot of low- and center-money nations around the world are but to adapt and contextualise these frameworks. On top of that, many nations around the world absence legal guidelines that apply especially to AI.
The world wide south requirements locally relevant conversations about the ethical and authorized implications of adopting this new technologies to make sure that its benefits are liked and rather dispersed.
MANHASSET, N.Y., February 24, 2023–(Business enterprise WIRE)–Beginning in the brain and extending to our organs, the vagus nerve aids talk and manage how the entire body functions, including heart level, respiration and immune reaction. For the initially time, scientists at The Feinstein Institutes for Professional medical Investigation are microscopically mapping a lot more than 100,000 person fibers that make up the vagus nerve to ascertain how they are anatomically connected and which bodily perform it controls. Bioelectronic medication scientists posted their early mapping in the journal Mind Stimulation, together with a novel vagus nerve stimulator that can activate qualified fibers, opening up new avenues of vagus nerve stimulation (VNS) investigate.
Stavros Zanos, MD, PhD, is senior creator on the exploration, which published in the journal Brain Stimulation. (Credit score: Feinstein Institutes)
The research, led by Stavros Zanos, MD, PhD, associate professor at the Feinstein Institutes’ Institute of Bioelectronic Medication, deployed highly developed solutions for surgical dissection, imaging and microscopic anatomy to map how vagal fibers are organized within the vagus nerve in animal styles. The workforce identified fibers that hook up to the larynx, lung and heart lie in diverse elements of the nerve. They also found that sensory and motor fibers are in separate locations, which are shut to the neck and later disappear as the nerve enters the upper body cavity.
“To progress the subject of bioelectronic medication and efficiency of vagus nerve stimulation therapies, we will have to very first recognize what section of the nerve we are stimulating and what that does to the body,” claimed Dr. Zanos, senior writer of the paper. “By way of our early mapping and new electrical stimulation vagal nerve cuff, we hope to unlock the probable of VNS to treat more successfully organ-distinct ailments.”
The team’s animal model VNS cuff wraps close to the vagus nerve and has 10 contacts as a substitute of the regular two contacts utilized currently in scientific VNS gadgets. By electrically stimulating particular person contacts about the nerve, the group showed that nerve fibers can be extra selectively activated. For instance, by stimulating the get hold of that lies away from nerve fibers to the larynx and nearer to nerve fibers to the lung, they were in a position to affect lung perform with a lesser affect on laryngeal functionality.
The cuff’s efficiency exhibits the capability to hone in and pick fibers to a one organ of interest whilst averting other people. Current VNS therapies are unable to very easily concentrate on the nerves that engage a specific organ (i.e. the heart in atrial fibrillation or the lungs in pulmonary hypertension). Regularly, present VNS therapies generate aspect effects from non-specific organs, like voice improvements, throat agony and coughing. Even although all those consequences are not lifetime-threatening, a more selective, focused solution to VNS could probably lessen those facet outcomes and use VNS to handle organ-certain ailments improved.
“Irrespective of the relevance of the vagus nerve and extensive fascination in methods to stimulate it, the basic anatomy of this nerve is mainly unidentified,” claimed Kevin J. Tracey, MD, president and CEO of the Feinstein Institutes and Karches Loved ones Distinguished Chair in Health-related Analysis. “Dr. Zanos’ existing study presents a new basic foundation for comprehending vagus nerve operate and composition.”
The Feinstein Institutes for Professional medical Analysis is the world-wide scientific dwelling of bioelectronic medicine, which brings together molecular medication, neuroscience and biomedical engineering. At the Feinstein Institutes, health-related researchers use contemporary know-how to produce new system-based therapies to address condition and injuries.
Constructed on yrs of investigate in molecular mechanisms of disease and the backlink between the anxious and immune systems, our scientists uncover neural targets that can be activated or inhibited with neuromodulation products, like vagus nerve implants, to management the body’s immune response and inflammation. If inflammation is effectively managed, health conditions – such as arthritis, pulmonary hypertension, Crohn’s disorder, inflammatory bowel diseases, diabetic issues, most cancers and autoimmune disorders – can be taken care of extra properly. Past swelling, utilizing novel brain-laptop interfaces, our researchers formulated approaches to bypass injuries of the nervous technique so that individuals living with paralysis can get back sensation and use their limbs. By creating bioelectronic medication expertise, disease and harm could a single working day be handled with our individual nerves with no pricey and potentially unsafe pharmaceuticals.
About the Feinstein Institutes
The Feinstein Institutes for Health-related Analysisis the house of the investigation institutes of Northwell Well being, the most significant health care company and non-public employer in New York State. Encompassing 50 analysis labs, 3,000 scientific study scientific studies and 5,000 scientists and personnel, the Feinstein Institutes raises the standard of health-related innovation by means of its 5 institutes of behavioral science, bioelectronic medicine, cancer, overall health procedure science, and molecular medicine. We make breakthroughs in genetics, oncology, mind investigate, psychological wellbeing, autoimmunity, and are the world wide scientific leader in bioelectronic medication – a new area of science that has the potential to revolutionize drugs. For additional information and facts about how we develop knowledge to cure condition, check outhttp://feinstein.northwell.eduand abide by us onLinkedIn.
IN 2011 BEN MOL, a professor of obstetrics and gynaecology at Monash University, in Melbourne, came across a retraction notice for a study on uterine fibroids and infertility published by a researcher in Egypt. The journal which had published it was retracting it because it contained identical numbers to those in an earlier Spanish study—except that that one had been on uterine polyps. The author, it turned out, had simply copied parts of the polyp paper and changed the disease.
“From that moment I was alert,” says Dr Mol. And his alertness was not merely as a reader of published papers. He was also, at the time, an editor of the European Journal of Obstetrics and Gynaecology, and frequently also a peer reviewer for papers submitted to other journals. Sure enough, two papers containing apparently fabricated data soon landed on his desk. He rejected them. But, a year later, he came across them again, except with the fishy data changed, published in another journal.
Since then, he has teamed up with other researchers to investigate groups of papers by authors he has spotted as data fabricators. Wherever he saw smoke, he found fire. There were tables on patients’ characteristics that contained only even numbers. There were values that were clinically unlikely. There was an implausible 40:60 sex ratio of babies when the mothers-to-be had, purportedly, been selected at random. Eye-popping speeds of completing clinical trials were common.
The fabrication of unreality
Dr Mol and his colleagues have sent their concerns about more than 750 papers to the journals that published them. But, all too often, either nothing seems to happen or investigations take years. Only 80 of the studies they have flagged have so far been retracted. Worse, many have been included in systematic reviews—the sort of research round-ups that inform clinical practice.
Millions of patients may, as a consequence, be receiving wrong treatments. One example concerns steroid injections given to women undergoing elective Caesarean sections to deliver their babies. These injections are intended to prevent breathing problems in newborns. There is a worry that they might cause damage to a baby’s brain, but the practice was supported by a review, published in 2018, by Cochrane, a charity for the promotion of evidence-based medicine. However, when Dr Mol and his colleagues looked at this review, they found it included three studies that they had noted as unreliable. A revised review, published in 2021, which excluded these three, found the benefits of the drugs for such cases to be uncertain.
Partly or entirely fabricated papers are being found in ever-larger numbers, thanks to sleuths like Dr Mol. Retraction Watch, an online database, lists nearly 19,000 papers on biomedical-science topics that have been retracted (see chart 1). In 2022 there were about 2,600 retractions in this area—more than twice the number in 2018. Some were the results of honest mistakes, but misconduct of one sort or another is involved in the vast majority of them (see chart 2).
John Carlisle, a British anaesthetist and journal editor, has uncovered hundreds of problematic papers. He reckons “almost all [clinical] guidelines will be affected in some way by false data that is currently unrecognised”. Fabricated studies also send those who try to build on them down blind alleys, wasting millions of dollars.
Yet journals can take years to retract, if they ever do so. Going by these numbers, roughly one in 1,000 papers gets retracted. That does not sound too bad. However, Ivan Oransky, one of Retraction Watch’s founders, reckons, based on various studies of the matter and reports from sleuths, that something more like one in 50 papers has results which are unreliable because of fabrication, plagiarism or serious errors.
Most fabricated papers come from one of two sources. Some, particularly those claiming to report clinical trials, are the products of prolific individual fraudsters or groups of fraudsters. Those uncovered by Dr Mol fall into this category. Others, more often purporting to be about basic science, such as molecular biology, are written, for a fee, by outfits known as “paper mills”. Frequently, these are fabricated by copying published papers and substituting the gene or disease a legitimate paper refers to with another.
According to the Retraction Watch database, the 200 authors with the most retractions account for over a quarter of all 19,000 retractions. Many of the most prolific fraudsters are senior scientists at big universities or hospitals. Few have spoken openly about their motives for making up research. But the confessions of those who have speak volumes about what may push others down the same path.
Cheats ever prosper
Scientific research is a hard slog, and the results are often disappointingly equivocal answers to a researcher’s bold hypothesis. Diederik Stapel, once a psychology professor at Tilburg University in the Netherlands, had 58 papers retracted after revelations that he fabricated studies. He did so, he said in his confessional memoir, “Faking Science”, because they otherwise failed to provide a solution that was “simple, clear, beautiful and elegant”. Like many similar fabulists, however, he was also driven by career incentives. The aphorism “publish or perish” reflects an academic truth. A long publication list is crucial for promotion, or for switching institutions to get a better job. But journals prefer studies that show strong, positive results—meaning much of a researcher’s effort is, in terms of career advancement, wasted.
Publishing lots of studies has enabled some fraudsters to be perceived as leading experts in their fields, with the perks of professional prestige which go with that—at least until things unravel. As Dorothy Bishop, a retired experimental psychologist from Oxford University who volunteers her time identifying problematic studies observes, such fraudsters often run research groups or have collaborative networks with other research centres. When the fabrication is discovered, those colleagues are affected by the aftermath. “Quite often”, she says, “junior people get their careers completely derailed by this.”
It is a particular problem in China. Unrealistic publication quotas are often needed to obtain the best jobs in hospitals, and those who publish in top journals also get big cash bonuses. Not surprisingly, China is thus a country that has developed a thriving paper-mill industry. Indeed, almost all retractions linked to paper mills list Chinese authors. Of papers submitted to journals, about a fifth have at least one contributor from a Chinese institution, yet this fifth accounts for nearly half of papers subsequently retracted.
A review of submissions to two journals specifically aimed at by paper mills does, however, show that the problem stretches way beyond China. It found that the fakes had authors from more than 70 countries. And, though those from middle income countries (China included, see chart 3) are the most numerous, some of the most consequential fabrications of clinical trials which have come to light were concocted in America, Canada, Europe and Japan.
How much cheating is never caught is anyone’s guess. As Dr Bishop notes, “The only ones we know about are the ones that are not very good at it. If somebody is very good at fraud, you’re not going to detect it.” And it is not just a few bad apples. In 2009 PLOS ONE published a round-up of 18 surveys of scientists, mostly in America, that had asked about fraud. Though only 2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of respondents admitted falsifying data themselves, 14{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} said they knew someone who had. Similarly, a third of those asked confessed to other questionable research practices, such as dropping inconvenient data points based on “gut feeling”, or making important changes to a study’s protocol while it was in progress. But they pointed the finger at 72{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of their colleagues.
America is not exceptional in this. In a survey of academics in Britain, published in 2016, nearly one in five reported having fabricated data. And in a recent survey of researchers in the Netherlands, 10{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of those in the life and medical sciences admitted they had falsified or fabricated data.
Many fake papers are me-too studies, supporting treatments already backed by other work. For the most part, these are unlikely to sway clinical practice. But some fraudsters have been the inspiration for specific medical interventions which have turned out to be useless, or even harmful.
For example, critically ill patients undergoing surgery were once sometimes given starch infusions to boost their blood pressure. This was based in part on seven now discredited studies by Joachim Boldt, a German anaesthesiologist. A revised round-up of the evidence published in the Journal of the American Medical Association, in 2013, after his fabrications were discovered, concluded that giving starch infusions in these circumstances caused kidney damage and sometimes killed people.
Likewise, for more than a decade cardiac patients in Europe were given beta-blockers before surgery, with the intention of reducing heart attacks and strokes—a practice that rested on a study from 2009 which was eventually determined to have been based, at least in part, on fabricated data. By one estimate, this approach may have caused 10,000 deaths a year in Britain alone. And a systematic review showing that infusion of a high-dose sugar solution reduces mortality after head injury was retracted after an investigation failed to find evidence that any of the trials included in it, which were all ascribed to the same researcher, had actually taken place.
Bricks without straw
Spotting fabricated papers often starts with catching one by chance and then looking at others by the same hand, as Dr Mol did. “A lot of the problems are only apparent when you look across publications by an author. So if you had one paper, you wouldn’t necessarily identify them,” says Alison Avenell of the University of Aberdeen, who is part of a team that has raised concerns about hundreds of clinical trials published by several research groups. Common patterns in dodgy papers, she opines, include unusually big effects of the reported treatments, peculiar drop-out rates among participants, or the same data appearing in different trial reports. “You see things that are virtually statistically impossible,” she says.
Dr Carlisle and others have devised various statistical checks to catch unusual numbers in single papers. As an editor of Anaesthesia, he used such checks on all 526 clinical-trial studies submitted to the journal between 2017 and 2020. When he looked at papers for which the authors had not submitted individual patients’ underlying numbers, he found that 2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} included false data. This jumped to 44{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} for those for which he could also examine such individual numbers, including 26{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} which he judged as “fatally flawed”.
Doing checks like these routinely could stop a lot of fake papers being published. Yet, though reviewers who vet journal papers for publication “get all of these supplemental files and links to data sets”, says Lisa Bero, of Cochrane, “most of them don’t look at it.” Moreover, though authors often say that the backup data for their papers will be made available on request, a study conducted in 2022 reported that 93{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} fail to provide them when so requested by other researchers. “You ask for the original data and then, my goodness, you realise we live in a dangerous world,” says Ian Roberts of the London School of Hygiene and Tropical Medicine. Floods, earthquakes, termites, stolen laptops—he has seen all sorts of excuses for lost data.
Blots on the landscape
Cochrane maintains a database of retracted studies, and its systematic reviews are revised as needed. But that is rare for these types of reviews, partly because retracted papers are often not flagged prominently as such in online libraries and so continue to be cited as if they were valid research. Indifference plays a role too, with many researchers reluctant to set things straight even when told their reviews included fabricated studies. The attitude is, “it was right at the time”, says Jack Wilkinson, a biostatistician at Manchester University.
For example, Dr Avenell and her colleagues assessed the impact of 27 retracted clinical-trial papers, covering several medical conditions. These papers were included in 88 systematic reviews and clinical guidelines. The researchers reckoned that in half of those the conclusions were likely to change if the retracted trials were removed. They notified the authors of all the reviews about the retractions. Only half of them bothered to reply. A year later, in 39 of the 44 reviews that would have been affected, no action was undertaken.
Similarly depressing discoveries have been made in recent years for paper-mill articles. Though lots of these are so sloppy that any serious researcher would consider them a joke, and they are thus often published in obscure periodicals which would print anything for a fee, some look solid enough to be accepted by leading scientific journals. These are now discovering they have published hundreds of them. One analysis of 53,000 papers submitted to journals in a variety of disciplines, spanning six publishers, flagged between 2{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} and 46{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of them as suspicious.
Molecular-biology articles, those paper-mill specialities, often include pictures of Western blots—a laboratory technique used to study proteins. Such images can be found, for example, in papers that investigate how a given drug affects human cells. No two Western blots should look the same, so a sharp pair of eyes can spot duplicates. Elisabeth Bik, a Dutch microbiologist turned full-time detective hunting for fabricated papers, has an exceptional talent for doing just that. Using her “pattern-matching eyes and lots of caffeine”, as she put it in a recent opinion piece, she has analysed more than 100,000 papers, and found blot-based evidence of error or cheating in 6,500 of them.
Studies with falsified Western blots may seem less consequential than fabricated clinical trials. But consider a recent controversy concerning a series of influential papers on the causes of Alzheimer’s disease of which the lead author is Sylvain Lesné of the University of Minnesota (which is investigating the matter).
Dr Bik and others have recently found what they say is evidence of image-manipulation, including of pictures of blots, in these studies. And other scientists have tried and failed to replicate the results of a landmark study Dr Lesné published in Nature in 2006, which appeared to provide crucial evidence concerning a hypothesis that links the disease with so-called amyloid plaques in the brain, and which is one of the most cited papers in Alzheimer’s research. This particular article may have sent an entire line of scientific inquiry into that hypothesis in the wrong direction, by pointing a finger at one particular form of amyloid beta, the plaque-forming protein. In July 2022 Nature published an expression of concern, while it investigates.
Similar patterns are emerging in genetics. In a study published last year Jennifer Byrne, a cancer researcher at the University of Sydney, led a team that screened nearly 12,000 papers using Seek & Blastn, a piece of software they developed themselves, to check details of substances called nucleotide-sequence reagents (NSRs).
NSRs are short pieces of DNA or RNA that form part of many studies of genes. They are intended to bind to specific bits of natural genetic material. Seek & Blastn extracts the sequences of these reagents from papers and compares them with those in Blastn, a public sequence database, to check whether they match their supposed genetic targets. The team found that 6{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of papers contained errors suggestive of paper-mill production.
The consequences of fake genetic studies such as these could be as far-reaching as those involving dodgy Western blots. Dr Byrne and her co-authors estimate that as many as 100,000 published papers about human genes may emanate from paper mills, and that a quarter of these are such that they “may misinform the future development of human therapies”.
Disciplining the discipline
It is often asserted that science is self-correcting. And it is true that, if a claimed result is important enough, an inability to replicate it or of subsequent work to conform to it will eventually be noticed. In the short term, though, it is easy to hide in the shadows. Even co-authors of a data-fabricating scientist—those, in other words, who are closest to him or her—may not notice what the culprit is up to. In complex studies of a particular disease, several types of researchers will be involved, who are, by definition, not experts in each other’s fields. As Dr Bishop observes, “You just tend to take on trust the bits of data that somebody else has given you.”
Moreover, even after a published paper is flagged as containing fabricated data, self-correction often fails to kick in. There is a “massive variation” in how journals and publishers react when alerted to problems, says Dr Wilkinson—whether they investigate at all, how long it takes to reach a decision, and what they do after that.
Dr Avenell avers that in her experience it usually takes two to three years to get an expression of concern or a retraction published. “The only way we get retractions is to repeatedly badger the journals over and over and over again”, she says. “If you just send them a one-off email with details of all of your concerns, it’s very unlikely that anybody is ever going to do anything.” Dr Bero says that many Cochrane reviewers think it a waste of time to alert journal editors about problematic studies they have identified, so they don’t bother. “Many of our authors have written to editors and just gotten no response, or the editor doesn’t do anything to retract the article or doesn’t investigate at all,” she observes.
One problem is that journals rarely have staff, such as statisticians, with the expertise needed to deal with such matters. Publishers, for their part, make profits from publishing more, not from investigating potential retractions. They also fear being sued by belligerent fraudsters. They therefore often pass the ball to the institutions that employ the suspected miscreants.
In America, institutions accepting federal grant money (which is almost all of the serious ones) are required to follow government rules which say that they should investigate allegations of research misconduct within 60 days. But many take more than a year or two, says C.K. Gunsalus, an ethicist at the University of Illinois, who has conducted such investigations.
Just do it
In some cases, there are good reasons for delay. The difficulty of finding experts competent to conduct complex analyses is one. Another is that an investigation of one paper may turn up further suspicious publications. All too often, though, “there is very little sense of urgency”, says Dr Gunsalus. The goal is to decide whether a researcher should be fired, rather than a desire to protect the integrity of the scientific literature. Until an employment decision is made, the university usually stays mum.
Even in America, the quality of such investigations often leaves a lot to be desired, says Dr Gunsalus. And many places have no relevant regulations. In Western countries people fired for research misconduct have sometimes gone on to do the same thing elsewhere, says Dr Bishop. And in their list of concerns with 172 papers published by a group led by Zatolleh Asemi at the Kashan University of Medical Sciences, in Iran, Andrew Grey of the University of Auckland, in New Zealand, and his colleagues note that five of the seven vice-chancellors at his university are co-authors of at least one affected submission.
Nor do universities provide incentives for whistle-blowers to act, though that can stop fabricated studies being produced in the first place. Their rules usually say lots about the consequences of spurious allegations, but little or nothing about any duty to raise the alarm about fraud.
Few whistle-blowers have Dr Bik’s perseverance. After she raised concerns about more than 60 papers by Didier Raoult, a now-retired professor at a university hospital in Marseille, she received online threats and her home address was posted on Twitter by one of his colleagues. Dr Raoult also filed a legal complaint against her for attempted blackmail and harassment, an action the French National Centre for Scientific Research, a government agency, condemned as “judicialisation of scientific controversy and criticism”. In 2021 she won the John Maddox prize—awarded jointly by Sense about Science, a British charity, and Nature, of which Maddox was, for many years, editor—for “courage and integrity in standing up for sound science and evidence”.
There are some signs of hope. Besides scanning retraction databases for new additions, and redoing the analyses that include them, Cochrane has also started to check papers for integrity. A recent Cochrane review of research on drugs intended to prevent pre-term labour excluded 44 studies on such grounds, which was one in four of those on the starting list.
In a similar vein, Britain’s National Institute of Health and Care Research pays for INSPECT-SR, a project run by Dr Wilkinson that is developing integrity-checking tools for systematic reviews like those conducted by Cochrane. STM, a publishing-industry association, is working on a similar system to detect fabrications in submitted papers. The idea, says Joris van Rossum, who leads this work, is that the system will give editors signals about suspicious features commonly used by paper mills, such as duplicated images, the same paper being submitted simultaneously to several journals, authors with no record of having expertise in the subject, and so on.
Both Dr Wilkinson and Dr van Rossum worry about an arms race between fabricators and those employed to catch them. Such fears are amplified by the growing sophistication of artificial-intelligence (AI) tools like ChatGPT. In a recent study for which this was asked to generate 50 medical-research abstracts, both human reviewers and an AI-output detector failed to identify a third of the bot’s papers as such.
Trust. But verify
In the end, however, keeping fakes out of the scientific record depends on the willingness of publishers to stump up more resources. Statistical checks of clinical-trial papers often involve laborious manual work, such as typing up specific data in spreadsheets. This would require journals to hire dedicated staff, cutting into profits.
Many academics who have spent years trying to get fabricated papers retracted are pessimistic that better ways to detect fraud will, alone, make a big difference. Dr Roberts and Dr Mol want journals to be regulated in the way that social media and the news business are in some countries, with standards on what they publish. Peter Wilmshurst, a British cardiologist who has raised the alarm about numerous cases of research misconduct in his field, thinks there should be criminal penalties for those who fabricate data. Dr Gunsalus wants universities to make public the reports from their research-fraud investigations. And everyone agrees that publish or perish is a recipe for disaster.
None of these solutions will be quick or straightforward. But it is now clear that choosing to look the other way is causing palpable harm to patients. As Stuart Richie of King’s College, London, notes in his book, “Science Fictions”: “For the sake of the science, it might be time for scientists to start trusting each other a little less.” ■
YANGZHOU, China, Feb. 21, 2023 /PRNewswire/ — Meihua International Medical Technologies Co., Ltd. (“MHUA” or the “Company”) (NASDAQ: MHUA), a reputable manufacturer and provider of Class I, II and III disposable medical devices with operating subsidiaries in China, today announced the Company, via its subsidiary company Hainan Guoxie Medical Technology Co. (“Hainan Guoxie”), has entered into cooperation agreement (the “Qionghai Agreement”) with Qionghai City of Hainan Province to build technology park project. Hainan Guoxie also entered into cooperation agreement (the “Hope City Agreement”) with Hainan Free Trade Port Boao Hope City (“Hope City”) to build MHUA a medical research and development center in the Hope City.
Pursuant to the Qionghai Agreement, Hainan Guoxie plans to invest in the construction of a medical industrial park in Hainan Province for the will be focused on the development of minimally invasive interventional medical devices, new materials and surgical robotics technologies. Hainan Guoxie and Qionghai City government reached preliminary agreement to bid for the usage of nearly 574,080 sq ft of land around Hope City for the construction of a Contract Development and Manufacturing Organization (CDMO) medical industrial park. The Company anticipates making a more detailed public announcement of the land use right purchase information in about one month’s time.
Pursuant to the Hope City Agreement, the planned MHUA medical R&D center will carry out the research and development of stem cell to human targeted therapies and rehabilitation training projects.
Presently, Hope City is the only special medical parkin China, which was approved by China State Council in 2013 and offers a series of special policies such as “licensed medical treatment, licensed research, licensed operation and licensed international medical technology exchange,” and is a key project for the construction of the Hainan Free Trade Port. At present, there are 20 medical institutions involved in more than 10 projects under construction or planned in the pipeline, with 51 medical academicians forming the expert advisory team. In addition, Hope City has established cooperation with 30 of the top international pharmaceutical and medical devices enterprises, serving as one of the main channels for the importation of innovative products into China. The volume of licensed medicines and medical devices imported has exceeded 200 categories, effectively facilitating the advancement of medical technology, devices and medicine development in China to catch up with the international market.
MHUA’s project is highly valued by the local government of Hope City, who recently paid a special visit to the Company’s headquarters. Mr. Liu Yongjun, chairman of MHUA, commented: “Hainan has many advantageous conditions as China’s national free trade port, which will provide many convenience for MHUA’s products exporting to foreign markets, new product research and development, and taxation, among other things. It is a great honor for us that Qionghai City and Hope City selected the Company as one of the contracted companies to promote medical industry projects locally. MHUA will strive to improve the level of intelligence, information technology, digitalization and innovation, and accelerate the transformation and upgrade of our business, in order to promote the Company’s high-quality development and create sustainable value for our shareholders.”
About Meihua International Medical Technologies Co., Ltd.
Meihua International Medical Technologies is a reputable manufacturer and provider of Class I, II and III disposable medical devices with operating subsidiaries in China. The Company manufactures and sells Class I disposable medical devices, such as eye drop bottles, medicine bottles and anal bags, and Class II and III disposable medical devices, such as identification tape, gynecological examination kits, inspection kits, surgical kits, medical brushes, medical dressing, masks, disposable infusion pumps, electronic pumps and puncture kits, which products are sold under its own brands and also sourced and distributed from other manufacturers. The Company has received international “CE” certification and ISO 13485 system certification and has also registered with the FDA (registration number: 3006554788) for more than 20 products. The Company has served hospitals, pharmacies, medical institutions and medical equipment companies for over 30 years, providing more than 800 types of products for domestic sales, as well as 120 products which are exported to more than 30 countries internationally across Europe, North America, South America, Asia, Africa and Oceania. For more information, please visit www.meihuamed.com.
Forward-Looking Statements
This press release contains forward-looking statements as defined by the Private Securities Litigation Reform Act of 1995. Forward-looking statements include statements concerning plans, objectives, goals, strategies, future events or performance, and underlying assumptions and other statements that are other than statements of historical facts. When the Company uses words such as “may,” “will,” “intend,” “should,” “believe,” “expect,” “anticipate,” “project,” “estimate” or similar expressions that do not relate solely to historical matters, it is making forward-looking statements. Forward-looking statements are not guarantees of future performance and involve risks and uncertainties that may cause the actual results to differ materially from the Company’s expectations discussed in the forward-looking statements. These statements are subject to uncertainties and risks including, but not limited to, the following: the Company’s ability to achieve its goals and strategies, and its ability to fully execute on the planned agreement, the Company’s future business development and plans of future business development, including its ability to successfully develop robotic assisted surgery systems and obtain licensure and certification for such systems, financial conditions and results of operations, product and service demand and acceptance, reputation and brand, the impact of competition and pricing, changes in technology, government regulations, fluctuations in general economic and business conditions in China, and assumptions underlying or related to any of the foregoing and other risks contained in reports filed by the Company with the U.S. Securities and Exchange Commission (“SEC”). For these reasons, among others, investors are cautioned not to place undue reliance upon any forward-looking statements in this press release. Additional factors are discussed in the Company’s filings with the SEC, including under the section entitled “Risk Factors” in its annual report on Form 20-F, as filed with the SEC on July 29, 2022, as well as its current reports on Form 6-K and other filings, all of which are available for review at www.sec.gov. The Company undertakes no obligation to publicly revise these forward-looking statements to reflect events or circumstances that arise after the date hereof.
You may imagine that the hard part of being a Canadian scientist is having a bright idea. However, while curiosity, persistence and inventiveness are prerequisites for scientific success, the major obstacle to being a biomedical scientist in Canada is obtaining research funding.
Canadian biomedical scientists receive funding to hire scientific staff and buy experimental materials by applying for federally funded grants from the Canadian Institutes of Health Research (CIHR).
Securing CIHR grants has become impractically competitive. Most applications require multiple revisions and resubmissions, often imposing an interval of one to two years between first submission and funding. Since funding from a CIHR project grant only lasts five years, the life of the lab — and the jobs of Canadian scientists — are recurrently in jeopardy.
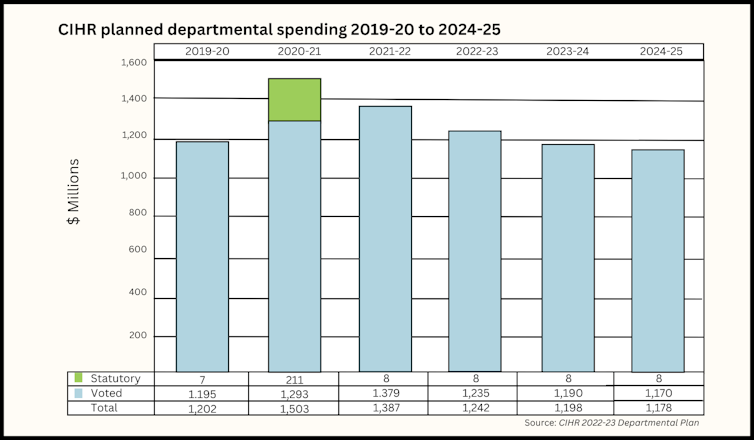
Graph of planned spending over time illustrates that CIHR funding is flat. (CIHR data)
The United States is a relevant comparator because it is home to many of the world’s leading scientists. Canadian scientists, if not funded, often relocate to the U.S. Compare America’s National Institutes of Health (NIH) 2020-21 budget of US$45 billion (roughly C$60 billion) to CIHR’s C$1.2 billion. America’s NIH budget is 50-fold that of Canada’s CIHR budget, but the U.S. population is only nine-fold greater than ours.
The success rate in CIHR grant competitions has declined from 31 per cent in 2005 to around 15 per cent in 2020.
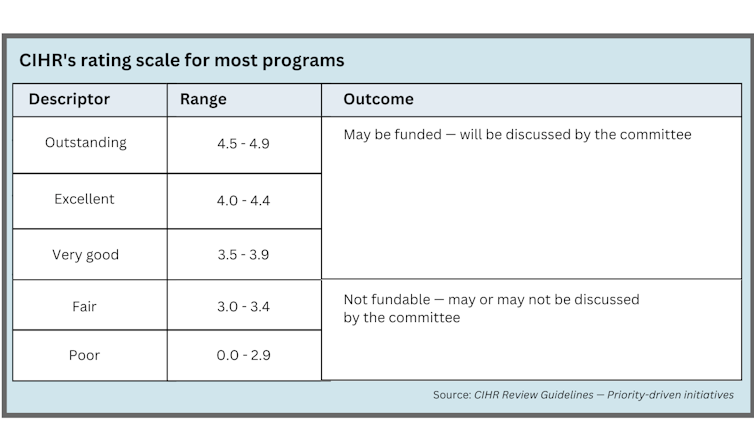
CIHR evaluates applications on a scale of zero to 4.9, corresponding to categories of poor, fair, very good, excellent and outstanding. Currently, CIHR grants are rarely funded unless the voted score is outstanding (rated 4.4 to 4.9). Usually only the top 18 per cent of all grants — fewer than one in five — are funded, and virtually all grants rated excellent are rejected.
This low-success endeavor is a demoralizing waste of time for the 82 per cent of scientists who are rejected and for the peer-review volunteers — unpaid colleagues who spent weeks reviewing the applications.
Almost all grants scored by CIHR as excellent go unfunded. (CIHR data)
Once funded, challenges remain. All CIHR awarded project grants are now subject to a 23.5 per cent across-the-board funding cut. This cut allowed CIHR to fund 87 additional grants per competition from 2018 to 2020, however the value of a five-year project grant shrank from $950,000 to $725,000.
These cuts mean scientific staff must take pay cuts or be terminated, and the approved research can only be partially completed.
Fixing funding
Canada needs to revitalize its scientific mojo and to do so must improve research funding. There are several steps that would improve science funding in Canada.
1. Implement the Fundamental Science Review recommendations
It noted that federal underfunding is exacerbated by CIHR’s practice of earmarking substantial portions of its limited funds to targeted proposals that address governmental priorities, rather than funding research and discovery science.
The report made simple recommendations to improve Canadian research: “Rapidly increase its investment in independent, investigator-led, research to redress the imbalance caused by differential investments favouring priority-driven, targeted research.”
Members of the author’s research team at the Archer laboratory at Queen’s University. (Author provided), Author provided
It also recommended “formation of an independent advisory committee on basic research and industrial innovation, comprised of leaders in research and industry” (not government employees). Our government currently makes many top-down science funding decisions without a strategic scientific plan or an external scientific committee to advise them. An independent advisory committee would reduce political interference in science.
The Naylor report’s recommendations have not been fully implemented, but would transform Canadian research. This would require commitment of an additional 0.4 per cent of the Government of Canada’s annual budget to our science sector.
2. Fund salaries for scientists who run infrastructure
In the meantime, CFI and CIHR could each implement “researcher-centric” changes.
CFI could accompany its infrastructure grants with funding for the scientists who are needed to operate these complex research platforms.
This makes it difficult to sustain a CFI scientific platform.
3. Bring back the foundation grant program
CIHR could resurrect its very successful foundation grant program.
Foundation grants allowed scientists to bundle all their research into a single, comprehensive application. (Shutterstock)
CIHR understood that its most successful scientists usually required two to three project grants, and recognized the time drag that acquiring multiple project grants required.
They responded in 2014 with the foundation grant program. Foundation grants allowed scientists to bundle all their research into a single, comprehensive application which offered more funding (equivalent to two to three project grants) for a longer duration (seven years instead of five years for project grants).
This allowed researchers to spend more time on doing science and less on writing and reviewing grants. My foundation grant gave me the stability and flexibility to simultaneously study oxygen sensing, mitochondrial dynamics and to develop drugs to treat pulmonary hypertension, cancer and COVID-19.
Read more:
How COVID-19 damages lungs: The virus attacks mitochondria, continuing an ancient battle that began in the primordial soup
Funding research pays off
Researchers are key to Canada’s capacity to create a high-tech economy, build the biomedical sector and seed entrepreneurial activity. Researchers also support our academic health sciences centres and universities, making them internationally competitive.
In addition to launching medical innovations, patents and spin-off companies, Canada’s researchers teach university students, and many CIHR-funded clinician-scientists provide patient care in our hospitals. In all of these ways, investment in research is critical to making Canada healthy, wealthy and wise.