Asia-Pacific Roundup: TGA seeks information from medical devices manufacturers at the point of care

Australia’s Therapeutic Goods Administration (TGA) is accumulating comments on the regulatory needs of internet sites that manufacture professional medical products at the point of treatment. The consultation is section of TGA’s endeavours to have an understanding of how the framework for tailor made-manufactured devices applies to position-of-treatment system output.
 
In 2021, the Australian govt introduced a framework supposed to apply an “appropriate” level of regulation to individualized, personalized-produced gadgets. The regulatory framework changed the definition of personalized-made professional medical gadget and, in doing so, required the suppliers of most products and solutions that ended up formerly equipped under an exemption to add their gadgets to the Australian Sign up of Therapeutic Merchandise (ARTG). Products equipped in volumes of far more than five a 12 months need to be in the ARTG.
 
Now, TGA is operating to comprehend how the framework applies to production at the level of treatment and “what refinements could be created to ensure regulation is proper without introducing unnecessary load for stage-of-treatment amenities.” The initiative led TGA to post a survey aimed at producing hubs operated by a stage-of-care facility, companies based in a stage-of-treatment facility and academic sites.
 
1 query asks respondents what would help them, and their facility, fulfill their regulatory obligations for medical units. The company also questioned companies exactly where they assume to be equipped to uncover facts about their regulatory obligations, these kinds of as from the administration who runs their facility and TGA, and posed various concerns about the respondents’ companies.
 
TGA released the session along with three associated surveys aimed at allied healthcare professionals, dental and oral wellbeing specialists and hospital and health care amenities. Each individual survey is supposed to present TGA with info about how to refine the custom made-made health-related unit regulations to avoid avoidable burdens. The surveys are tailored to the unique sets of stakeholders involved in the level-of-treatment generation of healthcare products.
 
TGA is accepting responses to all the surveys right until 7 May well. The regulator has clarified that the information provided will only be utilized to advise refinements to the regulatory framework and will not be used for compliance things to do.
 
TGA Survey
 
Philippine Food and drug administration again delays implementation of new guidelines to keep away from disruption to health care gadget market
 
The Philippine Food and Drug Administration (Food and drug administration) has delayed the implementation of new policies on the registration of medical devices for a next time owing to the threat that the “strict implementation” of the specifications would disrupt the offer of units and shipping of care.
 
In August 2021, Fda gave suppliers, importers and other stakeholders that manage Class B, C and D professional medical products right until 31 March 2023 to acquire a Certification of Clinical Product Notification (CMDN). Immediately after that day, Food and drug administration was to halt accepting CMDN filings and demand suppliers to protected a Certification of Health-related Gadget Registration (CMDR).
 
The first approach, unveiled in 2018, was to have to have Class B, C and D units to obtain a CMDR. The CMDN was for Class A units, the most affordable risk class less than the ASEAN Clinical Product Directive that handles the Philippines and other international locations in the area.
 
By April 2022, the company had rethought its proposal. Under the revised program, units that have been previously on the sector before 1 June 2022 could keep on to be sold without the need of a CMDN right up until 31 March 2023. From 1 April, manufacturers would at least require a pending CMDN submitting.
 
Times just before the deadline, Food and drug administration has rethought its proposal for a second time. The agency will now settle for CMDN programs for Class B, C and D healthcare products until finally 31 March 2024. Food and drug administration will halt accepting any CMDN filings for the 3 lessons of device soon after that date. From 1 April 2024, the agency will only accept CMDR submissions and all devices will need to have to be protected by at minimum a pending CMDN or CMDR submission. Companies will need to implement for a CMDR at minimum six months ahead of their CMDN expires.
 
Fda made the variations simply because “strict implementation” of the necessities would make “a danger that offer of healthcare units in the industry will be negatively influenced which could induce disruption in the wellbeing treatment company supply in the place.” The company “recognizes that there is a have to have to supply health-related gadget companies much more time to put together the technical documentary demands primarily based on the ASEAN frequent submission dossier template in implementing for CMDR.”
 
Food and drug administration Round
 
Indian Pharmacopoeia Commission releases draft on vaccine top quality manage
 
The Indian Pharmacopoeia Commission (IPC) has printed a draft standard chapter on vaccine excellent management that supplies assistance on employing in vitro procedures somewhat than in vivo tests for human and veterinary vaccines.
 
As IPC clarifies, in vivo potency and safety assays have historically performed a central purpose in safeguarding the high quality of vaccines. Having said that, “the inherent variability” of the assays can make them “less suited than properly made in vitro assays for monitoring regularity of output and for examining the probable affect of production improvements.”
 
When in vivo tests have minor or no benefit, IPC would like to get rid of them “given the ethical considerations and the obligations under the suitable conventions.” To aid that aim, the draft describes considerations for transitioning to in vitro tests.
 
The draft produced to the public options tracked adjustments, which include a section headed “General Feedback from Sanofi.” The comment claims the textual content “is pretty welcome in get to support established steering on substituting in vivo methods by different non animal-centered strategies which let to introduce more trusted assays to show product or service quality, efficacy and safety” but warns the draft contradicts its references in elements.
 
Draft Doc
 
TGA adjustments health-related product necessary ideas for nanomaterials to clarify present obligations
 
TGA has modified an crucial theory to explicitly demand manufacturers of healthcare devices to pay out certain attention to the chemical and bodily houses and biocompatibility of nanomaterials.
 
The obligation to spend attention to the homes already existed but the current critical principle provides additional depth to make clear the prerequisites. In a new subsection on nanomaterials, TGA wrote that health-related products should be designed and manufactured to lessen “risks associated with the dimension and the qualities of particles which are, or can be, launched into a patient’s or user’s body.”
 
Subsequent details condition that “particular notice will have to be given to the use of nanomaterials” and that the necessity “does not use to particles that appear into speak to with intact skin only.” TGA updated its vital ideas checklist for healthcare equipment in conjunction with the transform.
 
TGA Recognize

Manufacturers should work diligently to transition medical devices

The Secretary of the Department of Health and Human Services (HHS), Xavier Becerra, has extended the Public Health Emergency (PHE) for the twelfth time on January 11, 2023, as a consequence of the Coronavirus Disease 2019 (COVID-19) pandemic.[1] As a result, liability protections granted to medical device manufacturers by virtue of this declaration will continue for now. However, once this declaration is ended, medical device manufacturers who received such protections will need to consider what actions they will need to take in order to insure that their products can lawfully remain on the market. This article addresses the strategies and considerations medical device manufacturers should take in preparation for the termination of the COVID-19 pandemic and PHE to ensure a smooth transition of their devices on the market back to the pre-COVID-19 regulatory scheme.

Former HHS Secretary Alex Azar initially declared the PHE on January 31, 2020, nationwide, [2] pursuant to section 319 of the Public Health Service Act.[3] Termination of the PHE is determined upon the Secretary declaring that the emergency no longer exists, or upon the expiration of the 90-day period beginning on the date on which the determination is made by the Secretary, whichever occurs first.[4] The renewed PHE is effective through April 11, 2023, unless terminated by the Secretary sooner.  HHS has indicated it will give at least a 60-day notice of termination before the PHE ends.[5] This notice would need to occur between now and March 12, 2023.  Whether the PHE is renewed for the thirteenth time depends on a multitude of factors and COVID-19 circumstances, but many believe that the end of the pandemic may be in sight sometime this year. 

Once the PHE was declared, the U.S. Food and Drug Administration (FDA or “Agency”), to foster the development and availability of medical products that would assist in combating the pandemic, issued Emergency Use Authorizations (EUAs) to certain device manufacturers to encourage innovation and manufacturing of products that, among other things, would provide protection from and treatment for the COVID-19 virus. These EUAs allow manufacturers to market and distribute unapproved medical products, or allow an unapproved use of an approved medical product in certain situations. The EUAs, issued by the FDA pursuant to section 564(b) of the Federal Food, Drug, and Cosmetic Act (FD&C Act)[6] and ensuing guidances, altered the usual standards and enforcement policies to help expand the availability of medical products during the time of the PHE. Once the COVID-19 PHE comes to an end, however, the FDA will revert to its normal operations, whereby all stakeholders, including device manufacturers, healthcare facilities, healthcare providers, patients, and consumers will need to adjust from policies adopted and implemented during the declared COVID-19 PHE back to pre-PHE times. 

Emergency Use Authorization
Section 564 of the FD&C Act (21 U.S.C. 360bbb-3) authorizes the FDA to issue EUAs,[7] once the Secretary declares that an EUA declaration is appropriate.[8] Shortly after the initial declaration of the COVID-19 PHE, the Secretary of HHS also determined that “there is a public health emergency that has a significant potential to affect national security or the health and security of United States citizens living abroad,”[9] involving the virus that causes COVID-19, now known as SARS-CoV-2, thereby justifying the emergency use of medical devices and in vitro diagnostics for detection, diagnosis and/or treatment of SARS-CoV-2. Just in the year following the EUA declaration, the FDA reviewed over 2,300 EUA requests and issued more than 600 EUAs for medical countermeasures to combat COVID-19.[10]

Termination of an EUA declaration
Unlike the section 319 PHE declaration that expires if not extended, an EUA declaration under section 564 generally continues until the HHS Secretary terminates it. Thus, an EUA may remain in effect beyond the duration of the PHE. The HHS Secretary can terminate an EUA declaration on the earlier determination by the HHS Secretary that “the circumstances that precipitated the declaration have ceased (after consultation as appropriate with the Secretary of Homeland Security or the Secretary of Defense),” or “a change in the approval status of the product such that the authorized use(s) of the product are no longer unapproved (section 564(b)(2)),”[11] as in the case of an unapproved product distributed and used under an EUA that was subsequently approved by the FDA for the use allowed by the EUA. The Secretary shall provide advance notice that a declaration will be terminated and “the period of advance notice shall be a period reasonably determined”[12] to allow sufficient time for the disposition and transition of the unapproved product. The FDA has suggested the period of advance notice be 180 days before the day on which the EUA declaration is terminated.[13],[14]

Enforcement discretion
The FDA creates, implements and enforces its regulations, which are based on the laws set forth in the FD&C Act or other laws under which the Agency operates. These regulations have the full force of law. However, the FDA, as well as other government agencies, may choose to apply enforcement discretion as in the case where a medical product falls under the regulatory scheme of medical devices within its purview, but the FDA chooses not to enforce the requirements when the risk to patients is low.[15] Thus, while the legal obligations of the FDA in overseeing and regulating drugs and medical devices remain in effect technically, the Agency may issue enforcement policies to inform the public that it will not seek to enforce certain provisions of the statutes in enumerated situations under the COVID-19 PHE and EUA declarations.[16] During the COVID-19 PHE, the FDA issued a number of guidances outlining its enforcement policies concerning medical devices to address supply issues and ensure access to care, and to give health care providers the flexibilities needed to respond to COVID-19 and help keep people safer.[17],[18] For example, these guidances typically recite an enforcement policy indicating that the “FDA does not intend to object to modifications to the indications or design of FDA cleared or approved devices … without prior submission of a premarket notification or premarket approval application supplement where the modification does not create an undue risk in light of the public health emergency.”[19] The FDA applied enforcement discretion to numerous other medical devices such as ventilators, in vitro diagnostics, sterilizers, infusion pumps and digital health devices, among others.[20]

Transitioning medical devices
It is not clear when the COVID-19 PHE declaration or the EUA declaration may end, but as discussed above, the Secretary of HHS is required to provide advance notice of termination of the PHE[21] and EUA.[22] In preparation for transitioning medical devices back to pre-EUA normal operations, the FDA issued two draft guidances (“transition guidances”) directed at device manufacturers, healthcare facilities, healthcare providers, patients, consumers and FDA “to adjust from policies adopted and operations implemented during the declared COVID-19 [PHE] to normal operations.”[23],[24] The key features outlined in these transition guidances include:

  • The timeline for withdrawal of the enforcement policy guidances issued during the COVID-19 PHE and the advance notice of termination of each EUA issued during the EUA declaration
  • Manufacturer notice of intent to distribute its device after withdrawal of the enforcement guidances
  • Submissions of marketing applications prior to EUA termination date
  • Products continued to be marketed after EUA termination 

The FDA anticipates the final transition guidances will likely be issued early 2023. It is highly advised that manufacturers carefully consider strategies and options for transitioning their medical devices when the relevant EUAs and COVID-19-enforcement policies cease to be in effect. While these most likely will terminate at the same time, an EUA declaration under section 564 may remain in effect beyond the duration of the PHE.

Timeline
The FDA is proposing a 180-day transition period beginning on the “implementation date” and ending on the date enforcement guidances are withdrawn.[25] The FDA lists 17 enforcement policies that will be effected by the draft guidance.[26] The transition plan is a phased approach allowing manufacturers to become compliant with applicable statutory and regulatory requirements once the policies are no longer in effect and the more stringent requirements are reinstated. Manufacturers are still expected to comply with all statutory and regulatory requirements applicable to their devices, such as adverse event reporting requirements, during this period under 21 CFR Part 803, and submit reports consistent with FDA guidance,[27] and, if not already doing so, prepare marketing submissions if applicable. The FDA also proposes a similar timeline for termination of EUAs whereby advance notice of the “EUA termination date” will be published in the Federal Register 180 days before the EUA declaration is terminated.[28] Manufacturers also must continue to comply with the terms of the device’s EUAs as well as statutory and regulatory requirements applicable to their devices following the notice of the termination date. 

Notifications of intent and transition implementation plan
The FDA recommends medical device manufacturers notify the Agency whether or not they intend to submit a marketing application to continue distributing their devices after the termination date. It also encourages that communications with the Agency begin early and that the “Notifications of Intent” be submitted within 90 days following notice of termination. If a manufacturer does not intend to continue to distribute its device, it should follow 21 CFR Part 806 for the reporting requirements of any correction or removal of a medical device(s). The Agency does note that it will not object (i.e., apply its enforcement discretion) to the disposition of certain devices, such as single use and reusable non-life-supporting/non-life-sustaining devices that were distributed prior to the guidance withdrawal or EUA termination date. However for reusable devices, the device should be restored to the previously FDA-cleared or approved version of the device, or have publicly available labeling that accurately describes the product features and regulatory status (i.e., device lacks FDA clearance or approval). For life-supporting/life-sustaining devices, the FDA recommends devices should have both publicly available and a physical copy of the labeling.[29] In vitro diagnostic devices that remain distributed are to be used no more than two years after the EUA termination date or until the expiration date, whichever is less.[30]

For manufacturers planning to continue to distribute medical devices after the termination date, a marketing application should be submitted to the FDA allowing sufficient time to get through the “refuse to accept” process for 510(k) medical devices[31] and/or the “acceptance and filing review” process for premarket approvals[32] or De Novo classification requests[33] before the termination and withdrawal date. Marketing submissions are expected to be submitted to the Agency and approved prior to the withdrawal of the enforcement guidances. The FDA describes hypothetical scenarios to illustrate the policies outlined in the transition guidances. A key recommendation for manufacturers to include in their marketing submissions is a “transition implementation plan” that addresses the manufacturer’s plan for devices already distributed in the case of a positive or negative Agency decision.[34]  The Agency notes that it will not object to the continued distribution of devices as long as the manufacturer’s marketing submission has been submitted to and accepted by the FDA before the EUA termination date and the FDA has not taken a final action on the marketing submission.[35]  In cases where a manufacturer receives a negative decision from the FDA on its marketing submission for a product that has been distributed under an EUA prior to the termination date, the transition implementation plan is recommended to include:[36]

  • An estimated number of devices that are currently under an EUA in distribution in the U.S.
  • A manufacturer’s benefit-risk based plan and explanation for disposition of already distributed devices
  • A description of the process for notifying patients, consumers, healthcare facilities, healthcare  providers and distributors of the device’s regulatory status (i.e., device lacks FDA clearance or approval)
  • A description of the process and timeline for restoring distributed devices to the previously FDA-cleared or approved version of the devices, with publicly available labeling (and a physical copy if applicable)
  • A description of the maintenance plan for distributed devices

For manufacturers receiving a positive decision on their marketing submission, the transition implementation plan should include:[37]

  • An estimated number of devices that are currently under an EUA in distribution in the U.S.
  • A description of the process for notifying patients, consumers, healthcare facilities, healthcare providers and distributors of the device’s regulatory status (i.e., FDA cleared or approved)
  • A description of the process and timeline for providing to users of previously distributed devices updated labeling or components that reflect any changes made to the cleared or approved device

Although the FDA provides hypothetical scenarios to exemplify the timeline and expectations of the transition policy, it also recognizes that there may be unique situations raising compliance issues not covered.  To that extent, the Agency suggests manufacturers to initiate discussions through the Q-Submission Program (including Pre-Submissions) in order to develop a plan to address specific scenarios.[38]  As with all FDA guidance, these draft transition guidances — when finalized — will contain nonbinding recommendations and represent the FDA’s current view on the topic, but does not have the force and effect of law.

Conclusion
The COVID-19 pandemic will come to a welcomed end. As the supply chain crisis eases, the need for emergency measures will diminish, the continuity of patient care will be restored, and the burdens on our health care system will decrease. The FDA believes an orderly and transparent transition is appropriate for devices that fall within the scope of its guidances and encourages manufacturers to work toward a marketing submission before the termination date. The Agency intends to help facilitate this process by working with manufacturers during this transition period to avoid exacerbating product shortages and supply chain disruptions. The PHE and EUA declarations will terminate at some point and it is incumbent on manufacturers to work diligently to transition their medical devices in a timely manner without overwhelming FDA resources. In the post-COVID-19 PHE/EUA era, the FDA will likely increase the scrutiny of medical devices to assure proper transitioning  and to protect the public health by ensuring safety and efficacy. The FDA recognizes that continued flexibility is necessary, while still providing necessary oversight, and expects manufacturers to prepare early.

George Hajduczok, J.D., Ph.D., F.A.H.A., is special counsel at Phillips Lytle LLP and a member of the firm’s Life Sciences & Health Effects Practice Team. He can be reached at (716) 504-5772 or ghajduczok@phillipslytle.com.

Eric M. Kraus is a partner at Phillips Lytle LLP and co-leader of the firm’s Life Sciences & Health Effects Practice Team. He can be reached at (212) 508-0408 or ekraus@phillipslytle.com.


[1] Admin. for Strategic Preparedness & Response, Renewal of Determination That a Public Health Emergency Exists (Jan. 11, 2023), https://aspr.hhs.gov/legal/PHE/Pages/covid19-11Jan23.aspx.

[6] Section 564 was first added to the FD&C Act by the Project BioShield Act of 2004 (Pub. L. No.  108-276, 188 Stat. 835 (July 21, 2004) and amended or added by the Pandemic & All-Hazards Preparedness Reauthorization Act of 2013 (PAHPRA), Pub. L. 113-5, 127 Stat. 161 (Mar. 13, 2013). (Among other things, PAHPRA added sections 564A and 564B to the Federal Food, Drug, and Cosmetic (FD&C) Act to provide new authorities for the emergency use of approved products in emergencies and products held for emergency use.)

[7] Pandemic & All-Hazards Preparedness Reauthorization Act of 2013, Pub. L. 113-5, 127 Stat. 161 (Mar. 13, 2013).

[9] U.S. Dep’t of Health & Human Servs., Determination of a public health emergency and declaration that circumstances exist justifying authorizations pursuant to Section 564(b) of the Federal Food, Drug, and Cosmetic Act, 21 U.S.C. § 360bbb-3 (Feb. 4, 2020), https://www.fda.gov/media/135010/download.

[11] U.S. Food & Drug Admin., supra note 8, at 6.

[12] 21 U.S.C. § 360bbb-3(b)(3).

[13] U.S. Food & Drug Admin., Transition Plan for Medical Devices That Fall Within Enforcement Policies Issued During the Coronavirus Disease 2019 (COVID-19) Public Health Emergency. Draft Guidance for Industry and Food and Drug Administration Staff (Dec. 2021), https://www.fda.gov/media/155038/download.

[14] U.S. Food & Drug Admin., Transition Plan for Medical Devices Issued Emergency Use Authorizations (EUAs) During the Coronavirus Disease 2019 (COVID-19) Public Health Emergency. Draft Guidance for Industry and Food and Drug Administration Staff  (Dec. 2021), https://www.fda.gov/media/155039/download.

[16] Courts have generally held that when an agency adopts a policy where it refrains from bringing an enforcement action, such non-enforcement decisions are “committed to agency discretion” and not subject to judicial review under the Administrative Procedure Act (APA) (5 U.S.C. § 701(a)(2)). (See Heckler v. Chaney, 470 U.S. 821, 831 (1985) (noting that an enforcement decision “often involves a complicated balancing of a number of factors which are peculiarly within its expertise.  Thus, the agency must not only assess whether a violation has occurred, but whether agency resources are best spent on this violation or another, whether the agency is likely to succeed if it acts, whether the particular enforcement action requested best fits the agency’s overall policies, and, indeed, whether the agency has enough resources to undertake the action at all. An agency generally cannot act against each technical violation of the statute it is charged with enforcing.  The agency is far better equipped than the courts to deal with the many variables involved in the proper ordering of its priorities.” Furthermore, “an agency’s decision not to take enforcement action should be presumed immune from judicial review under § 701(a)(2)” of the APA). Id. at 831-32  (emphasis added))

[18] U.S. Food & Drug Admin., supra note 15, at 4-6.

[19] U.S. Food & Drug Admin., Enforcement Policy for Extracorporeal Membrane Oxygenation and Cardiopulmonary Bypass Devices During the Coronavirus Disease 2019 (COVID-19) Public Health Emergency. Guidance for Industry and Food and Drug Administration Staff, at 9 (April 2020), https://www.fda.gov/media/136734/download.

[20] U.S. Food & Drug Admin., supra note 19.

[22] 21 U.S.C. § 360bbb-3(b)(3).

[23] U.S. Food & Drug Admin., supra note 15, at 2.

[24] U.S. Food & Drug Admin., supra note 16, at 2.

[25] U.S. Food & Drug Admin., supra note 15, at 7-8.  (For timing purposes, the implementation date is set to occur at least 45 days after finalization of the guidance and the withdrawal date would occur 180 days after the implementation date.)

[28] U.S. Food & Drug Admin., supra note 16 at 5.

[29] See U.S. Food & Drug Admin., supra note 15, at 10-11 and U.S. Food & Drug Admin., supra note 16, at 11-12.

[30] See U.S. Food & Drug Admin., supra note 16, at 12.

[31] U.S. Food & Drug Admin., Refuse to Accept Policy for 510(k)s. Guidance for Industry and Food and Drug Administration Staff (April 21, 2022), https://www.fda.gov/media/83888/download, (Under this policy, the FDA reviews and informs the entity submitting the 510(k) within 15 calendar days if the submission does not meet the acceptance criteria).

[32] U.S. Food & Drug Admin., Acceptance and Filing Reviews for Premarket Approval Applications (PMAs). Guidance for Industry and Food and Drug Administration Staff (Dec. 2019), https://www.fda.gov/media/83408/download, (Acceptance and filing reviews are intended to determine whether the application submitted by the interested party is complete from an administrative standpoint).

[33] U.S. Food & Drug Admin., Acceptance Review for De Novo Classification Requests. Guidance for Industry and Food and Drug Administration Staff (Oct. 5, 2021), https://www.fda.gov/media/152657/download, (The De Novo classification option is an alternate pathway to classify novel medical devices that had automatically been placed in Class III after receiving a “not substantially equivalent” (NSE) determination in response to a premarket notification (510(k)) submission).

[34] See U.S. Food & Drug Admin., supra note 15, at 14-16 and U.S. Food & Drug Admin., supra note, 16 at 9-12.

[35] See U.S. Food & Drug Admin., supra note 16, at 11.

[38] U.S. Food & Drug Admin., Requests for Feedback and Meetings for Medical Device Submissions: The Q-Submission Program. Guidance for Industry and Food and Drug Administration Staff (Jan. 6, 2021), https://www.fda.gov/media/114034/download.

Despite the slowdown in elective medical procedures prompted by the COVID-19 pandemic, 2021 has been a banner year for medical device manufacturers.

I

ntuitive Surgical opened its Peachtree Corners, Georgia, campus nearly 10 years ago, serving as a primary training facility for surgeons and care teams on the East Coast. For 27 years, the advanced robotic systems company, headquartered in Sunnyvale, California, has changed the landscape of medical practice through minimally invasive robotic-assisted surgery. Dozens of hospitals around Georgia use Intuitive’s systems and technologies, such as the da Vinci, with portions of the da Vinci XI and X systems manufactured in Peachtree Corners, a northeast Atlanta suburb in the metro area’s booming Gwinnett County.

Despite the slowdown in elective medical procedures prompted by the COVID-19 pandemic, 2021 has been a banner year for medical device manufacturers.

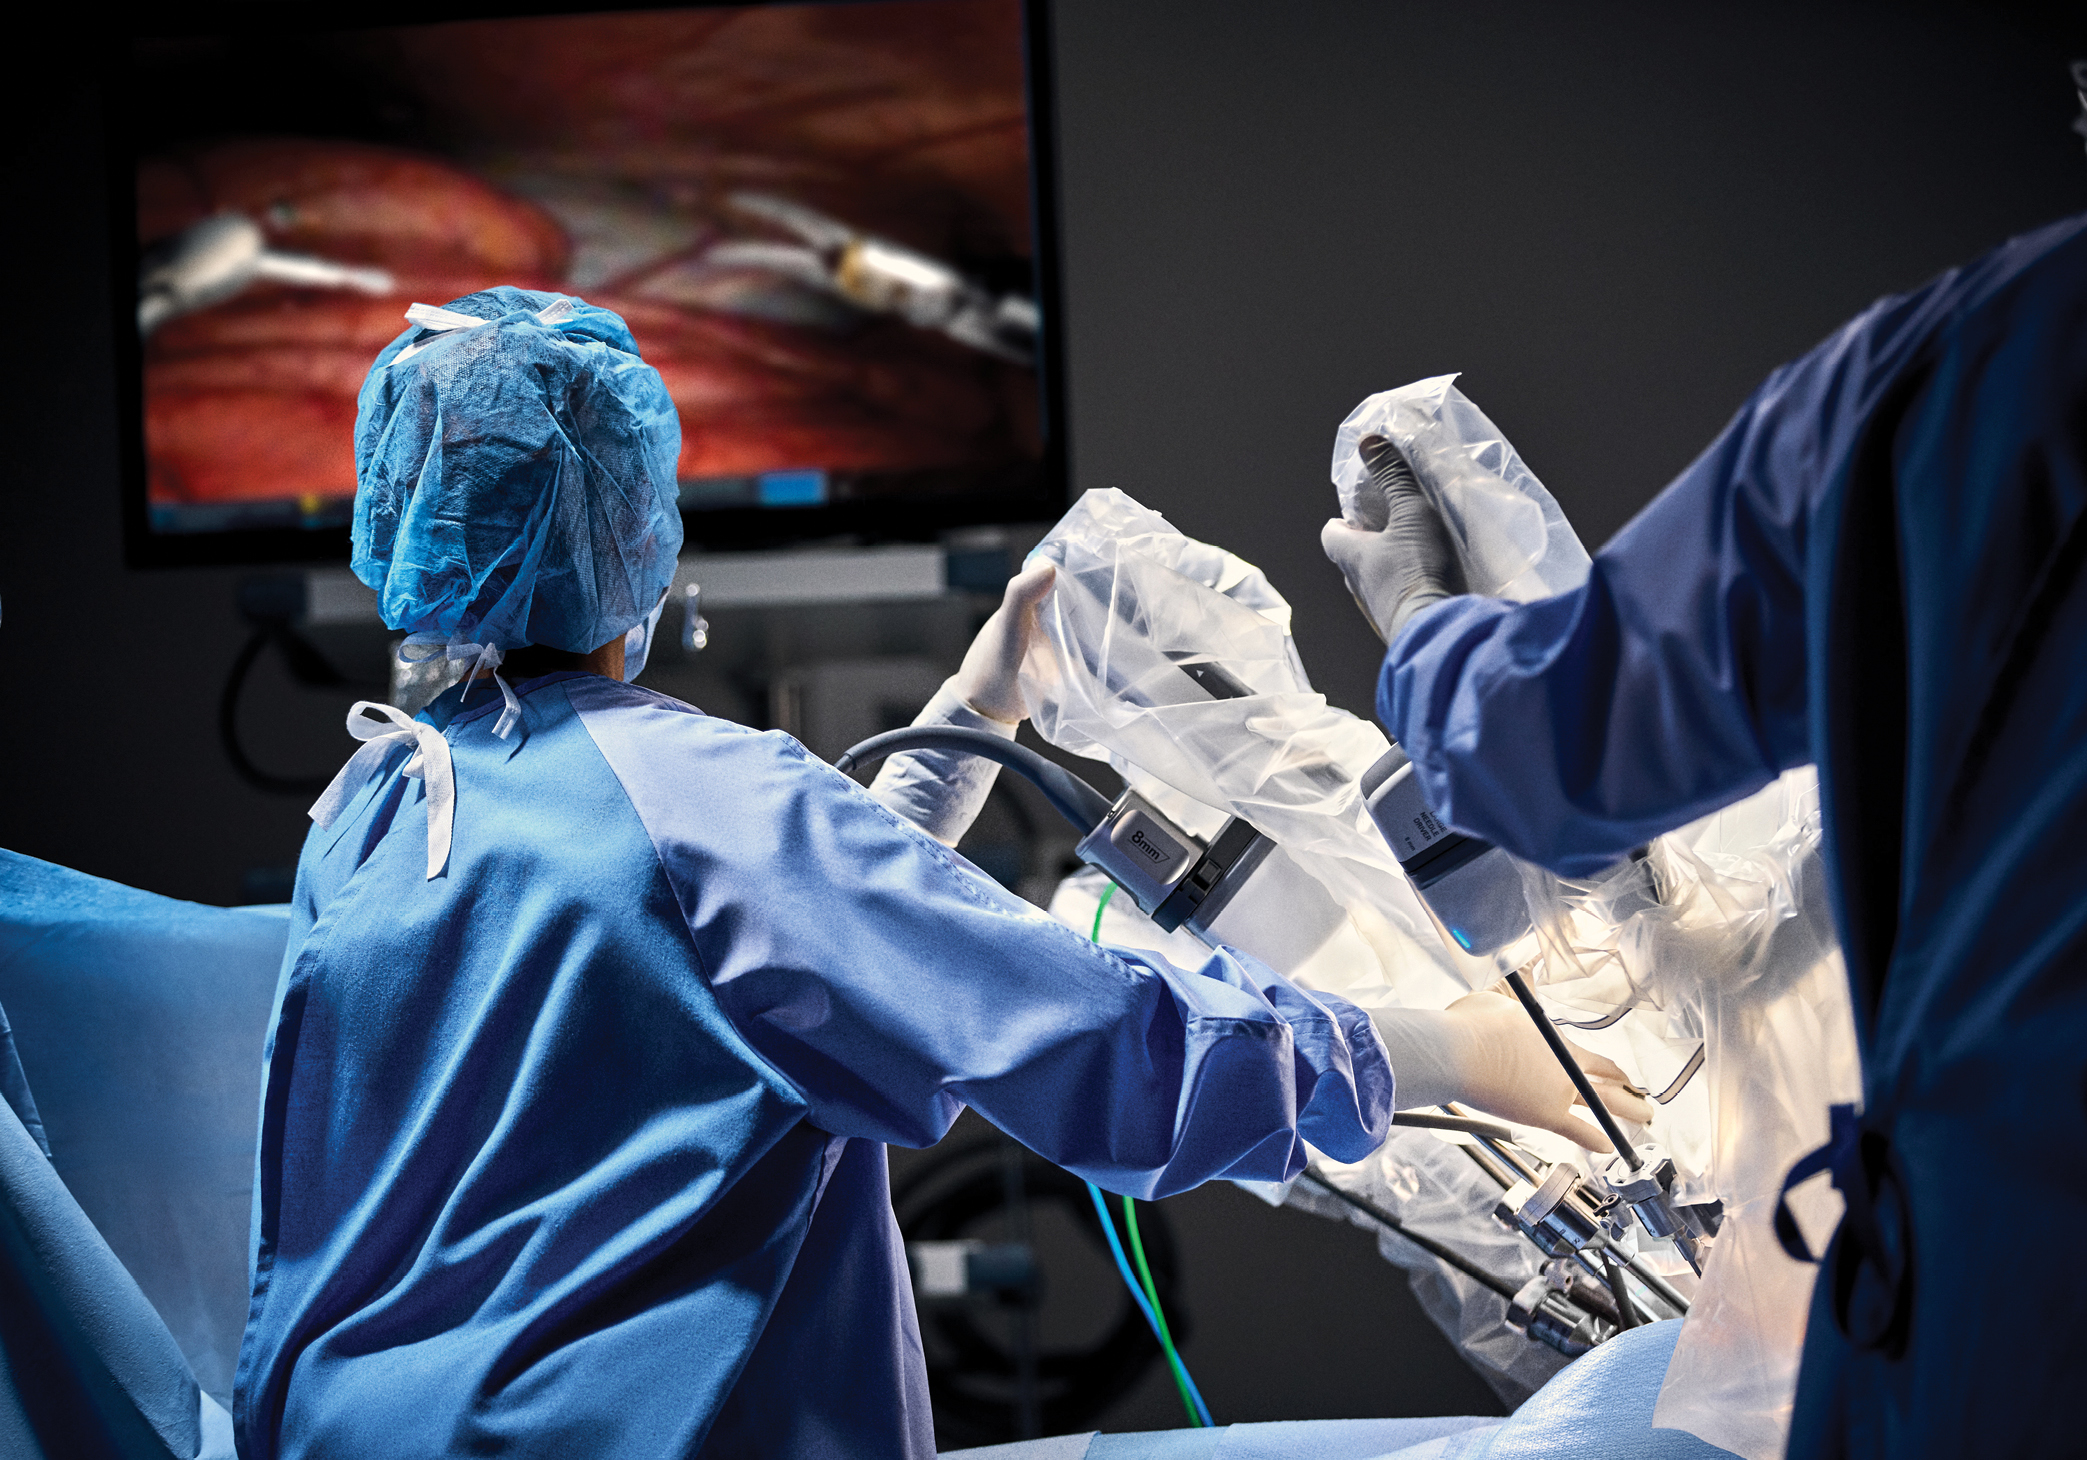
Surgeon operating with da Vinci XI system.

Photo courtesy of Intuitive Surgical.

Intuitive plans to expand its Georgia site to 750,000 sq. ft. with a $500 million investment to include manufacturing and engineering operations, training facilities and administrative offices. Now under construction, the site (about a mile from Site Selection’s headquarters) will be opening in phases until completion, with full operation anticipated by 2024.

“This expansion is part of our broader, multi-year global growth strategy to build and expand global ‘hubs’ where we can best support our customers and all elements of our business,” says Eric Torbenson, senior manager of global public affairs at Intuitive. “Over the next few years, we anticipate adding approximately 1,200 employees in manufacturing, production, distribution, engineering, sales, customer training, customer service and more.”

Torbenson tells Site Selection that access to a strong and diverse talent pool and quality infrastructure were key factors in Intuitive’s decision to expand in Georgia.

Peachtree Corners City Manager Brian Johnson says Intuitive’s investment is the largest economic development project in Gwinnett County’s history. With the creation of 1,200 high-paying jobs, Johnson notes the move is a “game changer” for the community, a win that state and local officials worked hard to score.

The impact on the local economy through increased need for housing, education and retail developments brings challenges that Johnson looks forward to addressing. Investments like Intuitive’s not only bring new talent to the area, but site acquisitions from suppliers as well.

“These are companies that want to be close to the mothership,” Johnson says. “We have definitely had interest and are working with some of those companies now to show why they should move to Peachtree Corners.”

CBRE’s Americas Life Sciences Leader Matthew Gardner says markets like Atlanta are gaining recognition.

“I think that’s a very important signal for the industry to hear they can find a highly educated life sciences workforce in a number of markets around the U.S.”

— Matthew Gardner, Americas Life Sciences Leader, CBRE

“There’s something really interesting as a signal to other multinationals about that decision, which is that a lot of the industry feels like it has matured in Massachusetts and California and has to think about [which] emerging markets should be next,” he says. “I think that’s a very important signal for the industry to hear they can find a highly educated life sciences workforce in a number of markets around the U.S.”

Georgia, with assets such as the Atlanta-based Centers for Disease Control and Prevention in its holster, indeed has gained recognition and attracted investments from top players in the industry, including Boston Scientific and Moderna.

CBRE’s top five life sciences markets — Boston, Washington, D.C., San Francisco, New York and San Diego — tote a high cost of living relative to salary earnings. Atlanta finds itself in a favorable situation as the annual cost of living averages $48,752, according to the U.S. Bureau of Labor Statistics. That low cost of living in comparison to other metros plays a vital role in not only talent retention, but real estate costs as well.

CBRE’s 2022 Life Sciences Talent Report ranked Atlanta 14th out of the top 25 life sciences research talent clusters. “Denver/Boulder, Minneapolis/St. Paul, Houston, Atlanta, Dallas/Ft. Worth and Miami, though sometimes overlooked, also have world-class health centers and universities, and in turn, sizable pools of life sciences research talent,” the report stated.

Institutions such as Emory University and Georgia Institute of Technology offer a wealth of skilled talent to add to over 75,000 life science employees in the state. Between 2016 and 2020 the state produced over 33,000 graduates with life sciences-related degrees. Over the next 10 years, Georgia occupations in the industry are expected to increase by 7{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}, higher than the U.S. average.

Just Up the Street

Georgia Governor Brian Kemp announced in June 2022 that Boston Scientific plans to expand its Johns Creek facility. About 11 miles northwest of Initiative’s campus, what was once an EndoChoice site became part of Boston Scientific’s Endoscopy business in 2016 after a $210 million acquisition.

MedicalDevicesFinal1122a-two

Construction underway at Intuitive’s Peachtree Corners site.

Photo by Adam Bruns

For over 40 years, the medical technology leader has designed and manufactured a portfolio of over 17,000 products. The company’s medical devices and therapies cater toward less-invasive procedures, its Georgia facility specializing in endoscopy.

Boston Scientific is investing $62.5 million to expand and integrate a new manufacturing and supply chain plant. The expansion will create 340 new jobs, adding to its roster of 300 employees in Fulton County.

“As we expand our presence in Georgia, we remain grateful to all of our local employees whose work is already making a difference for healthcare providers and patients around the world,” said Brad Sorenson, executive vice president of global operations at Boston Scientific, in a press release. “Our new site in Johns Creek will enable continued growth as we fulfill our mission to transform lives.”

Like the city of Peachtree Corners, Fulton County figures prominently in Atlanta’s budding life sciences market. According to Georgia Power’s 2021 Life Sciences Database there are 110 medical device companies in Georgia, employing over 10,000. The sector accounts for $2.8 billion of Georgia’s Gross Regional Product.

Georgia’s potential to be one of the next big medical devices markets is not a far-fetched idea.