The hospital treating her baby was in-network, but another hospital charged her : Shots

The hospital treating her baby was in-network, but another hospital charged her : Shots

Brenna Kearney plays with her daughter, Joey, at home in Chicago. When Kearney was pregnant, she developed a rare type of preeclampsia and had to undergo an emergency cesarean section. Joey was discharged after a 36-day stay in the NICU.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Brenna Kearney plays with her daughter, Joey, at home in Chicago. When Kearney was pregnant, she developed a rare type of preeclampsia and had to undergo an emergency cesarean section. Joey was discharged after a 36-day stay in the NICU.

Taylor Glascock for KHN

Brenna Kearney was seven months pregnant in December 2019 when she experienced what she thought were bad flu symptoms.

Her husband, Casey Trumble, drove her from their Chicago home to her OB-GYN’s office at Northwestern Medicine Prentice Women’s Hospital downtown. With suddenly elevated blood pressure and protein in her urine, she was diagnosed with preeclampsia, a potentially fatal but treatable pregnancy complication. Doctors admitted her to the hospital, saying she could expect to stay up to six weeks and have an induced delivery.

Then Kearney developed a bad headache and her blood platelet count plummeted, signs she was experiencing a rare, dangerous type of preeclampsia and required an immediate delivery by cesarean section.

Casey Trumble shows a photo of his daughter, Joey, after her premature birth in 2019. Her parents later learned she was treated in her Chicago hospital’s NICU by out-of-network neonatologists from the children’s hospital next door.

(Taylor Glascock for KHN)


hide caption

toggle caption

(Taylor Glascock for KHN)


Casey Trumble shows a photo of his daughter, Joey, after her premature birth in 2019. Her parents later learned she was treated in her Chicago hospital’s NICU by out-of-network neonatologists from the children’s hospital next door.

(Taylor Glascock for KHN)

Kearney’s daughter, Joey, born at 31 weeks, was placed on a ventilator and moved to the hospital’s neonatal intensive care unit. Small but healthy, she slowly began breathing on her own and eating normally. She was discharged in late January 2020, after 36 days in the NICU.

Then the bill came.

The Patient: Josephine “Joey” Trumble, now 3, was covered by her mother’s health plan through her employer, an advertising agency. For 2019, it was an Aetna plan, and for 2020, it was a plan from Blue Cross and Blue Shield of Illinois. Both policies were fully insured plans governed by Illinois laws.

Medical service: Neonatology physician services provided in January 2020. Joey needed tube feeding and ventilator care to provide oxygen.

Service rovider: Ann & Robert H. Lurie Children’s Hospital of Chicago, whose staff physicians treated Joey at Northwestern Medicine Prentice Women’s Hospital. Ownership-wise, Lurie is independent of Northwestern Medicine, but it is physically connected to Prentice Women’s by an enclosed walkway. Lurie has a collaboration agreement with Northwestern Medicine to provide neonatology and pediatric physician services to Prentice Women’s patients.

Total bill: Aetna paid for nearly all of Joey and her mother’s hospital and physician charges in December, while Blue Cross picked up nearly all of Joey’s hospital charges in January. Physician charges from Lurie in January totaled $14,624.55, of which the family was asked to pay $12,531.58 after payments from Blue Cross.

What gives: It took Kearney months of calls to Blue Cross and the two hospitals to find out why Lurie billed more than $14,000 for physician services: The physicians treating her daughter at Prentice Women’s — an in-network hospital under her health plan — actually worked for a separate, out-of-network hospital.

Illinois law bars insurers from charging patients out-of-network rates for neonatal care at in-network hospitals.

Kearney said no one had told her or her husband that Lurie doctors were treating their daughter. She said the family never signed an agreement consenting to receive care from out-of-network doctors.

Though it did not happen here, many patients unknowingly sign broad financial agreements — saying they’ll pay for almost anything their insurance doesn’t cover — in the piles of paperwork they receive upon admission to a hospital. In many cases, they are simply asked to sign on a screen, without seeing the document.

Blue Cross agreed to pay Lurie the in-network rate for the doctors’ services, reducing the bill to about $12,500 — which Lurie expected the family to pay.

In November 2020, Kearney started receiving letters from ICS Collection Service, a collection agency.

“Talking to Blue Cross was impossible, and Lurie said it’s not their problem and just wanted to put us on a payment plan,” Kearney said.

Details of the out-of-network medical bills totaling about $12,500 that Brenna Kearney and husband Casey Trumble received after their daughter, Joey, was born prematurely in 2019.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Details of the out-of-network medical bills totaling about $12,500 that Brenna Kearney and husband Casey Trumble received after their daughter, Joey, was born prematurely in 2019.

Taylor Glascock for KHN

Joey’s 36-day stay in the NICU happened before the federal government implemented the No Surprises Act barring surprise out-of-network billing. A state law prohibiting it, though, was in effect.

Since 2011, Illinois law has prohibited insurers from charging out-of-network rates for neonatologists, anesthesiologists, and certain other physicians when patients are treated at in-network hospitals.

Kearney said she repeatedly mentioned the law to Lurie and Blue Cross representatives, who denied knowledge of the provision.

“It definitely appears that under the 2011 law, Brenna can only be billed for in-network cost sharing,” said Kathy Mikos, a registered nurse and patient advocate with the Navocate Group in Woodridge, Illinois, who is not involved with Kearney’s case.

In December 2020, an insurance broker working for Kearney’s employer persuaded Blue Cross to pay the full out-of-network charges for the Lurie doctors, leaving the family owing $289.63 for coinsurance, which they promptly paid.

Having spent nearly the first year of her daughter’s life fighting medical bills from her birth, Kearney thought the ordeal was over.

Then, last month, she got a call from the collection agency, which again demanded payment at the full out-of-network rate for Lurie physician services provided to her daughter three years ago — the bill she believed Blue Cross had paid.

It took five hours on the phone for Kearney to piece together what had happened. Blue Cross had indeed paid the out-of-network charges in December 2020 — but, two days later, had taken back the money, ultimately paying Lurie’s doctors only the in-network rate.

A Lurie representative said Kearney and her husband still owed thousands of dollars. A Blue Cross representative suggested she set up a payment plan.

“I was at wits’ end, and I didn’t know how to fight this anymore,” Kearney said.

Lurie, Blue Cross, and Northwestern Medicine did not respond to numerous requests from KHN for comment. Lurie cited patient privacy, despite receiving a release from Kearney regarding the federal Health Insurance Portability and Accountability Act, or HIPAA, which authorized the hospital to discuss Joey’s case with KHN.

Joey Trumble was born prematurely in 2019 at Northwestern Medicine Prentice Women’s Hospital in Chicago. Unbeknownst to her parents, she was treated in the NICU by doctors from Lurie Children’s Hospital next door — and charged despite a state law protecting patients from such out-of-network billing.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Joey Trumble was born prematurely in 2019 at Northwestern Medicine Prentice Women’s Hospital in Chicago. Unbeknownst to her parents, she was treated in the NICU by doctors from Lurie Children’s Hospital next door — and charged despite a state law protecting patients from such out-of-network billing.

Taylor Glascock for KHN

The resolution: After KHN contacted Lurie and Blue Cross, a Lurie representative called Kearney offering to accept payment at the in-network rates after all.

Kearney said Tracy A. Spicer, manager of consolidated services at Lurie, told her Lurie has a “long-standing policy” of accepting in-network rates for Lurie physician services provided at Prentice Women’s. Spicer subsequently described it as a “long-standing courtesy,” then explained that acceptance of in-network rates was subject to “case-by-case consideration,” Kearney said.

Spicer said the family owed about $3,000, for their coinsurance share, and offered to set up a payment plan.

A day later — following additional requests by KHN for comment — Spicer called Kearney and said she would remove all physician charges for her daughter’s care. Spicer did not return KHN’s call seeking comment.

“I’m certain I’m not the only person still dealing with this” kind of predicament, Kearney said.

Kearney has filed complaints with the Illinois Department of Insurance and the Illinois Attorney General’s Office. The attorney general’s office told KHN it had never enforced the 2011 law barring certain out-of-network billing.

Presented with the facts of Kearney’s case, state Sen. Ann Gillespie, who sponsored a 2022 state law expanding consumer protections against out-of-network bills, told KHN she plans to contact Lurie, Blue Cross, and Northwestern Medicine to ask about their billing arrangement and whether they are in compliance with state law.

“We’ll see if it was a pattern and whether they need to look back and see if refunds are warranted,” Gillespie said.

The attorney general’s office told KHN it will investigate Kearney’s complaint, including whether Lurie violated the state Consumer Fraud and Deceptive Business Practices Act by telling her it was extending a “courtesy” by charging her only in-network rates, when that is what the 2011 law required. The insurance department also said it would investigate the complaint.

Brenna Kearney and husband Casey Trumble at home with daughter Joey, 3, and their 5-month-old son. Joey was born prematurely in 2019 and, unbeknownst to her parents, treated in the NICU by doctors from a neighboring hospital, Lurie Children’s.

Taylor Glascock for KHN


hide caption

toggle caption

Taylor Glascock for KHN


Brenna Kearney and husband Casey Trumble at home with daughter Joey, 3, and their 5-month-old son. Joey was born prematurely in 2019 and, unbeknownst to her parents, treated in the NICU by doctors from a neighboring hospital, Lurie Children’s.

Taylor Glascock for KHN

The Takeaway: Even resourceful consumers who appear to have the law on their side, like Kearney, may find themselves in a losing, time-consuming battle with medical billing bureaucracies and facing collection actions.

Gillespie, the state senator, said Lurie, Northwestern Medicine, and Blue Cross should have known about the state law. She said patients who believe they have been improperly charged should file complaints with their state’s insurance department, which can trigger a broader investigation.

The federal No Surprises Act, which took effect last year, prohibits medical providers or insurers from billing patients for out-of-network physician charges at an in-network hospital, unless the patient formally consents to an out-of-network doctor. To be safe, patients should ask treating doctors whether they are in or out of network, even at an in-network hospital.

While the federal law offers patients new protections from out-of-network bills, many Americans still face problems from before the law took effect, said Loren Adler, associate director at the USC-Brookings Schaeffer Initiative for Health Policy. Illinois is one of relatively few states that had prior laws to protect consumers.

Also, some out-of-network physicians continue to bill patients, despite the new federal protections. So know your rights. Cite the new law. And don’t write the check.

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

FDA Experts Are Still Puzzled Over Who Should Get Which Covid Shots and When

At a meeting to simplify the nation’s covid vaccination plan, the FDA’s panel of specialists could agree on only one particular factor: Info is woefully missing about how generally unique teams of Americans want to be vaccinated. That information hole has contributed to common skepticism, undervaccination, and ultimately needless fatalities from covid-19.

The committee voted unanimously Thursday to help the FDA’s proposal for all vaccine-makers to undertake the similar strain of the virus when producing improvements in their vaccines, and suggested they may meet in May possibly or June to select a pressure for the vaccines that would be rolled out this tumble.

However, the panel users disagreed with the FDA’s proposal that all people get at least 1 shot a calendar year, saying much more details was required to make such a declaration. Many panelists famous that in new research, only about a 3rd of people hospitalized with a constructive covid examination in fact were there because of covid health issues. Which is since all people getting into a medical center is examined for covid, so fatalities of sufferers with incidental bacterial infections are counted as covid deaths even when it is not the lead to.

The industry experts questioned the rationale for annual photographs for everybody, presented that latest vaccines do not seem to safeguard versus an infection for much more than a couple months. Yet even a single booster appears to protect against demise and hospitalization in most people today, besides for the quite previous and persons with particular health care ailments.

“We need to have the CDC to notify us just who is getting hospitalized and dying of this virus — the ages, vulnerability, the style of immune compromise, and no matter if they had been handled with antivirals. And we need to have immunological details to point out who’s at danger,” stated Dr. Paul Offit, director of the Vaccine Schooling Center and a pediatrician at Children’s Medical center of Philadelphia. “Only then can we decide who will get vaccinated with what and when.”

Offit and many others have expressed frustration over the deficiency of crystal clear authorities messaging on what the public can hope from covid vaccines. When common boosters could possibly be vital for keeping the elderly and medically frail out of the healthcare facility, he claimed, the yearly boosters prompt by the Fda and the drug businesses could not be vital for everybody.

“The intention is to maintain men and women out of the healthcare facility,” he stated. “For the vulnerable, it would be essential for vaccines to preserve up with circulating strains. But for the general populace, we by now have a vaccine that stops hospitalization.”

Other panelists reported the government needs to force exploration tougher to get much better vaccines. Pamela McGinnis, a retired formal of the National Institutes of Overall health, said she had trouble detailing to her two youthful-adult sons why they immediately obtained ill after venturing out to bars a single night only months after having their bivalent booster.

“‘Think how sick you would have gotten if you weren’t totally vaccinated’ is not a good message,” she mentioned. “I’m not guaranteed ‘You would have landed in the hospital’ resonates with recipients of the condition.”

Associates of the FDA’s advisory committee have been irked in the latest months, saying the agency didn’t existing them with all the data it experienced on the bivalent vaccine in advance of it was unveiled in September. And some critics have said the Fda should have instructed drug companies to involve only the more recent strains of the virus in the shot.

Asked about that Thursday, Jerry Weir, a senior Food and drug administration vaccine officer, mentioned his “gut feeling” was that a vaccine matched to a single omicron pressure would have done far better than the bivalent shot, which also consists of the authentic covid pressure. “But the real issue is the place we’re headed,” he claimed, “and I do not know the respond to.”

Potentially the most important presentation Thursday was from Heather Scobie, who retains tabs on covid at the Centers for Condition Command and Avoidance. She reported that less than fifty percent of Us residents 65 and more mature experienced gotten the most up-to-date booster, and that only two-thirds of that age group had gotten even a single booster.

Nonetheless proof continues to mount that it’s primarily the aged who are at really serious possibility from covid. Dying prices from the illness have declined in each and every age group other than those people more than 75 due to the fact April, in spite of the uptick in new strains. Except for the extremely old, the dying charge has hovered about 1 in 100,000 due to the fact April. Before in 2022, infants 6 months old and more youthful have been hospitalized and died at relatively significant prices. Vaccination stages in the 4-and-beneath team hover at about 10{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}.

Though acknowledging the FDA’s motivation to regularize its covid vaccine policy, panel customers claimed it is nevertheless too early to know for positive whether or not covid will surge only in the winter season, like flu, respiratory syncytial virus, and other respiratory bacterial infections.

“For the following couple of decades we may possibly not know how normally we have to have to make a strain change in the vaccine,” said Dr. Steven Pergam, professional medical director of an infection avoidance at the Seattle Cancer Treatment Alliance. Or even if individuals who are not in poor overall health or aged have to have extra boosters.

One vaccine-maker represented at the conference, Novavax, reported it would have to have to know by the stop of March which pressure to include things like in its vaccine for slide. Companies with mRNA vaccines like Pfizer and Moderna can adjust their formulation speedier, but their solutions aren’t clearly better than Novavax’s.

All three of those vaccine-makers discovered at the meeting that they are establishing one-dose vials or prefilled syringes. Up to now, they’ve shipped their vaccines in multidose vials, but considering that the governing administration has run out of revenue to acquire vaccines, individual pediatricians might get them in the long run. Because the vaccine ought to be utilised swiftly as soon as a vial is open, doctors are leery of squandering vaccine and dropping income.

KHN (Kaiser Well being Information) is a countrywide newsroom that creates in-depth journalism about well being difficulties. With each other with Policy Assessment and Polling, KHN is 1 of the 3 significant functioning systems at KFF (Kaiser Loved ones Basis). KFF is an endowed nonprofit business offering info on health and fitness concerns to the nation.

USE OUR Information

This tale can be republished for free of charge (particulars).

A Real Danger for People With Alzheimer’s

By Cara Murez HealthDay Reporter

A Real Danger for People With Alzheimer’s

(HealthDay)

FRIDAY, Jan. 27, 2023 (HealthDay News) — Wintertime weather can include a layer of risk to the wandering actions prevalent in people with dementia.

The Alzheimer’s Foundation of The united states (AFA) delivers some tips to assistance protect against wandering and get ready individuals to react speedily if it occurs.

“During the winter season, it is particularly important for people residing in locations influenced by chilly weather conditions, snow and ice,” stated Jennifer Reeder, director of academic and social solutions for the foundation.

“Being proactive by understanding and addressing the causes somebody may perhaps wander, even though also having a system in put in situation of an crisis, are the ideal means to shield the person’s security and excellent of life,” she said in an AFA information launch.

Start off by figuring out what motivates your loved one with dementia to wander outside.

It may perhaps be that it offers the person a feeling of purposefulness, enjoyment or enjoyment. It could also be activated by also significantly stimuli and the want to get absent from noises and individuals. It could also sign an unmet have to have, such as hunger, thirst or the have to have to use the bathroom.

You could be equipped to fill any of these desires far more properly and minimize dangerous wandering, Reeder explained.

Try developing strolling paths around the dwelling with visible cues and stimulating objects. Engage the human being with dementia in basic responsibilities. Present stimulating and satisfying functions, this kind of as work out, songs or crafts. And, of training course, assure basic needs are satisfied.

Make certain the property is harmless. Begin by retaining walkways absolutely free of muddle and tripping dangers. Be conscious about how acquiring specific objects in perspective, such as motor vehicle keys, jackets and purses, could result in the human being to leave out of the blue.

Put in electronic chimes or doorbells on doorways. That will inform you if the person tries to exit. Take into account working with a clever doorbell with an app that can notify you when someone is getting into or exiting the house.

Detect what periods of working day make your beloved one far more energetic and attempt to provide stimulating things to do during that time. Encourage healthier snooze practices to cut down the odds of the individual leaving through the center of the evening.

Preserve a report of wandering designs — frequency, period, time of working day — to help guide you in the potential.

Have a security approach. This could incorporate a listing of locations a individual could go, this sort of as their past household or put of employment. Be certain you have a the latest near-up photograph of your liked one and accessible healthcare information for initial responders.

Retain a checklist of people to get in touch with if the particular person goes missing. Check with neighbors to contact you if they see the individual out on their personal.

Look into group safety programs, these types of as Undertaking Lifesaver, which can supply finding engineering. To start with responders can activate this if your liked a single is missing. If doable, get enter from the particular person with dementia when building the strategy.

If you require far more tips, arrive at out to a social employee at AFA’s helpline. It’s accessible by cell phone at 866-232-8484 textual content at 646-586-5283, and world wide web chat at www.alzfdn.org.

The U.S. Nationwide Institute on Growing old has ideas on property basic safety.

Source: Alzheimer’s Basis of The usa, information release, Jan. 26, 2023

Copyright © 2023 HealthDay. All legal rights reserved.

COVID vaccine strategy to get an overhaul by FDA : Shots

COVID vaccine strategy to get an overhaul by FDA : Shots

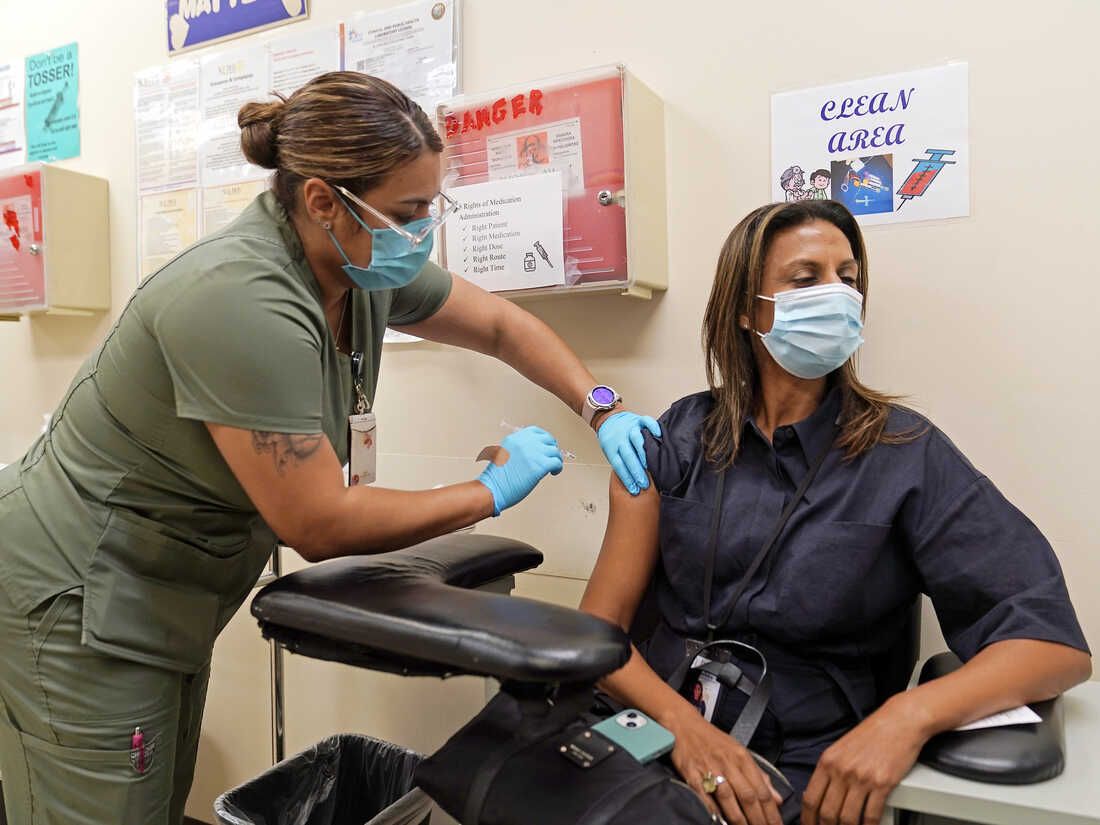
Licensed vocational nurse Denise Saldana vaccinates Pri DeSilva, associate director of Individual and Corporate Giving, with a fourth Pfizer COVID-19 vaccine booster at the Dr. Kenneth Williams Health Center in Los Angeles, Nov. 1, 2022.

Damian Dovarganes/AP


hide caption

toggle caption

Damian Dovarganes/AP


Licensed vocational nurse Denise Saldana vaccinates Pri DeSilva, associate director of Individual and Corporate Giving, with a fourth Pfizer COVID-19 vaccine booster at the Dr. Kenneth Williams Health Center in Los Angeles, Nov. 1, 2022.

Damian Dovarganes/AP

The Food and Drug Administration is considering a major shift in the nation’s COVID-19 vaccine strategy.

The goal is to simplify vaccination against COVID and perhaps adopt an approach similar to what is used for the flu vaccine, with annual updates to match whatever strain of the virus is circulating. This is according to a federal official who spoke under the condition of anonymity because they were not authorized to speak publicly.

NPR reported the proposed shift early Monday morning, and later Monday the FDA outlined it publicly in a set of documents released in advance of a meeting Thursday of the agency’s Vaccine and Related Biological Products Advisory Committee (VRBPAC). The committee will vote on the agency’s proposal.

Currently, people who want to be fully vaccinated against COVID have to first get their primary vaccinations — two shots of the original vaccine spaced weeks apart. That’s followed at least two months later by a booster, currently the bivalent shot that’s tailored to protect against omicron.

Under the new approach, most people would be advised to simply get whatever the latest version of the vaccine is annually each fall like the flu vaccine. They wouldn’t have to worry about how many shots they’ve already gotten and which one they got when. Those who still need to receive two doses initially, such as young children and older people, would use the same formulation for all three shots.

Vaccine makers would update the annual shot through a process that would begin each spring to try a match the vaccine as closely as possible to whatever variant will likely be dominant in the coming winter. That’s how the flu vaccine is formulated each year.

“FDA anticipates conducting an assessment of SARS-CoV-2 strains at least annually and to engage VRBPAC in about early June of each year regarding strain selection for the fall season,” the FDA wrote in its briefing document, adding that updated vaccines would be readied for use by September each year.

The agency notes that if a more dangerous COVID variant were to emerge, it might reconsider the vaccine strain at other times of the year on an “as-needed and emergent basis.”

Some immunologists and vaccine researchers say simplifying the process along the lines of the flu vaccine is appropriate at this point in the pandemic. However, many questions remain about emerging booster strategy.

“As far as the tools that we have right now, I think it just makes the most sense to plan to update each year as close as we can to the currently circulating variant,” says Deepta Bhattacharya, an immunologist at the University of Arizona. “So I think all the things the FDA is considering make a lot of sense.”

Questions about efficacy of updated shots

There’s an intense debate about the wisdom of updating the COVID vaccines regularly to try to match new variants. Some researchers question whether that really makes the vaccines more effective. They also argue that the low demand for the latest booster shows the public has little appetite for continued boosting with the vaccines, even if they’ve been updated with new strains.

“The public is voting with their arms if you will and said, ‘No. I’m not going to get this. This doesn’t make sense to us,'” says Dr. Gregory Poland, a vaccine researcher at the Mayo Clinic.

While endorsing continued boosters for those at high risk, such as the elderly, some question whether the current bivalent vaccines updated to target omicron have enhanced protection compared to the original vaccines. Most people are still well-protected against severe disease by the immunity they already have, they say.

“We have no solid data about the performance of the bivalent boosters,” says John Moore, an immunologist at Weill Cornell Medical College. “The hard evidence is lacking, and the evidence that is out there is at the very least inconclusive and to me trends towards saying the bivalent boosters were little if no better.”

Moore and others argue that the virus is changing so fast that it’s pointless to constantly try to match the vaccines to the latest variants.

“We shouldn’t really be chasing these variants, which are evanescent and are often gone by the time you’ve created the vaccine,” says Dr. Paul Offit of the University of Pennsylvania, one of the FDA’s advisers.

Offit and others also question whether everyone will necessarily need to be boosted regularly, or just those at high risk, like the elderly.

Arguments for alternate vaccine strategies

Critics of the FDA’s proposed new strategy argue that it would be better to invest in developing better vaccines that might be more appealing to people, and in campaigns to get more people vaccinated. Better vaccines could include those that could keep people from catching the virus in the first place not just from getting seriously ill — such as a nasal spray vaccine. Or perhaps vaccines that provide longer protection or are administered in pill form, to make them more acceptable to the needle-averse.

“Particularly now when Congress is not allocating new funds for COVID response, we have to be especially judicious in how we spend our money and what would be most cost-effective,” says Dr. Celine Gounder, a senior fellow at the Kaiser Family Foundation. “It’s unclear whether updating the booster formulations and repeatedly boosting people is the most effective approach to controlling COVID at this stage.”

Another concern some researchers have is that the FDA continues to rely on antibody levels to test vaccine efficacy.

“I think we need to raise the bar and require more evidence of clinical efficacy,” says Dr. Eric Rubin, a professor of immunology and infectious diseases at Harvard who is also a member of the advisory committee. For instance, Rubin says the FDA should require proof the updated vaccines are actually reducing the risk of getting infected, getting sick, hospitalized and dying.

Others say updating the vaccines make sense to make sure people are as well-protected as possible while researchers continue to try to develop new vaccines.

“Even if you don’t have a booster that matches 100{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} what’s circulating, you will have a booster that matches 75{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} to 80{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} to 90{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of what’s circulating,” says David Martinez, an immunologist at the University of North Carolina, Chapel Hill. “And that will be good enough. It would probably benefit most people.”

The FDA looks ahead to endemic COVID

Some researchers think it’s too soon to rely on annual boosters. COVID hasn’t quite settled into a seasonal pattern like the flu, they note, and the SARS-CoV2 virus is changing more quickly than the flu virus. So people may need to be boosted more frequently, especially since protection against severe disease may only last about four to six months, they say.

“We’re going to be reaching that pretty soon with the early adopters of the bivalent boosters, like myself,” says Dr. Peter Hotez, co-director of the Center for Vaccine Development at Texas Children’s Hospital and dean of the National School of Tropical Medicine at Baylor College of Medicine. “I don’t know if an annual strategy is going to cut it.”

The FDA’s plan comes as COVID appears to be moving toward becoming an endemic disease. That doesn’t mean it’s going away or it’s not a threat anymore. The disease will continue to be a threat for the foreseeable future, making many people sick and even potentially killing hundreds a day, making it a major public health problem and a leading cause of death, health experts say.

But unless some more dangerous version of the virus suddenly emerges, the world might finally be settling into a more predictable co-existence with the virus. The federal official NPR spoke to says the goal of the new vaccine strategy is to make the vaccines, which are the major weapon for protecting ourselves, simpler and hopefully therefore more appealing. The latest boosters have found very few takers.

The thinking is that at this point in the pandemic the overwhelming majority of people have a significant levels of immunity, either from having gotten vaccinated and boosted, or infected one of more times, or both. And while that immunity appears to protect most people from severe disease, that protection does appear to fade with time.

The FDA is also considering making the shots interchangeable. That way people wouldn’t have to worry which brand they’re getting. Again, the change is aimed at making COVID shots more like the flu shots. People don’t typically worry about the brand of the flu vaccine they receive.

The vaccine would still be administered at different doses for different ages. And very young children and older people would still get two shots each year, much like the flu vaccine.

If the FDA advisory committee endorses the approach Thursday, the FDA would work with the vaccine companies and Centers for Disease Control and Prevention to finalize the details. And the FDA advisers would meet again in the spring to pick the specific strain or strains of the virus the new shots should target.

As States Seek to Limit Abortions, Montana Wants to Redefine What Is Medically Necessary

Montana’s conservative leaders, stymied by the courts from passing laws that impose major statewide abortion restrictions, find to tighten the state’s Medicaid regulations to make it additional challenging for lower-income women of all ages to receive abortions.

The Montana Department of Public Health and fitness and Human Products and services is proposing to outline when an abortion is medically necessary, limit who can execute these kinds of providers, and call for preauthorization for most situations.

The drive to transform the polices is borne of a belief by Republican Gov. Greg Gianforte’s administration that wellness providers are applying existing policies that enable Medicaid reimbursements to deal with abortions that aren’t medically needed.

“Taxpayers shouldn’t foot the monthly bill for elective abortions,” mentioned Gianforte spokesperson Brooke Stroyke.

Professional medical pros have claimed the expression “elective abortions” can misrepresent the advanced reasons somebody could look for an abortion and constrain wellbeing providers from making their best scientific judgment. Laurie Sobel, associate director of Women’s Health Policy at KFF, mentioned that seems to be the purpose of the Montana proposal’s aim on defining medically necessary abortions.

“It appears like Montana’s trying to curtail abortion obtain beneath Medicaid and acquire the conversation of ‘medically necessary’ absent from a physician and a affected individual,” Sobel said.

Democratic lawmakers and lots of wellness providers have said existing point out policies guarantee suppliers look at and document why an abortion is needed to guard a client.

Democratic state Rep. Ed Stafman, who a short while ago chaired the Youngsters, Families, Well being, and Human Providers Interim Committee, mentioned the proposed improvements are pointless simply because the point out presently complies with federal Medicaid rules on abortion.

“It’s obvious that this is portion of the anti-abortion agenda,” Stafman said.

States are barred from applying federal cash to pay for abortions other than in conditions of rape or incest, or when a woman’s lifetime is at threat. On the other hand, states have the option of making use of their have cash to let reimbursements below the joint condition-federal Medicaid application in other circumstances.

Montana is one of 16 states that permit the use of point out Medicaid resources for abortions deemed medically important. A research revealed in 2017 in the journal Obstetrics & Gynecology located that states with Medicaid protection of medically required abortions experienced a diminished danger of intense maternal morbidity for that populace, 16{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} on average, as opposed with states without the need of that protection.

Montana’s proposed adjustments are extra restrictive than the guidelines in lots of of the other states that make it possible for medically essential Medicaid abortions. At least nine states that use condition money to shell out for Medicaid abortions do not call for overall health providers to report the instances for an abortion, according to a 2019 U.S. Govt Accountability Business office report on point out compliance with abortion coverage regulations. For illustration, California’s Medi-Cal application does not have to have any clinical justification for abortions, and requires preauthorization only when the affected individual wants to be hospitalized.

Most of the states that permit medically needed Medicaid abortions, like Montana, are beneath courtroom orders to fund the treatment as they would other general health providers for small-earnings men and women.

Montana’s coverage is tethered to a 1995 courtroom circumstance that determined the state’s Medicaid method was recognized to supply “necessary health-related services” and the state just cannot exclude precise products and services. The state’s present eligibility regulations governing when a Medicaid-funded assistance is medically essential contain when a being pregnant would result in struggling, pain, or a physical deformity end result in sickness or infirmity or threaten to bring about or worsen a disability.

Under the health and fitness department’s new proposal, abortions would be decided to be medically needed only when a physician — not a different sort of supplier — certifies a client suffers from an ailment, problem, or personal injury that threatens their daily life or has a physical or psychological issue that would be “significantly aggravated” by pregnancy.

Elsewhere, courts have turned down some states’ tries to develop a definition for medically vital abortions aside from present Medicaid requirements as constitutional violations of equivalent defense. The Alaska Supreme Court docket struck down a 2013 condition legislation transforming the definition of a medically needed abortion for the reason that it addressed Medicaid beneficiaries who desired an abortion differently than these trying to get being pregnant-relevant strategies like a cesarean portion. And New Mexico’s higher court said in 1999 that a state rule restricting Medicaid-funded abortions applied diverse expectations of medical requirement to adult men and girls.

Montana opponents of the proposed alterations have threatened to sue if the regulations are adopted.

The state’s Medicaid software addresses a lot more than 153,900 females. From 2011 as a result of 2021, the system paid for 5,614 abortion methods, which commonly represents just about a third of all abortions in the point out, in accordance to point out details.

Now in Montana, doctors, health practitioner assistants, and state-of-the-art nurse practitioners are permitted to complete abortions. At minimum 1 Montana clinic that supplies abortions to Medicaid beneficiaries is operate by a nurse practitioner, All People Healthcare’s Helen Weems, who is suing the point out for attempting to block nurses from performing abortions.

Professional medical providers make the final decision of irrespective of whether an abortion is medically essential and post a kind afterward to the state wellbeing section.

The proposed transform would require companies to get condition acceptance right before doing an abortion, apart from in emergencies, and submit supporting files to justify the health care requirement. That preauthorization process would entail giving condition officers aspects of patients’ clinical background, this kind of as how several pregnancies a individual has experienced, the day of their previous menstrual cycle, irrespective of whether they smoke, the final results of any pregnancy exams, and irrespective of whether they have ever experienced behavioral wellness issues or material use disorders.

Martha Fuller, president and CEO of Prepared Parenthood of Montana, claimed suppliers by now obtain that information but never deliver it to the state. If they are expected to do so, she stated, that will have a chilling influence that might keep individuals from trying to find enable or lead them to pay for it out-of-pocket, if they can.

“Patients could really feel like, ‘Oh, and every thing that I convey to you, it’s heading to be now shared with my insurance company for the objective of them making a choice about regardless of whether or not I can have an abortion?’” Fuller explained.

In Montana, a patient trying to find an abortion by means of medication ordinarily gets that by means of nurse practitioners or doctor assistants instead of heading as a result of a person of the number of medical professionals who deliver that care by way of Medicaid, Fuller mentioned. She reported Medicaid clients would see for a longer time hold out situations if the new procedures are set in put as they wait around to see a physician. And ready for prior authorization would add to the time in limbo.

Telehealth helps provide accessibility amid scattered assets across the significant, rural condition, but Montana’s proposed alterations would need a bodily examination.

“Patients could possibly have to make a far more invasive course of action. They could have to travel. They have to just take much more time off from do the job,” Fuller claimed. “There will be individuals who will make a decision not to seek abortion care because they are unable to pay for it.”

Of the 1,418 abortions coated by Montana Medicaid in 2020 and 2021, point out data exhibit, 1 was performed because a person’s existence was in hazard. The rest have been done below the broader medically needed justification, with paperwork about individuals situations including a short rationalization for why the course of action was needed.

In accordance to the state’s proposed principles, the deficiency of supporting documentation for the strategies sales opportunities “the division to reasonably believe that that the Medicaid software is paying out for abortions that are not actually medically essential.”

In 2021, point out lawmakers handed and Gianforte signed 3 legislation proscribing abortions that a courtroom quickly blocked. The Montana Supreme Court upheld the injunction, arguing that the condition constitution’s right-to-privateness provision extends to abortion.

Gianforte and the state attorney typical have called on the Montana Supreme Court docket to strike down the two-ten years-previous ruling that tied abortion to the right to privateness. Republican lawmakers also have submitted a slew of abortion-associated bills in the legislative session, such as 1 proposal to exclude abortion from the state’s right-to-privateness protections.

KHN (Kaiser Overall health News) is a nationwide newsroom that makes in-depth journalism about wellness difficulties. With each other with Coverage Examination and Polling, KHN is one of the 3 big functioning courses at KFF (Kaiser Household Foundation). KFF is an endowed nonprofit business giving data on health and fitness troubles to the nation.

USE OUR Information

This story can be republished for no cost (details).