As States Seek to Limit Abortions, Montana Wants to Redefine What Is Medically Necessary

Montana’s conservative leaders, stymied by the courts from passing laws that impose major statewide abortion restrictions, find to tighten the state’s Medicaid regulations to make it additional challenging for lower-income women of all ages to receive abortions.

The Montana Department of Public Health and fitness and Human Products and services is proposing to outline when an abortion is medically necessary, limit who can execute these kinds of providers, and call for preauthorization for most situations.

The drive to transform the polices is borne of a belief by Republican Gov. Greg Gianforte’s administration that wellness providers are applying existing policies that enable Medicaid reimbursements to deal with abortions that aren’t medically needed.

“Taxpayers shouldn’t foot the monthly bill for elective abortions,” mentioned Gianforte spokesperson Brooke Stroyke.

Professional medical pros have claimed the expression “elective abortions” can misrepresent the advanced reasons somebody could look for an abortion and constrain wellbeing providers from making their best scientific judgment. Laurie Sobel, associate director of Women’s Health Policy at KFF, mentioned that seems to be the purpose of the Montana proposal’s aim on defining medically necessary abortions.

“It appears like Montana’s trying to curtail abortion obtain beneath Medicaid and acquire the conversation of ‘medically necessary’ absent from a physician and a affected individual,” Sobel said.

Democratic lawmakers and lots of wellness providers have said existing point out policies guarantee suppliers look at and document why an abortion is needed to guard a client.

Democratic state Rep. Ed Stafman, who a short while ago chaired the Youngsters, Families, Well being, and Human Providers Interim Committee, mentioned the proposed improvements are pointless simply because the point out presently complies with federal Medicaid rules on abortion.

“It’s obvious that this is portion of the anti-abortion agenda,” Stafman said.

States are barred from applying federal cash to pay for abortions other than in conditions of rape or incest, or when a woman’s lifetime is at threat. On the other hand, states have the option of making use of their have cash to let reimbursements below the joint condition-federal Medicaid application in other circumstances.

Montana is one of 16 states that permit the use of point out Medicaid resources for abortions deemed medically important. A research revealed in 2017 in the journal Obstetrics & Gynecology located that states with Medicaid protection of medically required abortions experienced a diminished danger of intense maternal morbidity for that populace, 16{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} on average, as opposed with states without the need of that protection.

Montana’s proposed adjustments are extra restrictive than the guidelines in lots of of the other states that make it possible for medically essential Medicaid abortions. At least nine states that use condition money to shell out for Medicaid abortions do not call for overall health providers to report the instances for an abortion, according to a 2019 U.S. Govt Accountability Business office report on point out compliance with abortion coverage regulations. For illustration, California’s Medi-Cal application does not have to have any clinical justification for abortions, and requires preauthorization only when the affected individual wants to be hospitalized.

Most of the states that permit medically needed Medicaid abortions, like Montana, are beneath courtroom orders to fund the treatment as they would other general health providers for small-earnings men and women.

Montana’s coverage is tethered to a 1995 courtroom circumstance that determined the state’s Medicaid method was recognized to supply “necessary health-related services” and the state just cannot exclude precise products and services. The state’s present eligibility regulations governing when a Medicaid-funded assistance is medically essential contain when a being pregnant would result in struggling, pain, or a physical deformity end result in sickness or infirmity or threaten to bring about or worsen a disability.

Under the health and fitness department’s new proposal, abortions would be decided to be medically needed only when a physician — not a different sort of supplier — certifies a client suffers from an ailment, problem, or personal injury that threatens their daily life or has a physical or psychological issue that would be “significantly aggravated” by pregnancy.

Elsewhere, courts have turned down some states’ tries to develop a definition for medically vital abortions aside from present Medicaid requirements as constitutional violations of equivalent defense. The Alaska Supreme Court docket struck down a 2013 condition legislation transforming the definition of a medically needed abortion for the reason that it addressed Medicaid beneficiaries who desired an abortion differently than these trying to get being pregnant-relevant strategies like a cesarean portion. And New Mexico’s higher court said in 1999 that a state rule restricting Medicaid-funded abortions applied diverse expectations of medical requirement to adult men and girls.

Montana opponents of the proposed alterations have threatened to sue if the regulations are adopted.

The state’s Medicaid software addresses a lot more than 153,900 females. From 2011 as a result of 2021, the system paid for 5,614 abortion methods, which commonly represents just about a third of all abortions in the point out, in accordance to point out details.

Now in Montana, doctors, health practitioner assistants, and state-of-the-art nurse practitioners are permitted to complete abortions. At minimum 1 Montana clinic that supplies abortions to Medicaid beneficiaries is operate by a nurse practitioner, All People Healthcare’s Helen Weems, who is suing the point out for attempting to block nurses from performing abortions.

Professional medical providers make the final decision of irrespective of whether an abortion is medically essential and post a kind afterward to the state wellbeing section.

The proposed transform would require companies to get condition acceptance right before doing an abortion, apart from in emergencies, and submit supporting files to justify the health care requirement. That preauthorization process would entail giving condition officers aspects of patients’ clinical background, this kind of as how several pregnancies a individual has experienced, the day of their previous menstrual cycle, irrespective of whether they smoke, the final results of any pregnancy exams, and irrespective of whether they have ever experienced behavioral wellness issues or material use disorders.

Martha Fuller, president and CEO of Prepared Parenthood of Montana, claimed suppliers by now obtain that information but never deliver it to the state. If they are expected to do so, she stated, that will have a chilling influence that might keep individuals from trying to find enable or lead them to pay for it out-of-pocket, if they can.

“Patients could really feel like, ‘Oh, and every thing that I convey to you, it’s heading to be now shared with my insurance company for the objective of them making a choice about regardless of whether or not I can have an abortion?’” Fuller explained.

In Montana, a patient trying to find an abortion by means of medication ordinarily gets that by means of nurse practitioners or doctor assistants instead of heading as a result of a person of the number of medical professionals who deliver that care by way of Medicaid, Fuller mentioned. She reported Medicaid clients would see for a longer time hold out situations if the new procedures are set in put as they wait around to see a physician. And ready for prior authorization would add to the time in limbo.

Telehealth helps provide accessibility amid scattered assets across the significant, rural condition, but Montana’s proposed alterations would need a bodily examination.

“Patients could possibly have to make a far more invasive course of action. They could have to travel. They have to just take much more time off from do the job,” Fuller claimed. “There will be individuals who will make a decision not to seek abortion care because they are unable to pay for it.”

Of the 1,418 abortions coated by Montana Medicaid in 2020 and 2021, point out data exhibit, 1 was performed because a person’s existence was in hazard. The rest have been done below the broader medically needed justification, with paperwork about individuals situations including a short rationalization for why the course of action was needed.

In accordance to the state’s proposed principles, the deficiency of supporting documentation for the strategies sales opportunities “the division to reasonably believe that that the Medicaid software is paying out for abortions that are not actually medically essential.”

In 2021, point out lawmakers handed and Gianforte signed 3 legislation proscribing abortions that a courtroom quickly blocked. The Montana Supreme Court upheld the injunction, arguing that the condition constitution’s right-to-privateness provision extends to abortion.

Gianforte and the state attorney typical have called on the Montana Supreme Court docket to strike down the two-ten years-previous ruling that tied abortion to the right to privateness. Republican lawmakers also have submitted a slew of abortion-associated bills in the legislative session, such as 1 proposal to exclude abortion from the state’s right-to-privateness protections.

KHN (Kaiser Overall health News) is a nationwide newsroom that makes in-depth journalism about wellness difficulties. With each other with Coverage Examination and Polling, KHN is one of the 3 big functioning courses at KFF (Kaiser Household Foundation). KFF is an endowed nonprofit business giving data on health and fitness troubles to the nation.

USE OUR Information

This story can be republished for no cost (details).
Honoris United Universities Achieves International Recognition for Medical Research

Honoris United Universities Achieves International Recognition for Medical Research

Investigation from the revolutionary Honoris Medical Simulation Middle in Tunis was introduced at the Global Assembly on Simulation in Healthcare in Orlando, Usa

We continue to give distinctive obtain to a depth and breadth of cutting-edge simulation expert services that have not been obtainable right before on a pan-regional level”

— Professor Chadli Dziri MD, Director of the Honoris MSC

TUNIS, TUNISIA, January 24, 2023 /EINPresswire.com/ — Honoris United Universities (HUU) attended the world’s premier meeting committed to innovation in the field of health care simulation (IMSH 2023). The Honoris Professional medical Simulation Heart in Tunis, Tunisia presented the results of a randomized managed trial in professional medical simulation carried out at its planet-class facility.

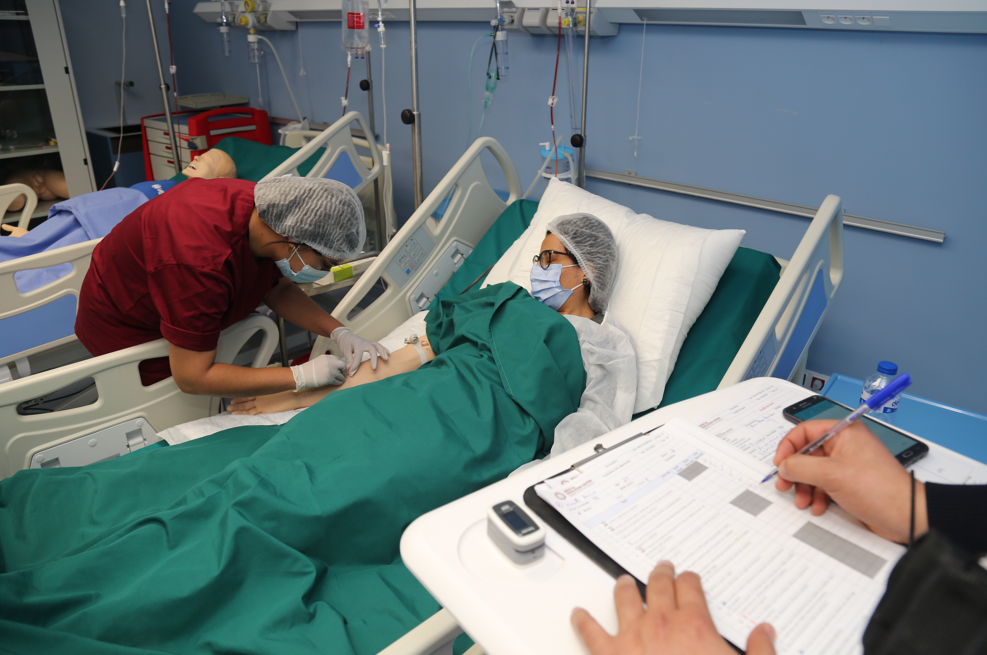
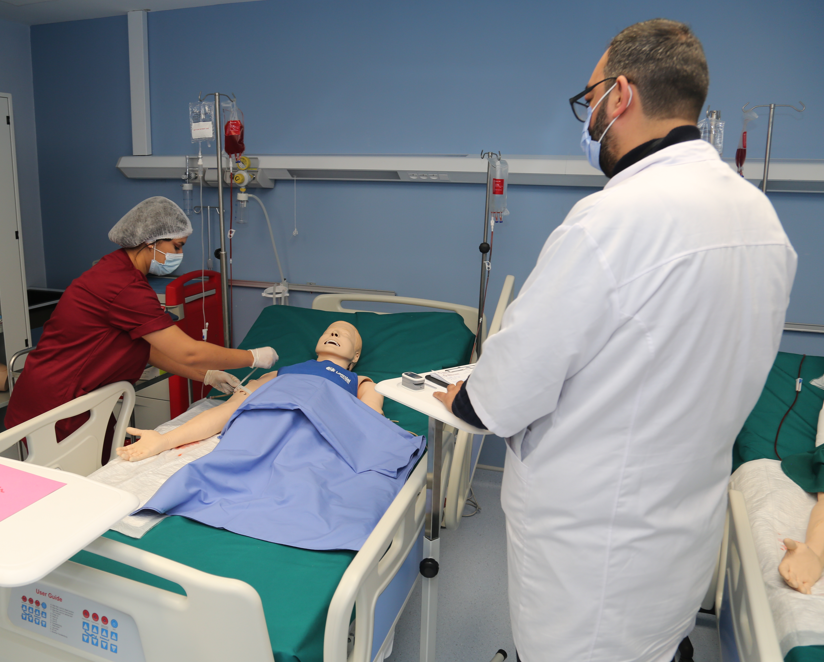
Led by the Culture for Simulation in Healthcare (SSH), the Global Meeting on Simulation in Healthcare (IMSH) is the largest scientific conference devoted to the most up-to-date innovations and most effective techniques in health-related simulation. Chadli DZIRI, MD, FACS, Professor Emeritus of Standard Operation at the Faculty of Medication of Tunis – Tunis El Manar University, Director of the Honoris Medical Simulation Middle, Fellow of the American School of Surgeons, and Member of the Board of Administrators of the American Journal of Surgical treatment, presented at the summit the effects of a randomized controlled demo involving additional than 170 2nd-calendar year Honoris well being university nursing learners, concentrating on health-related pedagogy and evaluating two education approaches: LFS (model) low-fidelity simulation as opposed to standardized individual schooling (SP) for peripheral venous line placement. The abstract of the cross over randomized trial was selected by the SSH organizers. The research protocol has been registered on the Pan African Clinical Demo Registry web site: PACTR202111766112898.

Established in 2018, the cutting-edge Honoris Healthcare Simulation Centre (MSC) is found in the coronary heart of Tunis. It was formulated in coordination with worldwide authorities and utilizing innovative technologies. In 2020, the MSC was a person of the initially centers in Africa to be accredited by SSH: one particular of three accredited facilities among eleven on the continent. The centre provides 4 simulation models like model systems in a hospital setting, state of affairs-primarily based simulations, actor-centered simulations, and cutting-edge virtual truth systems. Far more than 5,000 pupils, 400 health care industry experts, and far more than 60 obstetricians from Northern and Sub-Saharan Africa have been skilled at this facility.

Professor Chadli Dziri MD, Director of the Honoris MSC in Tunis, commented, “Our existence at this year’s IMSH was a wonderful chance to share our finest practice and findings from the use of our know-how and innovative strategies, constantly screening and learning to strengthen each learner and individual results. I am happy that the Honoris Health care Simulation Centre is noticed as a reference issue for international professional medical simulation as we continue on to provide one of a kind obtain to a depth and breadth of slicing-edge simulation services that have not been obtainable in advance of on a pan-regional degree.”

Provided its special network in instruction in Africa, Honoris is fully commited to continuing publishing educational analysis from its facilities of excellence, significantly in the crucial employability sectors for Africa together with well being sciences, organization, and engineering & IT. By encouraging analysis collaborations throughout establishments in numerous markets, Honoris can harness the collective power of its pan-African system and apply health tech remedies and immersive finding out technologies to advance training and finding out in its hubs in Tunisia, Morocco, Nigeria, and South Africa. To continually boost results for its student population of more than 40 nationalities, Honoris plans to broaden its clinical simulation providing to Nigeria and Morocco in the small expression.

Each 12 months, IMSH offers the instruments and resources health care specialists need to advance their abilities, impact change in supply programs and follow, and, in the long run, strengthen individual security. With in excess of 4,000 attendees in 2022, the function welcomes attendees from all about the earth like scientists, academics, medical professionals, and innovators for networking, arms-on workshops, plenary speakers, 300 education periods, and an exhibit hall for the most recent solutions and expert services in the sector.

For Media Info
James Deacon, Communications Manager, Honoris United Universities
jdeacon@honoris.web

James Deacon
Honoris United Universities
email us in this article

Medicaid: What to Watch in 2023

As 2023 kicks off, a number of issues are at play that could affect coverage and financing under Medicaid, the primary program providing comprehensive health and long-term care coverage to low-income Americans. The Consolidated Appropriations Act, passed in December 2022, ends the Medicaid continuous enrollment provision on March 31, 2023 with a phase-down in enhanced federal matching funds. The unwinding of this provision, as well as the trajectory of the pandemic and the economy, will have implications for Medicaid enrollees, providers, managed care plans, and the states that operate these programs. A divided Congress will make it difficult to pass federal legislation, and while the Administration is expected to continue to use existing authority to improve coverage, access, and health equity, limited action at the federal level will push even more policy focus to the states. The first glimpse of state policy priorities will be revealed in Governors’ state of the state addresses and proposed budgets. Within this context, this issue brief examines key issues to watch in Medicaid in 2023.

Medicaid Coverage and Financing

The Medicaid continuous enrollment provision in place during the pandemic has increased enrollment and reduced the uninsured rate, but will end in March 2023. Provisions in the Families First Coronavirus Response Act (FFCRA) required states to ensure continuous enrollment in Medicaid in exchange for enhanced federal matching funds during the Public Health Emergency (PHE). Largely due to these policies, enrollment in Medicaid and the Children’s Health Insurance Program (CHIP) grew to 91 million in September 2022, an increase of 27.9{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} from February 2020 (prior to the pandemic). KFF estimates that through federal fiscal year 2022, states received more than double the amount in federal fiscal relief relative to the costs of enrollment due to the continuous enrollment provision, with some variation across states. The Consolidated Appropriations Act ends the continuous enrollment provision on March 31, 2023, and phases down the enhanced federal Medicaid matching funds through December 2023. States can resume disenrollments beginning April 1 but must meet certain eligibility and reporting requirements to continue to be eligible for enhanced funding. An estimated 5 to 15 million people could lose Medicaid coverage during unwinding and how states manage the process could affect how many people are able to maintain coverage.

Debate about Medicaid expansion will shift back to the states. Democrats in Congress last year discussed a federal option to fill in the Medicaid coverage gap but ultimately did not pass it, and such an approach is now highly unlikely with divided control in Washington. The American Rescue Plan Act (ARPA) included a two-year fiscal incentive to encourage remaining “non-expansion” states to newly adopt the Affordable Care Act (ACA) Medicaid expansion. Over  2 million individuals living in the 11 states that have not adopted the (ACA Medicaid expansion fall into the “coverage gap”). These individuals do not qualify for Medicaid (as their income exceeds Medicaid eligibility limits in their respective states) but have incomes below poverty, making them ineligible for premium subsidies in the ACA Marketplace. A KFF analysis shows that all non-expansion states would see a net fiscal benefit from the ARPA incentive for two years if they adopt the expansion. The ARPA federal incentive reignited discussion around Medicaid expansion in a few non-expansion states during the last state legislative session. Notably, every state that has adopted expansion since 2019 has done so not through legislative or executive processes, but as a result of a successful ballot initiative. Most recently, South Dakota became the 40th state to expand Medicaid after voters approved a ballot question in November 2022. Although expansion ballot initiatives have been successful in all seven states where they have gone to voters (Idaho, Maine, Missouri, Nebraska, Oklahoma, and Utah), most of the remaining non-expansion states do not have ballot initiative processes. North Carolina may be the state most likely to expand Medicaid next given how far efforts advanced last year, with active efforts in Kansas and Wyoming as well.

Some states and the Administration are expected to continue to implement incremental policies to expand coverage. ARPA included an option, made permanent in the Consolidated Appropriations Act, to allow states to extend postpartum coverage from 60 days to 12 months. Under current law, after the 60 days of postpartum coverage, many people who qualify for pregnancy-related Medicaid  lose that coverage because Medicaid eligibility levels for parents are much lower than for pregnant people in most states, and especially in non-expansion states. As of January 2023, more than two-thirds of the states have taken steps to extend postpartum coverage. The Consolidated Appropriations Act also included a requirement for all states to implement 12 months of continuous coverage for children. In addition, Oregon received waiver approval to provide continuous eligibility for children from birth to age 6 and 2 years of continuous eligibility for all enrollees ages 6 and up, including adults; other states are seeking similar waivers for multi-year continuous eligibility. KFF analysis shows that for children, continuous eligibility policies help to provide coverage stability. Finally, the Administration released a proposed regulation designed to make it easier for individuals to obtain and retain coverage.

New state and federal attention to Medicaid financing could emerge in 2023. Medicaid financing is shared by the federal government and the states. Consequently, economic factors that affect state revenues including inflation, supply chain issues, and declining labor force participation rates, along with phase-down of the enhanced FMAP tied to the end of the continuous enrollment provision will have fiscal implications for states. In our annual state survey, states noted that inflation and workforce shortages were driving higher labor costs and pressure from providers for rate increases. Many states use reimbursement methodologies for some provider types, such as nursing facilities, that may automatically adjust for inflation. In addition, at the federal level the House of Representatives is likely to focus on measures to reduce the federal deficit and, while unlikely to pass in the Senate, proposals to limit federal spending for Medicaid could be debated again in Congress.

What to Watch:

  • What will happen to Medicaid enrollment during the unwinding of the continuous enrollment provision? How will changes vary across states? How many people losing Medicaid coverage will transition to other sources of insurance like the Affordable Care Act marketplaces, and what will happen to the number of uninsured?
  • Will any additional states implement Medicaid expansion or other coverage expansions like 12-month postpartum coverage?
  • How will administrative actions, including oversight of the unwinding of the continuous enrollment provision, waiver approvals, and new regulations contribute to changes in coverage?
  • How will broader economic factors, like inflation, affect state financing of Medicaid and will Congress debate broader proposals to cap federal Medicaid spending?

Access and Health Equity

Capitated managed care remains the predominant delivery system for Medicaid in most states. More than three-quarters of states that contract with MCOs (35 of 41) reported that 75{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} or more of their Medicaid beneficiaries were enrolled in MCOs as of July 1, 2022. Several states have recently implemented Medicaid managed care programs. Beginning July 1, 2021, North Carolina implemented its first MCO program, enrolling more than 1.8 million Medicaid beneficiaries in MCOs as of December 2022. Missouri implemented the ACA Medicaid expansion in October 2021, enrolling all expansion adults in Medicaid MCOs, and Oklahoma expects to implement capitated, comprehensive Medicaid managed care in October 2023. State managed care contracts vary widely in the populations required to enroll, the services covered, and the quality and performance incentives and penalties employed. Five multi-state, for-profit “parent” firms – Centene, UnitedHealth Group, Anthem, Aetna/CVS, and Molina – each have Medicaid MCOs in 12 or more states and account for half of all Medicaid MCO enrollment. MCOs are expected to play a large role in helping enrollees maintain coverage during the unwinding of the continuous enrollment provision. The Administration is expected to release revised regulations about Medicaid managed care and assuring access in Medicaid in the Spring of 2023.

In response to the pandemic, all states took action to expand coverage and access to telehealth in Medicaid, particularly for behavioral health services. In particular, nearly all states added or expanded audio-only telehealth coverage. These policy changes contributed to high telehealth utilization by Medicaid enrollees during the pandemic, overall and especially for behavioral health services. The rapid expansion of Medicaid telehealth policies and utilization has prompted state and federal questions about the quality of services delivered via telehealth. Most states have implemented or are planning initiatives to assess telehealth quality, though many states report ongoing considerations and uncertainty over how to effectively evaluate quality. States also report actions to address other telehealth challenges, including access to technology and broadband, program integrity, outreach and education, and equity. Most states have or plan to adopt permanent Medicaid telehealth expansions that will remain in place after the pandemic, including expansions of allowable modalities, services, and providers. At the same time, some states are considering guardrails on such policies, particularly for audio-only telehealth.

Beyond telehealth, many states are taking steps to expand access to behavioral health services as the pandemic has heightened demand for these services. Nine in ten Americans believe the nation is in the midst of a mental health crisis. Behavioral health conditions (i.e., mental health and substance use disorders) are more prevalent in Medicaid enrollees compared to people with other coverage, with data from 2020 showing that approximately 39{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of Medicaid enrollees were living with a mental health or substance use disorder. States have been expanding behavioral health benefits and access to care, including by adopting strategies to bolster the behavioral health workforce. These state efforts track with continued activity at the federal level: the Consolidated Appropriations Act and the 2022 Bipartisan Safer Communities Act included an array of provisions to expand access and funding for behavioral health, such as provisions to require guidance on expanding Medicaid-covered mental health services in schools, expand Certified Community Behavioral Health Clinics (CCBHC), fund new psychiatry residency positions, and eliminate administrative requirements to prescribe buprenorphine.

States and the Administration have identified advancing health equity as an important priority for the Medicaid program. The pandemic exacerbated longstanding racial and ethnic disparities in health and health care. Medicaid policies that could help address health equity include closing the “coverage gap” for adults in non-expansion states; increasing coverage among those eligible but not enrolled; and expanding benefits such as pregnancy and postpartum services, housing and housing-related supports, and community health worker services. High-quality, comprehensive data are essential for identifying and addressing health disparities and measuring progress over time and the majority of states are implementing strategies to improve race, ethnicity, and language (REL) data completeness. States are also using MCO financial quality incentives (e.g., performance bonuses, withholds) tied to health equity-related performance goals and other MCO contract requirements to advance health equity. Other reported state Medicaid initiatives to reduce racial health disparities include outreach to underserved populations, increasing cultural competency, and establishing departments and dedicated staff positions focused on promoting equity. In addition, states have received or are seeking Section 1115 waivers that aim to advance equity.

States and the Administration are implementing strategies to leverage Medicaid to address social determinants of health (SDOH) through managed care and Section 1115 waivers. The Biden Administration has encouraged states to propose waivers that expand coverage, reduce health disparities, and/or advance “whole-person care,” including by addressing health-related social needs (HRSN). Recent waivers approved in four states (AR, AZ, MA, and OR) include HRSN services to address food insecurity and/or housing instability for targeted populations. Additionally, following the approval of a California proposal to use “in lieu of” services (ILOS) to offer a menu of health-related services through managed care authority, the Centers for Medicare and Medicaid Services (CMS) recently released additional guidance on the use of in lieu of services and settings in Medicaid managed care to reduce health disparities and address unmet HRSN (such as housing instability and nutrition insecurity).

What to watch?

  • How effective will state and administration efforts to leverage Medicaid be in addressing SDOH and reducing health disparities? How will states use authorities including Section 1115 and managed care to pursue these goals?
  • What kinds of permanent telehealth expansions and/or guardrails will state Medicaid agencies adopt, and how will these policy changes be informed by data analyses, federal guidance, and cost concerns?
  • Will the Administration release new guidance in 2023 to address access to care and what provisions will be included in the anticipated access and revised managed care regulations?
  • Will Congress pass additional legislation and / or will states take additional actions to improve access to and funding for behavioral health services?

Enrollment and Access Among People Eligible for Medicaid through Age or Disability

The new proposed rule on eligibility and enrollment could increase enrollment among all Medicaid eligibility groups, but especially among seniors and people with disabilities. A proposed rule designed to make it easier for people to obtain and maintain coverage in Medicaid and CHIP includes provisions to simplify the enrollment and renewal processes for seniors and people with disabilities by applying many of the ACA’s simplified eligibility processes for children and other adult eligibility groups to these groups. There would also be simplified enrollment procedures for people who receive supplemental security income and people who are enrolled in Medicare but eligible for Medicaid coverage of Medicare premiums. KFF analysis finds that over one-third of Medicare-Medicaid enrollees lose Medicaid coverage within one year of their initial enrollment, which is one of the reasons for the proposed changes. CMS expects that the rule would increase Medicaid enrollment by nearly 3 million full-year equivalents, with seniors and people with disabilities accounting for over half of that total.

Staff and residents at long-term care facilities have been disproportionately affected by the pandemic. Over one-fifth of all deaths from COVID-19 were among residents and staff in long-term care facilities as of June 12, 2022. Although initial vaccination rates were high and the death rate among nursing facility residents and staff dropped, take-up of boosters and of the new bivalent booster has been much lower. Going into the 2022-2023 winter period, fewer than half of residents and one quarter of staff were up-to-date with their vaccinations, which may result in higher death rates moving forward. Compounding the challenges with COVID-19 illness is the ongoing workforce shortage for long-term care facilities. Whereas employment in most health care sectors has rebounded from the sharp drop in March 2020, employment in long-term care facilities remains well-below pre-pandemic levels.

The pandemic also highlighted workforce shortages and unmet need among people who use long-term services and supports (LTSS) delivered in home and community settings (HCBS). In a KFF survey of HCBS programs, nearly all states reported that workforce shortages were the number one impact of the COVID-19 pandemic on HCBS services and 44 states reported that at least one HCBS provider permanently closed. Virtually all states increased payment rates in response, but some of those increases are temporary rather than permanent. Many changes to HCBS programs relied on temporary funding through the ARPA or temporary authorities available during the PHE. Policymakers of both parties have called for additional and longer-term changes to HCBS including eliminating waiting lists for services, increasing opportunities for family members to be paid caregivers, enabling more people to live in their homes as they age, and permanently increasing wages for all HCBS providers.

There is bipartisan interest in improving the coordination for Medicare-Medicaid enrollees (also known as “dual eligibles”). People who are enrolled in both Medicare and Medicaid tend to have significant health and functional needs and higher health care spending than people with only Medicare or Medicaid. Policymakers have expressed interest in improving the coordination between Medicare and Medicaid with the goals of improved health outcomes and, possibly, reduced health care spending. Most recently, a bipartisan group of senators released a request for information, soliciting input from patients, providers, payors, and other stakeholders.

What to Watch:

  • How will the final eligibility and enrollment rule increase enrollment for seniors and people with disabilities?
  • Will nursing facility residents and staff be at increased risk of death as the virus evolves and immunity wanes among people who are vaccinated but not up to date? What efforts will emerge to improve rates of booster take-up?
  • How will the end of ARPA funding and PHE authorities affect access to HCBS?
  • Will bipartisan interest in improving the coordination between Medicare and Medicaid result in new legislation addressing Medicare-Medicare enrollees and their access to care?

Medical Writing for Medical Devices Training Course (March 15-16, 2023)

Dublin, Jan. 24, 2023 (Globe NEWSWIRE) — The

“Medical Crafting for Healthcare Units Coaching System”

convention has been extra to

ResearchAndMarkets.com’s

giving.

This complete program has been developed to deliver you with a extensive knowledge of the necessary aspects of health-related composing, with a certain concentrate on clinical units.

Composing for healthcare gadgets has its personal specific skill established and, with important regulatory alterations in the sector, all those people associated in health care creating facial area a challenge to ensure they have the necessary experience and sources to fulfil the requirements of the new regulation.

Underneath the steerage of our pro trainers, you will master how to prepare a doc that is linguistically and stylistically appropriate and have an understanding of the powerful use of visual features these types of as tables, graphs and movement charts. The programme will analyze the content material and construction of the CER – an integral aspect of the submission system, and assure that you are entirely aware of what a Notified Entire body is seeking for in your medical evaluation.

Realistic exercise routines and discussion will consolidate finding out, and beneficial recommendations and strategies from gurus in the field of health-related crafting and health-related products will boost your expertise.


Who Should really Show up at:

  • Health care product pros accountable for preparing, creating and finishing a CER
  • Health-related writers manufacturing stories for health care machine suppliers
  • Regulatory affairs personnel concerned in making ready scientific documentation
  • Clinical device personnel who have to have a basic understanding of what is essential when drafting scientific studies for their solutions
  • Deal investigate organisations (CROs)
  • R&D professionals


Critical Matters Included:


Overview of creating and editing documents

  • Substantive and specialized factors
  • Thinking of logic, text move, wordiness and accuracy
  • Seeking at the information this sort of as language editing, abbreviations and acronyms
  • Getting ready a very clear information for the meant reader


Regulations applicable to the scientific analysis of a professional medical gadget

  • Introduction to the European Health care Unit Regulation (MDR)
  • Guidance documents for clinical evaluations – what is demanded?
  • Notified Human body anticipations


Composing regulatory paperwork

  • Do distinct audiences and documents require distinctive strategies?
  • Corresponding with the authorities


Systematic literature lookups for the CER

  • Efficient look for strategies
  • Determining on what supply facts is essential
  • Condition of the art


Features of English

  • Typical errors in English that should be avoided
  • Short overview of key punctuation details affecting meaning and readability


Improving upon readability – be form to your reader

  • Structuring texts
  • In terms of language, how great do regulatory documents require to be?


Framework and content material of the CER

  • What is necessary to satisfy the regulation?
  • Contents of a CER
  • Conducting a scientific evaluation


CER case study workshop

  • Deciding on what resource knowledge is required


Introduction to other health-related device scientific regulatory paperwork

  • PMCF program and report
  • Scientific investigation approach and report


Proofreading essentials

  • Ultimate checks – not just a spell check out
  • Practicalities, suggestions and instruments


Key just take-property messages


Speakers

Janette Benaddi

Director of Scientific & Consulting Europe

NAMSA

Barbara Grossman

Biochemist

Hawkeye Health-related Restricted

For far more data about this convention take a look at

https://www.researchandmarkets.com/r/f1nhxj

Get hold of: ResearchAndMarkets.com 
         Laura Wooden,Senior Press Manager 
         push@researchandmarkets.com
         For E.S.T Workplace Hrs Phone 1-917-300-0470 
         For U.S./ CAN Toll Totally free Connect with 1-800-526-8630 
         For GMT Business office Hours Connect with +353-1-416-8900 


Medical Writing for Medical Devices Training Course (March 15-16, 2023)

These 4 Healthy Eating Patterns May Led to a Longer Life, Study Finds

Your nutritional sample may well assistance predict how extensive you live. This is the conclusion from a new research released in The Journal of the American Clinical Affiliation evaluating eating plan good quality and mortality. The examine uncovered that persons that consumed a a lot more nutrient-dense diet program had been fewer most likely to die early.

The feeding on behavior of 119,315 folks (75,230 girls and 44,085 adult men) from the Nurses’ Health Study and the Wellbeing Industry experts Stick to-Up Examine had been assessed more than 36 decades. In the course of that time body, they evaluated adherence and results related to four distinctive nutritional designs, all of which adhere in some capability to the United States Dietary Tips for Americans.

The four having patterns analyzed ended up:

  • The Wholesome Consuming Index 2015 (HEI), which measures diet excellent and adherence and makes use of guidelines from the Dietary Tips for Americans in its scoring assessment.
  • The Alternate Healthy Consuming Index (AHEI), which was designed by scientists at the Harvard T.H. Chan School of Community Health as an choice to the unique HEI. Like the HEI, it provides scoring but focuses more on minimizing serious sickness danger.
  • The Alternate Mediterranean Diet program (AMED), which measures adaptation to the Mediterranean diet plan principles.
  • The Healthful Plant-based Food plan Index (HPDI), which measures adherence to a healthier plant-dependent diet plan.

The examine found there are various ways to adhere to a nutritious diet regime

Folks with the best adherence to at least 1 of the much healthier ingesting indexes experienced the most affordable threat of death in contrast with people with the most affordable adherence. This outcome was found among all 4 balanced feeding on indexes. Additionally, this end result was consistent among multiple racial and ethnic groups. It was also noticed in a dose-dependent manner (the better the rating, the reduced the risk for early loss of life from cardiovascular disease, respiratory disorder, and cancer). Higher adherence scores for AMED and AHEI were being even further linked with a lessen risk of neurodegenerative illness mortality.

There were being quite a few critical takeaways from the research. Very first, it emphasised that there are various means to adhere to a much healthier way of having. Considering the fact that there is no “one size fits all” food plan, it demonstrated that distinct nutritional designs could be tailored to any ethnic or own desire. Next, there were many similarities concerning the four ingesting patterns. For case in point, all eating practices were being nutrient-dense, providing considerable natural vitamins and minerals. They were also far more slanted to far more plant-dependent techniques. Dr. Frank Hu, chair of office of nourishment and epidemiology at Harvard T.H. Chan Faculty of Public Overall health, was the study’s lead creator. He tells Currently.com, “Despite the fact that these diet programs differ in some facets, they all include high quantities of healthy plant food items these as fruits, vegetables, full grains, nuts, and legumes, and reduced amounts of refined grains, added sugars, sodium, and purple and processed meats.”

For a for a longer period everyday living, target on these 5 dietary behavior:

1. Focus on fiber

Just one of the finest methods to consume additional crops is to concentrate on receiving much more fiber. A 2019 systematic critique and meta-assessment in the journal Lancet found that ample fiber ingestion (amongst 25g to 29g for every day) was also linked with a reduction in danger of all will cause and decreases in heart disorder, Sort 2 diabetic issues, and colorectal cancer.

2. Nosh on nuts

Nut use was emphasized in all four eating patterns in the examine. Nuts are substantial in wholesome fat, which may help maximize satiety and fullness, a essential part of excess weight management. They have also been connected with greater mind overall health and could lower the danger of coronary heart condition.

3. Get colorful

Coloration is important in the plant entire world and will come from compounds known as phytonutrients that give both of those hue and benefit to the plant. Studies demonstrate that consuming colorful fruits and vegetables can also direct to a lengthier existence.

4. Opt for plant and marine sources of protein

Beans, legumes and fish had been highlighted in several of the eating styles. The AMED sample, for illustration, encouraged the usage of fatty fish, like salmon, that can supply plentiful quantities of omega-3 fatty acids. In distinction, beans and legumes present fiber in addition to protein.

5. Find flexibility

The analyze shown that healthful taking in can be personalized to the particular person — and that pursuing various methods within just the popular themes could guide to important health advantages. “In get for a person to adhere to a nutritious diet program very long-phrase, 1 demands to enjoy it. So it is significant for people today to adapt these balanced ingesting styles to their personal food stuff and cultural choices. Also, 1 does not want to adhere to only just one dietary approach for their total daily life. To boost wide variety and adherence, one particular can switch between these a variety of wholesome diets or produce their individual flexitarian food plan. Even so, the core healthy taking in principles should continue being the very same: Try to eat far more minimally-processed plant foods these types of as fruits, veggies, nuts, whole grains, and legumes take in less purple meat and ultra-processed foods substantial in sugar, sodium, and refined starch,” Hu points out.

If overhauling your nutritional sample would seem overpowering, take into account this — toddler ways will go even more than no movement at all. Hu claims that many nutritious dietary patterns have been linked with, not only a for a longer time life, but a reduction in persistent condition danger complications as perfectly. Hu points out that, for case in point, “a bigger adherence to the Mediterranean diet plan lowers the chance of cardiovascular issues among individuals with diabetic issues.” Also, balanced consuming designs have been affiliated with much better survival amongst men and women with breast or colorectal most cancers.”

As Hu claims, “it’s never ever way too late to undertake a healthier diet program.”

WHO launches funding appeal to help a record number of people in complex, intersecting health emergencies

WHO is launching its 2023 health and fitness crisis attractiveness nowadays for US$ 2.54 billion to deliver support to tens of millions of men and women close to the entire world going through health and fitness emergencies. The amount of persons in require of humanitarian reduction has amplified by practically a quarter in contrast to 2022, to a history 339 million.

At the moment, WHO is responding to an unparalleled quantity of intersecting health emergencies: local climate improve-associated disasters these as flooding in Pakistan and foodstuff insecurity across the Sahel and in the increased Horn of Africa the war in Ukraine and the well being impact of conflict in Yemen, Afghanistan, Syria and northern Ethiopia – all of these emergencies overlapping with the health procedure disruptions triggered by the COVID-19 pandemic and outbreaks of measles, cholera, and other killers.

“This unparalleled convergence of crises needs an unprecedented reaction,” said Dr Tedros Adhanom Ghebreyesus, WHO Director-Normal. “More men and women than ever right before facial area the imminent possibility of disease and starvation and require assistance now. The world are not able to glance away and hope these crises resolve by themselves. I urge donors to be generous and assist WHO to preserve lives, avoid the spread of disease within just and throughout borders, and help communities as they rebuild.”

WHO is now responding to 54 wellbeing crises all around the entire world, 11 of which are classified as Quality 3, WHO’s optimum amount of crisis, necessitating a response at all 3 amounts of the corporation. As it is typically the circumstance, the most vulnerable are the worst hit.

In 2022, WHO delivered medicines, other supplies, training for doctors and other health and fitness employees, vaccines, enhanced condition surveillance, mobile clinics, mental overall health aid, maternal wellbeing consultations and a lot more. WHO delivers charge-productive, significant-effects responses that protect health, lives and livelihoods. Each and every US$ 1 invested in WHO generates at least US$ 35 in return on investment decision*.

WHO responds to well being emergencies in shut collaboration with Member States, other UN agencies, non-governmental companies, civil culture businesses and other partners in the communities and across international locations and locations.

The charm will be launched at an function from WHO’s Headquarters in Geneva, hosted by WHO’s Director-Typical, Dr Tedros Adhanom Ghebreyesus. It will be webcast from this site, and on WHO’s YouTube channel, Twitter, LinkedIn.

Resources

Note to editors:

WHO is responding to Quality 3 well being emergencies in Afghanistan, the Democratic Republic of the Congo, the better Horn of Africa, Northern Ethiopia, Somalia, South Sudan, the Syrian Arab Republic, Ukraine, and Yemen. The COVID-19 pandemic and mpox (monkeypox) outbreaks are also Quality 3 emergencies. See extra about health emergencies.

*A Wholesome Return. Investment decision scenario for a sustainably financed WHO, May perhaps 2022.