Regulatory Horizons Council report on medical devices: government response

Executive summary

The Regulatory Horizons Council (RHC) report on medical devices comes at an opportune time. Following the UK’s withdrawal from the EU and the Medicines and Healthcare products Regulatory Authority’s (MHRA) consultation on the future regulation of medical devices, the government is well placed to take forward the report’s recommendations and deliver a world-leading regulatory framework.

This response addresses the report’s recommendations in 4 key areas:

1. Patient outcomes and safety

By building greater patient engagement into the regulatory framework and enhancing the reporting of safety risks, we will ensure a system that is centred on the needs and safety of patients.

2. International leadership and engagement

Positioning the MHRA as a world-leading regulator, the new framework will expand international engagement and establish the UK as a pioneer in the regulation of emerging technology, including software as a medical device and in-vitro diagnostics (IVD).

3. Investment in regulatory capacity

We will maximise the opportunities offered by the transition to UK Conformity Assessed (UKCA) marking – not only increasing the number of UK approved bodies to meet capacity, but also exploring opportunities to increase UK-based regulatory expertise.

4. Unlocking innovation and emerging technology

The MHRA is committed to supporting responsible innovation while minimising risk to patients and the public. Across government, we will continue to explore pathways to bring the most transformative emerging technologies to market and to the NHS, and attract investment in innovative devices.

Introduction

The RHC is an independent expert committee that identifies the implications of technological innovation, and provides government with impartial, expert advice on the regulatory reform required to support its rapid and safe introduction. The RHC is supported by civil servants from the Better Regulation Executive (BRE) in the Department for Business, Energy and Industrial Strategy (BEIS)

The RHC published its report on medical devices on 19 August 2021, in response to rising complexity of medical technology and the opportunities for global leadership that EU exit has enabled. It sought to answer the following question: ‘How can the UK encourage international investment and innovation and improve safety in the medical devices area through regulatory and non-regulatory changes?’. The RHC engaged with industry experts and across government, and commissioned evidence.

The government has considered each of the report’s 11 recommendations and this response focusses on the actions being taken in response.

This response builds on the government’s response to the MHRA’s consultation on the future regulation of medical devices, published on 26 June 2022, which confirms the direction of travel for medical devices regulation in the UK. Having left the EU, we have been given a substantive opportunity to update and improve the UK’s medical devices regulatory landscape, supporting the growth of the UK life sciences sector. Full details of the future regulatory framework for medical devices can be found in the government’s response and appropriate references are included in this document.

Summary of the government response to each of the report’s recommendations

Building a regulatory system for medical devices that works for patients

Recommendation 1

The regulation of medical devices should be centred on the needs of patients, informed by patients, record outcomes that matter to patients, and provide evaluations that are understandable to patients.

Government response – accept

The government recognises and supports the MHRA’s delivery plan 2021 to 2023 Putting patients first: a new era for our agency, which sets out the MHRA’s roadmap for the future, centred on better public and patient involvement throughout their work.

This delivery plan has initiated a substantial programme of work to:

  • improve how it listens and responds to patients and the public
  • develop a more responsive system for reporting adverse incidents
  • strengthen the evidence to support timely and robust decisions that protect patient safety

This emphasis has already had an impact on how the MHRA works with patients in tangible ways. For example, the MHRA actively engaged with patient representatives in the development of the policies for the future regulatory framework for medical devices, during the public consultation that ran in autumn 2021, with over 300 attendees joining a public engagement session in October 2021.

The MHRA will continue to actively engage stakeholders, including patient representatives, in a series of planned focus groups. The focus groups will commence in January 2023 and will meet regularly to provide guidance around the chapters of the government response. A series of one-to-one meetings with patient representatives is also planned and will feed into all focus groups to gather patient input across a total of 20 topics for the guidance and other support materials necessary to aid transition to the amended regulatory system.

The government will continue to monitor the impact of the MHRA’s delivery plan and ensure that patient-centred regulation becomes embedded in the MHRA’s ways of working.

Increasing capacity to address present needs and emerging opportunities

Recommendation 2

Strengthen and increase funding to the MHRA to significantly expand their capacity in medical devices, including in emerging technologies.

Government response – accept in principle

The government continues to support the appropriate funding required for the operation of the MHRA, taking into account all of its functions. The MHRA’s regulatory functions for medical devices are primarily funded by the Department of Health and Social Care (DHSC), with the remaining revenue from fees charged for services.

In August 2022, the MHRA launched a consultation on proposals for changes to their statutory fees. The proposals are intended to ensure the MHRA is adequately resourced, including in areas of technological progress in medical devices where increased resource is required.

Recommendation 3

Address bottlenecks in the approval of medical devices, notably the shortage of UK approved bodies for conformity assessment.

Government response – accept

The MHRA focuses on ensuring conformity assessments are carried out consistently and robustly by UK approved bodies (ABs), which must effectively assess medical devices to assure their safety, quality and performance. View a list of UK approved bodies for medical devices.

The MHRA is currently reviewing several applications from organisations that have applied for designation as a UK approved body (AB). The MHRA is also actively working with organisations that are preparing to apply for UK AB designation either through new applications or extending their existing scope for conformity assessment.

Further information on mitigations for bottlenecks in the approval of medical devices is detailed in the response to recommendation 4 below.

Recommendation 4

Prepare mitigations that supplement AB capacity to ensure supply of devices after transition to UKCA.

Government response – accept

The MHRA has been exploring options to mitigate AB capacity issues, and will continue to communicate with industry for views to ensure there is a smooth transition to any regulatory changes, recognising that the medical devices sector requires time to make changes.

To address anticipated challenges relating to AB capacity, the future regulatory framework for medical devices will set out the government’s plans for a phased introduction of the proposed requirements to ensure there is a considered approach to implementation. This will allow manufacturers to leverage certification under the existing UKCA and CE marking processes.

Devices that are UKCA marked under the existing UK regulations prior to the new regime taking effect will be permitted to continue to be placed onto the GB market for 3 years for general medical devices and 5 years for in-vitro diagnostic (IVD) medical devices or until their current certifications expire, whichever is sooner. This will allow for the upscaling of the approved body capacity.

Devices that are CE marked under EU legislation will be permitted similar transition timescales and these will run from 1 July 2024, when the new regime is planned to come into effect. For devices CE marked under the EU directives (former EU legislation), these timescales will be 5 years for IVD medical devices and 3 years for other medical devices, or until their certifications have expired, whichever is sooner. For devices CE marked under the new EU regulations (EU Medical Device Regulation (MDR) and In Vitro Diagnostic Regulation (IVDR)), it will be permitted to place these devices onto the GB market for up to 5 years from 1 July 2024.

It is not anticipated that an extension of this provision will be required, as the intervening period will be used to support an increase in AB capacity to ensure the UK has sufficient capacity to transition all medical devices to the UKCA marking system. The MHRA will also be working to build the UKCA marking for medical devices on a global standing.

These approaches have been designed specifically to alleviate pressure on ABs, given current capacity restraints. The phased implementation of the new regime has also been developed to prioritise patient safety and minimise the risk of critical supply issues, ensuring the continued safe supply of medical devices to the UK market.

International leadership and partnership in medical devices

Recommendation 5

Support the MHRA to increase UK visibility, international engagement and leadership.

Government response – accept

The government’s response to the MHRA’s consultation outlines the future regulatory framework for medical devices, which includes proposed changes that will position the MHRA as a world-leading regulator.

The future regulatory framework will be unique, innovative and ambitious in areas such as software as a medical device, artificial intelligence as a medical device, and IVDs, while maintaining a focus on patient safety. This leading regulatory model will put the MHRA in a leadership position among international peers in addressing challenges such as proportionate regulation of software as a medical device, ensuring that the UK attracts a world-class life sciences industry. Through the coronavirus (COVID-19) pandemic, the MHRA has shown itself to be one of the world’s foremost regulators – and true innovators.

The MHRA has recently gained full membership of the International Medical Devices Regulators Forum (IMDRF), a group of 10 regulatory authorities focussing on accelerating international medical device regulatory convergence. As a full IMDRF member, the MHRA will be able to take a greater international role in promoting an efficient and effective regulatory model for medical devices, responding to emerging challenges while protecting and maximising public health and patient safety.

The MHRA is also an official observer of the Medical Device Single Audit Programme (MDSAP). MDSAP is a way in which manufacturers can seek a single assessment of conformity of their quality management systems against the regulatory requirements for any of the 5 full member states: Australia, Brazil, Canada, Japan and the US.

More specifically, the MHRA has worked with the US Food and Drug Administration (FDA) and Health Canada to publish an agreed list of 10 Good Machine Learning Practice Principles (October 2021). This document is intended to ensure aligned thinking between the regulators and is the first step of collaborative work in this area between regulators. Building on this collaboration, the MHRA continues to strengthen their relations and are working together to deliver further documents to ensure internationally aligned thinking on artificial intelligence (AI) and machine learning-enabled medical devices. In addition, through participation of the IMDRF, the MHRA is developing AI-specific guidance that will set the global standards for regulatory compliance.

More widely, the MHRA has collaborated with the NHS Transformation Directorate on the G7 health track digital health proposal on AI governance as part of the UK delegation (paragraphs 40 and 41, G7 Health Ministers Declaration). Through this work we are contributing to the international dialogue on digital health and providing recommendations on how countries can work together to ensure their citizens can benefit from digital health technologies.

The MHRA is working closely with the British Standards Institute (BSI) in its roles as the UK national standards body and a global standards promoter in partnership with their US counterpart, the Association for the Advancement of Medical Instrumentation (AAMI). The MHRA contributes to several standards committees in this space, namely: BS30440 Validation Framework for the use of AI in Health and Care, and Committees: CH/62/2 Diagnostic Imaging Equipment, CH/62/3 Equipment for Radiotherapy, Nuclear Medicine and Radiation Dosimetry, and IST/35 Health Informatics. Additionally, the MHRA also provides input on many of the major reporting guideline variants for AI, such as CONSORT-AI, SPIRIT-AI, and DECIDE-AI, increasing the MHRA’s international engagement and leadership in developing regulatory guidelines.

This international work is a key component in ensuring alignment and the long-term success of MHRA’s domestic legislative and regulatory guidance plans for the future regulation of software as a medical device (SaMD) and artificial intelligence as a medical device (AIaMD).

Recommendation 6

Invest in the UK as a global centre for regulatory science and the training of regulatory professionals with expertise in medical devices, including in emerging technologies.

Government response – accept in principle

The government’s current focus for medical devices is to implement changes to the regulatory framework that increase patient safety and promote innovation, thereby growing the life sciences sector in the UK. Alongside this, we are interested in the opportunities posed by a UK centre of excellence in regulatory science and innovation (CERSI). This was also a recommendation of the Taskforce on Innovation, Growth and Regulatory Reform report 2021, and we will continue to work with stakeholders to explore options for this.

While the activities related to the future medical devices regulations do not bring additional direct investment, they do provide a robust and positive environment in which the UK can build its reputation in all areas of life sciences, and in particular a supportive UK regulatory environment for the safe and rapid development of innovative medical devices.

In addition to the new regulatory framework, the government’s ambition to ensure the UK is a leading global hub for all aspects of life sciences is being driven by the Life Sciences Vision, published by the Office for Life Sciences in July 2021. On skills, the vision makes commitments to:

  • welcoming and advocating the free flow of life sciences talent globally, underpinned by the UK’s new immigration system
  • boosting the proportion of the apprenticeship levy recovered by the life sciences sector
  • building links between life sciences university courses and industry
  • exploring how the sector can effectively meet emerging skills demands

The vision also sets out its aims to deliver a progressive UK regulatory offer with the capacity to unleash innovation in regulatory processes. This includes a specific funding allocation to the MHRA and the National Institute for Health and Care Excellence (NICE) to develop a new access and licensing pathway for medical devices, similar to that which exists for medicines.

To further support this work, the MHRA’s future regulatory framework for medical devices will actively address the safety and availability of medical devices, and the favourability of the UK as a place to research, develop, manufacture and supply medical devices. The government has outlined intentions for requirements for a Qualified Person within the response to the MHRA’s consultation on the regulatory changes for medical devices. This proposal will require that manufacturers have available within their organisation (or in the case of small and medium-sized enterprises (SMEs), at their disposal) at least one Qualified Person with qualifications or regulatory experience that meets minimum standards that would be set out in the UK medical devices regulations in the field of medical devices and IVDs. This commitment will provide a strong incentive for increased training of regulatory professionals with expertise in medical devices.

Recommendation 7

Build international partnership through mutual recognition and reliance or assurance where this may lead to overall efficiencies while preserving safety.

Government response – accept

The MHRA delivery plan 2021 to 2023 outlines commitments to building excellent international relationships that:

  • deliver high standards of patient protection
  • prompt access to innovation products
  • keep the UK as an attractive market for developers and manufacturers

The government sees international partnership as vital to deepen co-operation, exchange information and encourage the adoption of international standards and best practice.

The government also intends to use both certificates from the Medical Device Single Audit Program (MDSAP) and domestic assurance as alternative routes to market in the UK, which will make it easier for manufacturers to bring medical devices to the UK market while retaining strong regulatory oversight of their safety and performance.

The UK will require UK approved bodies to consider MDSAP assessments. However, adoption will be optional for manufacturers. Domestic assurance routes will allow an abridged assessment with the appropriate scrutiny, and UK approved bodies will hold the capacity to reject applications under the domestic assurance route if they do not consider the evidence provided to be sufficiently robust to undergo assessment through this route.

In 2019, the UK signed a mutual recognition agreement (MRA) with Australia that contains conditions under which each country will accept conformity assessment results from the other. This means that UK goods can be tested in the UK against Australia’s regulations, and then sold in the respective country without additional testing. This also applies for goods tested in Australia to the UK regulations.

We are in ongoing discussions to expand existing MRAs to include medical devices, and to build new MRAs that provide for a mutual acceptance of conformity assessment results with other countries. The UK-Canada Trade Continuity Agreement highlighted that the medical devices sector is a priority for mutual recognition of the acceptance of conformity assessment results, and further expansion will be explored in the future.

Through bilateral engagement, the government is encouraging other countries to join and adhere to multilateral medical device regulatory forums, which produce best practice guidelines for regulators and reduce the discrepancies between regulatory systems. Through further international collaboration and regulatory harmonisation, we will promote an efficient and effective global market for placing medical devices on the market, which is responsive to emerging challenges while maximising patient safety.

Using medical devices as a template to help enable regulatory innovation that improves patient safety, system efficiency and UK growth

Recommendation 8

Identify and resource areas where regulatory innovation within the medical device sector may attract inward investment and growth.

Government response – accept

The MHRA’s future regulatory framework outlines plans to create new routes to market to support innovation in medical devices. This will ensure the UK remains an excellent place to launch new medical devices and avoid repeat assessments, while maintaining robust safety standards.

Following the UK’s departure from the European Union, the MHRA now has direct responsibility for the regulation of medical devices in the UK. One of the freedoms that come with this is the ability to reform medical device regulation to ensure it better fits software and AI.

The regulation of AIaMD is an area where regulatory innovation will attract inward growth and investment. The MHRA has an opportunity to become a global leader in the regulation of AIaMD and to demonstrate the MHRA’s capacity to support responsible innovation while minimising risk to patients and the public.

The MHRA has embarked upon an ambitious Software and AIaMD Change Programme to help achieve this, reforming medical devices regulation as it applies to software and AI, and introducing new guidance and support packages. This work programme will deliver bold change to bring a high degree of protection for patients and the public, while also making sure that the UK is the home of responsible innovation for medical device software.

As mentioned in the response to recommendation 6 above, the MHRA and NICE also have plans to establish a pathway for medical devices that is similar to the Innovative Licensing Access Pathway that is currently in place for medicines. This pathway will allow for increased MHRA and NICE support for products that meet a critical unmet need, thereby attracting growth and investment in this sector.

To further explore pathways for innovative devices, the government is working to explore options to increase access and adoption of medical technologies. This will accelerate the work already in motion as part of the Life Sciences Vision, the MHRA’s new regulatory framework and the upcoming MedTech strategy by finding opportunities to increase market access and adoption of medical technology. As a result, we will seek to increase investment by making the UK a more attractive regulatory environment for companies bringing new products to market.

Recommendation 9

Develop a UK patient safety database that collects key details of all medical devices and monitors patient safety and wellbeing moving forward.

Recommendation 9A

Strengthen existing safety reporting through digital tools and the use of comprehensive data collection from health systems, patients and carers to a central MHRA-held UK patient safety database.

Recommendation 9B

When medical devices are used, their unique device identifier (UDI) should be recorded as standard within a patient’s health record, and this should be returned to a central MHRA-led UK patient safety database.

Government response – accept in principle

The MHRA has recently launched improvements to its Yellow Card scheme, which collects and monitors information from the public on suspected safety concerns involving healthcare products, including medical devices. The scheme helps the MHRA monitor the safety of medical devices along with all healthcare products in the UK, and reports through the scheme are used to help the MHRA identify any trends in the safety or efficacy of a medical device and take action accordingly.

The scheme’s improved website went live on 7 February 2022 with new functionality for reporters, such as a single reporting form, and further enhancements to the reporting journey will be made in coming months. One technology platform for incident management and signal detection across medicines and devices is being developed for the MHRA’s use, which will allow improved analysis and faster signal detection, and enable the MHRA to proactively respond to safety concerns.

Another key focus of current work in improving the safety of patients using medical devices is in the area of implantable devices. Following several high-profile failures of implanted medical devices, the government has recognised the need for greater, systematic information to be captured and shared on these interventions. The need for better data on patient outcomes and device traceability was highlighted by the Independent Medicines and Medical Devices Safety (IMMDS) Review, which recommended a system be established that would capture key information on implanted devices at the time of the operation and linked to specifically created registers to research and audit the outcomes both in terms of device safety and patient-reported outcome measures. The government accepted that recommendation in its response to the IMMDS Review on 21 July 2021.

In 2021 to 2022, a scoping exercise was undertaken that provided substantial learnings for how best to deliver on these traceability and patient outcome objectives. The government sets out more detail on how this work is progressing in the IMMDS implementation update. It is envisaged that the data collected as part of this programme will be shared with the MHRA for post-market surveillance purposes and therefore we do not accept that part of the recommendation.

Building resilience and preparing for future threats

Recommendation 10

Pandemic preparedness should include fast-track evaluation of new IVDs.

Government response – accept

The MHRA’s future regulatory framework intends to reform IVD regulation to update classification and include an extended patient risk review, recognising the central role that diagnostic devices have played in our response to the COVID-19 pandemic.

While stronger regulation is needed, the diagnostics sector needs to be sufficiently responsive. The 100 Days Mission to Respond to Future Pandemic Threats (June 2021), announced at the G7 Summit in Cornwall – proposed to build a framework for fast pandemic threat response and related work – will be taken forward through this strand. This framework will include plans for enabling prioritisation of clinical trials for diagnostic products (as well as vaccines and therapeutics) and faster approvals from regulators.

The 100 Days Mission for diagnostics, therapeutics and vaccines was welcomed by G7 and G20 leaders respectively. The first implementation report was published by the G7 Chief Scientific Advisers in December 2021, which outlined progress to date and a roadmap for achieving the mission by 2026. As part of the 100 Days Mission, the MHRA and the US FDA will collaborate with their G7 counterparts to implement proposals to streamline regulatory processes over 2022 to 2026. This could include a streamlined process for new product applications, and will explore the possibility of reciprocal agreements on regulatory approval to negate the need for the same product to be approved in multiple jurisdictions.

The lessons from the COVID-19 pandemic are being considered, and the government intends to enable a fast-track route for IVDs, as part of the ambition outlined in the 100 Days Mission, that is proportionate and workable for industry should future threats emerge, while maintaining quality and performance.

Recommendation 11

Reporting of diagnostic tests should be transparent and standardised.

Government response – accept in principle

The MHRA’s future regulatory framework intends to address the recommendation to increase the level of scrutiny applied to IVD devices. The new framework for IVDs will amend the classification rules to increase the level of scrutiny applied to IVDs. This will mean a higher proportion of IVDs will undergo an assessment by a UK approved body prior to being placed on the UK market. The proposed regulatory changes will take into account the intended purpose of the medical device and will reflect relevant international systems of regulation, driving greater patient safety.

The new regulatory framework will bring significant improvements in patient safety and ensure more robust pre and post-market requirements are introduced for IVDs, aligning with the international set of standards set by the IMDRF, rather than the Standards for Reporting of Diagnostic Accuracy Studies Framework. This will provide clarity and ensure that performance studies for IVDs are carried out in a consistent way. The government aims to set out in detail the specific requirements for any performance study, and to publish detailed guidance to accompany the regulatory requirements.

Association between healthy lifestyle and memory decline in older adults: 10 year, population based, prospective cohort study

Abstract

Objective To identify an optimal lifestyle profile to protect against memory loss in older individuals.

Design Population based, prospective cohort study.

Setting Participants from areas representative of the north, south, and west of China.

Participants Individuals aged 60 years or older who had normal cognition and underwent apolipoprotein E (APOE) genotyping at baseline in 2009.

Main outcome measures Participants were followed up until death, discontinuation, or 26 December 2019. Six healthy lifestyle factors were assessed: a healthy diet (adherence to the recommended intake of at least 7 of 12 eligible food items), regular physical exercise (≥150 min of moderate intensity or ≥75 min of vigorous intensity, per week), active social contact (≥twice per week), active cognitive activity (≥twice per week), never or previously smoked, and never drinking alcohol. Participants were categorised into the favourable group if they had four to six healthy lifestyle factors, into the average group for two to three factors, and into the unfavourable group for zero to one factor. Memory function was assessed using the World Health Organization/University of California-Los Angeles Auditory Verbal Learning Test, and global cognition was assessed via the Mini-Mental State Examination. Linear mixed models were used to explore the impact of lifestyle factors on memory in the study sample.

Results 29 072 participants were included (mean age of 72.23 years; 48.54{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} (n=14 113) were women; and 20.43{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} (n=5939) were APOE ε4 carriers). Over the 10 year follow-up period (2009-19), participants in the favourable group had slower memory decline than those in the unfavourable group (by 0.028 points/year, 95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.023 to 0.032, P<0.001). APOE ε4 carriers with favourable (0.027, 95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.023 to 0.031) and average (0.014, 0.010 to 0.019) lifestyles exhibited a slower memory decline than those with unfavourable lifestyles. Among people who were not carriers of APOE ε4, similar results were observed among participants in the favourable (0.029 points/year, 95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.019 to 0.039) and average (0.019, 0.011 to 0.027) groups compared with those in the unfavourable group. APOE ε4 status and lifestyle profiles did not show a significant interaction effect on memory decline (P=0.52).

Conclusion A healthy lifestyle is associated with slower memory decline, even in the presence of the APOE ε4 allele. This study might offer important information to protect older adults against memory decline.

Introduction

Although a fundamental function of daily life, memory continuously declines as people age,1 impairing both life quality and work productivity and increasing the risk of dementia.234 However, age related memory decline is not always a prodrome of dementia; memory loss can merely be senescent forgetfulness, which is more prevalent among older individuals, and can be reversed or become stable rather than progress to a pathological state.5 Thus, the prevention and slowing of age related memory decline in older individuals is paramount. Fortunately, memory decline can be mutable because various contributing factors are reportedly associated with memory loss.

Studies have been conducted to identify factors that might affect memory, including ageing, the apolipoprotein E (APOE) ε4 genotype, chronic diseases, and lifestyle patterns.67 Among these, lifestyle has received increasing attention as a modifiable behaviour because this factor is relatively easily amendable with potential benefits for overall health as well as memory. Studies on the effect of a healthy lifestyle on cognition are increasing.89101112 However, few studies have focused on its effect on memory, and most were cross sectional in nature,13 which is insufficient to evaluate the relationship between a long term healthy lifestyle and memory decline. Additionally, those studies did not consider the interaction between a healthy lifestyle and genetic risk; thus, the exact effect of a healthy lifestyle on memory decline in individuals with a higher genetic risk remains unknown. Therefore, longitudinal studies are needed to further investigate the effect of modifiable lifestyle factors on memory decline in older individuals, considering genetic risks, such as the presence of an APOE ε4 genotype.

We used data from a large population based cohort (the China Cognition and Ageing Study; COAST) to investigate whether adherence to a combination of healthy lifestyle factors was associated with a slower memory decline in cognitively normal older adults, even those genetically susceptible to memory decline.

Methods

Study design and participants

The COAST is a nationwide, population based, cohort study on dementia in China (ClinicalTrials.gov identifier: NCT03653156). This investigation included individuals from 12 provinces from the north, south, and west of China, representing the geographical characteristics, degree of urbanisation, economic status, dietary patterns, and cultural and social differences in China. We conducted a multistage, stratified, cluster sampling procedure, which considered sex and age distribution, among these provinces. A total of 96 study sites (48 urban and 48 rural) were randomly selected (supplementary 1). Written or oral informed consent was obtained from all participants.

The study enrolment procedure began on 8 May 2009 and comprised two sequential phases (lasting about six months together). In phase 1, individuals aged 60 years or older, who gave consent to participate in the study, were listed in the community census or village registry, and had resided there for at least one year preceding the survey date, were included in the study. We excluded participants with a life threatening disease, hearing loss, or vision loss. In phase 2, participants from phase 1 with available APOE genotyping and without mild cognitive impairment or dementia were included. Four rounds of follow-up were conducted—ie, a follow-up any time in 2012, 2014, 2016, and 2019. The end date of the study was 26 December 2019.

Diagnosis of dementia and mild cognitive impairment

The aim of this study was to investigate the association between lifestyle and memory in participants with normal cognitive function throughout the study period. Neuropsychological tests were done to determine the cognitive status of the participants at baseline and at each follow-up. For people who progressed to mild cognitive impairment or dementia during the follow-up period, the data after their diagnosis were excluded in the main analyses. Global cognitive function was assessed using the Mini-Mental State Examination,14 which evaluates orientation, attention, calculation, executive function, language, among others. The total score of the Mini-Mental State Examination ranges from 0 to 30, with higher scores representing a better cognitive function. Participants whose score was less than 26 were suspected of cognitive impairment and would receive further evaluation, including physical and other neuropsychological testing. The results and participants’ medical records were reviewed by neurologists who were masked to the genetic results. Dementia was diagnosed on the consensus of at least two neurologists, according to the Diagnostic and Statistical Manual of Mental Disorders (4th edition, text revision criteria).15 Mild cognitive impairment was diagnosed according to the Peterson criteria.16 Having normal cognitive function was defined as having a score of 0 for the Clinical Dementia Rating.17 People for whom a consensus could not be reached were considered controversial cases. These cases would be discussed and diagnosed by an expert group, which included senior neurologists, psychiatrists, and neuropsychologists.

Assessment of lifestyle factors

Lifestyle information was collected at baseline and each follow-up based on each individual’s performance over the past year through a healthy behaviour questionnaire (supplementary 2). We assessed lifestyle status by six modifiable lifestyle factors: physical exercise, diet, drinking, smoking, cognitive activity, and social contact. For physical exercise, weekly frequency and total time were collected, and at least 150 min of moderate or 75 min of vigorous activity per week was considered a healthy factor, according to the American guidelines for physical activity in adults.18 For smoking, participants were categorised as smokes current, never (participants who had smoked <100 cigarettes in their lifetime) smokes, or used to smoke (participants who had quit smoking at least three years before). Never or former smoking was deemed a healthy lifestyle factor.19 For alcohol consumption, the current frequency and volume of alcohol consumption were recorded, and individuals were categorised into never drinking (never drank or drank occasionally), low to excess drinking (daily alcohol consumption of 1-60 g), and heavy drinking (daily alcohol consumption >60 g).20 The category of never drinking was deemed a healthy lifestyle factor.21 The remaining three lifestyle factors were deemed healthy based on the top 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of the population distribution, according to previous studies.22232425 For diet, we recorded the participant’s daily intake of 12 food items (fruits, vegetables, fish, meat, dairy products, salt, oil, eggs, cereals, legumes, nuts, and tea) (supplementary 2).26 For cognitive activity (writing, reading, playing cards, mahjong, and other games) and social contact (participation in meetings or attending parties, visiting friends or relatives, travelling, and chatting online), engagement frequencies were investigated. Ultimately, these factors were deemed healthy when participants consumed appropriate daily amounts of at least 7 of the 12 food items for diet, and they engaged in cognitive activity or social contact at least twice weekly in this study.

We evaluated the association of each single lifestyle factor with memory function. For further investigation of the combined effect of lifestyle factors on memory function, we categorised participants into three groups based on the third of the number of healthy lifestyle factors: favourable (4-6 healthy factors), average (2-3), and unfavourable (0-1). To investigate the effect of lifestyle on memory stratified by APOE genotypes, participants were also grouped into people who were APOE ε4 carriers and people who were not carriers.

Outcomes

Memory function was measured at baseline and each follow-up using the World Health Organization/University of California-Los Angeles Auditory Verbal Learning Test (AVLT),27 which included measurement of immediate recall, short delay free recall (3 min later), long delay free recall (30 min later), and long delay recognition. During the test, a rater read a list of words consisting of 15 nouns; immediately after its completion, the participant attempted to repeat as many words as possible. The score of immediate recall was 0-60, and the scores of all other tests were 0-15. The standard z scores for the auditory verbal learning test were calculated based on the respective mean and standard deviation test scores. The composite z score for memory function was constructed by averaging the z scores for each test in the auditory verbal learning test.

Covariates

Potential confounders were selected based on directed acyclic graphs (supplementary figure 1) depicting the best known relations between the variables in this study. Sociodemographic information obtained at baseline were sex, place of residence (rural or urban), region (north, west, or south), marital status (married, widowed, or divorced/separated/single), years of education (<1 year, 1-6 years, 7-12 years, >12 years), monthly household income (1000-2999, 3000-4999, 5000-10 000, >10000 Chinese Yuan), occupation (manual labourer, office worker, household, or others). Health related covariates were collected at baseline and each follow-up, including age, body mass index and medical illnesses (hypertension, diabetes, hyperlipidaemia, heart attack, head injury, cerebrovascular disease, and depression). We also included the learning effect of each participant as a covariate due to repeated cognitive assessments.

Statistical analysis

Baseline characteristics of the analytical sample were summarised across three lifestyle groups as a percentage for categorical variables and mean and standard deviation for continuous variables. Missing values are summarised in supplementary table 1. A multiple imputation chain-equation was used to impute missing data. Data were assumed to be missing at random. Missing continuous variables were imputed using predictive mean matching method, and binary variables were imputed by Logistic regression model. We generated five imputed datasets with 100th iteration, and analysed each dataset separately, then combined their results by use of Rubin’s method.

Linear mixed effects models were used in this study, and all statistical assumptions were tested before interpretation of results. The data met the distributional requirements in each case. We examined the effects of different lifestyle profiles, APOE ε4 status, as well as their interactions on longitudinal memory trajectories in participants with normal cognition throughout the study by use of linear mixed effects models. The composite z score of the auditory verbal learning test was the dependent variable. The fixed effects were the following: lifestyle profiles (each respective lifestyle factor as well as the combination); APOE ε4 status; time (follow-up year from baseline); two way interactions of lifestyle with APOE ε4 status and time; and three way interactions between lifestyle, APOE ε4 status, and time. The random effects included intercept and time. Age (centred at 74 years to reduce the correlation between the age and age squared terms), age squared (to allow for the comparison of acceleration in the rate of memory decline between lifestyle groups), baseline memory score, learning effect (by assignment code to the first assessment as 1 versus subsequent assessments coded as 0), and other covariates were also adjusted in this model. In addition, the global cognitive trajectories in the cognitively normal population were evaluated using a linear mixed effects model with global cognition (standard z score of the Mini-Mental State Examination) as dependent variable. Furthermore, we investigated the interaction between lifestyle and age on memory decline.

As lifestyle status and some of the covariates changed over time, a time dependent Cox regression model (non-proportional hazard model) was used to assess the effect of lifestyle groups on progression to mild cognitive impairment or dementia in the total study population and APOE ε4 stratified population. In this model death and drop-out data were treated as censoring data. Additionally, we evaluated whether dropping out from the study affected the effects of lifestyle on mild cognitive impairment or dementia using an inverse probability weighting model. We also assessed the influence of death as a competing risk for mild cognitive impairment or dementia via competing risk analyses.

Sensitivity analyses

We conducted several additional sensitivity analyses to evaluate the robustness of our findings. Firstly, we included the number of lifestyle factors as a continuous variable in the mixed model to test the rationale of our grouping method. Secondly, we derived a weighted standardised healthy lifestyle score based on the β coefficient of each lifestyle factor in the linear mixed effects model adjusted for covariates.28 Specifically, the original binary lifestyle variables were multiplied by the β coefficients, and all the β coefficients were summed. The score of each lifestyle factor was obtained via the β coefficient of each lifestyle factor divided by the sum of the β coefficients, multiplied by 100. Participants were categorised into three groups based on the third of weighted standardised score into low, intermediate, and high score groups. Third, we excluded each lifestyle factor to identify possible factors that might drive the associations with memory. The excluded lifestyle factor was used as a confounder. Fourthly, we excluded participants who later developed mild cognitive impairment or dementia to determine whether the results were consistent with the main results. Fifthly, we excluded participants who died or dropped out throughout the study in order to evaluate the possible effects of death or drop-out on the results (if the results were consistent when participants were excluded with when they were not excluded, death or drop-out would have had no effect on the results). Finally, to assess the reverse causality of memory decline and healthy lifestyle profile, we performed a cross-lagged panel model, which is used when examining reciprocal causal processes in longitudinal data with at least two waves of data. Each analysis included a cross-wave component that estimated the change in each outcome from one wave, characterised by relationships between outcomes from each specific wave. We examined changes in composite z scores for memory in relation to changes in healthy lifestyle profiles over time.

All statistical analyses were done in R (version 3.6.3). We used the following packages: mice, for imputing; lmerTest, for linear mixed effects models; cmprsk, for competing risk models; lavaan, for cross-lagged analysis; and ipw, for inverse probability weighting. The two tailed significance level was set at P<0.05.

Patient and public involvement

Participants of the COAST study were not involved in setting the research question or the outcome measures, nor were they involved in developing plans for recruitment, design, or implementation of the study. No participants were asked for advice on interpreting or writing up of results. We know that the public involvement has great value in improving the quality of research; however, we did not have the necessary funding to invite participants for their advice. We intend to engage participants and the public to disseminate the results of our study.

Results

In total, 56 894 individuals were screened for eligibility. In phase 1, we excluded 17 148 individuals who were younger than 60 years or did not give permission to participate. In total, 39 746 individuals completed the neuropsychological assessment and clinical examination. In phase 2, we excluded 7814 individuals with mild cognitive impairment and 2860 individuals with dementia. Overall, we enrolled 29 072 with normal cognitive function who underwent APOE genotyping at baseline. During the 10 year follow-up period, 7164 individuals died and 3567 individuals discontinued participation for various reasons (fig 1).

Association between healthy lifestyle and memory decline in older adults: 10 year, population based, prospective cohort study
Fig 1

Study profile. MCI=mild cognitive impairment

Table 1 summarises the participants’ baseline demographic characteristics according to the three lifestyle groups. At baseline, all participants had normal cognitive function (48.54{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} female), with a mean age of 72.23 years (standard deviation 6.61), and 20.43{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} were carriers of APOE ε4 (supplementary table 2). Additionally, 6967 participants were enrolled in the unfavourable lifestyle group, 16 549 in the average group, and 5556 in the favourable group.

Table 1

Demographic characteristics of the cognitively normal population and time dependent healthy lifestyle groups at baseline. Data are number ({bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}), unless otherwise specified

Lifestyle and memory function in older adults

We used linear mixed effects models to describe the trends in global cognition and memory function and to examine the influence of healthy lifestyle and APOE ε4 status on the annual rate of change in memory function over the 10 year follow-up period. The trajectories in the population with normal cognitive function indicated that, although the overall cognition state remained stable, memory declined continuously over time (supplementary figure 2, supplementary tables 3-4). This memory decline occurred faster in the APOE ε4 carriers than in the APOE ε4 non-carriers (0.002 points/year, 95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.001 to 0.003, P=0.007) (supplementary figure 2, supplementary table 5).

We evaluated the contribution of each binary lifestyle component on memory decline. The results showed that a healthy diet had the strongest effect on memory (β=0.016, 95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.014 to 0.017, P<0.001), followed by active cognitive activity (β=0.010, 0.008 to 0.012, P<0.001), regular physical exercise (β=0.007, 0.005 to 0.009, P<0.001), active social contact (β=0.004, 0.002 to 0.006, P<0.001), never or former smoking (β=0.004, 0.000 to 0.008, P=0.026), and never drinking (β=0.002, 0.000 to 0.004, P=0.048) (supplementary table 6). Furthermore, we analysed the association between lifestyle groups and memory performance. Our results showed that participants with favourable and average lifestyles had a slower rate of memory decline than did participants with an unfavourable lifestyle (P<0.001) (fig 2). Specifically, the decline in the composite z score was slower by 0.028 points/year (95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.023 to 0.032) in the favourable group and by 0.016 points/year (0.012 to 0.020) in the average group than in the unfavourable group. Figure 2 (bottom panel) shows that the mean composite Auditory Verbal Learning Test scores continuously declined over the 10 year period; the highest test scores were observed in the favourable group and the lowest in the unfavourable group.

Fig 2
Fig 2

Longitudinal change in memory among favourable, average, and unfavourable groups in the cognitively normal population. (Top panel) Estimated change in memory function over 10 years, by group. Dots represent individuals’ estimated composite z scores for AVLT. (Bottom panel) Mean composite AVLT z scores of all groups. AVLT=Auditory Verbal Learning Test

Assessing the interaction between lifestyle and age showed a slower rate of age related memory decline in the favourable and average lifestyle groups compared with that in the unfavourable group. Compared with the unfavourable group, the memory score in the favourable lifestyle group was 0.007 (95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.005 to 0.009, P<0.001) points higher per increased year of age and in the average group was 0.002 (0.000 to 0.003, P=0.033) (supplementary table 7).

Lifestyle and memory function in people with or without APOE ε4

Similar results were obtained in the analyses that were stratified according to the APOE genotype (fig 3). In people who carry APOE ε4 allele and in people who do not, a favourable lifestyle was associated with better memory performance over time compared with average and unfavourable lifestyles (P<0.001). Among people who carry APOE ε4, participants with favourable and average lifestyles exhibited a slower rate of memory decline than did those with an unfavourable lifestyle (0.027 (95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.023 to 0.031) and 0.014 (0.010 to 0.019) points/year, respectively). Among people who did not carry the APOE ε4 allele, the estimated rates of decline were 0.029 (0.019 to 0.039) points/year slower for participants with favourable lifestyles and 0.019 (0.011 to 0.027) for participants with average lifestyles, compared with participants who had an unfavourable lifestyle. Further analysis showed no significant interaction effect between APOE ε4 status and lifestyle profiles on memory decline (P=0.52).

Fig 3
Fig 3

Longitudinal change in memory among favourable, average, and unfavourable groups in the APOE ε4 stratified population. Dots in the left panels represent individuals’ estimated composite AVLT z scores. AVLT=Auditory Verbal Learning Test; APOE=apolipoprotein E

Lifestyle and mild cognitive impairment or dementia

Time dependent Cox regression models suggest that, over 10 years of follow-ups, a favourable lifestyle was associated with a lower probability of progression to mild cognitive impairment and dementia. Compared with an unfavourable lifestyle, the hazard ratios were 0.71 (95{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} confidence interval 0.68 to 0.73) for an average lifestyle and 0.11 (0.10 to 0.12) for a favourable lifestyle. The result was similar when considering the competing risk of death (supplementary table 8). The inverse probability weighting model showed that participants who dropped out of the study did not affect the association between lifestyle and mild cognitive impairment or dementia (supplementary table 9). The APOE stratified analysis showed a similar result with that of the total population (supplementary table 8).

The relations between the mean auditory verbal learning test score and the percentage of participants with dementia or mild cognitive impairment are presented in figure 4. The percentage of participants with dementia or mild cognitive impairment increased as the mean Auditory Verbal Learning Test scores decreased among the older adults in our study.

Fig 4
Fig 4

Mean AVLT scores and the percentage of participants with dementia (top panel) and mild cognitive impairment (bottom panel) among older adults, at different follow-up periods. The percentages of participants with dementia and mild cognitive impairment increase with a reduction in the mean AVLT scores. AVLT=Auditory Verbal Learning Test; MCI=mild cognitive impairment

Sensitivity analyses

The results of the sensitivity analyses are presented in the supplementary material. The first sensitivity analysis was conducted to test the robustness of the rationale of our grouping methods. When the number of lifestyle factors was considered as a continuous variable in the mixed effects model, two or more healthy lifestyle factors were associated with a slower rate of memory decline than did no healthy factors (supplementary table 10). The results of the analysis investigating the association between lifestyle and memory based on the weighted standardised healthy lifestyle scores showed that participants in the high and intermediate score groups had a slower rate of memory decline by 0.029 (0.025 to 0.033, P<0.001) and 0.017 (0.015 to 0.019, P<0.001) points/year, respectively, compared with participants in the low score group (supplementary tables 11-12). We found that no particular healthy lifestyle factor drove the association between lifestyle and memory (supplementary table 13). Additionally, among participants who did not develop mild cognitive impairment or dementia, did not drop out, and were alive throughout the follow-up period, the association between lifestyle profiles and memory decline remained significant (supplementary tables 14-15). Cross lagged analyses were done to assess the bidirectional, longitudinal associations between memory function and a healthy lifestyle during the 10 year follow-up period. The results supported the absence of a reverse causality between memory decline and healthy lifestyle profiles (supplementary figure 3).

Discussion

This large scale study is the first to our knowledge to estimate the effects of different lifestyle profiles, APOE ε4 status, and their interactions on longitudinal memory trajectories over a 10 year follow-up period. Our results show that a healthy lifestyle was associated with a slower rate of memory decline in cognitively normal older individuals, including in people who are genetically susceptible to memory decline.

Comparison with other studies

This study characterised the longitudinal memory trajectories of the participants with normal global cognition. Of note, the results showed that, although global cognition remained relatively stable, memory declined rapidly as the individual aged. Therefore, focusing on global cognition might lead to overlooking memory problems, especially among people older than 65 years, a third of whom are reported to experience memory complaints.29 Effective strategies for protecting against memory decline might benefit many older individuals. Previous studies have investigated the associations between lifestyle factors and memory loss; however, most have focused on a single lifestyle factor, such as smoking,30 drinking,3132 diet,33 or physical activities.734 Few studies have been conducted to target the combined effects of multiple lifestyle factors on memory decline. Thus, comparison of the contribution of each factor to memory decline has been a challenge.

In this study, we investigated the contribution of each lifestyle factor and their combined effects in a large sample size over an entire decade. We found that diet had the strongest association with memory, followed by cognitive activity, physical exercise, and social contact. Although each lifestyle factor contributed differentially to slowing memory decline, our results showed that participants who maintained more healthy lifestyle factors had a significantly slower memory decline than those with fewer healthy lifestyle factors. This information could be useful in making personal choices that can help to protect against memory decline, and our results provide further evidence that memory loss is potentially modifiable. Although the mechanisms responsible for such changes were not determined in this study, they might include reduced cerebrovascular risk, enhancement of cognitive reserve, inhibition of oxidative stress and inflammation, and promotion of neurotrophic factors.11133536

Another defining feature of our study is that all participants underwent APOE genotyping. The APOE ε4 allele is reportedly correlated with earlier and more rapidly progressive memory decline,137 and the frequency of the ε4 allele dramatically increases to 40{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} in patients with Alzheimer’s disease.38 People who have the APOE ε4 allele are more likely to exhibit abnormally high Aβ levels in the brain and experience more rapid neurodegeneration and memory loss than people who do not.39404142 The APOE ε4 allele can also magnify the effects of other risk factors, including physical inactivity, unhealthy diet, and smoking.43 However, most studies that have explored the role of APOE have focused on the associations between lifestyle and global cognition rather than memory.444546 Here, we observed a positive effect of a healthy lifestyle on memory in both carriers of APOE ε4 and non-carriers, and no interaction effect was observed between the APOE genotype and lifestyle profiles over time. These results provide an optimistic outlook, as they suggest that although genetic risk is not modifiable, a combination of more healthy lifestyle factors are associated with a slower rate of memory decline, regardless of the genetic risk.

Strengths and limitations of this study

Although many studies have investigated the relationship between a healthy lifestyle and dementia, few have focused on memory loss, which is a condition that older adults with normal cognitive function can experience and that differs from dementia. This multicentre study with a large sample and a long term follow-up period provided an opportunity to observe the longitudinal trajectories of memory function in older adults with different lifestyles. However, our study also has some limitations. Firstly, the assessments of lifestyle factors were based on self-reports and are, therefore, prone to measurement errors. Secondly, several participants were excluded due to missing data or not returning for follow-up evaluations, which might have led to selection bias. Thirdly, the proportion of individuals with an unhealthy lifestyle might have been underestimated in our study because people with poor health were less likely to have participated in the study. Fourthly, given the nature of our study design, we could not assess whether maintaining a healthy lifestyle had already started influencing memory by the time of enrolment in the study. Fifthly, we evaluated memory using a single neuropsychological test that does not comprehensively reflect overall memory function. However, the Auditory Verbal Learning Test is an effective instrument for memory assessment, and we used a composite score based on four Auditory Verbal Learning Test subscales to represent memory conditions to the greatest extent possible. Sixthly, as participants might become familiar with repeated cognitive testing, a learning effect could have influenced the results, although, we considered that possibility in the design of the statistical analysis method. Finally, we studied memory decline solely among older adults; however, memory problems commonly affect young individuals as well. Thus, further studies should be conducted to facilitate a more extensive investigation into the effects of a healthy lifestyle on memory decline across the lifespan. This approach would help to elucidate the crucial age window during which a healthy lifestyle can exert the most favourable effect.

Conclusions

The results of this study provide strong evidence that adherence to a healthy lifestyle with a combination of positive behaviours, such as never or former smoking, never drinking, a healthy diet, regular physical exercise, and active cognitive activity and social contact, is associated with a slower rate of memory decline. Importantly, our study provides evidence that these effects also include individuals with the APOE ε4 allele. This study might offer important information to protect older adults against memory decline.

What is already known on this topic

  • Memory is a fundamental function of daily life that continuously declines with increasing age

  • Evidence from cohort studies is insufficient to evaluate the effect of healthy lifestyle on memory trajectory

  • Given the multifactorial biological cause of memory decline, a combination of healthy lifestyle factors might be necessary for an optimal effect, even for people who are genetically susceptible to memory decline

What this study adds

  • A combination of positive healthy behaviours is associated with a slower rate of memory decline in cognitively normal older adults, including in people with the apolipoprotein E ε4 allele

  • These results might offer important information for public health initiatives to protect older adults against memory decline

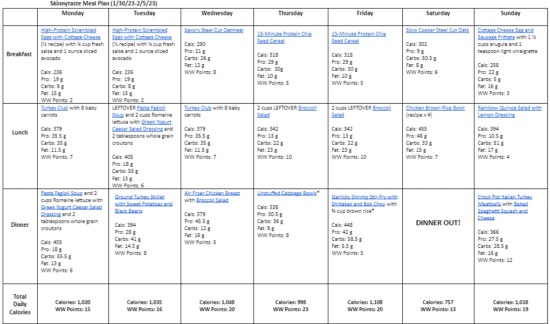
7 Day Healthy Meal Plan (Jan 29-Feb 5)

This post may contain affiliate links. Read my disclosure policy.

A free 7-day, flexible weight loss meal plan including breakfast, lunch and dinner ideas and a shopping list. All recipes include macros and WW points.

7 Day Healthy Meal Plan

I am so happy to see and hear all your positive comments about the new site! Tell me what your favorite new thing about it is! Is is the new recipe index? The Skinnytaste Shop (I’ll be adding more to this weekly)? Or maybe the new “search by diet” option? I love it all!

With grocery prices soaring, many of us are having to adjust, scale back and/or get more creative with our meals. One of the absolute BEST ways to stay within a budget and maintain healthy eating habits is to MEAL PLAN. You can get more 5-day Budget Friendly Meal Plans by signing up for Relish+ (get a 14-day free trial here!)

Ultimate Skinnytaste Meal Planner

Skinnytaste Ultimate Meal Planner

Get the Skinnytaste Ultimate Meal Planner! The 52 week spiral bound meal planner has weekly meal planning grids you can tear out and put on your fridge if you wish, a 12-week meal plan, 30 (15 new) recipes, and tear-out grocery lists. I love starting my week with gratitude, affirmations and intentions, so I included a space for that as well. I hope you will love this as much as I do!

Skinnytaste Ultimate Meal Planner

Buy the Skinnytaste meal planner here:

A note about WW Points

All recipe points have been updated to reflect the new WW program, points will display under the recipe title. I will keep the  ww button in the recipe card, click on that and it takes you to the Weight Watchers website where you can see the recipe builder used to determine those points and add it to your day (US only, you must be logged into your account). All cookbook recipes in the cookbook index are also updated!

About The Meal Plan

If you’re new to my meal plans, I’ve been sharing these free, 7-day flexible healthy meal plans (you can see my previous meal plans here) that are meant as a guide, with plenty of wiggle room for you to add more food, coffee, beverages, fruits, snacks, dessert, wine, etc. or swap recipes out for meals you prefer, you can search for recipes by course in the index. Depending on your goals, you should aim for at least 1500 calories* per day. There’s no one size fits all, this will range by your goals, your age, weight, etc.

There’s also a precise, organized grocery list that will make grocery shopping so much easier and much less stressful. Save you money and time. You’ll dine out less often, waste less food and you’ll have everything you need on hand to help keep you on track.

Lastly, if you’re on Facebook join my Skinnytaste Facebook Community where everyone’s sharing photos of recipes they are making, you can join here. I’m loving all the ideas everyone’s sharing! If you wish to get on the email list, you can subscribe here so you never miss a meal plan!

Meal Plan:

Breakfast and lunch Monday-Friday, are designed to serve 1 while dinners and all meals on Saturday and Sunday are designed to serve a family of 4. Some recipes make enough leftovers for two nights or lunch the next day. The grocery list is comprehensive and includes everything you need to make all meals on the plan.

MONDAY (1/30)
B: High-Protein Scrambled Eggs with Cottage Cheese (½ recipe) with ¼ cup fresh salsa and 1 ounce sliced avocado
L: Turkey Club with 8 baby carrots
D: Pasta Fagioli Soup and 2 cups Romaine lettuce with Greek Yogurt Caesar Salad Dressing and 2 tablespoons whole grain croutons

Total Calories: 1,020*

TUESDAY (1/31)
B: High-Protein Scrambled Eggs with Cottage Cheese (½ recipe) with ¼ cup fresh salsa and 1 ounce sliced avocado
L: LEFTOVER Pasta Fagioli Soup and 2 cups Romaine lettuce with Greek Yogurt Caesar Salad Dressing and 2 tablespoons whole grain croutons
D: Ground Turkey Skillet with Sweet Potatoes and Black Beans
Total Calories: 1,035*

WEDNESDAY (2/1)
B: Savory Steel Cut Oatmeal
L: Turkey Club with 8 baby carrots
D: Air Fryer Chicken Breast with Broccoli Salad

Total Calories: 1,048*

THURSDAY (2/2)
B: 15-Minute Protein Chia Seed Cereal
L: 2 cups LEFTOVER Broccoli Salad
D: Unstuffed Cabbage Bowls**

Total Calories: 998*

FRIDAY (2/3)
B: 15-Minute Protein Chia Seed Cereal
L: 2 cups LEFTOVER Broccoli Salad
D: Garlicky Shrimp Stir-Fry with Shiitakes and Bok Choy with ¾ cup brown rice
Total Calories: 1,108*

SATURDAY (2/4)
B: Slow Cooker Steel Cut Oats
L: Chicken Brown Rice Bowl (recipe x 4)
D: DINNER OUT

Total Calories: 757*

SUNDAY (2/5)
B: Cottage Cheese Egg and Sausage Frittata with 1 ½ cups arugula and 1 teaspoon light vinaigrette
L: Rainbow Quinoa Salad with Lemon Dressing
D: Crock Pot Italian Turkey Meatballs with Baked Spaghetti Squash and Cheese
Total Calories: 1.018*

*This is just a guide, women should aim for around 1500 calories per day. Here’s a helpful calculator to estimate your calorie needs. I’ve left plenty of wiggle room for you to add more food such as coffee, beverages, fruits, snacks, dessert, wine, etc.
**Make 5 cups extra rice for dinner Friday and lunch Saturday, if desired.

*Google doc

FDA Experts Are Still Puzzled Over Who Should Get Which Covid Shots and When

At a meeting to simplify the nation’s covid vaccination plan, the FDA’s panel of specialists could agree on only one particular factor: Info is woefully missing about how generally unique teams of Americans want to be vaccinated. That information hole has contributed to common skepticism, undervaccination, and ultimately needless fatalities from covid-19.

The committee voted unanimously Thursday to help the FDA’s proposal for all vaccine-makers to undertake the similar strain of the virus when producing improvements in their vaccines, and suggested they may meet in May possibly or June to select a pressure for the vaccines that would be rolled out this tumble.

However, the panel users disagreed with the FDA’s proposal that all people get at least 1 shot a calendar year, saying much more details was required to make such a declaration. Many panelists famous that in new research, only about a 3rd of people hospitalized with a constructive covid examination in fact were there because of covid health issues. Which is since all people getting into a medical center is examined for covid, so fatalities of sufferers with incidental bacterial infections are counted as covid deaths even when it is not the lead to.

The industry experts questioned the rationale for annual photographs for everybody, presented that latest vaccines do not seem to safeguard versus an infection for much more than a couple months. Yet even a single booster appears to protect against demise and hospitalization in most people today, besides for the quite previous and persons with particular health care ailments.

“We need to have the CDC to notify us just who is getting hospitalized and dying of this virus — the ages, vulnerability, the style of immune compromise, and no matter if they had been handled with antivirals. And we need to have immunological details to point out who’s at danger,” stated Dr. Paul Offit, director of the Vaccine Schooling Center and a pediatrician at Children’s Medical center of Philadelphia. “Only then can we decide who will get vaccinated with what and when.”

Offit and many others have expressed frustration over the deficiency of crystal clear authorities messaging on what the public can hope from covid vaccines. When common boosters could possibly be vital for keeping the elderly and medically frail out of the healthcare facility, he claimed, the yearly boosters prompt by the Fda and the drug businesses could not be vital for everybody.

“The intention is to maintain men and women out of the healthcare facility,” he stated. “For the vulnerable, it would be essential for vaccines to preserve up with circulating strains. But for the general populace, we by now have a vaccine that stops hospitalization.”

Other panelists reported the government needs to force exploration tougher to get much better vaccines. Pamela McGinnis, a retired formal of the National Institutes of Overall health, said she had trouble detailing to her two youthful-adult sons why they immediately obtained ill after venturing out to bars a single night only months after having their bivalent booster.

“‘Think how sick you would have gotten if you weren’t totally vaccinated’ is not a good message,” she mentioned. “I’m not guaranteed ‘You would have landed in the hospital’ resonates with recipients of the condition.”

Associates of the FDA’s advisory committee have been irked in the latest months, saying the agency didn’t existing them with all the data it experienced on the bivalent vaccine in advance of it was unveiled in September. And some critics have said the Fda should have instructed drug companies to involve only the more recent strains of the virus in the shot.

Asked about that Thursday, Jerry Weir, a senior Food and drug administration vaccine officer, mentioned his “gut feeling” was that a vaccine matched to a single omicron pressure would have done far better than the bivalent shot, which also consists of the authentic covid pressure. “But the real issue is the place we’re headed,” he claimed, “and I do not know the respond to.”

Potentially the most important presentation Thursday was from Heather Scobie, who retains tabs on covid at the Centers for Condition Command and Avoidance. She reported that less than fifty percent of Us residents 65 and more mature experienced gotten the most up-to-date booster, and that only two-thirds of that age group had gotten even a single booster.

Nonetheless proof continues to mount that it’s primarily the aged who are at really serious possibility from covid. Dying prices from the illness have declined in each and every age group other than those people more than 75 due to the fact April, in spite of the uptick in new strains. Except for the extremely old, the dying charge has hovered about 1 in 100,000 due to the fact April. Before in 2022, infants 6 months old and more youthful have been hospitalized and died at relatively significant prices. Vaccination stages in the 4-and-beneath team hover at about 10{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}.

Though acknowledging the FDA’s motivation to regularize its covid vaccine policy, panel customers claimed it is nevertheless too early to know for positive whether or not covid will surge only in the winter season, like flu, respiratory syncytial virus, and other respiratory bacterial infections.

“For the following couple of decades we may possibly not know how normally we have to have to make a strain change in the vaccine,” said Dr. Steven Pergam, professional medical director of an infection avoidance at the Seattle Cancer Treatment Alliance. Or even if individuals who are not in poor overall health or aged have to have extra boosters.

One vaccine-maker represented at the conference, Novavax, reported it would have to have to know by the stop of March which pressure to include things like in its vaccine for slide. Companies with mRNA vaccines like Pfizer and Moderna can adjust their formulation speedier, but their solutions aren’t clearly better than Novavax’s.

All three of those vaccine-makers discovered at the meeting that they are establishing one-dose vials or prefilled syringes. Up to now, they’ve shipped their vaccines in multidose vials, but considering that the governing administration has run out of revenue to acquire vaccines, individual pediatricians might get them in the long run. Because the vaccine ought to be utilised swiftly as soon as a vial is open, doctors are leery of squandering vaccine and dropping income.

KHN (Kaiser Well being Information) is a countrywide newsroom that creates in-depth journalism about well being difficulties. With each other with Policy Assessment and Polling, KHN is 1 of the 3 significant functioning systems at KFF (Kaiser Loved ones Basis). KFF is an endowed nonprofit business offering info on health and fitness concerns to the nation.

USE OUR Information

This tale can be republished for free of charge (particulars).

FDA Passes New Cannabis Guidance for Clinical Research | Beveridge & Diamond PC

Critical Takeaways

  • What Happened: The Food items and Drug Administration (Food and drug administration) finalized a 2020 draft guidance detailing the agency’s suggestions for scientific analysis for building hashish and cannabis-derived human medication.
  • Who’s Impacted: Individuals associated in the clinical study of hashish can rely on this Food and drug administration guidance for suggested sources of cannabis for medical analysis and sources for facts on high-quality and control status issues. The steerage also suggests strategies for researchers to work out the THC dissimilarities concerning “hemp” and “cannabis.” The guidance can help tell stakeholders, lawmakers, and other folks in the hashish field by addressing particular issues elevated about drugs made up of cannabis and crucial Fda regulatory principles.

History

On January 24, 2023, the Food and drug administration announced new assistance entitled “Cannabis and Hashish-Derived Compounds: Top quality Criteria for Clinical Investigation.” The non-binding guidance discusses a few critical cannabis-associated subjects:

  • Sourcing cannabis for medical analysis
  • How to estimate percent delta-9 tetrahydrocannabinol (THC) all through the study cycle and,
  • Normal high quality considerations for creating human medications that contain hashish and cannabis-derived compounds.

Typically, to be viewed as “hemp,” a merchandise have to incorporate much less than .3 p.c delta-9 THC by dry bodyweight. Anything at all earlier mentioned .3 per cent delta-9 THC is regarded as hashish (or marijuana), a Plan I controlled substance. Human medications that incorporate hemp, hashish, and hashish-derived compounds are commonly subject to the exact same authorities and demands, together with excellent expectations, as Fda-regulated drug solutions that contains any other material.

The target of FDA’s hottest steering is to assist clinical exploration for the growth of hashish and cannabis-derived human prescription drugs. The direction does not handle the progress of thoroughly artificial variations of substances that take place in cannabis and does not deal with other Food and drug administration-regulated items.

Sourcing of Cannabis

The National Institute on Drug Abuse (NIDA) Drug Offer Plan was the only legal resource for scientists to purchase cannabis for many many years. The NIDA Drug Supply Application continues to be a resource of cannabis in excess of the .3 percent delta-9 THC threshold for clinical study. In 2020, the Drug Enforcement Company (DEA) adopted new procedures to permit the registration of new companies to plant, increase, cultivate, or harvest cannabis. There was confusion, even so, over no matter whether medical studies could use these new producers. This guidance intends to make clear that confusion and presents that:

  • For hashish in excess of the .3 {bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} delta-9 THC threshold and not part of an investigational new drug (IND) software – the NIDA Drug Provide Program and other sources authorized by DEA to supply Routine I cannabis resources for research can be made use of.
  • For any cannabis resources (earlier mentioned or beneath the .3 per cent threshold) as part of an IND software- other resources can be utilised matter to the approval of the software.

When the sourcing of hashish for medical analysis has been a apparent location of problem for individuals associated in the scientific research of hashish, the Food and drug administration also presented direction on additional nuanced problems that this sector faces.

Calculation of THC

Farmers and researchers have extended been involved about the calculation of THC, provided the unpredictable nature of the plant. Uncontrollable environmental factors as properly as extraction and manufacturing processes can influence the THC concentration and press lawful hemp into a managed substance. The steering endorses that experts calculate the THC material in their proposed hashish or hashish-derived investigational drug merchandise early in the enhancement procedure to decide their product’s probable abuse legal responsibility and command standing. The direction also discusses the very best calculation approaches all over the lifecycle of medical scientific studies.

Common High-quality Things to consider

As section of an IND for any drug, scientists are envisioned to display that they can continually manufacture a quality product or service. In each stage of clinical investigation, they must post enough details to show the drug’s identity, excellent, purity, and potency. The direction includes added concepts and tips that are specially related for acquiring prescription drugs that consist of cannabis and cannabis-derived compounds:

  • Hashish and cannabis-derived compounds are held to the same regulatory benchmarks as any other botanical uncooked content, botanical drug compound, or botanical drug product. This incorporates making sure batch-to-batch consistency, conducting microbiological exams and sterility assessments, and screening for raw components (between other unique necessities on p. 6 of the guidance).

  • Top quality assessments, particular to dosage type, should be done.
  • Impurities for obviously taking place compounds should be managed.
  • Researchers ought to not count on posted literature in area of details from a total toxicology system, as the certain botanical drug product below evaluate might differ from that of the released examine.
  • Evaluate the metabolic profile of big cannabinoids in human beings early for security.

Impacts

This Fda guidance allows presents clarity to the cannabis marketplace on hashish and hashish-derived drug progress in the wake of Congress passing the Healthcare Marijuana and Cannabidiol Analysis Expansion Act. Stakeholders have been eagerly awaiting updates from the Fda and other federal businesses with regards to the sale and promoting of cannabis-derived merchandise as effectively as a scientific assessment of cannabis to aid reevaluate the substance’s plan under the Controlled Substances Act. As a high precedence of the Biden Administration, we will most likely see numerous important regulatory updates for cannabis in 2023.

Businesses can submit on the web or published comments on this steerage at any time. The tips in this steering are not required or binding – researchers may possibly use an different strategy as extensive as it satisfies the necessities of the relevant statutes and polices.

[View source.]

The Power Of Ordinary English To Improve Healthcare

For non-medical professionals, professional medical terminology can be frustratingly opaque. Just one of my good friends is a extremely-educated personal computer specialist who knows multiple programming languages, but he has also advised me, “I really don’t converse ‘Doctor’.” When doctors talk with clients utilizing cryptic health care jargon, clients can very easily misunderstand the supposed indicating.

Drugs is 1 of the several fields where by “negative” usually signifies a thing fantastic, while “positive” indicates anything undesirable. A latest analyze by Dr. Rachel Gottleib and colleagues in JAMA Network Open up showed how usually patients “misunderstood and often assigned which means opposite to what the clinician meant.” In distinct, they examined jargon that may well have a person indicating in standard speech, but a various meaning in healthcare discussions.

Some of their unique findings ended up interesting. For illustration, most non-physicians (96{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}) understood that a unfavorable most cancers screening consequence intended that they did not have most cancers. However, “fewer respondents knew that ‘your tumor is progressing’ was undesirable news” (79{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}) or that “positive nodes meant their most cancers experienced spread” (67{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f}).

For radiology terminology, some misunderstandings have been even worse. 80{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} of patients understood that an “unremarkable” upper body x-ray was fantastic news. But only 21{bf0515afdcaddba073662ceb89fbb62b6b1bf123143c0e06b788e1946e8c353f} understood that a upper body x-ray described as “impressive” was bad news.

Equivalent misunderstandings happened with the time period “occult”: “More individuals considered that the phrase ‘had an occult infection’ had one thing to do with a curse than recognized that this intended that they experienced a hidden an infection.”

Dr. Gottleib and colleagues observe that a significant resource of the challenge is that doctors frequently do not know they are making use of terminology that can be very easily misinterpreted by non-physicians — a phenomenon recognised as “jargon oblivion.” A person of their paper’s vital take-residence details for physicians is that “by greater being familiar with what healthcare conditions and phrases individuals do or do not understand, we can grow our jargon identification toolkit and eventually strengthen our interaction with individuals.”

Following the theme of improving upon communications involving doctors and sufferers, I was inspired to learn of a analyze by Dr. Shanmukha Srinivas and colleagues in the American Journal of Roentgenology executed jointly at UC San Diego and at Stanford College, finding out how to make improvements to patient knowledge of health care procedures by working with “Patient Final decision Aids” (PDAs) thoroughly crafted in common English. These PDAs were established by the non-gain academic firm, The Interventional Initiative fascinated viewers can perspective on line versions here.

Dr. Srinivas and colleagues researched the outcome of supplying patients about to go through invasive interventional radiology methods specific two-site brochures written at the “sixth- to eighth-quality health and fitness literacy level” describing the regular advantages, challenges, and possibilities to the method, prior to owning the regular informed consent meeting with their doctor. The interventional radiologists doing the strategies have been blinded as to which people did (or did not) acquire the educational brochures beforehand the physicians expended the same sum of time with the patients speaking about the process and getting consent.

Curiously, the researchers identified that “patients who acquired a PDA prior to the take a look at noted appreciably better understanding of the process and its added benefits, pitfalls, and alternatives and were significantly extra probable to sense that the clinician listened to them and answered all inquiries.” In addition, the use of the PDA did not sluggish down the workflow and essential no “additional time or work by the clinicians accomplishing the consent discussions.”

Dr. Srinivas and colleagues mentioned that the key was effectively-vetted educational content aimed at the “sixth- to eighth-grade well being literacy stage.” Regretably, they notice that most hospitals and healthcare centers typically present educational substance to people “written over the necessarily mean reading level, with readability scores that ended up assessed as fairly difficult or complicated.”

One particular of my clinical college professors employed to emphasize that communications takes place only when the receiver has recognized the intended information, not when the sender has transmitted the message. A medical professional can use a thousand superbly eloquent phrases to describe a technique or a test consequence. But if the affected person does not grasp the intended that means, then no conversation has in fact happened! The function of Dr. Gottleib, Dr. Srinivas, and their associates has proven how working towards doctors can a lot more reliably communicate with their patients.

Of class, communications is a two-way avenue. Whenever clients can additional precisely connect their signs and problems to their doctors, both of those will reward. Physicians are qualified to question issues to elicit insightful answers from clients. But sufferers can help if they learn standard strategies of describing indicators that will enable their doctor to far more immediately slender down the opportunities that could be leading to their problems.

For illustration, Anne Asher, CPT, has created a awesome tutorial for patients on how ideal to describe again agony to their doctors. Her report offers ideas on how individuals can explain many aspects of agony, which includes the intensity, place, timing, and excellent of their ache. Phrases that describe timing could possibly include things like “constant, intermittent, at evening only, and many others.” Terms that that explain soreness high quality may possibly include “flickering”, “sharp”, “dull”, “shooting”, and so on. (Much more illustrations can be observed at the McGill Pain Questionnaire.)

Clients can also explain their signs in terms of how it affects their every day lifestyle routines — e.g., “I can no for a longer time achieve down to put my footwear on my toes for the reason that my again hurts as well a lot when I bend that way.”

Once again, sufferers do not necessarily have to have to know all the nuances of clinical agony vocabulary. But to the extent they can use their possess text to describe their inner encounters, they and their physicians can a lot more fruitfully get the job done collectively to arrive at an exact diagnosis and an efficient treatment strategy.

I am a radiologist who specializes in decoding MRI and CT scans. But I also recognize that the most productive tool for high-quality individual treatment is good communication concerning clients and medical practitioners. A several well-selected terms can be truly worth a thousand large-tech photographs. The English language is a fantastic communications medium, and the skillful use of everyday language can be a potent tool to help both clients and doctors alike.